Understanding the Core Difference
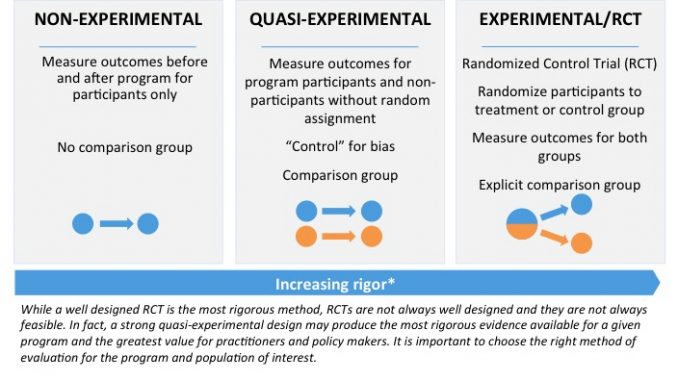
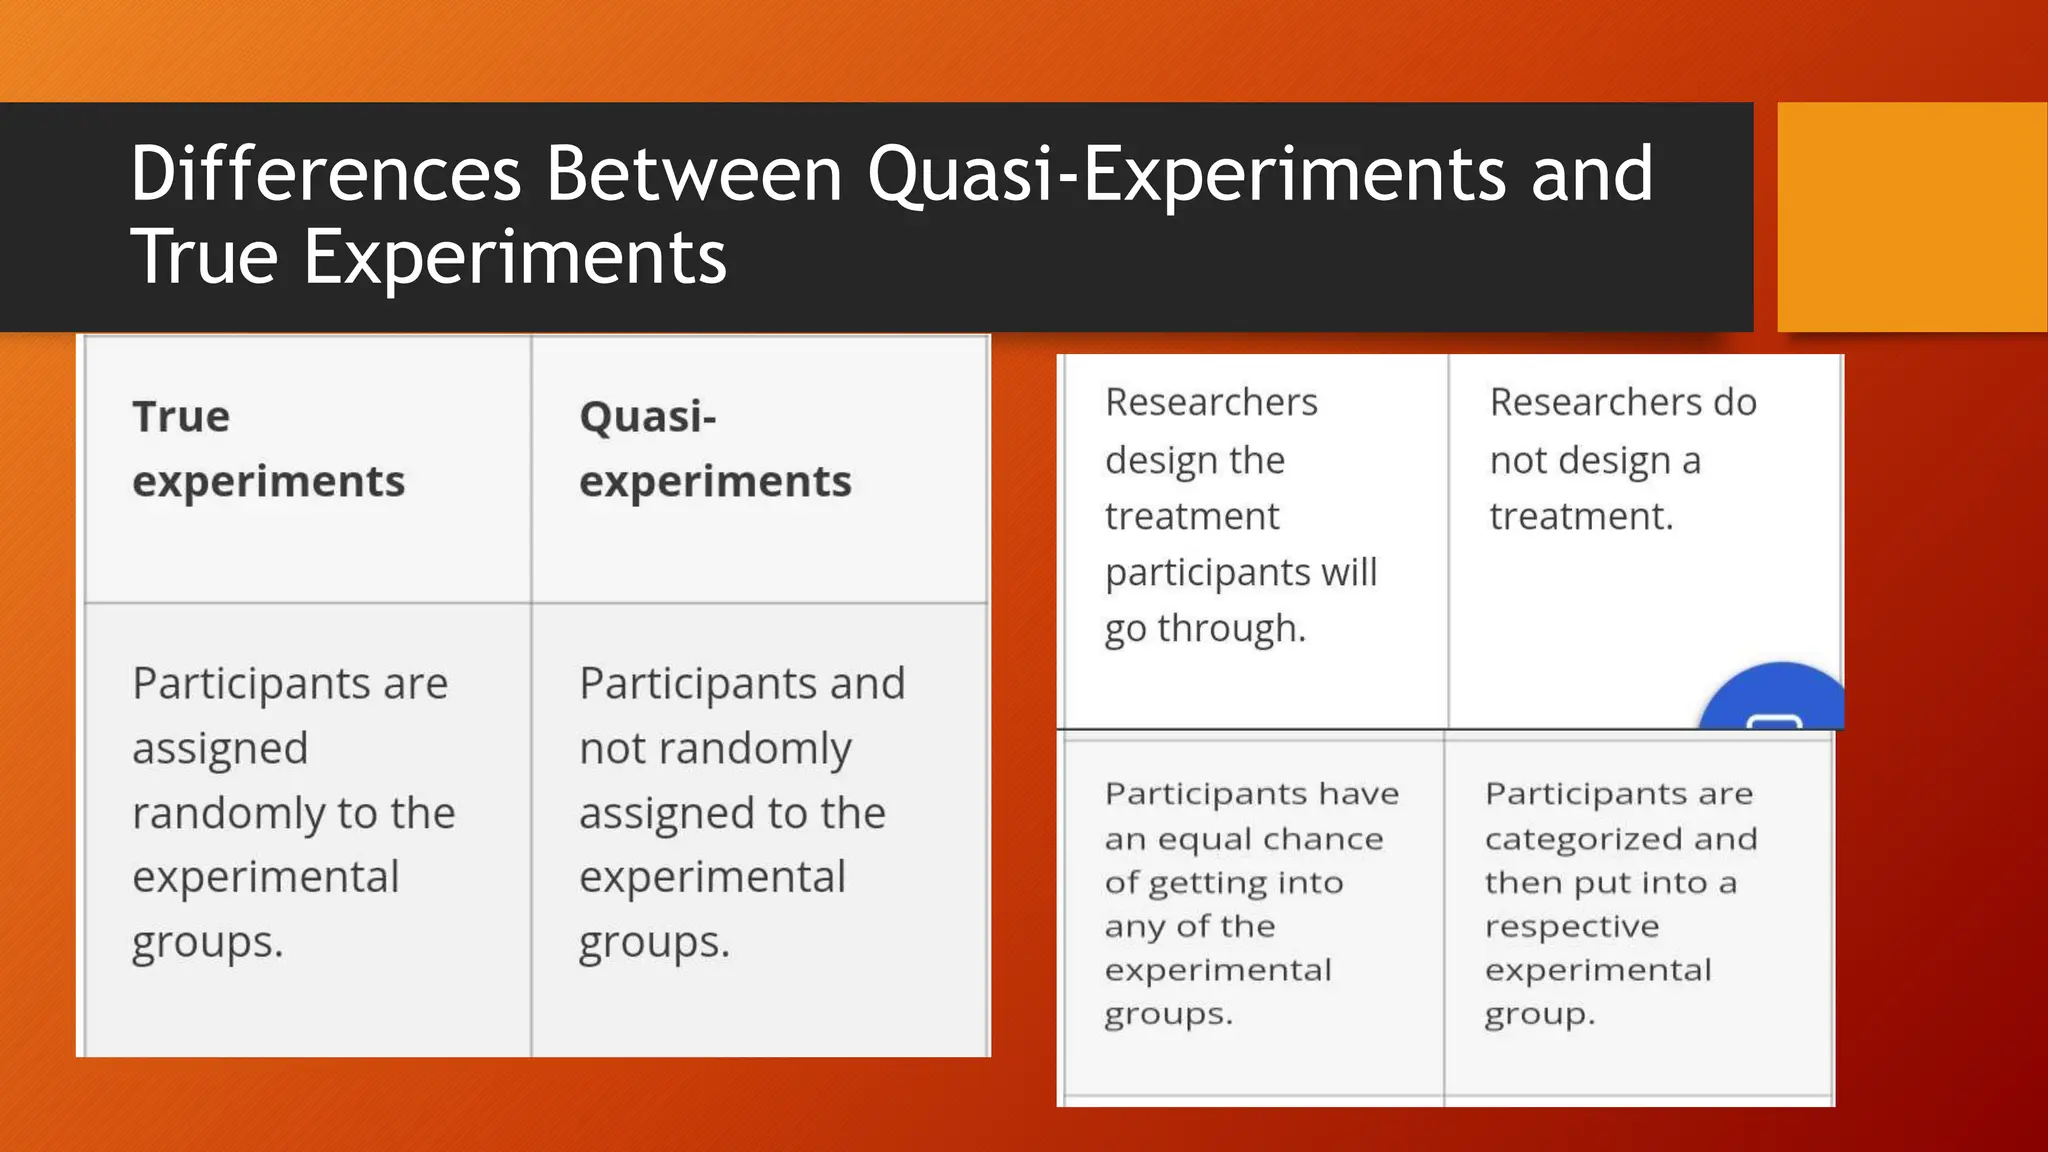
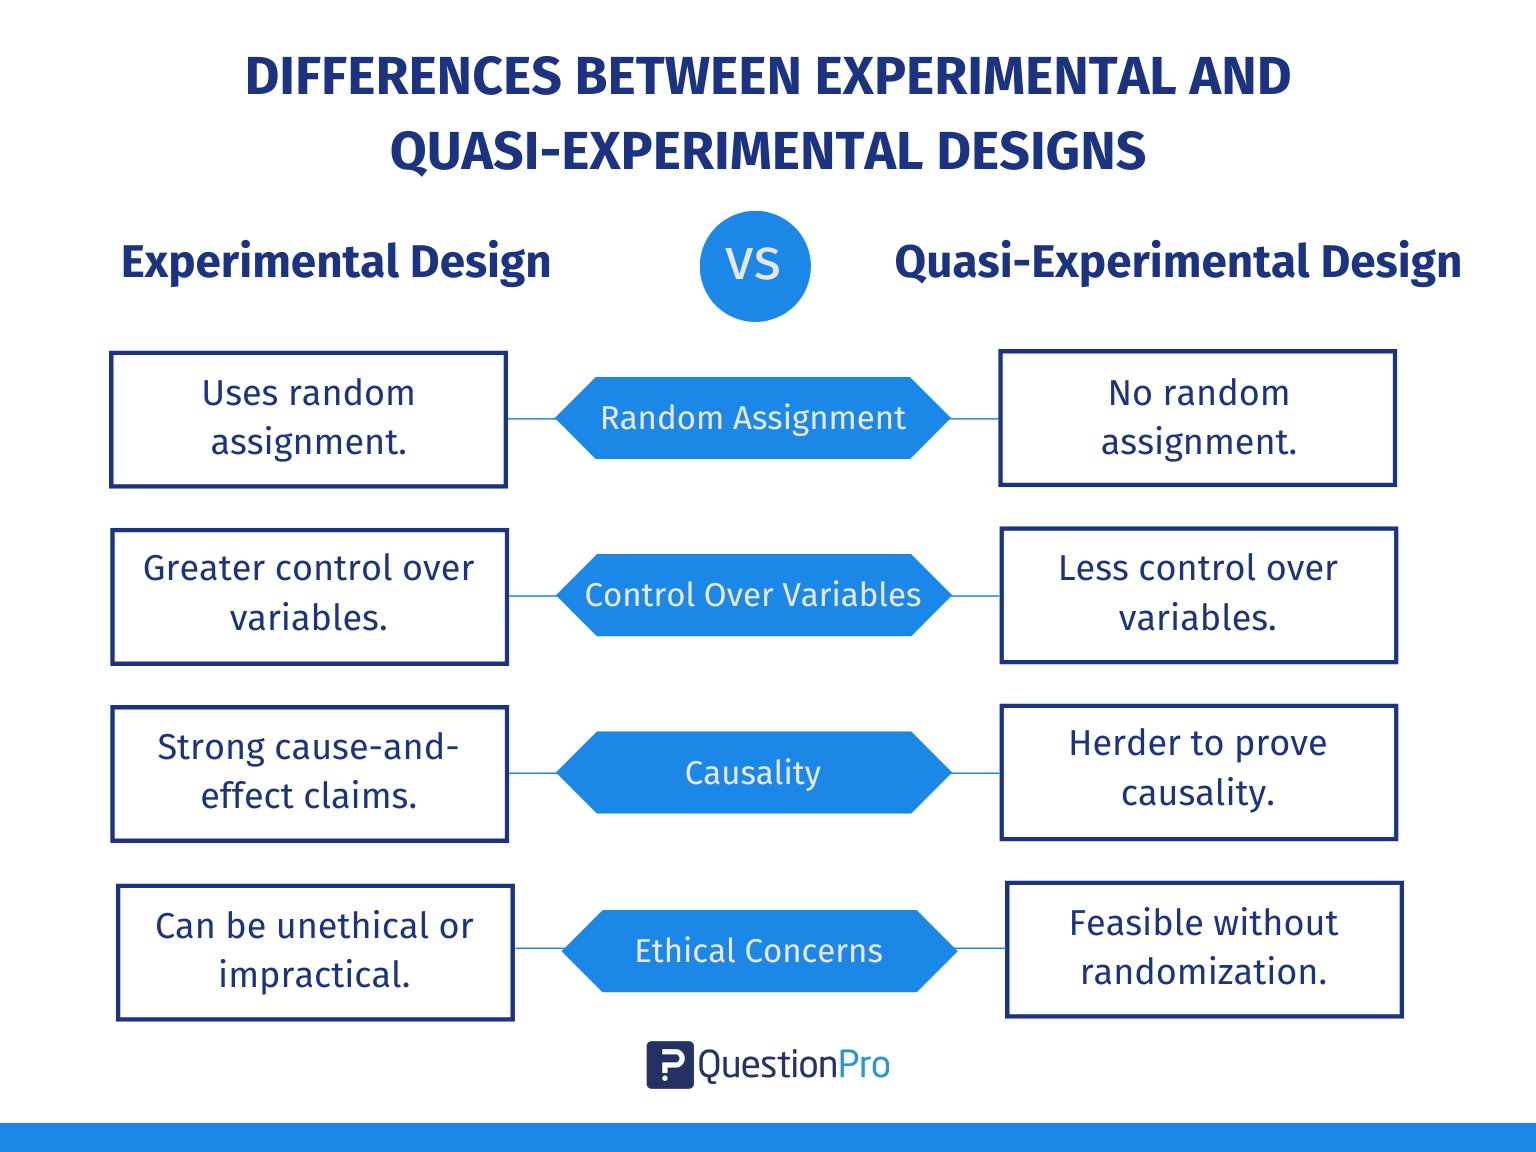
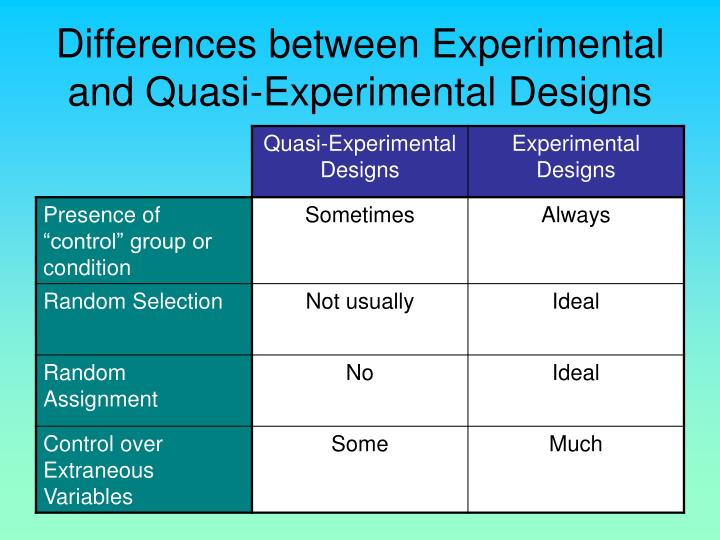
Experimental and quasi-experimental designs both try to establish causality, but they diverge sharply on one question: who controls the assignment of participants to conditions. In a true experiment, you or your protocol decide who gets the treatment and who doesn't. That random assignment is the engine that makes causal claims possible. In a quasi-experiment, that control is gone. Participants end up in groups because of pre-existing circumstances—policy changes, geographic boundaries, eligibility cutoffs, or administrative decisions you didn't make. I've spent years running programs where randomization was either politically impossible or ethically off the table. You learn pretty quickly that quasi-experimental design isn't a compromised experiment. It's its own category with its own rules, its own threats to validity, and its own acceptable standards of evidence.
Quasi Experimental Vs Experimental: What Actually Changes
When random assignment works, selection bias gets shuffled out. That's why the internal validity bar is higher for experiments. But quasi-experiments aren't dead ends. They just require you to do more upfront work to prove that your comparison groups are actually comparable before the treatment happens. Start by identifying a clear intervention and a natural source of variation in how it gets applied. The intervention might be a new curriculum rolled out to certain schools, a policy change affecting specific zip codes, or a hospital adopting a protocol in March while the rest of the region waits until June. Once you've identified that variation, pick a design strategy. The most common approaches are difference-in-differences, regression discontinuity, propensity score matching, and interrupted time series. Each has different data requirements and different assumptions you need to defend.
Difference-in-Differences
This design compares the pre-to-post change in your treatment group against the pre-to-post change in a control group. The key assumption is parallel trends—that in the absence of treatment, the two groups would have moved the same direction. You test this by looking at pre-treatment periods. If the groups were already diverging before the intervention, your design is compromised. I once ran a DiD study on a workforce training program where the treated counties happened to be growing faster economically than the control counties even before the program started. The parallel trends assumption was clearly violated. What saved it was adding county-level economic controls and using a synthetic control variant instead. That adjustment shifted the estimated effect from a modest positive to essentially zero. I reported that. It was the honest result.
Get the Full Details
Regression Discontinuity
RD designs exploit a cutoff rule. Students scoring below 50 get tutoring. Income under a threshold qualifies for benefits. Age 65 triggers Medicare eligibility. People just above and just below that line are nearly identical in every way except they received (or didn't receive) the treatment. That near-identical quality is what gives RD its experimental-level credibility. The main practical challenge is bandwidth selection. Too wide and you're comparing fundamentally different people. Too narrow and you lose statistical power. I usually run the analysis across several bandwidths and report the full range. Readers can see whether the estimate is stable or collapsing at the edges.
Propensity Score Matching
When you can't use an existing cutoff or don't have pre-treatment periods, propensity score matching is the fallback. You model the probability of receiving treatment based on observed covariates, then pair each treated unit with one or more untreated units that have similar scores. The critical weakness here is that matching only balances what you measured. If there's an unobserved factor driving both treatment assignment and the outcome—something like motivation or family support—your estimate is still biased. I always run a sensitivity analysis after matching to show how strong an unmeasured confounder would need to be to wipe out the result. It's a small addition that adds real credibility.
How to Run a True Experiment
Randomized controlled trials remain the gold standard when feasible. The mechanics are straightforward: define your population, randomize units to treatment and control, deliver the intervention, measure outcomes, and analyze the difference. The randomization does the heavy lifting that quasi-experiments have to approximate through statistical techniques. The constraints are usually practical rather than theoretical. Sample size requirements, implementation fidelity, attrition, and the cost of compliance monitoring are the real friction points. A trial that looks clean on paper often falls apart because participants in the control group find ways to access the intervention anyway. That contamination shrinks your measured effect toward zero.
Common Pitfalls Across Both Designs
Publication bias hits quasi-experimental work harder than experiments because null findings from DiD or matching studies get less traction. This skews the literature toward optimistic estimates. Be honest about your results and you'll build more trust than someone who quietly pushes a marginally significant finding. Another issue is overconfidence in your identification strategy. reviewers and readers will poke at your assumptions whether you ask them to or not. Address the weakest one yourself first. It's better to say "here's my biggest threat and here's why I think it's manageable" than to wait for someone else to find it.
When to Choose Which Approach
Use a randomized experiment when you have the resources, the timeline, and the authority to assign treatment. Use a quasi-experiment when randomization is impossible but you have credible sources of exogenous variation to lean on. Neither option produces perfect evidence. The goal is always the same: produce the most defensible estimate you can given the constraints you're working under. If your question matters enough to answer, the design choice matters too. Pick the strongest approach your situation allows and be transparent about its limitations. That's the standard that actually holds up over time.