A Quick Look At The Nuchal Translucency Scan
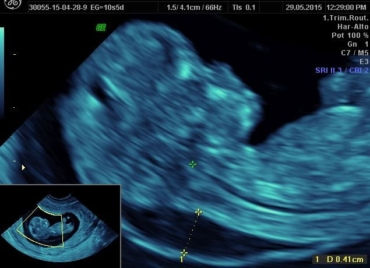
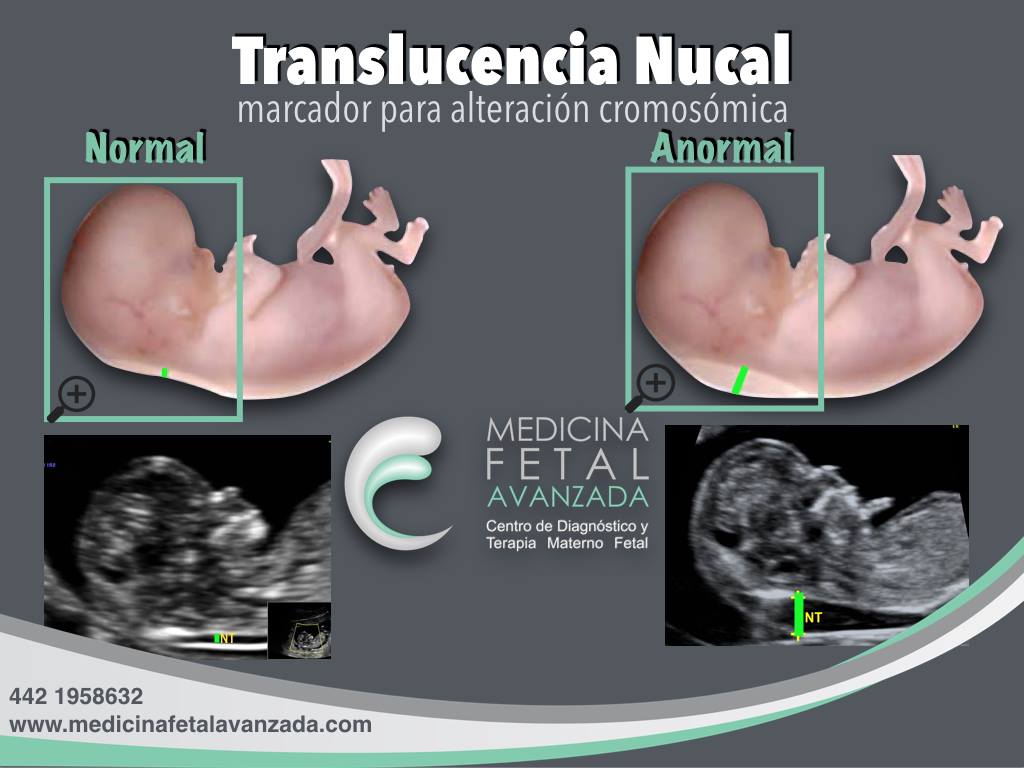
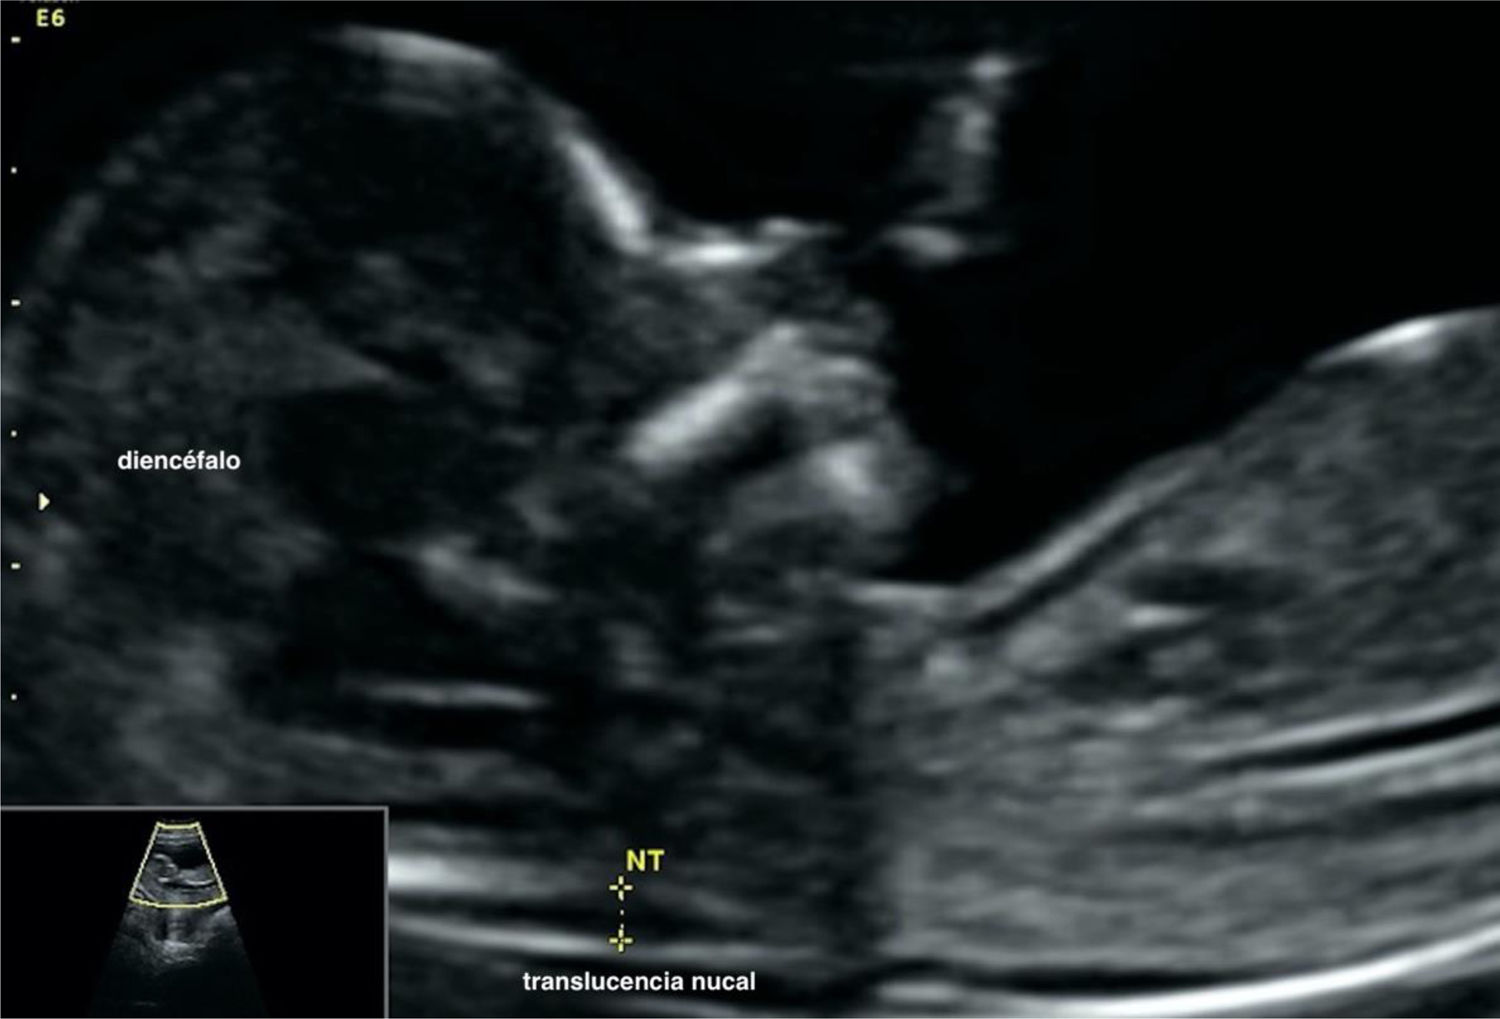
The nuchal translucency exam is a first-trimester ultrasound that measures the fluid space at the back of a developing fetus's neck. It's typically done between 11 and 14 weeks of gestation. The measurement, taken in millimeters, helps assess the risk of certain chromosomal conditions, including Down syndrome and Trisomy 18. It's a screening tool, not a diagnostic one, which is an important distinction that gets lost on a lot of people. How it works is straightforward enough. A trained sonographer uses a high-frequency transducer, usually placed on the mother's abdomen, to get a magnified view of the fetus in a precise sagittal plane. They look for the clear, dark (anechoic) space between the skin line and the soft tissue overlying the cervical spine. That space gets traced and measured. A thicker measurement generally correlates with higher risk, but the actual interpretation depends heavily on gestational age, crown-rump length, maternal weight, and whether it's a singleton or multiple pregnancy. I remember dealing with a case where the fetal position made the sagittal view nearly impossible to capture cleanly. The baby was hunched forward, and the neck region wasn't extending properly. Standard protocol says you should attempt measurement only when the head is in a neutral position — not flexed or extended. In that situation, waiting about 20 minutes and asking the patient to change position or have a light snack usually helps the fetus shift. I've also seen situations where maternal obesity degraded image quality to the point where a reliable measurement just wasn't feasible. In those cases, referring for cell-free DNA screening or scheduling a later scan are the realistic options.
The measurement technique matters more than most people realize. The image needs to be magnified so that the fetus fills at least 75 percent of the screen. The calipers must be placed from the inner edge of the skull bone to the inner edge of the skin — not the outer edges, which is a common error that inflates the reading. You also want to make sure you're seeing the distinct membranes clearly. If the nuchal area shows a septated appearance, that's likely a nuchal cystic hygroma rather than simple translucency, and the clinical implications are different. One counter-intuitive thing about this exam: a normal nuchal translucency measurement doesn't completely rule out chromosomal abnormalities. Studies show it detects roughly 70 to 80 percent of Down syndrome cases at a 5 percent false-positive rate. That means a meaningful number of affected pregnancies will still fall within the normal range. Combining it with first-trimester serum markers — PAPP-A and free beta-hCG — typically raises the detection rate to around 85 to 90 percent. That combination is what most guidelines now recommend rather than relying on the ultrasound finding alone. Another nuance worth noting is that the measurement has a wide normal range that changes rapidly with each week of gestation. At 11 weeks, anything under 2.2 mm is generally considered within normal limits. By 14 weeks, that threshold shifts slightly. A value that looks borderline at 11 weeks and 5 days might be completely unremarkable at 12 weeks and 2 days. Getting the crown-rump length right is essential because it anchors the gestational age, and even a small error there can push a normal result into the abnormal range depending on how the lab's software calculates the multiple of the median.
The main limitation here is operator dependency. This isn't a test you can reliably automate or outsource to a low-resolution machine. The quality of the measurement depends entirely on the skill and experience of the person performing the scan. Accreditation standards exist for exactly this reason — clinics without proper NT certification tend to produce more variable and less reliable results. There's also the issue of inter-observer variability. Two different sonographers measuring the same image can sometimes arrive at slightly different readings, especially when the boundaries are faint or the image quality is suboptimal. If the nuchal translucency comes back elevated, the next step isn't panic. It's usually genetic counseling followed by either diagnostic testing like CVS or amniocentesis, or expanded cell-free DNA screening if the patient hasn't already had that. The exact pathway depends on how elevated the measurement is, the patient's age, other ultrasound findings, and personal preferences around invasive testing. Results are typically reported as a MoM value or as a risk ratio combined with maternal age and serum markers. A risk of 1 in 250 or higher for trisomy 21 is commonly used as the cutoff for offering further diagnostic testing, though individual clinics may set their own thresholds. Understanding exactly which cutoff your provider uses and what it means for your specific situation is worth asking about directly.
Get the Full Details
I've also seen cases where a prominent nuchal translucency turned out to be associated with cardiac anomalies rather than a chromosomal issue. Follow-up fetal echocardiography around 18 to 22 weeks is often recommended in those scenarios, since increased NT can be an early soft marker for structural heart defects even when the karyotype is normal.