The Physical Exam: What It Actually Is and Why Most People Get It Wrong
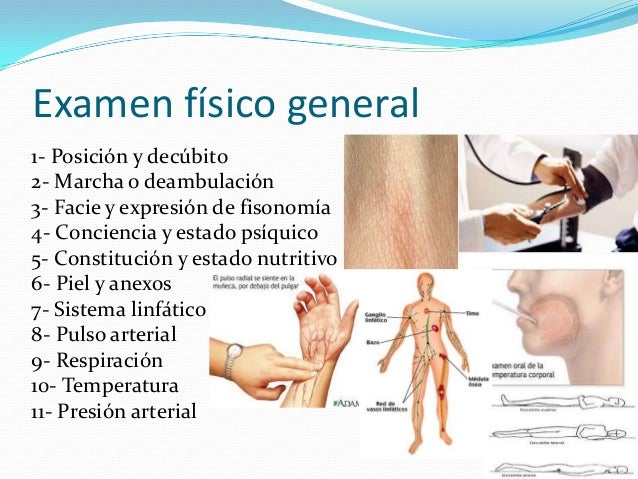
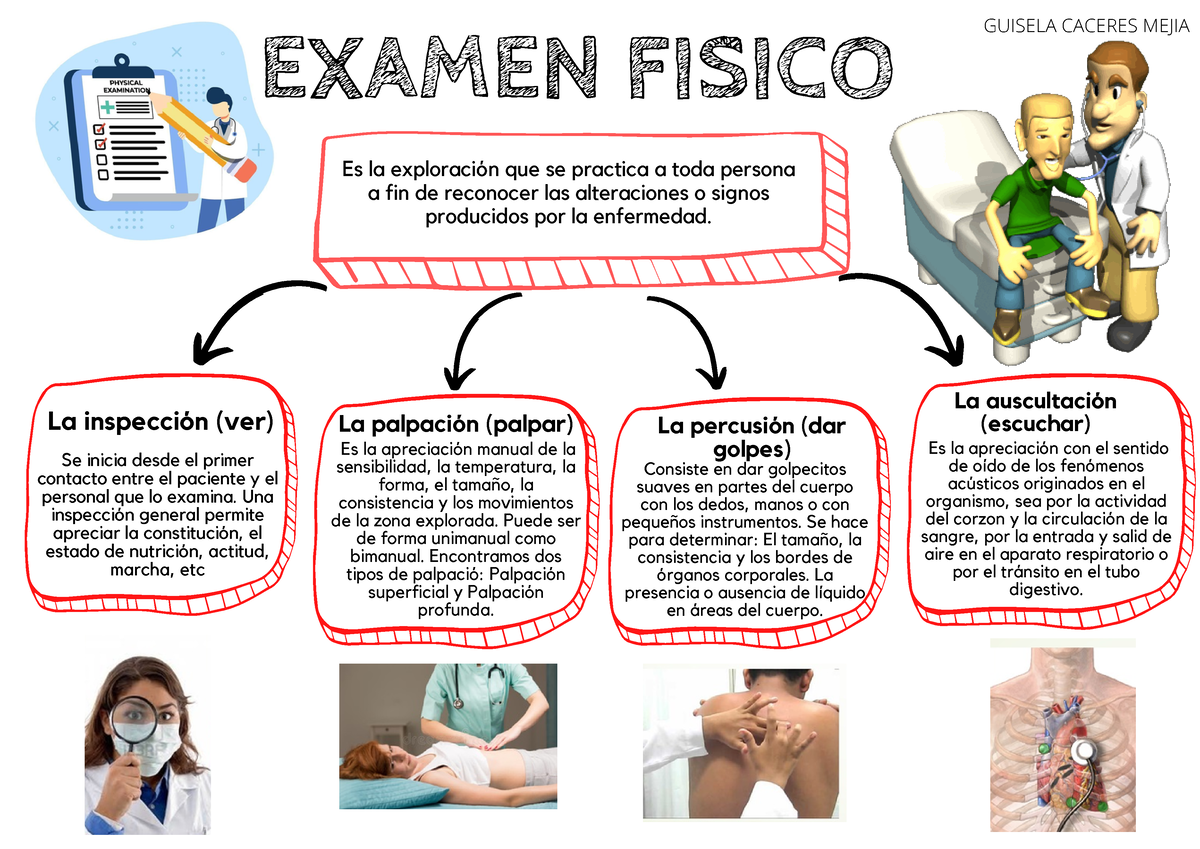
A physical examination is the systematic assessment of a patient's body using inspection, palpation, percussion, and auscultation. It's not a ritual. It's a data-gathering process that often precedes any lab work or imaging. In many clinical settings, it's still the single most efficient diagnostic tool available. You don't need a $40,000 MRI machine to detect ascites, a thyroid nodule, or early signs of heart failure. You need a quiet room, your hands, and a brain that knows what normal looks like. The term Que Es El Examen Fisico comes up frequently in Spanish-speaking medical contexts, and it refers to the same core practice: a structured clinical evaluation of vital signs, organ systems, and functional status. The approach hasn't changed much in forty years. What has changed is how hurried people get through it.
How I actually perform it in a busy clinic
I start with vitals, but I don't just run through the checklist and move on. I look at the patient while I'm taking their blood pressure. If someone is in obvious respiratory distress, I'm not going to spend two minutes finding a vein before I address the breathing. Sequence matters. I've seen residents waste ten minutes searching for a radial pulse on a hypotensive patient when a carotid check would have taken three seconds and given them the same answer. The order I use is: general appearance, vital signs, cardiac, pulmonary, abdominal, neurologic, and then targeted systems based on the chief complaint. I do not perform a complete head-to-toe exam on every patient who walks in with a ankle sprain. That wastes everyone's time and often leads to missing the real pathology because you're skimming through systems that have nothing to do with the problem. I once spent twelve minutes examining a 24-year-old's lungs and heart before a attending asked me why I was doing that. The patient came in for abdominal pain. The answer was cholecystitis. I hadn't palpated the abdomen yet because I was too busy listening to clear lungs.
Counter-intuitive things most people miss
First, inspection is the most underutilized step. You can diagnose jaundice, anemia, clubbing, goiter, and severe malnutrition before you touch the patient. Most clinicians rush past the first thirty seconds and jump straight to palpation. They miss half the findings sitting right in front of them. Second, the absence of a positive finding is itself data. If you percuss and find no shift in dullness across the abdomen, that doesn't mean you "ruled out ascites" definitively — it means you found no evidence of clinically significant ascites. A bedside ultrasound would pick up 200ml of fluid that percussion misses entirely. These are two different conclusions. Students tend to treat negative exam findings as proof of absence rather than proof of non-detection. Third, normal lung sounds don't mean normal lungs. By the time a person has diffuse wheezing or crackles audible with a stethoscope, the underlying pathology is usually moderate to severe. A patient with early pneumonia can have perfectly clear breath sounds anteriorly. I had a patient in 2019 who presented with a low-grade fever and mild tachypnea. Her lung exam was essentially unremarkable. I ordered a chest X-ray anyway. It showed a segmental consolidation in the right lower lobe. She would have been sent home if I had stopped at the exam.
Get the Full Details

Specific pitfalls and how to avoid them
Palpating the liver is one of the most commonly done and most poorly interpreted maneuvers. The rule is simple: you're feeling for the edge, not the surface. Many practitioners press too hard and push the liver edge away from their fingers, creating a false negative. Or they palpate during full expiration when the liver has already retracted upward. Always ask the patient to take a slow, deep breath in. Your fingers should be light, just below the costal margin, and you're waiting for the edge to meet your fingertips. If you can't find it on the right, check the left side too — a palpable spleen edge changes the entire differential. Cardiac auscultation has the same problem in reverse. People hear murmurs and immediately classify them. But many murmurs are innocent, especially in young patients. A grade 2/6 systolic murmur at the left upper sternal border in an asymptomatic 20-year-old is almost certainly still flow-related. The red flags are diastolic murmurs, murmurs that radiate to the carotids, associated S3 or S4 gallops, and any murmur accompanied by symptoms like syncope or exertional dyspnea. If you hear a murmur and you're unsure, don't call it benign and move on. Document the grade, location, radiation, and timing accurately. Let the next clinician decide if it matters.
When the physical exam fails you
It fails when you stop thinking and start mechanically going through motions. It fails when the patient's body habitus makes certain maneuvers impossible — obese patients, patients with extensive scar tissue, those who cannot tolerate positioning. It fails when you're tired and your findings are just what you expected to find rather than what you actually found. I've caught myself documenting "lungs clear to auscultation" on a patient who later turned out to have a pulmonary embolism. The exam was technically correct — breath sounds were clear — but the diagnosis requires a CT or V/Q scan because PE doesn't typically present with abnormal lung exam findings in the early stages. That's not a failure of the exam. That's a failure of my own reasoning when I let a normal exam give me false reassurance. The workaround I use now is to maintain a running differential throughout the entire exam instead of collecting data first and interpreting it afterward. I form hypotheses as I go. Clear lungs, but is the heart rate elevated out of proportion? Asymmetric leg swelling, but is there tenderness along the superficial veins or is the whole calf involved? These questions stay active in my head the entire time and they prevent the mechanical checkbox mentality that leads to missed diagnoses.
Tools that complement rather than replace
A stethoscope, a penlight, a reflex hammer, and a thermometer are the complete kit for most ambulatory settings. An otticoscope adds ear and throat evaluation. A tape measure for midline distances and testicular volume. That's it. Point-of-care ultrasound is increasingly standard but it is an extension of the exam, not a substitute for it. You can miss an abdominal aortic aneurysm on ultrasound if you haven't first palpated the aorta and noted its caliber and pulse character. The hands tell you where to point the probe.