How to Actually Use PANSS in Clinical Practice
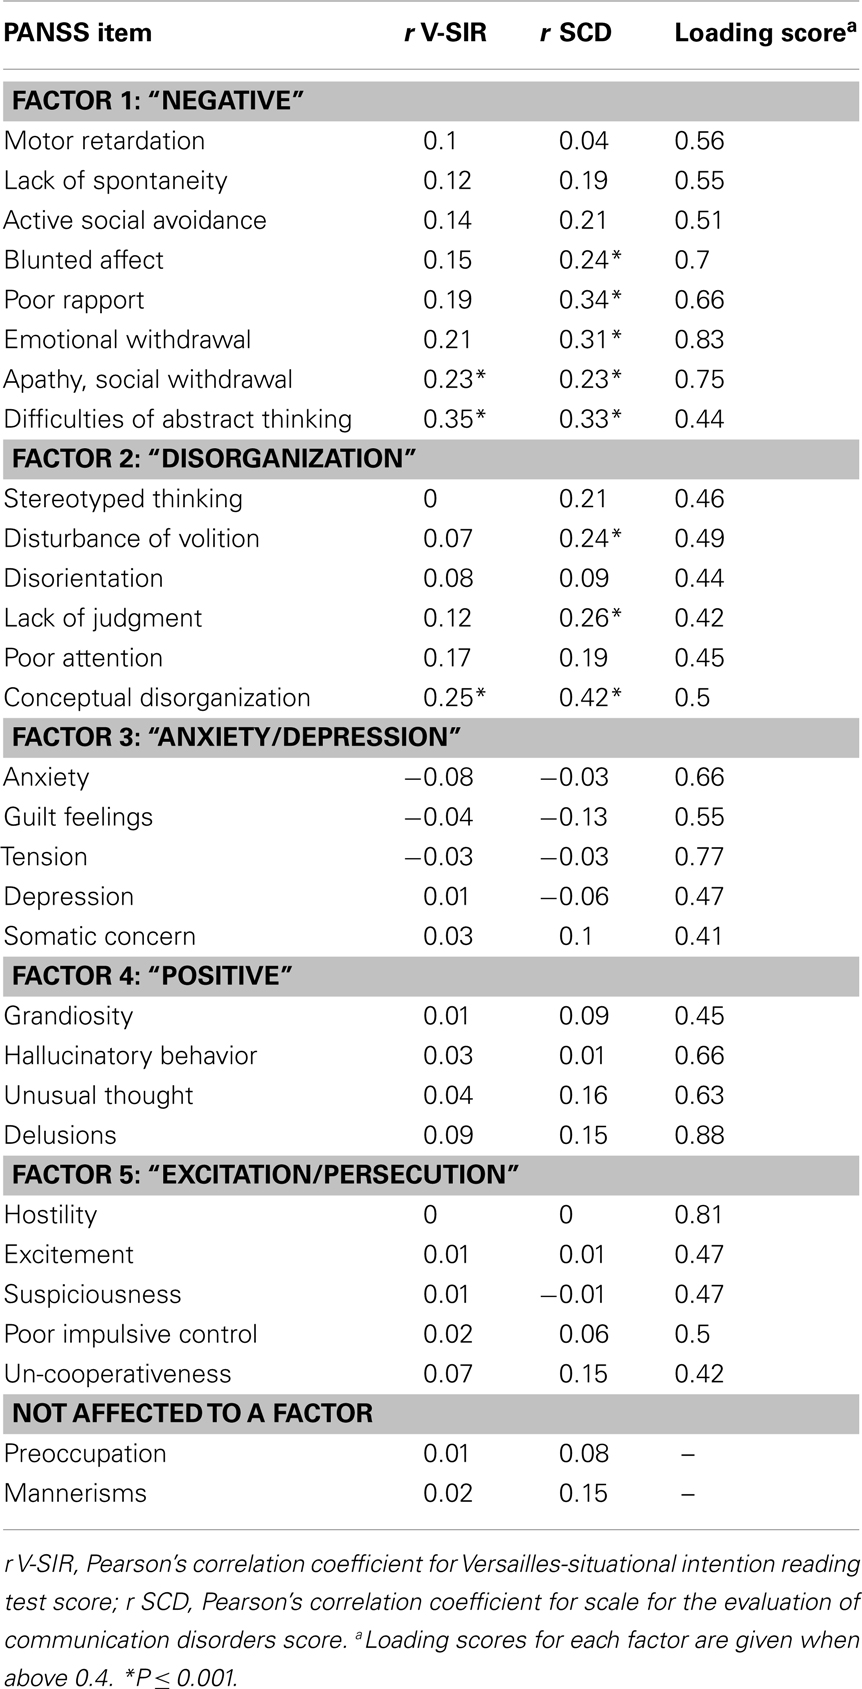
The PANSS, or Positive and Negative Syndrome Scale, is a 30-item clinician-rated instrument used primarily in schizophrenia research and clinical settings. It covers positive symptoms, negative symptoms, and general psychopathology. Each item is scored on a 1-to-7 scale. That part everyone knows. What nobody tells you until they've wasted a dozen assessment hours is how fiddly the actual administration is. Before you open the form, you need good source material. You're not just reading a patient's responses off a clipboard. You're cross-referencing information from clinical interview, collateral history, and behavioral observation. The official PANSS manual insists on at least two sources of information for each rating. I learned that the hard way during my second year when I rated a patient purely from a brief interview and scored them 15 points lower on negative symptoms than a colleague who'd spent 40 minutes with the same person watching them in the common room. The discrepancy wasn't subtle. Here's the structure you're working with:
- Positive scale (7 items): P1 delusions, P2 conceptual disorganization, P3 hallucinations, P4 excitement, P5 grandiosity, P6 suspiciousness, P7 hostility
- Negative scale (7 items): N1 blunted affect, N2 emotional withdrawal, N3 poor rapport, N4 avolition, N5 abstraction difficulty, N6 anhedonia, N7 apathy
- General psychopathology scale (16 items): G1 somatic concern, G2 anxiety, G3 guilt feelings, G4 tension, G5 mood depression, G6 moral concern, G7 social withdrawal, G8 deterioration of abstraction, G9 uncooperativeness, G10 imagination loss, G11 stereotyped thinking, G12 tension, G13 motor retardation, G14 emotional response, G15 pathos (mannerisms/posturing), G16 dysphoria
The scoring range is 30 to 210. Total scores above 100 are generally considered clinically elevated. But raw totals are almost useless on their own without looking at the subscale breakdown. You start with the positive scale items. These tend to be the most observable in an acute setting. Delusions and hallucinations come up naturally during structured interview if you know how to ask. The trick with P2 (conceptual disorganization) is that patients will often just be disorganized in their speech, so you have to distinguish between what they're actually saying and how they're saying it. I rate this based on coherence of content rather than fluency of speech, which catches people out because fluent speech can still be profoundly disorganized in meaning. The negative scale is where most assessments fall apart. Things like blunted affect and emotional withdrawal require you to watch a patient across multiple contexts, not just answer one interview question. A patient might make eye contact and respond appropriately during a structured conversation but then sit completely still and mute for the next hour. You have to capture both behaviors and weight them fairly. I keep a mental note throughout the assessment rather than trying to fill in ratings retrospectively. The retrospective approach always skews higher toward whatever you got at the end of the session.
For the general psychopathology items, you need to be careful about symptom overlap. G5 (mood depression) and G2 (anxiety) frequently co-occur with negative symptoms, and it's easy to double-count. The manual has notes on this but they're easy to gloss over when you're tired, which is always.
Get the Full Details

Scoring and Interpretation
Once you've rated all 30 items, you sum the three subscales. The most common error I see is people adding the positive and negative totals and forgetting to include the general scale in the overall picture. A patient can present with a deceptively low positive scale score but severe negative and general symptoms, which changes treatment decisions entirely. The general scale alone ranges from 16 to 112 and often gets treated as the catch-all, which it isn't. Reliability depends heavily on rater training. Studies show that inter-rater reliability on the PANSS typically falls in the 0.70 to 0.85 range for trained raters, which is decent but not exceptional. Untrained raters drop significantly lower, especially on the negative subscale where clinical judgment matters most. If you're using this in a research context, you need formal reliability certification, not just having read the manual once. There's also the modified PANSS (MNS) and the short PANSS (SPANSS) variants if you're looking for something faster for routine clinical use. The full version takes about 45 minutes to an hour with a cooperative patient. With an acutely psychotic patient, it can run much longer or need to be split across sessions.
Where PANSS Falls Short
The scale was developed in the late 1980s and it shows. It doesn't capture cognitive symptoms well, which modern treatment guidelines consider central to schizophrenia management. It also underweights disorder-related quality of life and functional outcomes. If you're only tracking PANSS scores, you're missing a big chunk of what matters to patients. I supplement it with the GAF or WHODAS when I need a fuller picture. Another issue is cultural bias in item interpretation. Somatic concern and moral concern items map poorly onto experiences in non-Western contexts. I had a patient from a different cultural background who scored very high on G6 (moral concern) and G3 (guilt feelings) purely because of religious framing of their delusional content. Once I understood the cultural context, those ratings dropped to appropriate levels. The scale doesn't account for that automatically. For download links to the official PANSS instruments, you'd go through the multi-Health Systems (MHS) website or the original authors' affiliated institutions. The scale is copyrighted, so free PDFs floating around the internet are usually unofficial reproductions that may have formatting errors. Don't use those for actual clinical work.
Practical Notes
If you're administering this regularly, invest in a rating book or a digital version with built-in cross-checks. I once caught myself accidentally scoring the same symptom twice because the paper form laid out P2 and G8 both under disorganization themes and I'd confused which item I'd already rated. Digital scoring tools that flag potential double-counting have cut my correction rate down considerably. The PANSS remains the most widely used positive-negative symptom scale in psychiatry for good reason. It's thorough and well-validated. It's also not a questionnaire you complete in five minutes and move on from. Treat it like what it is: a structured clinical assessment tool that requires time, multiple information sources, and genuine engagement with the patient's presentation across the duration of the interview.