
Understanding the Female Reproductive System: What Actually Matters
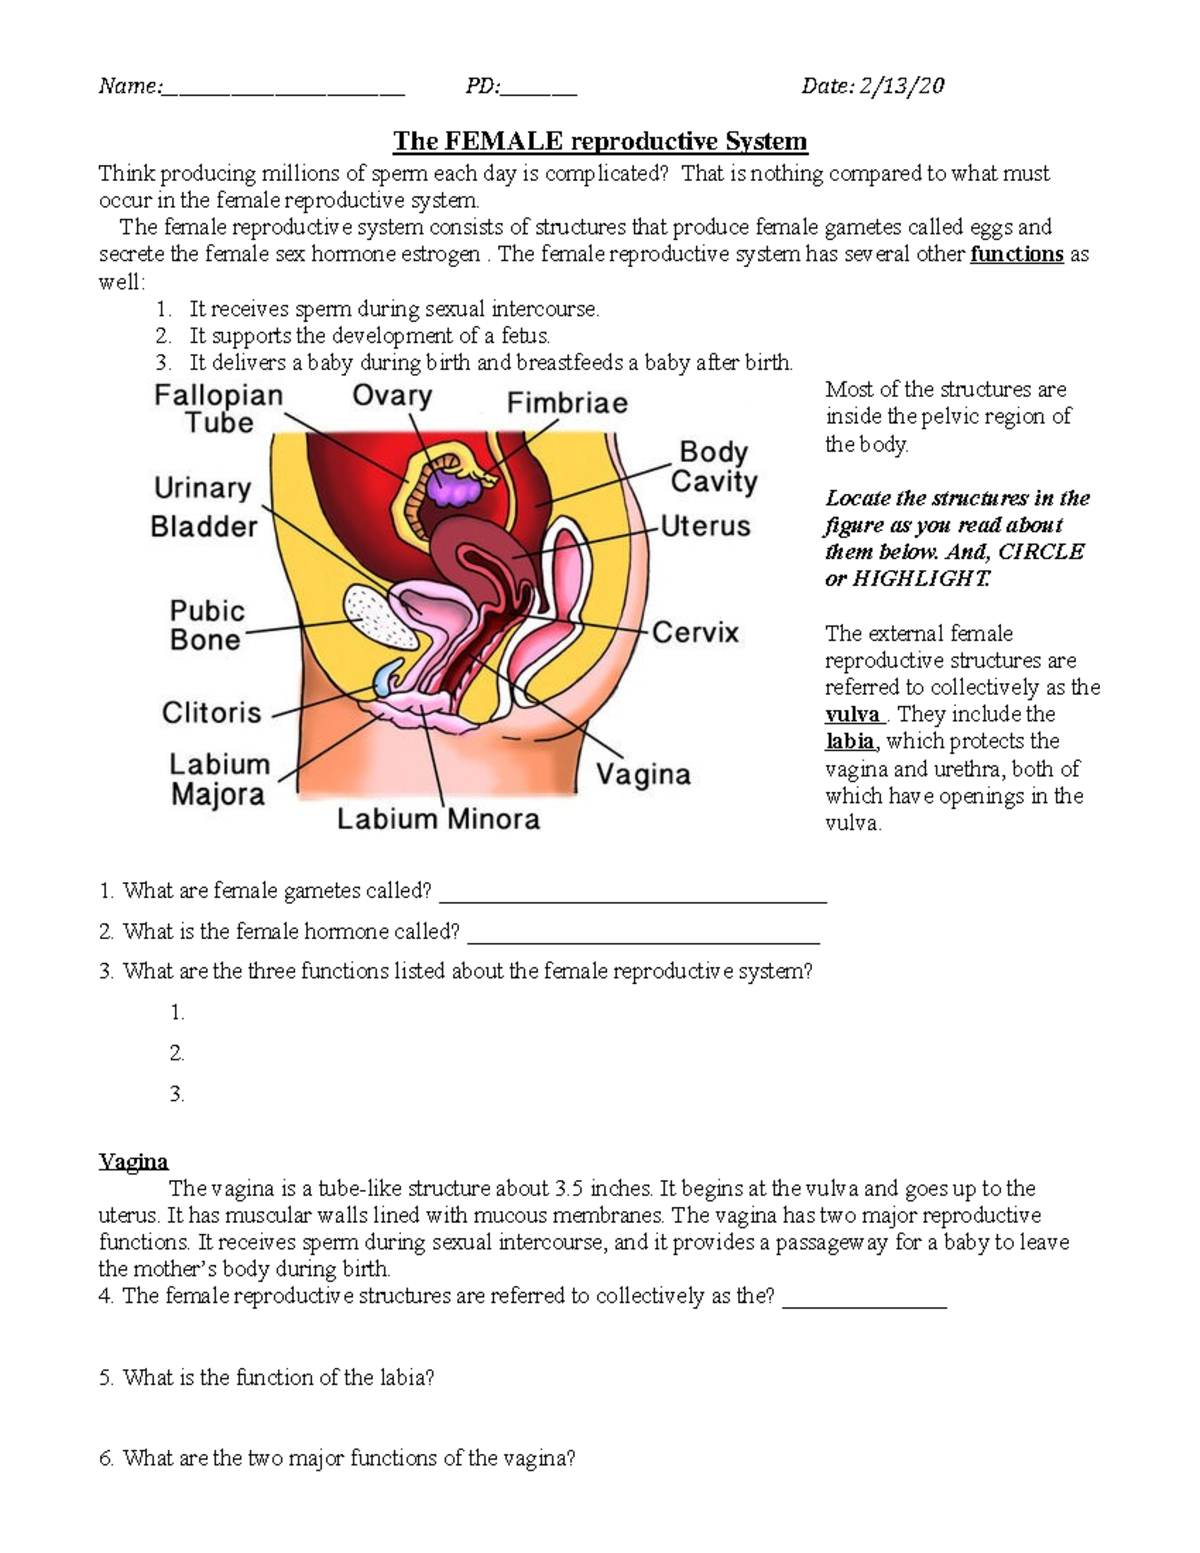
I spent a few years working in women's health education, and the most common issue I ran into wasn't that people lacked basic facts. It was that most resources either skip over the messy, uncomfortable parts entirely or dress them up in such sterile language that the reader ends up more confused than before. When someone comes to me with Questions About Female Reproductive System, the problem usually isn't a lack of curiosity. It's that the information they've found doesn't match how their own body actually behaves. The reproductive system is made up of internal and external structures that work together in a cycle that isn't quite as neat as most diagrams suggest. The ovaries produce eggs and hormones, the fallopian tubes are the pathways where fertilization happens if sperm is present, the uterus is the muscular organ that can support a pregnancy, and the cervix connects the uterus to the vagina. The external structures include the vulva, which encompasses the labia, clitoris, and vaginal opening. Here is where it gets complicated in practice. The menstrual cycle average is often stated as 28 days, but that number covers a very narrow slice of the population. A cycle between 21 and 35 days is considered normal, and even that range shifts depending on stress, illness, travel, and age. I had a patient once who thought her 42-day cycle meant something was wrong because her textbook said 28. It was completely normal for her. The takeaway is that regularity matters more than any specific day count.
The ovulation window is another area where people routinely misinterpret their bodies. Ovulation generally occurs about 14 days before the next period starts, not 14 days after the last one begins. If someone has a shorter cycle, they ovulate earlier. If the cycle is longer, ovulation is later. Tracking ovulation with basal body temperature or LH predictor kits works, but these methods have a margin of error that most people don't account for. A fever, poor sleep, or even a glass of wine the night before can throw off a temperature reading.
Practical Things Most Sources Don't Tell You
The clitoris is not just the external nub most people learn about. The full structure includes internal bulbs and limbs that extend several centimeters inside the body, wrapping around the vaginal canal. This is relevant because arousal and blood flow involve more tissue than people typically realize. Similarly, the vaginal canal is not a fixed open tube. It's a collapsed space that expands during arousal and childbirth. At rest, the walls touch each other, which is why issues like prolapse or atrophy become noticeable later in life when tissue elasticity decreases. One counter-intuitive point that comes up constantly: the cervix does not have pain receptors for the kind of pain most people expect. You can have cervical exams,Pap smears, and even procedures that involve the cervix without feeling sharp pain in the way you might imagine. What you might feel is pressure, cramping, or nausea from a vasovagal response. I learned this the hard way when a colleague once insisted a procedure hurt the cervix directly, when in reality the discomfort came from the surrounding ligaments and the peritoneum being tugged. Another thing that trips people up is the idea that the reproductive system stops working abruptly at menopause. It does not. Ovarian function declines gradually over what is called perimenopause, which can last four to ten years. During that time, cycles become unpredictable, estrogen and progesterone levels swing rather than decline steadily, and symptoms can range from mild to severe. Some people have almost no issues. Others cannot function normally without intervention. Both outcomes are within the normal range.
Get the Full Details
When to Actually See a Professional
Most symptoms that worry people are not emergencies, but a few patterns should prompt a visit to a healthcare provider. Bleeding between periods, bleeding after sex, or bleeding that is significantly heavier than usual deserves attention. Periods that last longer than seven days or require changing protection every hour or less are not normal and should be evaluated. Severe pain that interferes with daily activity during menstruation is worth looking into, especially if it is a new pattern or getting worse over time. A missed period when pregnancy is not desired is another common reason to get checked. I once worked with someone who had been told her severe menstrual pain was just something she would have to live with. She had endometriosis, which is when tissue similar to the uterine lining grows outside the uterus. This is not rare. It affects roughly one in ten people of reproductive age. The delay in diagnosis is one of the biggest failures in women's health, and the average time to get a correct diagnosis is seven to ten years from symptom onset. Pain should not be automatically dismissed as normal.
What to Watch Out For
Self-diagnosis through online forums is a minefield. The internet is full of anecdotes presented as universal truths. One person's experience with a supplement, a diet change, or an alternative therapy is not medical evidence. Information from reputable sources like the American College of Obstetricians and Gynecologists, the World Health Organization, or peer-reviewed journals is far more reliable, but even those have limitations. Guidelines are based on population data, not individual bodies. Over-the-counter menstrual products are generally safe, but some people develop irritation from scented products or certain materials. Organic cotton liners and unscented pads tend to be the safest bet for sensitive skin. For birth control, there is no one-size-fits-all method. Hormonal options work well for many people but are not suitable for those with certain medical conditions like a history of blood clots or migraines with aura. Non-hormonal options like copper IUDs exist but can make periods heavier and more painful for some. The bottom line is that the female reproductive system is complex and highly individual. General information is useful as a starting point, but specific concerns should be discussed with a qualified healthcare provider who can take a full history and run appropriate tests. No article, no matter how thorough, can replace an actual clinical evaluation.




