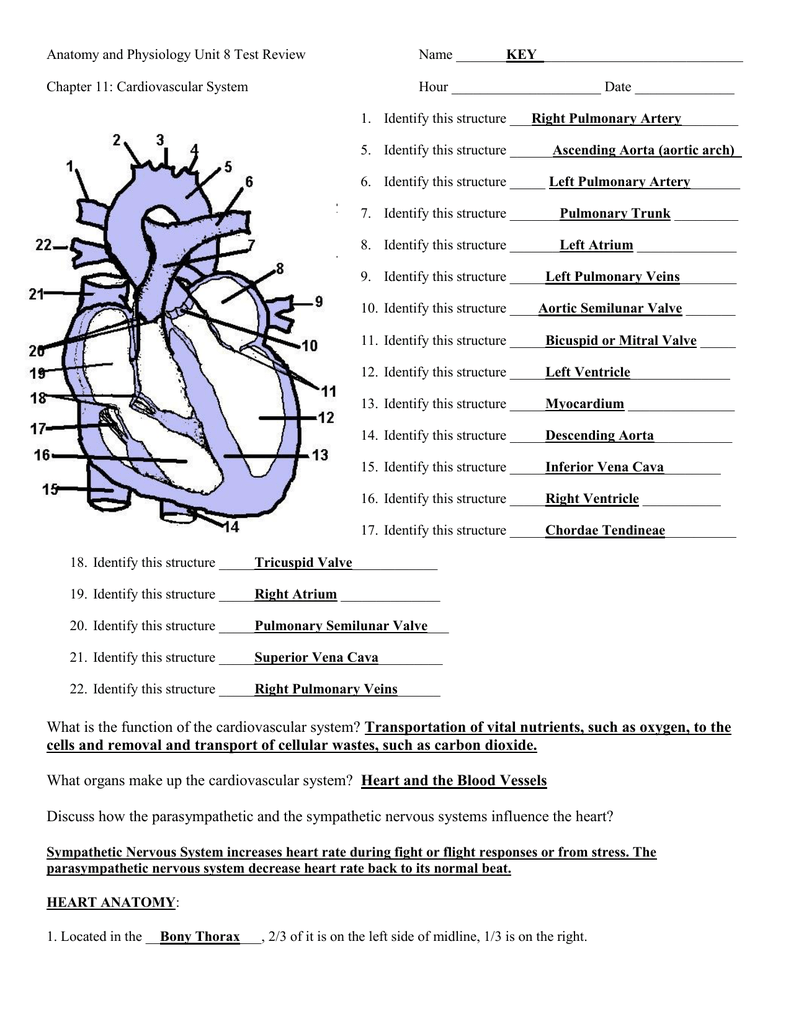
Understanding The Cardiovascular System: What Actually Matters
The cardiovascular system is often taught in biology classes as if it's just about pumping blood, but anyone who has actually studied it knows it's more complex than that. You hear terms like "systemic circulation," "coronary perfusion," and "autonomic regulation" thrown around without real context. That's where Questions About The Cardiovascular System come in — not as a buzzword, but as the real you run into when trying to connect textbook diagrams to how the body actually behaves under stress, disease, or pharmacological intervention. I remember working through a case study back when I was still in training. We had a patient with what appeared to be a straightforward hypertension diagnosis. Blood pressure readings were consistently elevated, resting heart rate was normal, and there were no obvious signs of secondary causes. Standard protocols said to start with an ACE inhibitor. But something felt off about the case. The patient had normal sodium levels, no renal artery stenosis on imaging, and the blood pressure was labile — spiking unpredictably rather than staying chronically high. That inconsistency kept me up at night because it didn't fit the textbook model. Eventually, we discovered the patient had an undiagnosed pheochromocytoma, a rare tumor that secretes catecholamines intermittently. Starting with an ACE inhibitor would have been dangerous here because it could have precipitated a hypertensive crisis. This is the kind of edge case that no flashcard will prepare you for. What most people miss when learning about cardiovascular physiology is that the system doesn't operate in isolation. The kidneys, the endocrine system, the nervous system — they all feed back into cardiovascular function continuously. When you look at something like blood pressure regulation, you're not just looking at the heart and arteries. You're looking at a dynamic feedback loop involving baroreceptors, chemoreceptors, the renin-angiotensin-aldosterone system, antidiuretic hormone, and sympathetic nervous tone. Understanding this is what separates someone who can pass a multiple-choice exam from someone who can actually reason through clinical problems.
Another thing that trips people up is the distinction between preload, afterload, and contractility. Textbooks explain them individually, but they don't show how they interact in real time. Let me give you a practical example. If you're studying heart failure, you need to understand that increasing preload in a failing heart doesn't always improve cardiac output. In fact, beyond a certain point, additional preload just increases ventricular wall stress and oxygen demand without any meaningful gain in stroke volume. This is the Frank-Starling mechanism, yes, but the curve flattens out in heart failure, and that flattening is clinically significant. Beta-blockers, for instance, work partly by reducing heart rate and allowing more filling time, which improves preload utilization without increasing myocardial oxygen consumption. That's not intuitive unless you've worked through the hemodynamics carefully. The coronary circulation deserves more attention than it typically gets in introductory courses. The left coronary artery, which supplies the left ventricle, receives most of its blood flow during diastole, not systole. During systole, the contracting myocardium compresses the intramural vessels and actually restricts flow. This is why conditions like aortic stenosis — which prolong systole and increase ventricular pressure — are so dangerous for the coronary circulation. It's also why tachycardia is poorly tolerated in patients with coronary artery disease. A faster heart rate shortens diastole, which is when the coronaries perfuse, and that directly reduces oxygen supply to the myocardium. Here's a practical approach to studying the cardiovascular system that actually works:
Start with the hemodynamics. Learn how pressure, flow, and resistance relate to each other through the equation BP = CO x TPR. This isn't just a formula you memorize for a test. It's the framework you use to think through every cardiovascular problem. When someone has low blood pressure, you ask: is it a cardiac output problem or a vascular resistance problem? When someone has edema, you consider capillary hydrostatic pressure versus oncotic pressure. The equation organizes your thinking. Then move to the electrical system. The conduction pathway — sinoatrial node, atrioventricular node, Bundle of His, Purkinje fibers — isn't just anatomy trivia. Understanding the sequence and timing of electrical activation is essential for interpreting ECGs, which are the single most useful diagnostic tool in cardiovascular medicine. A premature ventricular contraction, a first-degree AV block, a bundle branch block — each tells you something specific about the state of the conduction system. Learning to read ECGs takes practice, but it's not magic. It's pattern recognition built on understanding the underlying physiology. For pharmacology, focus on mechanisms rather than memorizing drug lists. Knowing that beta-blockers antagonize sympathetic stimulation at the beta-1 receptor explains why they slow heart rate, reduce contractility, and are used in hypertension, angina, arrhythmias, and heart failure. You don't need to memorize ten different beta-blockers. You need to understand what blocking beta-1 receptors does and then learn the pharmacokinetic differences between the drugs in that class.
Get the Full Details

One thing I wish someone had told me earlier is that the cardiovascular system has remarkable compensatory mechanisms, but those mechanisms can become maladaptive over time. Consider heart failure. The initial response to decreased cardiac output includes activation of the sympathetic nervous system and the renin-angiotensin-aldosterone system. These increase heart rate, contractility, and blood volume to maintain perfusion. But chronic activation of these systems leads to ventricular remodeling, fibrosis, and worsening function. This is why treatments for heart failure target these very pathways — ACE inhibitors, beta-blockers, aldosterone antagonists — not because they fix the underlying problem, but because they blunt the compensatory responses that cause long-term damage. If you're looking for resources, the standard physiology textbooks like Guyton and Hall or Ganong remain the most comprehensive references available. For a more clinical angle, Braunwald's Heart Disease is the definitive reference, though it's expensive and dense. Online, the American Heart Association and the European Society of Cardiology publish guidelines that are freely accessible and reflect current evidence. YouTube channels like Ninja Nerd and Dr. Matt & Dr. Mike provide detailed physiology lectures that are useful for visual learners. For ECG interpretation, 12Lead.com and Life in the Fast Lane are solid free resources. There's a common misconception that studying the cardiovascular system is mostly about memorizing structures and pathways. It's not. It's about understanding function and how that function changes in health and disease. When you grasp the principles — hemodynamics, electrophysiology, neurohormonal regulation — you can reason through situations you've never seen before. That's what makes this topic worth investing time in, whether you're a medical student, a nursing student, or just someone who wants to understand how their own body works.
The cardiovascular system will continue to be a major focus of medical research and clinical practice. Issues like hypertension, coronary artery disease, heart failure, and arrhythmias affect hundreds of millions of people worldwide. Understanding the basics isn't just academically interesting — it's practically useful for anyone who wants to make informed decisions about their health or pursue a career in healthcare. Start with the fundamentals, build layer by layer, and don't rush to memorize before you understand.