Getting Started With Apraxia Assessment Tools
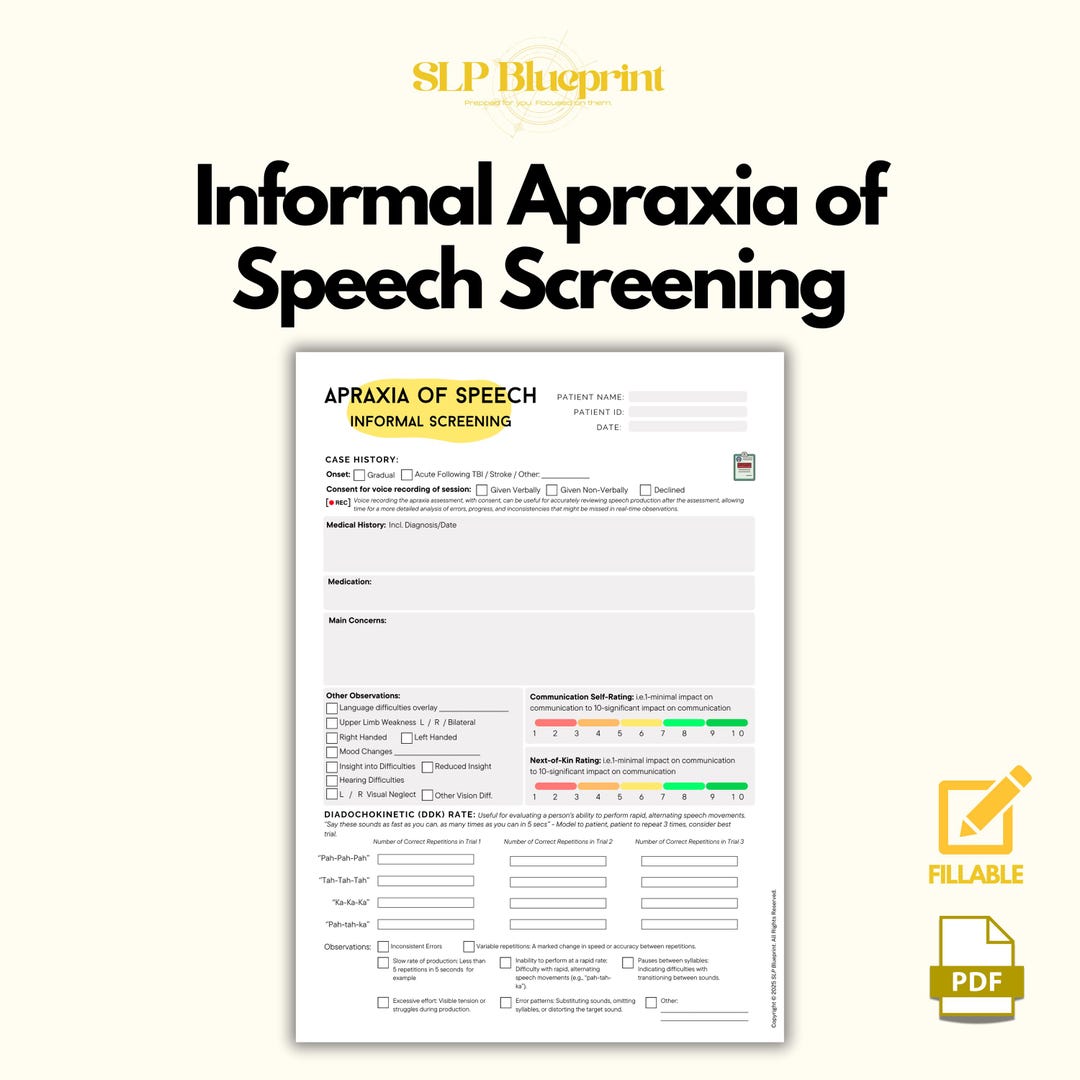
Most speech-language pathologists have spent more time than they'd like trying to pin down apraxia of speech in a client. The problem isn't that the disorder is vague—it's that the assessment tools themselves are scattered across expensive copyrighted materials, and what passes for a "quick assessment" in most practices is basically a checklist that misses half the relevant motor speech behaviors. I worked in a pediatric clinic for years, then moved into adult neurology, and the core issue stays the same: you need something that takes under twenty minutes, gives you defensible data, and actually discriminates apraxia from phonological disorders or dysarthria. A well-constructed Quick Assessment For Apraxia Of Speech Pdf does most of that, though it has real limitations you should know before you hand it to a parent or put it in a client file.What You Are Actually Testing
Apraxia of speech, whether childhood onset or adult-acquired, is a motor planning and programming deficit. It is not a muscle weakness problem, and it is not primarily a language problem. When you run through a quick assessment, the items that matter most are those that probe voluntary motor speech control versus automatic or imitated speech. The classic triad you're looking for: inconsistent errors across repeated productions, difficulty planning and sequencing articulatory gestures, and graded difficulty that scales with word length and phonological complexity. A PDF assessment tool that hits these points will ask the client to produce single words, pseudowords, and phrases across increasing syllable counts. If your document doesn't include nonword repetition, you're missing one of the strongest discriminators available.How To Actually Use The PDF In Practice
I downloaded a handful of free apraxia screening PDFs over the years. Most were fine as a starting point, but the one I ended up using regularly was a composite I built from public-domain stimuli combined with items adapted from standardized protocols. Here's how I run through it with a client who might be referred for suspected apraxia.I begin with oral mechanism screening, but I keep it brief—five minutes at most. Lip retraction, lip round, tongue lateralization, sequential versus simultaneous movements. Most adults with apraxia show some subtle difficulty on diadochokinetic tasks, though that overlap with dysarthria is why the motor speech portion alone never makes the diagnosis. Next comes the core item set. I use a controlled list of monosyllabic words first—"bed," "desk," "ship," "gone." I watch for effortful initiations, audible/grunting hesitations, and substitution errors that shift between trials. Then I move to bisyllabic and trisyllabic items. The escalation in error rate across syllable counts is usually where apraxia reveals itself clearly. A child or adult with a phonological process disorder will tend to apply the same rule consistently. Apraxia gets worse as demand increases, and the errors become more random. The pseudoword repetition segment is where I separate the plausible from the speculative. I gave my own examples like "blup," "tavish," and "prosnik" because the client hasn't memorized them and can't rely on lexical memory. Correct repetition of novel phonological sequences under moderate difficulty requires intact motor planning. Struggling here, especially when single-word imitation of familiar words was relatively intact, is a strong indicator.
I wrap up with sentence and connected speech samples, recording a short 2-3 minute sample so I can review prosody afterward. Groggy rhythm, equal stress placement, and prolonged transitions between syllables within words are telltale markers. The PDF I reference includes a scoring grid that captures these observations in a structured way, which matters if you ever need to justify the diagnosis to a school team or insurance reviewer.
A Real Problem I Encountered
About three years ago, I was working with a seven-year-old who scored near typical on the consonant inventory and single-word repetition but had clear speech intelligibility issues in conversation. The Quick Assessment For Apraxia Of Speech Pdf results were ambiguous because the child had strong auditory comprehension and used visual cues to compensate during the test. What tipped the balance was the nonword repetition task performed under dual-task conditions—I had the child tap a rhythm on the table while repeating pseudowords. The cognitive load unmasked the motor planning deficit that the quiet testing environment was hiding. I added that dual-task protocol to my own version of the assessment PDF afterward, and it has improved my sensitivity for milder cases ever since.Counter-Intuitive Details People Miss
Most practitioners treat apraxia assessment as if it's purely about speech production accuracy. That's incomplete. self-monitoring ability is a major factor. Clients with apraxia often detect their own errors more slowly than peers with phonological disorders, and they may not self-correct even when they notice a mistake. I recommend adding a brief self-correction observation interval to any assessment protocol. Have the client repeat the same word three times and note whether they initiate a correction after hearing their own error. The delay or absence of self-correction is clinically meaningful and rarely included in free PDF screening tools.Another overlooked detail is the relationship between vowel errors and apraxia. Consonant substitutions get all the attention, but vowel distortions that vary across repetitions are disproportionately associated with motor speech planning deficits rather than phonological processes. If your scoring sheet doesn't track vowel accuracy separately, you're losing data. If you're working in any of those zones, the quick assessment should be a footnote, not the basis of your referral or treatment plan. You'd be better served by a full CAS-2, the PROMIS protocol, or referral to a clinic that can run videofluoroscopic or electromagnetic articulography data. Those are expensive and slow, yes, but they give you information a PDF scan sheet cannot. Scoring itself is straightforward. Each item is marked as correct, approximated, or incorrect with a note on error type. The summary section tallies accuracy by syllable count, pseudoword repetition score, and self-correction frequency. There is no clinical cut-off built into the PDF because apraxia exists on a continuum and the tool is designed to flag risk rather than confirm severity. Use those flags to decide whether a full diagnostic evaluation is warranted.
Get the Full Details

If you have been waiting for a compact, practical tool that covers the essential motor speech behaviors without requiring a full hour of administration time, this PDF is about as close to functional as you will find. It won't replace comprehensive testing, and it won't catch every case, but it will give you a structured starting point that saves you from improvising your own stimuli each time a referral lands on your desk.