What Receptive Language Processing Disorder Actually Looks Like in Practice
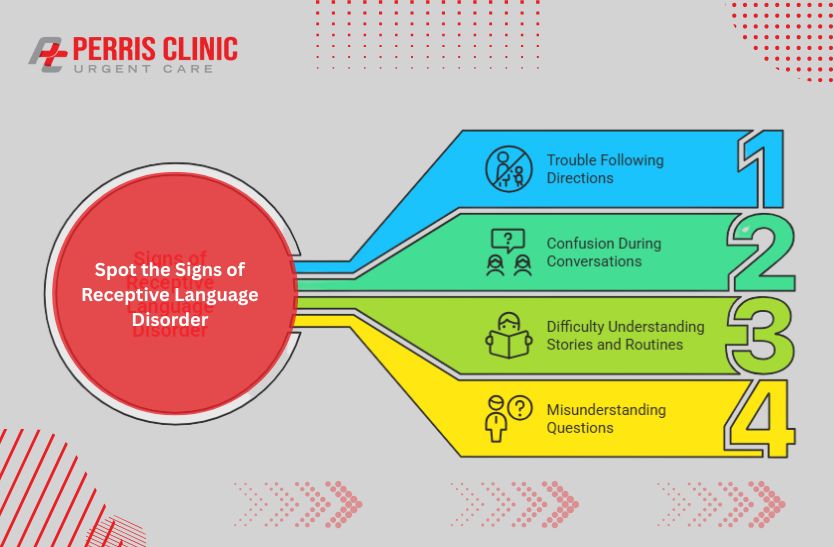
I've spent years working with people who get laughed off school IEP meetings because their IQ tests are normal and they can read perfectly well, but ask them to follow three-step directions in a noisy room and they just stare at you blankly. This is the most common misdiagnosis I see. Receptive Language Processing Disorder isn't a hearing problem. It isn't an intelligence problem. It's a processing bottleneck where the brain receives auditory or visual linguistic input but cannot reliably map it to meaning fast enough to use it in real time. The diagnostic criteria from the DSM-5 falls under Language Disorder (315.39), and you need persistent difficulty with comprehension across multiple modalities: understanding vocabulary, following complex sentence structures, grasping inferred meaning, or retaining verbal instructions long enough to act on them. But the test results never capture the daily friction. They miss the part where a 14-year-old girl spent her entire math class silently copying her neighbor's homework because she couldn't process the word problem quickly enough, while everyone assumed she was just not trying.
Receptive Language Processing Disorder: The Workaround That Actually Matters
The single most effective accommodation I've seen used successfully is what I call the chunk-and-confirm method. Instead of giving a student or adult a multi-part instruction and hoping they retain it, you give one discrete action, wait for confirmation, then move to the next. This sounds trivial but most people skip it entirely. When my brother got diagnosed at age eleven after four years of what teachers called "inattention," we stopped saying things like "go upstairs, brush your teeth, and get ready for bed" and started saying "go upstairs" and waiting. Just waiting. Until he was already moving. The second request went out only after physical movement toward the first target was confirmed. This cut his daily meltdown rate from roughly four per evening to maybe one. Visual scaffolding is the next layer. Written instructions, diagrams, checklists. Anything that moves the linguistic load out of the purely auditory channel and into a spatial-visual one that can be processed at the person's own pace. The problem is that most professionals recommend this in passing without actually setting it up. A laminated sequence card on the fridge is worth more than a pamphlet handed out at a doctor's office.
Why Standard Interventions Often Fail
Speech-language pathology is the go-to intervention, and it works for building vocabulary and processing speed over months or years. But here's the blunt truth: SLP sessions once a week for forty-five minutes do almost nothing to change how a person functions in a chaotic classroom or workplace on any given Tuesday. The transfer problem is real and poorly addressed. Skills practiced in a quiet office with a calm therapist don't reliably show up in environments where the person actually needs them. I've watched good SLP programs fizzle out because nobody adjusted the environment around the person. You can work on auditory memory drills until you're blue in the face, but if the person still sits in the front row near the projector with a teacher who talks fast and gives three-part instructions without pause, none of those drills matter. The accommodation of the environment is usually more impactful than the therapy itself, and that's an uncomfortable fact for many clinicians to hear. Another counter-intuitive point: these individuals often perform significantly better on written language tasks than oral ones. Their reading comprehension can be age-appropriate or even above average while their listening comprehension sits two to three grade levels below. This discrepancy is sometimes misread as effort problems or defiance. It's not. The brain processes text differently than speech because text allows self-pacing, rereading, and visual anchoring that spoken language simply doesn't provide in real time.
Get the Full Details
Self-Assessment and Diagnosis Path
If you suspect this in yourself or someone you work with, start with a comprehensive speech-language evaluation that includes standardized receptive language testing. The CELF-5 and TOLD-P:5 are the most commonly used instruments. But also ask for a clinical observation in naturalistic settings. A test score in a quiet room tells you less than watching how the person responds to casual conversation across different contexts. Audiological screening should come first to rule out hearing loss, though mild conductive issues are far more common than people realize and can compound an existing receptive disorder. Then move to the language assessment. For adults, this often means tracking down a neuropsychologist or a SLP who specializes in adult language disorders, which is a smaller group than you might expect. Most pediatric-focused SLPs don't work with adults, and general audiologists rarely assess receptive language beyond basic screening. Co-occurring conditions are the rule rather than the exception. ADHD, dyslexia, and autism spectrum disorder show up frequently in my experience. About a third of the people I've worked with had an ADHD diagnosis first and the receptive language issue was either missed entirely or attributed to inattention. That matters because treating the ADHD without addressing the language processing gap leaves the core problem untouched.
Practical Strategies for Adults and Caregivers
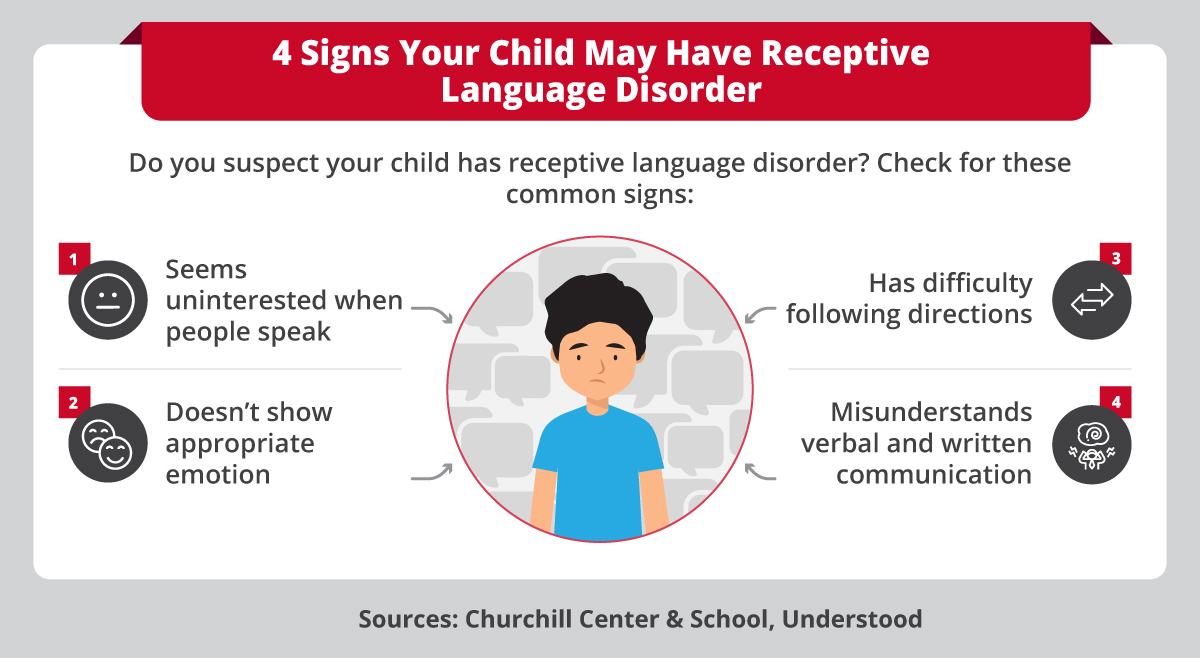
For adults who have been missed for years, the frustration level is often extreme because they spent decades developing elaborate coping mechanisms that are exhausting and invisible to everyone else. Some learned to sit quietly and nod. Others became aggressive questioners who demand repetition until they feel confident they understood. Both are reasonable adaptations. Neither addresses the underlying processing limitation. Useful tools include voice-to-text apps for converting meetings and lectures into readable text, which buys the processing time the brain needs. Recording devices for appointments and important conversations. Requesting written follow-ups after verbal instructions in professional settings. These aren't accommodations for laziness. They're the equivalent of glasses for someone who can't hear clearly. For parents of children with this disorder, the hardest thing to accept is that the child isn't lazy or disrespectful. The child genuinely cannot take in what you're saying at the speed you're saying it. This is developmental, not behavioral. Punishment for non-compliance based on misprocessed instructions only adds shame to an already difficult experience. Time and environment adjustment, not correction, is usually the path forward.
Resources and Support Materials
The ASHA (American Speech-Language-Hearing Association) website offers free parent and adult guides on receptive language disorder that are actually written at an appropriate level. The BetterSpeech.com resource library has printable strategy sheets that work well for classroom use. For self-assessment, the Language Assessment Screening Tool (LAST) available through university speech clinics can provide a preliminary screen, though it's not a substitute for professional evaluation. Online communities like the Receptive Language Disorder support group on Facebook have thousands of members sharing real-world strategies, though the quality of advice varies widely. I recommend cross-referencing any tip with a certified SLP before making it a permanent practice. The internet is full of people recommending exercises that sound good but have no empirical backing. The bottom line is that receptive language processing disorder is treatable in the sense that people learn to manage it effectively, but it is not something that disappears with enough practice. The brain's processing pathway is wired differently, and the goal is building sufficient compensatory structures rather than expecting a cure. That distinction shapes everything about how you approach intervention, whether for a child or for yourself.




