Understanding What Happens When Red Blood Cells Meet a Hypertonic Environment
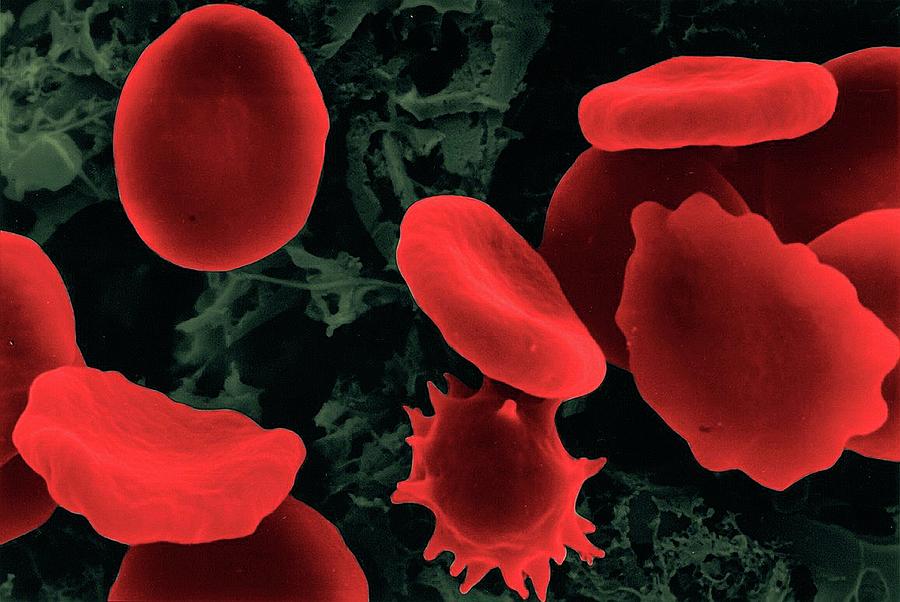
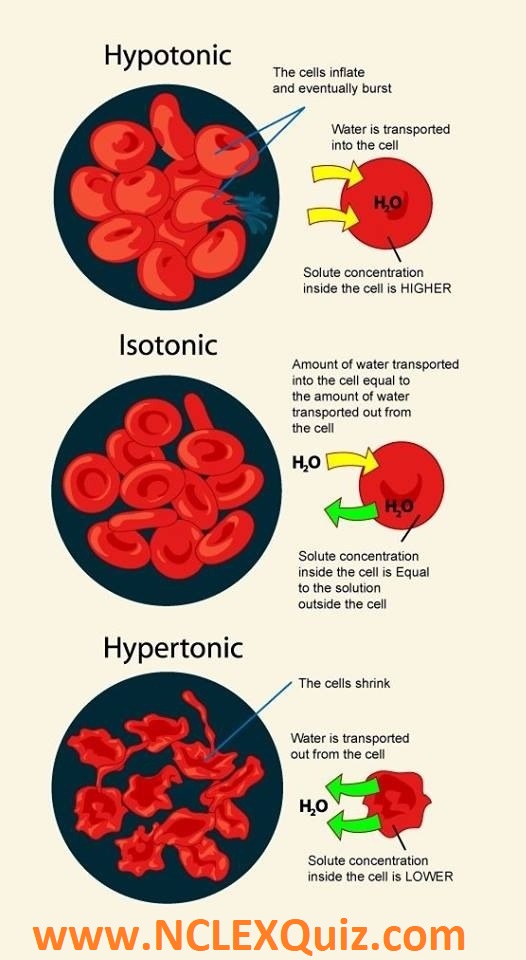
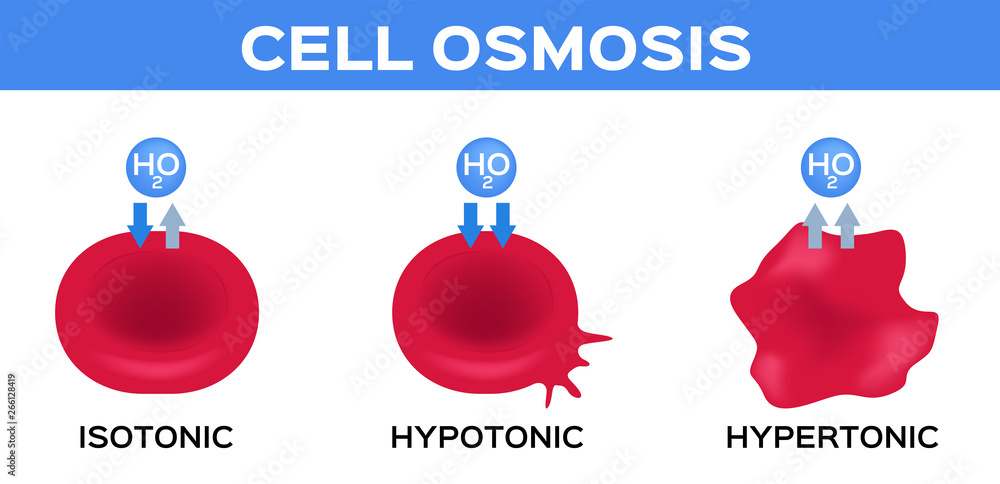
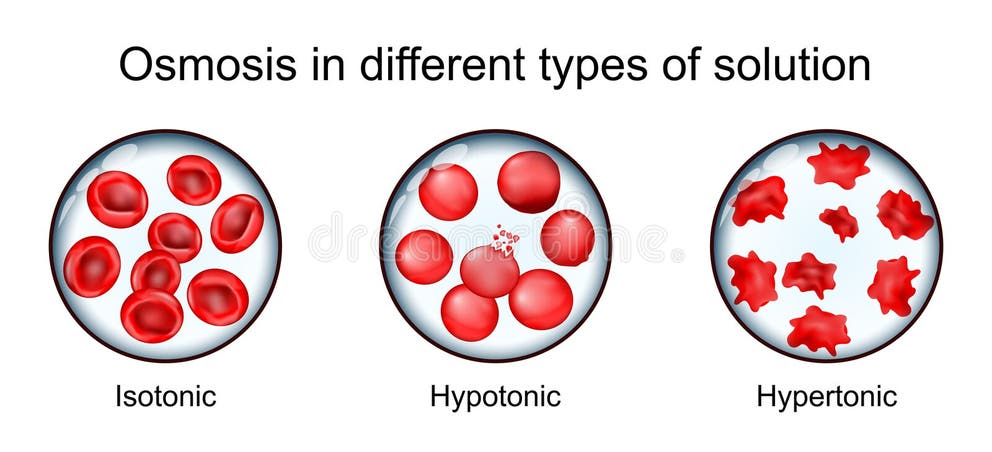
Most people learning about osmosis and red blood cells get tripped up because they memorize the diagram without understanding what actually happens at the membrane level. The process is straightforward, but the details matter more than you'd think if you're working in a lab or clinical setting. A hypertonic solution has a higher solute concentration than the fluid inside the red blood cell. When RBCs are placed in this environment, water moves out of the cell through the semipermeable membrane to try to balance the concentrations on both sides. This is passive osmosis — no energy required, just physics doing what it always does. The cell loses volume. It shrinks. The membrane develops a spiky, jagged appearance called crenation. This isn't the same as hemolysis, which is what happens in a hypotonic solution where the cell bursts from taking on too much water. Crenation is structurally different and, in most cases, reversible if the cells are returned to an isotonic environment quickly enough.
Here's something beginners routinely miss: not all hypertonic solutions produce the same degree of crenation, and the speed matters. A 3% NaCl solution will cause rapid, dramatic crenation in a matter of minutes. A slightly hypertonic solution at 1.5% NaCl takes longer and the effect is less pronounced. I've seen students report "no change" in their lab results when they assumed a marginal hypertonic solution would look the same as a strongly hypertonic one. It doesn't. The osmotic gradient determines the rate and extent of water movement, and small differences in concentration create big differences in what you actually observe under the microscope. I ran into a problem once where I was preparing hypertonic saline for a blood compatibility study and kept getting inconsistent crenation results across samples. Turns out I was using tap water to make the solutions instead of distilled or deionized water. The minerals and ions already present in tap water were shifting the effective tonicity in ways I hadn't accounted for. Switching to properly purified water and standardizing everything to a known baseline fixed the issue completely. That kind of thing doesn't show up in the textbook procedure. Another counter-intuitive point: crenation is generally reversible, but not always. If the hypertonic exposure is too severe or lasts too long, the membrane can be damaged beyond repair. The lipid bilayer and underlying spectrin network can suffer structural stress from the extreme volume change. Once the membrane integrity is compromised, returning the cell to isotonic conditions won't restore it to normal. The cell stays shriveled or eventually lyses anyway. I've seen this happen in samples that were left sitting in concentrated saline for extended periods during processing. The cells looked crenated at first glance, but when I transferred them back to isotonic buffer, they didn't recover — they stayed abnormal or fell apart entirely.
The clinical relevance here is worth noting. Hypertonic saline (usually 3%) is sometimes used in emergency settings for patients with increased intracranial pressure because it draws water out of swollen brain tissue. Red blood cells in those patients will experience crenation transiently. This is generally not a concern in acute use because the exposure is brief and systemic, but it's something to keep in mind if you're dealing with prolonged hyperosmolar states or repeated dosing. If you're doing this in a lab, the standard protocol is simple: prepare your hypertonic solution at the desired concentration, add a drop of blood, mix gently, place a small amount on a slide, cover with a coverslip, and observe under high power (400x or 1000x oil immersion). You should see the characteristic shriveled, spiky morphology within a few minutes. Normal RBCs are smooth, biconcave discs. Crenated RBCs look nothing like that. Common pitfalls:
Get the Full Details
- Using the wrong concentration and expecting dramatic results — marginal hypertonic solutions produce subtle changes that are easy to miss or misinterpret
- Not controlling for temperature, which affects membrane fluidity and the rate of osmosis
- Observing too late — prolonged exposure leads to irreversible damage that confuses the interpretation
- Contaminated water or improper solution preparation shifting the actual tonicity away from what you calculated
The main limitation of relying on this as a diagnostic or analytical tool is that crenation alone doesn't tell you much about the underlying cause of a patient's condition. It's a morphological observation, not a quantitative one. If you need to know the exact osmolality of a patient's serum, you measure it with an osmometer. You don't infer it from what the RBCs look like on a slide. The slide method is useful for teaching and quick visualization, but it's not precise enough for clinical decision-making on its own. For more accurate work, flow cytometry or automated hematology analyzers that measure cell volume distribution give you actual data instead of a visual guess. If you need quantifiable results, skip the microscope approach and use the instruments designed for it.