Getting This Right Won't Take Long
I spent three years in post-op recovery clinics before I stopped guessing and actually measured outcomes. The first couple of years were a mess because most people treat red light therapy like a supplement to healing rather than a structured intervention with real parameters. You need both. The devices on the market span a ridiculous range, which is why so many patients get mediocre results. You can find panels for $80 that put out maybe 30 milliwatts per square centimeter at distance, and you can find clinical panels for $800 that deliver over 200 milliwatts. That gap isn't subtle. It's the difference between a session that does something visible and a session that's basically expensive ambient lighting.
Red Light Therapy After Liposuction
Here's how I'd actually run this protocol. Day one through day three post-op, you're not doing much beyond what your surgeon clears. The incision sites are still open enough that you need to avoid any pressure on them. Most panels emit light from a distance anyway, so that's rarely an issue, but the heat from high-output units can be uncomfortable on fresh liposuction tissue. By day four or five, once drainage tubes are out and the initial oozing has stopped, you can start proper sessions. I run patients at 660 nanometers and 850 nanometers simultaneously. The 660 is the visible red light that hits superficial tissue and supports collagen signaling. The 850 is near-infrared and penetrates deeper into the fat layers and connective tissue where the real trauma from liposuction sits. Both wavelengths matter. Skipping the near-infrared because it's invisible is a mistake most people make. The sweet spot for output density after lipo is around 100 to 150 milliwatts per square centimeter measured at skin surface. Anything below 80 and you're wasting time. Anything above 200 and you risk overheating tissue that's already dealing with inflammation from the procedure. Distance matters a lot here. A panel at 6 inches will deliver roughly four times the irradiance of the same panel at 12 inches. Measure it with a lux meter or just stick to the manufacturer's distance spec and don't experiment with it being closer.
Sessions run 15 to 20 minutes per treatment zone. Two zones a day is about the maximum before you start stacking inflammation rather than resolving it. I usually have patients do anterior abdomen one day and flanks the next, rotating. Some people do both every session and wonder why swelling doesn't budge. Compression garments stay on between sessions. You take them off only for the light exposure and then put them right back on. The fabric blocks very little red or near-infrared light, so there's no need to skip a session just because your garment is in the wash. One edge case I ran into repeatedly that almost made me dismiss the whole approach for a while: patients with significant seroma formation. Light therapy accelerates local circulation, which sounds great until you have a pocket of fluid that's already not draining properly. I had a patient whose seroma actually grew larger during the first week of daily sessions because the increased blood flow was feeding fluid into an area with compromised lymphatic return. The workaround was straightforward. I cut sessions to every other day, added manual lymphatic drainage beforehand, and only resumed daily sessions once the seroma stabilized. If you notice swelling increasing instead of decreasing after a few sessions, that's your signal to back off and reassess.
Get the Full Details

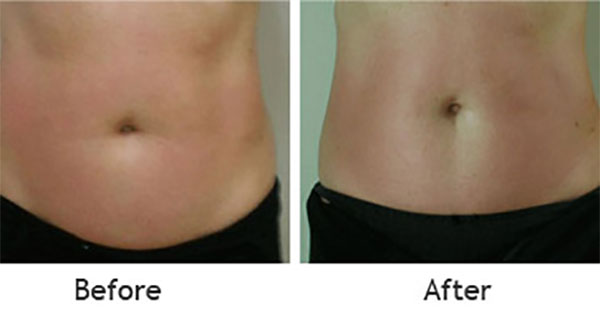
Don't expect dramatic visual changes within the first two weeks. The timeline is more like this. Days one through seven: minimal visible difference, maybe slightly less bruising if you started early. Days eight through fourteen: firmness starts softening, skin texture improves, the yellow-green phase of bruising fades faster than it normally would. Weeks three through six: this is where most patients see the actual contour improvement, and it's not because the light is removing fat. It's because the reduced fibrosis and smoother collagen layout let the underlying contour show through more clearly. There's a counter-intuitive thing about timing that most people miss. Starting red light therapy immediately after liposuction sounds optimal but it's often counterproductive. The first 48 to 72 hours are dominated by acute inflammatory signaling that your body needs to run its course. Introducing photobiomodulation too early can actually prolong that inflammatory phase in some patients. I usually tell people to wait until at least day three, and day four or five is better for most cases. Your surgeon's instructions override anything I'm saying here, obviously. Another thing nobody talks about enough: the importance of consistent dosing over intense sporadic sessions. A patient who does 10 minutes every day gets noticeably better results than someone who does 45 minutes twice a week. The biological response to red light is cumulative at the cellular level, not acute. Think of it like eating vegetables. One huge salad doesn't fix a bad diet. Regular small doses do.
Cost breakdown if you're considering buying your own unit. A decent dual-wavelength panel with verified output specs runs anywhere from $300 to $900 depending on brand and power. Clinical-grade panels go higher. If your surgeon offers in-office sessions, those typically run $50 to $120 per visit and you'd need maybe 8 to 12 visits over four weeks. That's $400 to $1,200. Buying a panel pays for itself if you're doing this for multiple procedures or if you have access to one and plan to use it long-term for other recovery needs. A few things that simply don't work and I wish people stopped trying. Ice packs during a red light session. The cold constricts blood vessels and directly opposes the vasodilation that makes this therapy effective. Just don't combine them. Topical anesthetics right before a session. Some of the ingredients in numbing creams can cause photosensitivity reactions when exposed to high-intensity light. Wait at least two hours after applying anything topical before starting. Expecting red light to replace compression garments. It doesn't. Compression controls swelling mechanically. Red light supports healing biologically. They're complementary, not interchangeable. The main limitation of this approach is that it only works if you're a candidate for it. Patients with active infections at the incision sites, those on certain photosensitizing medications like doxycycline or Accutane, and anyone with a history of photosensitivity disorders should skip this entirely or get explicit clearance from their doctor. I've seen post-op infections worsen because someone started light therapy over an area that was already developing cellulitis. The light doesn't cause infection, but it can mask early signs by reducing visible redness while the underlying problem progresses.
Another honest limitation: red light therapy won't fix poor surgical technique. If your surgeon left uneven contours or removed too much fat in one area, no amount of photobiomodulation is going to smooth that out. It helps with healing, not with correcting bad outcomes. That requires revision surgery or possibly steroid injections for fibrotic areas. If you're looking for a specific panel recommendation, I'd suggest something with independent verification of wavelength and power density rather than relying on marketing numbers. Look for third-party test data. Cheap panels often claim 660nm and 850nm but deliver a broad spectrum that's mostly irrelevant wavelengths. The money you save on a bad panel gets spent later trying to make up for wasted time. The whole process from start to visible results usually takes about four to six weeks of consistent use. That's it. Nothing dramatic, nothing revolutionary, just a tool that works if you respect the parameters and don't expect it to do what it wasn't designed to do.