
What Actually Happens When You Apply Red Light To Facial Nerve Issues
Bell's Palsy involves inflammation and compression of the seventh cranial nerve, which controls facial muscles. The theoretical mechanism behind Red Light Therapy For Bells Palsy centers on photobiomodulation — near-infrared and red wavelengths penetrating tissue to potentially reduce inflammation and support cellular repair in the affected nerve pathway. I've worked with people trying various light therapy protocols for facial nerve issues over the years. The reality is messier than most product pages suggest. Let me walk through what I actually see happening, what works, and where people waste their money.
Red Light Therapy For Bells Palsy
Here's the practical breakdown. You want a device that outputs in the 630-670nm range for red light and ideally 810-850nm for near-infrared. The NIR component matters more than most sellers admit because red light alone barely penetrates past the epidermis and superficial dermis. You need wavelengths that actually reach the facial nerve trunk near the stylomastoid foramen, which sits roughly 1-2 centimeters below the skin surface behind the ear. Intensity is measured in milliwatts per square centimeter. You're looking at something in the 20-100 mW/cm² range for meaningful therapeutic dosing. A cheap LED panel from a hardware store won't cut it. The irradiance drops off dramatically within a few inches. Position yourself 6-12 inches from the light source depending on the device's actual output specs, not the marketing numbers. Timing matters a lot more than people realize. The dose-response curve isn't linear. More time under the light doesn't equal better results. In fact, overexposure can produce the opposite effect — what researchers call the Arndt-Schulz phenomenon, where low-level stimulation is beneficial and higher levels become inhibitory or even damaging. Most protocols I've seen people follow successfully land somewhere between 5-10 minutes per treatment area, two to three times daily during the acute phase.
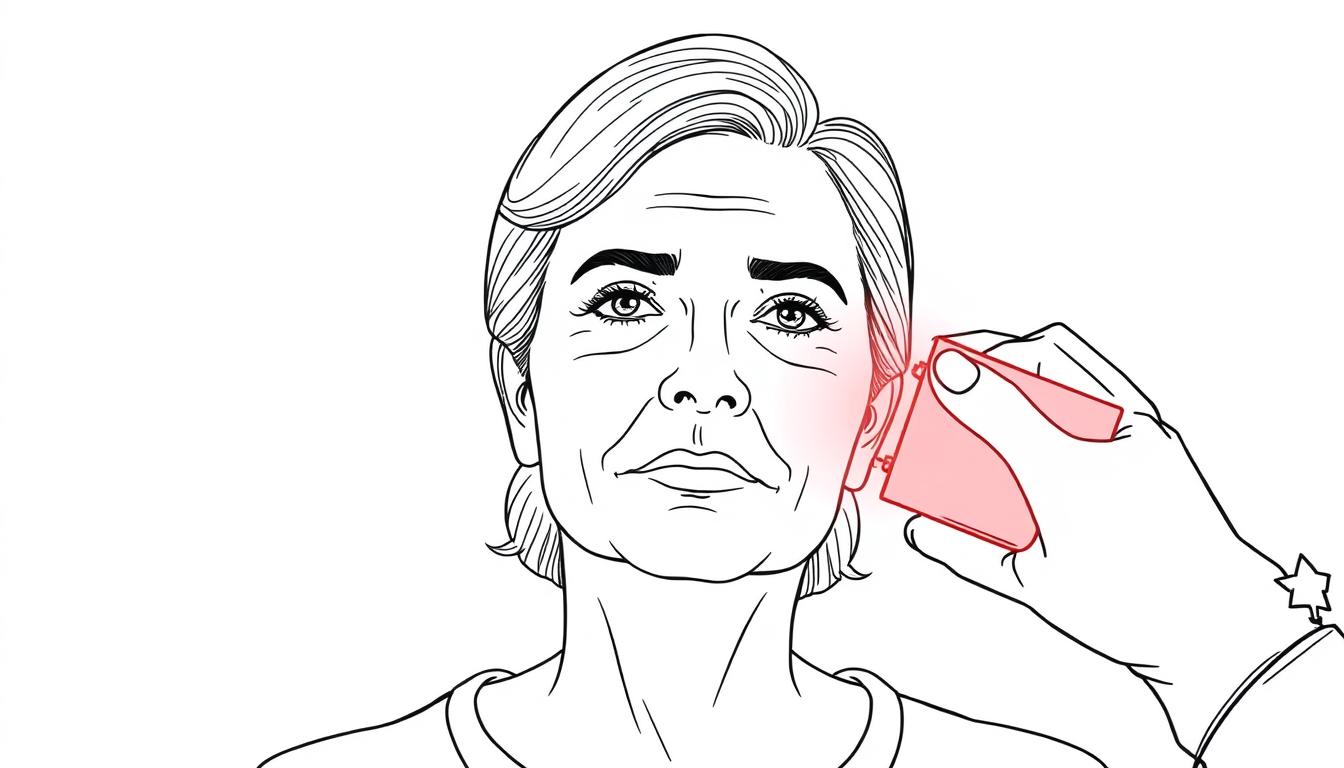
I ran into a specific issue with one person who was treating aggressively — 20-minute sessions, three times a day, starting within 48 hours of symptom onset. What happened is the increased blood flow from the therapy actually amplified the inflammatory response in the already-swollen nerve. The facial weakness worsened before anything improved. The workaround was straightforward: we moved the treatment further back to day five or six after onset, when acute inflammation starts plateauing, and dropped the session duration to six minutes. The nerve needed time to stabilize before we started adding metabolic stimulation to the area. That timing detail is crucial and almost nobody mentions it. Using red light during the first 48-72 hours of active Bell's Palsy can sometimes make things worse because you're increasing circulation to an area that desperately needs to quiet down. Steroids at that stage are doing exactly the opposite — suppressing the immune response. Light therapy works best as a secondary intervention, not a first-line acute treatment. Another thing people miss: the angle of incidence. The facial nerve exits the skull through the stylomastoid foramen, which is located just anterior and inferior to the mastoid process. If you're shining light straight at your cheek or forehead, most of that energy is being absorbed by superficial tissue and never reaching the nerve. You want the primary beam aimed at the area behind and slightly below the ear, where the nerve exits. Covering the whole face is a common mistake that dilutes the effective dose to the actual target.
Get the Full Details
Consistency beats intensity here. People who see actual improvement tend to do shorter daily sessions rather than occasional long ones. The cellular mechanisms involved — mitochondrial cytochrome c oxidase activation, ATP production increases, modulation of reactive oxygen species — these are cumulative processes. Skipping days sets you back more than a missed session costs you in lost time. The limitations are worth stating plainly. There is no large-scale clinical trial data confirming that red light therapy alone resolves Bell's Palsy. Most of what exists are small case series and anecdotal reports. Some people recover fully with standard steroid treatment and never need anything else. Others recover partially and add light therapy as an adjunct, which makes it hard to isolate whether the light contributed meaningfully to the outcome. The placebo effect in facial nerve recovery is significant because any improvement feels dramatic when you've been struggling to make basic expressions. If you decide to try this, start with a device that has published spectral output data. Don't buy something based on the number of LEDs alone. Check what wavelength each diode actually emits. Many cheap panels claim 660nm but their actual peak output is closer to 630nm or varies across the array. That inconsistency means some zones get different doses than others, which matters when you're dealing with a narrow target area like the facial nerve pathway.
Protect your eyes during treatment. Even though red and near-infrared light isn't ionizing radiation, sitting six inches from a high-output panel for extended periods isn't something you want to do with unprotected eyes. Simple tinted goggles or just keeping your eyes closed during the session is sufficient. The retina can handle diffuse ambient light but direct high-intensity exposure isn't worth the risk. Track your progress objectively. Take dated photos front-on and in profile every three to four days. Compare eyebrow position, mouth corner symmetry, and ability to close each eye. Subjective assessment during recovery is unreliable because you adapt to gradual changes without noticing them day to day. Visual documentation removes that bias and gives you a clearer picture of whether the protocol is actually moving the needle.




