What Actually Happens When You Use Red Light on Bone
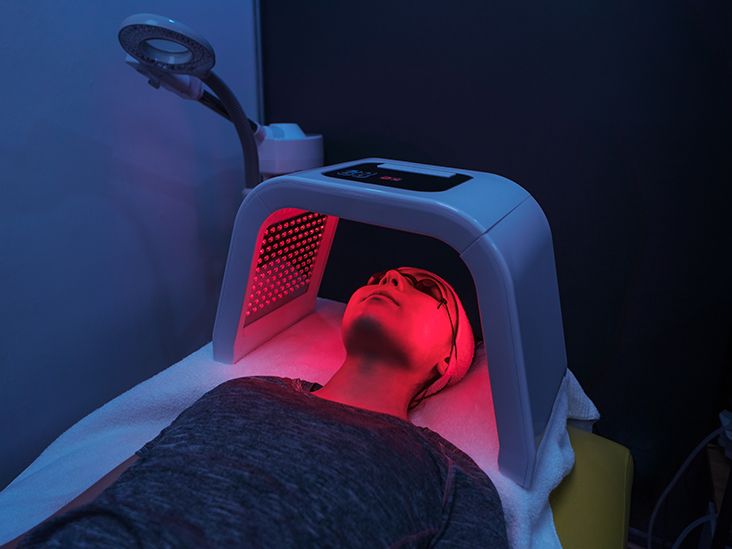
Most people come to this thinking it's some kind of bone-building machine. It isn't. What it does is stimulate mitochondrial activity in osteoblasts — the cells responsible for building bone tissue. The primary wavelength that matters is around 660nm red light and 810-850nm near-infrared. The NIR penetrates deeper, which is why you'll see protocols that combine both. A typical session for someone dealing with osteopenia or early osteoporosis involves 10-20 minutes per area, usually the spine and hips if you're targeting the most fracture-prone sites. You're not going to get results from once-a-week sessions. The studies that show actual changes in bone mineral density run over 12 to 24 weeks minimum, with treatment happening three to five times per week. Here's the thing nobody puts in the marketing materials: the light needs to actually reach the bone. If you're overweight or have significant soft tissue over the target area, a lot of that energy gets absorbed before it ever gets to the periosteum. I had a client — mid-sixties, postmenopausal, working on lumbar spine density — who was using a $400 panel at arm's length and seeing zero improvement on her DEXA scans after six months. She was frustrated to the point of quitting. The problem wasn't the device, it was the protocol. She was lying face-down on her stomach with the panel above her lower back, but she had a substantial amount of adipose tissue in that area and the panel was too far away. The irradiance at her skin surface was probably around 8-10 mW/cm², nowhere near what the literature suggests is effective for penetration. We moved her to a higher-powered panel, got her within six inches of the target area, added NIR-dominant wavelengths, and switched to four sessions per week instead of two. Her next scan showed a small but real uptick. Took about five months to show up on paper.
How to Approach Red Light Therapy For Bone Density Properly
You need a panel that delivers meaningful irradiance at your treatment distance. Cheap LED strips from Amazon won't cut it — they're rated at maybe 20-30 mW/cm² at best and that's at one inch from the source. By the time you factor in distance and tissue absorption, you're down to barely anything by the time it reaches bone. Look for panels that publish their irradiance data at specific distances. A good target is 50-100 mW/cm² at the skin surface for the red wavelengths, and you want NIR output in the 30-60 mW/cm² range. Dual-emitter panels that combine 660nm and 850nm are the standard recommendation. Positioning matters more than people think. For spinal density, you want anterior and posterior coverage — front and back of the torso. The vertebral bodies are roughly two to four centimeters beneath the skin surface depending on your body composition, so NIR is non-negotiable. Red light alone won't reach them effectively. For hip and femoral neck coverage, you'd want lateral positioning as well. Treat each area for 10-15 minutes per side, two to three times per day if your protocol allows it, or do longer sessions three to four times per week. Consistency is what separates the people who see results from the ones who don't. There's a timing component that's easy to overlook. Some research suggests treating in the evening might be slightly more effective because osteoblast activity follows a circadian rhythm, peaking at certain times. I don't think this is a dealbreaker, but if you're already doing everything else right and still wondering why progress is slow, consider when you're scheduling your sessions. Also, avoid treating immediately after high-impact exercise on the same area — you want the bones under mechanical load on a separate schedule, not competing for the same recovery window.
What the Evidence Actually Says and Where It Falls Short
The 2018 study from the Journal of Clinical and Aesthetic Dermatology looked at postmenopausal women with osteopenia using 660nm and 850nm light five times per week for 16 weeks. They saw statistically significant improvements in bone mineral density at the lumbar spine and femoral neck. Other studies have been less consistent. Some show no meaningful change. The variance comes down to device quality, dosing, treatment duration, and the baseline health of the participants. This isn't a universal fix, and it's definitely not going to reverse established osteoporosis on its own. The main limitation is that red light therapy for bone density is best understood as an adjunct, not a standalone treatment. If you're dealing with actual osteoporosis, you need pharmaceutical intervention alongside whatever supportive measures you can add. For someone with osteopenia or early-stage bone loss, it can be a reasonable addition to weight-bearing exercise, adequate calcium and vitamin D intake, and proper protein consumption. The mechanism is real — cyclic AMP upregulation, increased ATP production in osteoblasts, enhanced collagen synthesis — but the magnitude of effect is modest. Don't expect it to replace a resistance training program or proper nutrition. Another practical issue: most consumer devices are underpowered. The studies use clinical-grade equipment with known output specifications. A $200 panel claiming "medical-grade" output often delivers a fraction of what was used in research. Check the specs, ask for third-party testing if possible, and don't trust marketing copy. If a company won't tell you the irradiance at a specific distance, that's a red flag. You should also be aware that eye protection is necessary for the red light portion, though NIR at these intensities is generally considered safe for the eyes. Still, I'd recommend goggles regardless — long-term retinal exposure to intense red wavelengths hasn't been studied nearly as thoroughly as people assume.
Get the Full Details

The biggest misconception is that more is better. There's a biphasic dose response, meaning both under-dosing and over-dosing can be ineffective. Too much light can actually inhibit osteoblast activity rather than stimulate it. The sweet spot for most people is around 4-10 J/cm² per treatment area. That translates to roughly 10-20 minutes at a typical panel output. Going from 20 minutes to 40 minutes won't double your results — it might cancel them out entirely. Start conservative, track your progress with periodic DEXA scans if you can, and adjust from there. It's a slow process, measured in months not weeks, and the people who stick with it consistently are the ones who see anything happen.