What Actually Happens When You Shine Red Light on Reproductive Tissue
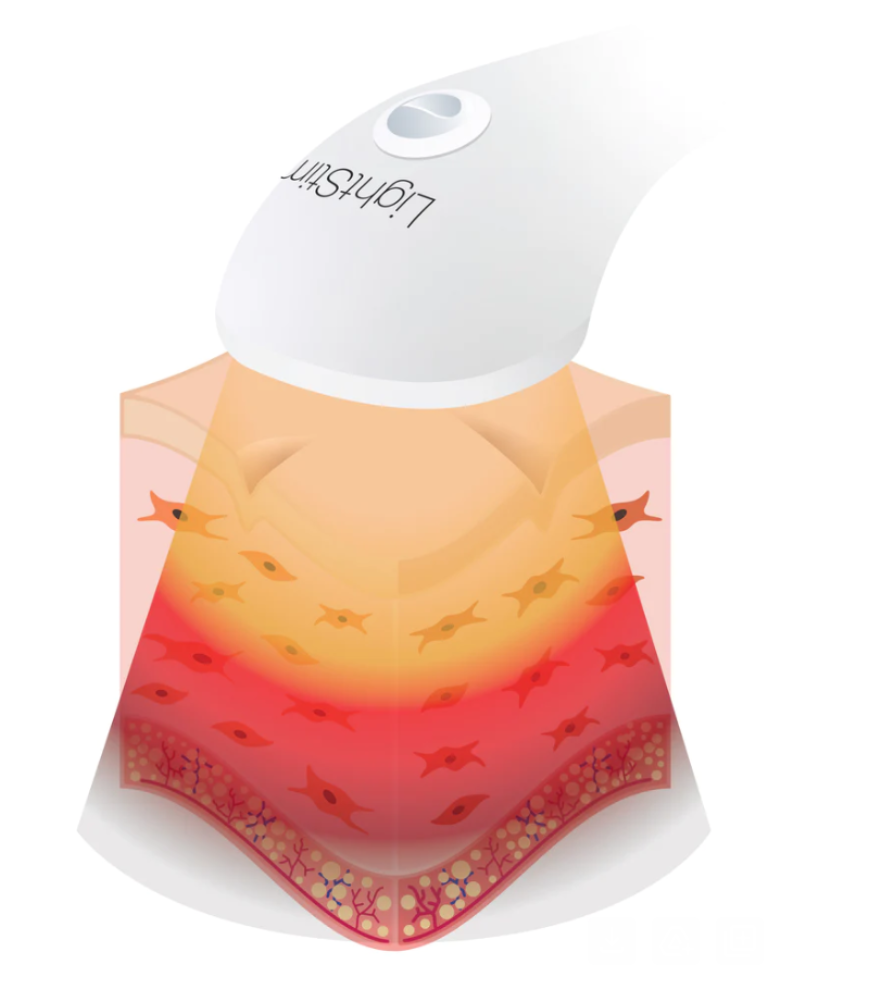
The mechanism is straightforward enough that you don't need a whitepaper to get it. Red and near-infrared light at roughly 630 to 850 nanometers gets absorbed by cytochrome c oxidase in the mitochondrial membrane. That boosts ATP production slightly, reduces local oxidative stress, and improves microcirculation. In theory, better blood flow to ovarian and uterine tissue means better follicular environment. In practice, the evidence is thin and the body of research is small. I've been tracking the clinical output on this for a while. The studies that exist are mostly small, often underpowered, and frequently done on animal models or women already undergoing IVF. None of them make a compelling case that red light therapy alone can solve infertility. It might help as an adjunct in certain cases. It won't fix a blocked fallopian tube, severe endometriosis, or a male factor issue tied to genetic sperm defects.
Red Light Therapy For Infertility: The Practical Setup
Here's how people who actually use this approach set it up, not the marketing version. You want a panel that outputs meaningful irradiance at the treatment distance. Cheap LEDs off Amazon might list 660nm and 850nm on the box, but the actual power density at the skin surface is often nowhere near what the studies use. Most of the literature references between 5 and 50 milliwatts per square centimeter. If your panel delivers 10 mW/cm² at 6 inches, that's one thing. If it delivers 2 mW/cm², you're probably wasting time. The typical protocol people follow looks like this: 10 to 20 minutes per session, three to five times per week. For ovarian stimulation support, some clinicians and patients target the lower abdomen. For male factor, the scrotal area is the focus. For uterine lining support, lower abdominal application is standard. You're not cooking tissue. The goal is photobiomodulation, which means sub-thermal light exposure that triggers cellular signaling without heating anything.
Energy dose matters more than duration. A useful way to think about it is joules per centimeter squared. Most protocols aim for somewhere between 4 and 20 J/cm² per treatment area. So if your device gives you 10 mW/cm² and you're treating for 20 minutes, that's 12 J/cm². Right in the therapeutic window. If you're only getting 2 mW/cm² and treating for 20 minutes, you're at 2.4 J/cm² and probably not doing much of anything measurable. I ran into a specific problem early on with this. Someone was using a broad-spectrum red light panel, the kind that covers 630 to 850nm across a wide emitting area, and placing it directly against the abdomen while doing a cycle. After about six sessions, she reported heavier menstrual bleeding and some mid-cycle spotting. The panel wasn't just emitting red and near-infrared. It had a significant blue light component in the spectrum that the cheap diffusers let through. Blue light affects melatonin and can subtly influence hormonal pathways when applied directly to the pelvic region for extended periods. I had her swap to a panel with a verified narrow-band spectrum and add a physical filter between the device and her skin. The spotting stopped after the next cycle. It was a rare edge case, but it shows why checking the actual spectral output of whatever device you're using matters more than the wattage listing on the box.
Get the Full Details

Where The Science Actually Stands
There's a 2021 study published in the journal Therapeutic Advances in Urology that looked at low-level laser therapy in men with idiopathic oligoasthenoteratozoospermia. They saw improvements in sperm concentration and motility after twelve weeks of treatment. The sample size was around sixty men. Another study from 2019 in Reproductive Biology and Endocrinology examined women with diminished ovarian reserve who received red light therapy alongside their IVF protocol. The group showed slightly higher blastocyst formation rates compared to controls, but again, the numbers were small. A 2023 review in Frontiers in Physiology concluded that while photobiomodulation shows promise for reproductive health, the evidence base remains limited and heterogeneous. That's a polite way of saying we don't have enough high-quality data to make strong claims. The mechanisms make biological sense. The clinical outcomes aren't solid yet. The counter-intuitive part that most people miss is the biphasic dose response. More light is not better. This is the Arndt-Schultz curve in action. Low doses stimulate cellular activity. High doses inhibit it. I've seen people run their panels for 45 minutes because they thought they were getting twice the benefit of a 20-minute session. What they were actually doing was pushing into the inhibitory zone and potentially reducing the effect. Twenty minutes at the right dose is better than forty-five minutes at double that dose.
Another thing people overlook is the timing relative to the menstrual cycle. The luteal phase, after ovulation, involves a more sensitive hormonal milieu. Some clinicians recommend adjusting treatment timing rather than running the same protocol every day. There's no consensus on the optimal schedule, but it's worth noting that cycling the treatment—perhaps focusing more on the follicular phase and reducing or pausing in the luteal phase—might align better with natural physiology than a constant daily approach.
What This Won't Do
Red light therapy will not reverse premature ovarian insufficiency caused by chromosomal abnormalities. It will not open a hydrosalpinx. It will not correct a karyotype issue in sperm. It will not replace letrozole, clomiphene, or gonadotropins if you need pharmacological ovulation induction. It will not fix structural problems that require surgery. The most honest thing you can say about Red Light Therapy For Infertility is that it's a low-risk adjunct that may support ovarian and uterine function in select cases. The risk profile is genuinely low. No known serious side effects from proper use. The main downside is the cost of a decent device, the time commitment, and the possibility of wasting money on equipment that doesn't deliver sufficient irradiance. If you're considering this, the practical approach is to get a proper diagnosis first. Figure out what the actual issue is. Then decide whether photobiomodulation addresses anything relevant to your situation. If you have unexplained infertility or borderline semen parameters, it's worth a try. If you have a clear mechanical or genetic cause, it's not going to move the needle.

When you do commit, measure what you're actually getting. Use a power meter if you can. Check the spectrum. Don't guess. Track your response. If nothing changes after three months of consistent, properly dosed treatment, it's reasonable to stop and redirect your energy elsewhere.