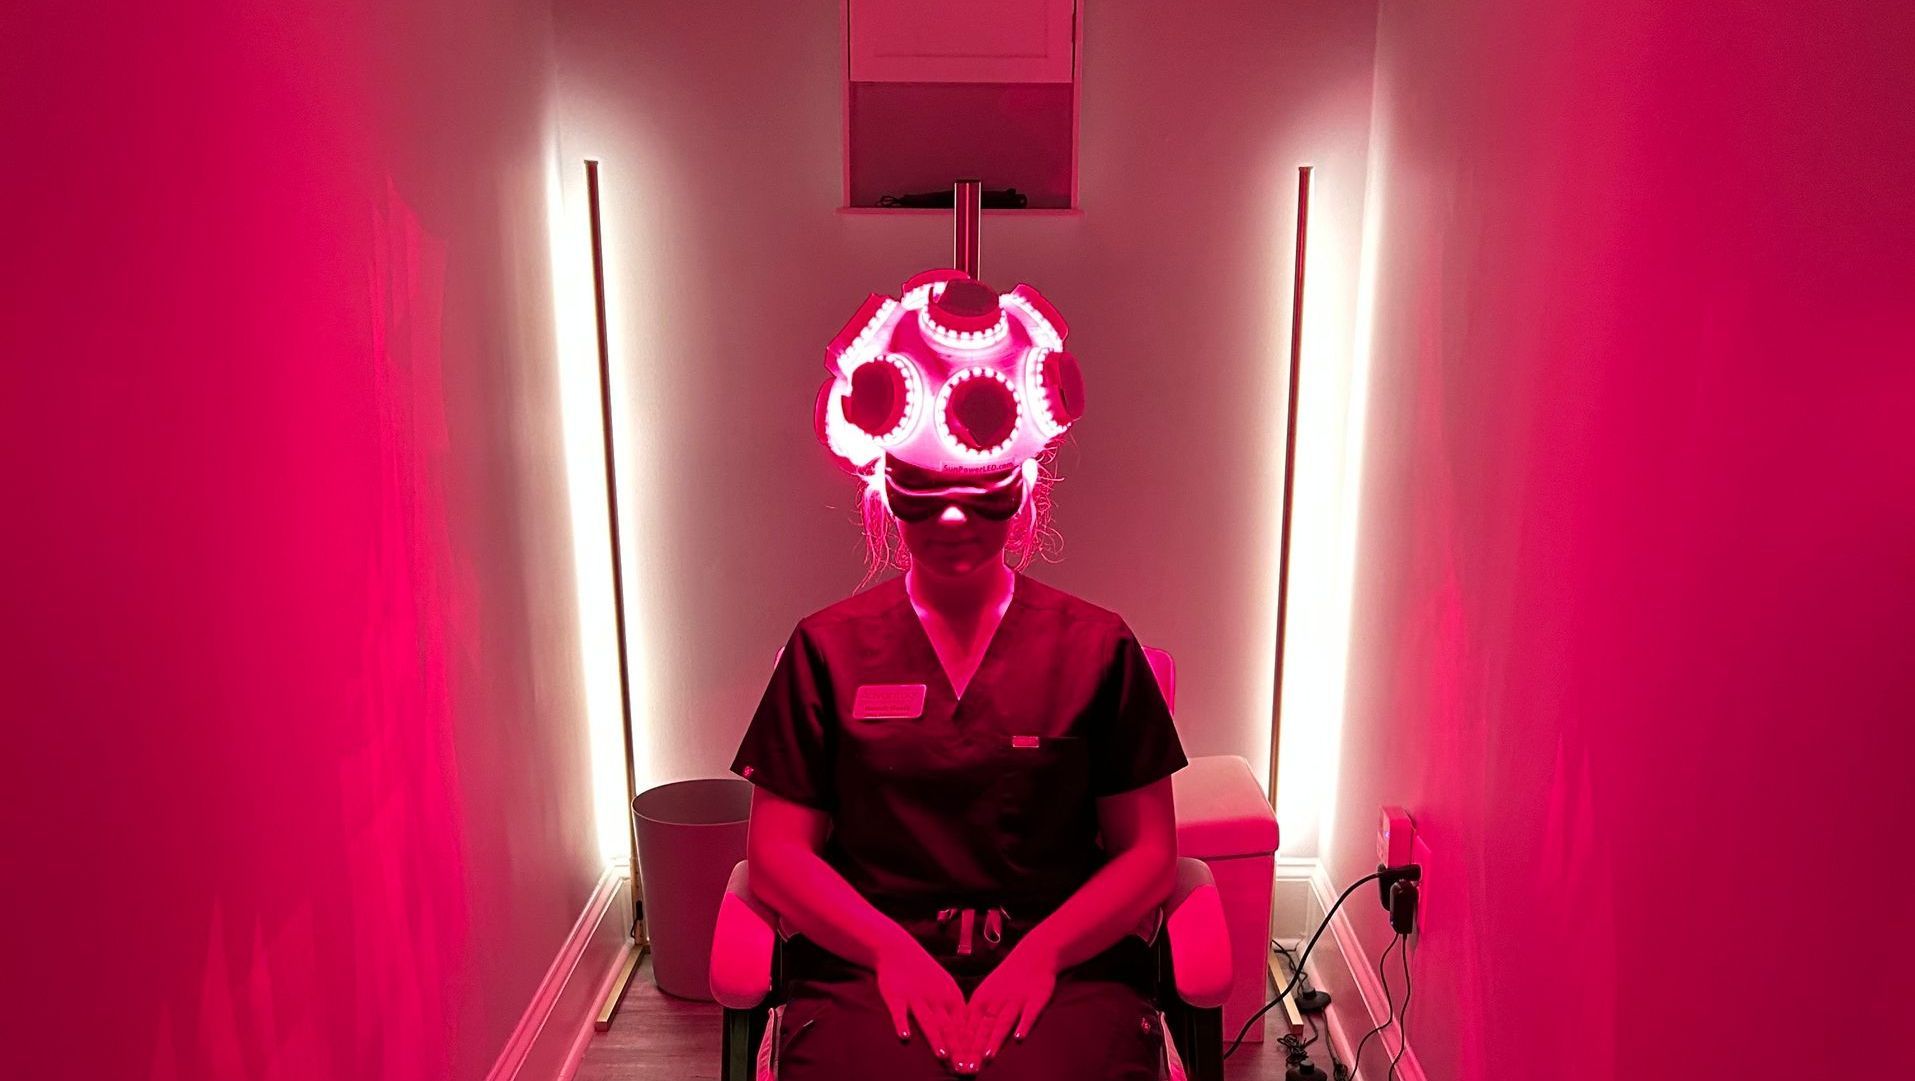
How I Use Red Light Therapy For Migraines
I set my panel about 12 inches from my face, run it for eight minutes, and rest. That's the whole routine. It doesn't work for every migraine. Some weeks it does almost nothing. Other times it cuts a bad episode down to half the usual duration. I've been running this protocol on and off for about four years now, usually when my headaches start with that vague behind-the-eyes pressure instead of the full throbbing. Most cheap panels on Amazon list 660nm red and 850nm near-infrared. Those numbers are correct for what you want. The red light at 660nm stays mostly in the superficial layers — skin, the upper blood vessels. The 850nm near-infrared goes deeper, into muscle and nerve tissue. For migraines, you're really targeting vascular reactivity and mitochondrial function in the perivascular tissue around the trigeminal nerve. Both wavelengths contribute, but 850nm does most of the heavy lifting for neurological migraines specifically. Some cheaper devices only emit red light. Those can still help if your migraines feel more tension-related, but if you have true vascular migraines with aura, skipping near-infrared means you're leaving about half the therapeutic effect on the table.
How Dosage Actually Works
Dosage in red light therapy is measured in joules per square centimeter. You need roughly 4 to 10 J/cm² per treatment area for migraine relief. A typical panel puts out between 20 and 60 milliwatts per square centimeter at a 12-inch distance. Do the math: at 40 mW/cm², reaching 6 J/cm² takes about 250 seconds, or just over four minutes. That's why I run mine for eight minutes — I'm covering both sides of my head and pushing a slightly higher dose because my panel runs closer to the lower end of the output range. The mistake most people make is treating distance as the main control knob. Moving from 12 inches to 24 inches drops your irradiance by roughly 75 percent because of the inverse square law. So a panel that delivers 40 mW/cm² at 12 inches is only pushing about 10 mW/cm² at 24 inches. You'd need to stay on for 20 minutes to get the same dose, and even then the light spreads wider and becomes less concentrated where you actually need it. Keep the panel close. minutes beats twenty poorly aimed ones.
What It Feels Like During a Session
Nothing. That's the point. You won't feel heat. You won't feel anything at all with 850nm near-infrared since it's invisible. The red 660nm light will look bright, but it won't warm your skin the way a heat lamp would. Sit there, eyes closed or looking away from the panel, and let it run. Some people get a mild tingling behind the eyes during a session — that's not a sign it's working or not working, it's just a random nerve response. I ignore it. I position the panel so the light covers both temples and the back of my head where the occipital nerve exits. That's roughly a 20 by 10 inch area on my skull. I keep it at 12 inches. I run it for eight minutes. I do this once daily during a flare-up, usually in the afternoon when my migraines tend to peak. If I catch it early enough — during the prodrome phase, that weird pre-headache window where I feel off but the pain hasn't started yet — I sometimes prevent the migraine entirely. That happens probably two out of ten times. The other eight, it shortens and softens the episode. I don't use it for prevention on days when I'm migraine-free. There's no point to treating tissue that isn't currently inflamed. I reserve it for active episodes only.
Get the Full Details

One Thing I Learned the Hard Way
Early on I bought a smaller handheld near-infrared device, the kind that looks like a flashlight. I figured I could just point it at specific trigger points along my jaw and neck. That approach was a failure. The active area on those devices is tiny — maybe two square centimeters — and the power density drops off fast once you move it around. I spent 20 minutes trying different spots and got less benefit than the eight minutes with the full panel. Stick with a panel. The broader the treated area, the better the result for migraines specifically. Cytochrome c oxidase is the primary chromophore — the molecule that absorbs the light — in red and near-infrared therapy. When 660nm and 850nm photons hit this enzyme in your mitochondria, it increases ATP production and modulates nitric oxide release. Nitric oxide is a vasodilator, and in migraines, abnormal vasodilation and constriction of cranial blood vessels is one of the main drivers of the pain. The light helps stabilize that vascular reactivity. There's also an anti-inflammatory effect. Red light therapy reduces levels of inflammatory cytokines like TNF-alpha and IL-1beta in the surrounding tissue. For migraines, which involve neurogenic inflammation around the trigeminal nerve, that reduction matters more than people realize. It's not just about blood vessels. It's about the entire inflammatory cascade around the nerve endings.
Research is still preliminary but encouraging. A 2020 study published in Headache found that transcranial near-infrared photobiomodulation reduced migraine frequency by about 50 percent in the treatment group over eight weeks compared to sham. Another study in the Journal of Clinical and Aesthetic Dermatology looked at red and near-infrared light applied to the neck and shoulders and saw significant reductions in both pain intensity and medication use. These aren't massive studies. The sample sizes are small. But the signal is consistent enough that I've kept using it regularly.
Common Pitfalls That Make People Quit Too Early
Most people who try red light therapy for migraines and give up did one of three things wrong. First, they used a device that only emits red light and expected deep tissue results. Second, they held the device too far away and wasted 20 minutes getting a fraction of the needed dose. Third, they expected it to work like a painkiller — immediate relief within minutes. It doesn't. The biological effects take time to accumulate. Most people need to use it for at least two to three weeks before they can judge whether it helps them at all. Another issue I see people run into: using it during an established severe migraine with full aura and vomiting. By that point, the inflammatory cascade is already well underway. Red light therapy works best when applied early. If you're already in the thick of it, the effect will be weaker. This is why catching it during prodrome is ideal, even though prodrome symptoms can be subtle and easy to miss.

Limitations and When It Won't Help
Red light therapy won't stop a migraine that's already at peak intensity. It's not a abortive treatment like triptans. Don't confuse it with one. It's a modulatory tool — it changes the environment around the migraine, makes it less likely to escalate, and shortens the duration if it does escalate. The difference matters. It also doesn't work for everyone. I've seen people report zero benefit. If you try it consistently for three weeks and notice no change, it's fine to stop. There's no harm in stopping. But give it a fair shot first. There's a specific edge case I ran into that I haven't seen discussed much: if you have cervical spine issues — my disc problems in the upper neck go back years — placing the panel too low or at a sharp angle can actually aggravate the neck muscles while treating the head. I learned this the hard way after a session left my trapezius tighter than usual. The fix was simple: adjust the angle so the light comes from slightly above and in front, not from below. My neck stays relaxed and the light still hits the target zones effectively.
If your migraines are primarily triggered by eye strain or screen time, combining red light therapy with proper blue light filtering during the day might give you better results than the therapy alone. I do both. The light therapy handles the vascular and inflammatory component, and the blue light filtering addresses the trigger. Together they're more useful than either alone.
A Word on Device Selection
You don't need an expensive medical-grade panel. I use a unit that cost about $150 and it does the job. What matters more than price is whether the device actually outputs the wavelengths you need. Check the specifications. If it doesn't list 660nm red and 850nm near-infrared specifically, skip it. Generic listings that just say "red light" and "infrared" without wavelength numbers are usually filler marketing. Look for third-party test reports or at least a clear spec sheet from the manufacturer. Irradiance numbers matter too — if a device lists output at the source but not at a practical distance, it's probably inflated. Some panels come with pulsed near-infrared options. I tried pulsing for a while — some research suggests pulsing at 10Hz can be more effective for neurological conditions — but I went back to continuous wave. The difference was negligible for my use case, and continuous is simpler to manage. If you have a panel with a pulse option, try it for a week. If you notice no difference, stick with continuous. The bottom line is that Red Light Therapy For Migraines is a real tool with real limitations. It won't cure you. It won't work every time. But for the right person using it correctly, it can meaningfully reduce the frequency and severity of episodes. The protocol is straightforward. The science is reasonable. The main obstacle is patience — giving it enough time and using it with proper technique before deciding whether it helps.