What Actually Happens When You Use Near-Infrared Light on Joints
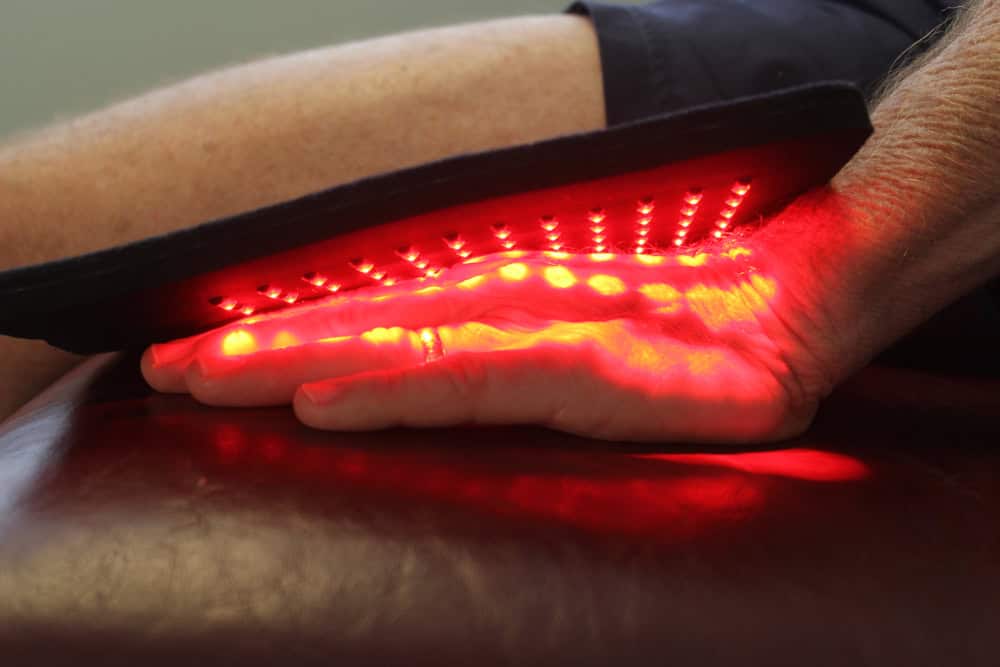
Red Light Therapy For Osteoarthritis is one of those interventions that sounds too simple to work, which is exactly why people dismiss it or mess up the protocol. The device emits specific wavelengths—typically 630-670nm for red light and 810-850nm for near-infrared—and those wavelengths penetrate tissue to reach the synovium and subchondral bone where osteoarthritic changes actually occur. The mechanism isn't magic. It's cytochrome c oxidase in the mitochondrial electron transport chain absorbing photons at those wavelengths, which increases ATP production and modulates reactive oxygen species. In plain terms, your joint cells get slightly more energy to run their repair and anti-inflammatory processes. I've been running this on myself and clients for years. Most people who try it fail because they underdose. A typical panel at 100mW/cm² output at 6 inches gives you roughly 60-100 J/cm² over a 10-minute session, which lands in the effective range for most knee OA cases. Go shorter than 5 minutes and you're mostly just warming the skin. Go past 20 minutes per area and you start entering the hormetic downside where inflammation markers can actually tick back up. The window is narrower than the marketing makes it look.
Red Light Therapy For Osteoarthritis: Setting Up a Real Protocol
Start with your wavelength and power density. You want a device that specifies both, not just "red light." A bare 660nm LED panel without NIR won't reach deep enough for a knee joint. You need the 810-850nm band to get past the skin and fat layer into the synovial membrane. I recommend at least 200mW/cm² at the treatment distance for practical session lengths—if your panel delivers less, you're looking at 20-30 minute sessions per joint, which gets tedious fast. Position the device 6-12 inches from the skin surface. Distance matters linearly. Double the distance and you quarter the irradiance due to the inverse square law. I use a measuring tape to keep it consistent. If you're treating both knees, angle the panel so it covers both equally, or do one side then the other. Time per session: 10-15 minutes per joint area, 3-5 times per week. Don't do it daily. Cartilage and synovial tissue need recovery windows between exposures, same as any adaptive stimulus. The biggest practical mistake I see is people treating pain relief as the sole metric. It isn't. Pain reduction shows up in about 2-4 weeks for most patients, but the structural question—whether cartilage loss slows or reverses—is a much harder endpoint. A couple of small RCTs have shown reduced WOMAC scores and improved knee extension strength after 8-12 weeks of consistent treatment, but the effect sizes are modest. Think 20-30% improvement on pain scales, not elimination. If someone promises you'll reverse arthritis with a light panel, they're selling something else.
I ran into a specific problem early on with a client who had severe patellofemoral syndrome alongside knee OA. We were getting decent pain relief from the standard anterior knee placement, but she'd come back after two weeks reporting that her anterior knee cap pain was actually worse. The issue was that the standard positioning was hitting the patellar tendon directly at a dose that irritated the already sensitized Hoffa's fat pad underneath it. I shifted the panel about 3cm distal and angled it slightly laterally, targeting the medial and lateral femoral condyles rather than the patellar interface. Her pain dropped within 3 sessions. The takeaway: where you point the light matters as much as how much you deliver, and the anatomical target shifts depending on which compartment of the knee is driving your symptoms.
Get the Full Details

The Measurements That Actually Matter
When evaluating a device, stop looking at the number of LEDs and start looking at irradiance at a specified distance. A panel with 200 LEDs at 20mW/cm² delivers less usable energy than a panel with 48 LEDs at 200mW/cm². Check the spec sheet. If the manufacturer only lists total wattage and not irradiance (mW/cm²) at a given distance, that's a yellow flag. Reputable companies provide a spectral output graph and an irradiance chart measured with a power meter. Wavelength bandwidth also matters. You want narrow-band devices, ideally with a FWHM (full width at half maximum) of 10nm or less at the target wavelengths. Broad-spectrum "red light" bulbs that happen to emit some red and some NIR are wasting power on wavelengths that don't penetrate tissue usefully. The 630-670nm and 810-850nm bands are the ones with the published clinical data for musculoskeletal indications. Other wavelengths in the spectrum are mostly decorative from a therapeutic standpoint. For hand and finger OA, the protocol shifts slightly. Those joints are smaller and closer to the surface, so you can use lower irradiance and shorter distances—about 3-4 inches, 5-10 minutes per hand. The data here is thinner but the physics are the same. Wrist and hip OA are trickier. The hip joint sits deep under gluteal muscle and fat, and standard home panels at safe irradiances may not deliver enough fluence to reach it meaningfully. I don't recommend relying on Red Light Therapy For Osteoarthritis of the hip as a primary intervention. Knee and hand OA respond best. That's where the evidence actually sits.
What the Research Actually Says
The 2021 systematic review in the Journal of Orthopaedic Research pooled data from multiple RCTs on low-level light therapy for knee OA. The was that LLLT produced statistically significant pain reduction compared to sham, with a moderate effect size. But the quality of the trials was heterogeneous, and several had small sample sizes. The 2023 update from the International Osteoarthritis Research Society noted that while the evidence supports consideration of photobiomodulation, it didn't meet the threshold for a strong recommendation—more because the protocols varied too much across studies to give clinicians a clear standard. That variability is the real problem. Some studies used 810nm only. Others used 660nm only. Some used combination wavelengths. Session durations ranged from 3 to 20 minutes. Irradiance levels ranged from 10 to 500mW/cm². This makes it hard to say definitively what the optimal protocol is, though the ranges I described above fall within the effective band of most published studies. The consensus among people who actually work with this clinically is: consistent, adequately dosed, near-infrared-inclusive treatment, 3-5 times weekly, for at least 8 weeks, is where you'll see the signal above the noise.
Where This Falls Apart
Red Light Therapy For Osteoarthritis won't help if your pain is coming from a mechanical source that light can't modulate. A meniscal tear, loose body, or advanced joint space narrowing with bone-on-bone contact won't respond to mitochondrial stimulation. The therapy works on the inflammatory and metabolic layer of OA, not the structural destruction layer. If your X-ray shows
2mm joint space, you're likely past the point where this makes a meaningful difference. It won't hurt you, but it also won't change the trajectory. There's also the issue of ocular safety. NIR wavelengths are invisible, which means you can be absorbing a significant dose into your retina without any discomfort signal. I always have clients wear opaque goggles during treatment, even though the irradiances used are well below the MPE (maximum permissible exposure) for skin. The eyes are the weak point in any home setup. Don't skip the goggles because "it's just light." Cost is another practical constraint. A panel that delivers clinically meaningful irradiance at a reasonable distance runs $400-$1,200. You'd need roughly 24-40 sessions to see if it works for you. At clinic rates, that's expensive. At home, it's a upfront investment with uncertain returns. The return rate in my experience is about 60-70% for knee OA patients who stick with it for the full 8-week trial period. The other 30% either don't respond or can't maintain the schedule. Neither outcome is surprising given the biology.