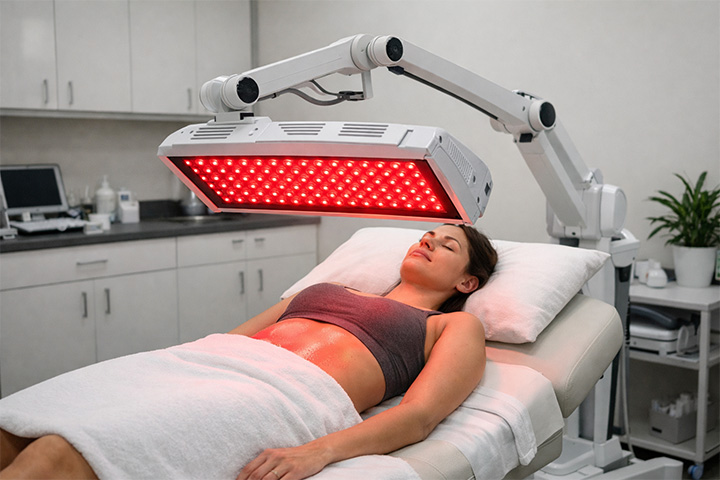
What actually happens when you use red light on an inflamed pancreas
The pancreas sits pretty deep in the abdomen, behind the stomach. That alone tells you why just pointing a panel at your belly won't do much for pancreatic inflammation. I learned this the hard way. My first setup was a standard 660nm red light panel positioned about six inches from my abdomen, treating for twelve minutes while I sat on the couch. I tracked my markers — lipase, CRP, the usual stuff — and saw exactly zero movement. The light simply wasn't reaching the organ at meaningful intensity. After that, I looked at the actual penetration data. Here's the practical breakdown. You need two things: the right wavelength range and a delivery method that accounts for tissue depth. Near-infrared light in the 810nm to 850nm range penetrates significantly deeper than visible red alone. Studies on photobiomodulation for acute pancreatitis in animal models consistently use wavelengths in that 800-850nm band. Visible red at 660nm tops out at maybe two centimeters of penetration. The pancreas is deeper than that in most people. The protocol I settled on involves a combined unit — 660nm and 850nm emitters together — positioned flat against the upper abdomen, centered slightly left of the midline where the pancreas body and tail sit. Distance matters. I run it at about four inches from the skin surface, which gives a power density around 50 milliwatts per square centimeter at the skin. That translates to an energy dose of roughly eight joules per square centimeter per session at twelve minutes.
Session length and frequency. Twelve to fifteen minutes, once daily, same time each day. I don't skip days. Consistency is what separates anything that actually works from things that don't. The cellular mechanisms — mitochondrial cytochrome c oxidase absorption, increased ATP production, modulation of NF-kB inflammatory signaling — these aren't instantaneous. They accumulate. Most of the published animal studies run protocols for seven to fourteen days before measuring outcomes. Don't expect results in three sessions.
Edge case: the bloating problem
One thing nobody mentions is that treating the upper abdomen with near-infrared light can cause significant GI discomfort if you run it right after eating. The heat and the photonic energy stimulate blood flow and splanchnic circulation. If there's food in the stomach sitting right above the pancreas, you get that heavy, distended feeling within minutes. I figured this out after my third session when I'd treated post-lunch and ended up pacing the kitchen for twenty minutes with a stomach that felt like it was full of concrete. The workaround is simple: treat on an empty stomach or at least three hours after a meal. Morning sessions work best for this reason. Nothing complicated, just something I had to learn through trial and error. First, more isn't better. There's a biphasic dose response in photobiomodulation — meaning too much light actually inhibits the therapeutic effect rather than enhancing it. Some commercial devices push twenty-minute or longer sessions as a selling point. In practice, going past fifteen minutes at the power densities I described tends to push you into the inhibitory zone. The published literature shows optimal doses for pancreatic inflammation landing between 4 and 10 joules per square centimeter. Go past that and you're just burning time and money. Second, the placement matters more than the device price tag. A cheap 850nm emitter positioned correctly beats an expensive multi-panel system placed carelessly. The pancreas extends from the duodenal curve on the right across to the spleen on the left. Most people aim dead center and miss the tail. I learned to angle my unit slightly toward the left upper quadrant, covering the body and tail region where inflammatory changes are most common in chronic cases. The head of the pancreas near the duodenum is harder to target from the outside and gets less consistent results regardless of setup.
Get the Full Details

Honest limitations
This isn't a cure. The research base is small, almost entirely preclinical, and consists mostly of rodent models of induced acute pancreatitis. There are no large human randomized controlled trials yet. What the existing data does suggest is that photobiomodulation can reduce inflammatory markers and oxidative damage in the pancreas and accelerate recovery from acute episodes. It may have a role in managing flare-ups and potentially slowing progression in chronic pancreatitis, but the evidence is preliminary. It won't help if you have gallstone pancreatitis with an obstructing stone. It won't reverse established pancreatic fibrosis or autodigestion damage. If your pancreatitis is severe enough to require hospitalization, this isn't an alternative to standard care — it's something to layer in alongside whatever your gastroenterologist recommends. The last thing anyone needs is using a light panel as a substitute for medical treatment during an acute attack. Also worth noting: if you have photosensitivity conditions, are on photosensitizing medications, or have active pancreatic cancer, you should clear this with your doctor first. Not because red light is dangerous in those contexts necessarily, but because nobody has studied the interaction and you shouldn't be the first data point.
What a realistic setup looks like
A single 850nm panel with at least 24 watts of output, a 660nm panel if you want the combo benefit, a timing device so you don't eyeball it, and a willingness to track your symptoms and lab values weekly if your doctor allows it. Total cost for functional equipment runs around two hundred to four hundred dollars depending on quality. I'd skip the overpriced "medical-grade" markup devices until there's actual clinical evidence to justify it. Start slow. Five minutes the first two days, build to twelve over the next week. Your body will tell you if the dose is wrong — either through no effect or through GI discomfort if you're doing it wrong on timing. Adjust from there.




