How I Actually Set Up My Red Light Panel for Pelvic Floor Work
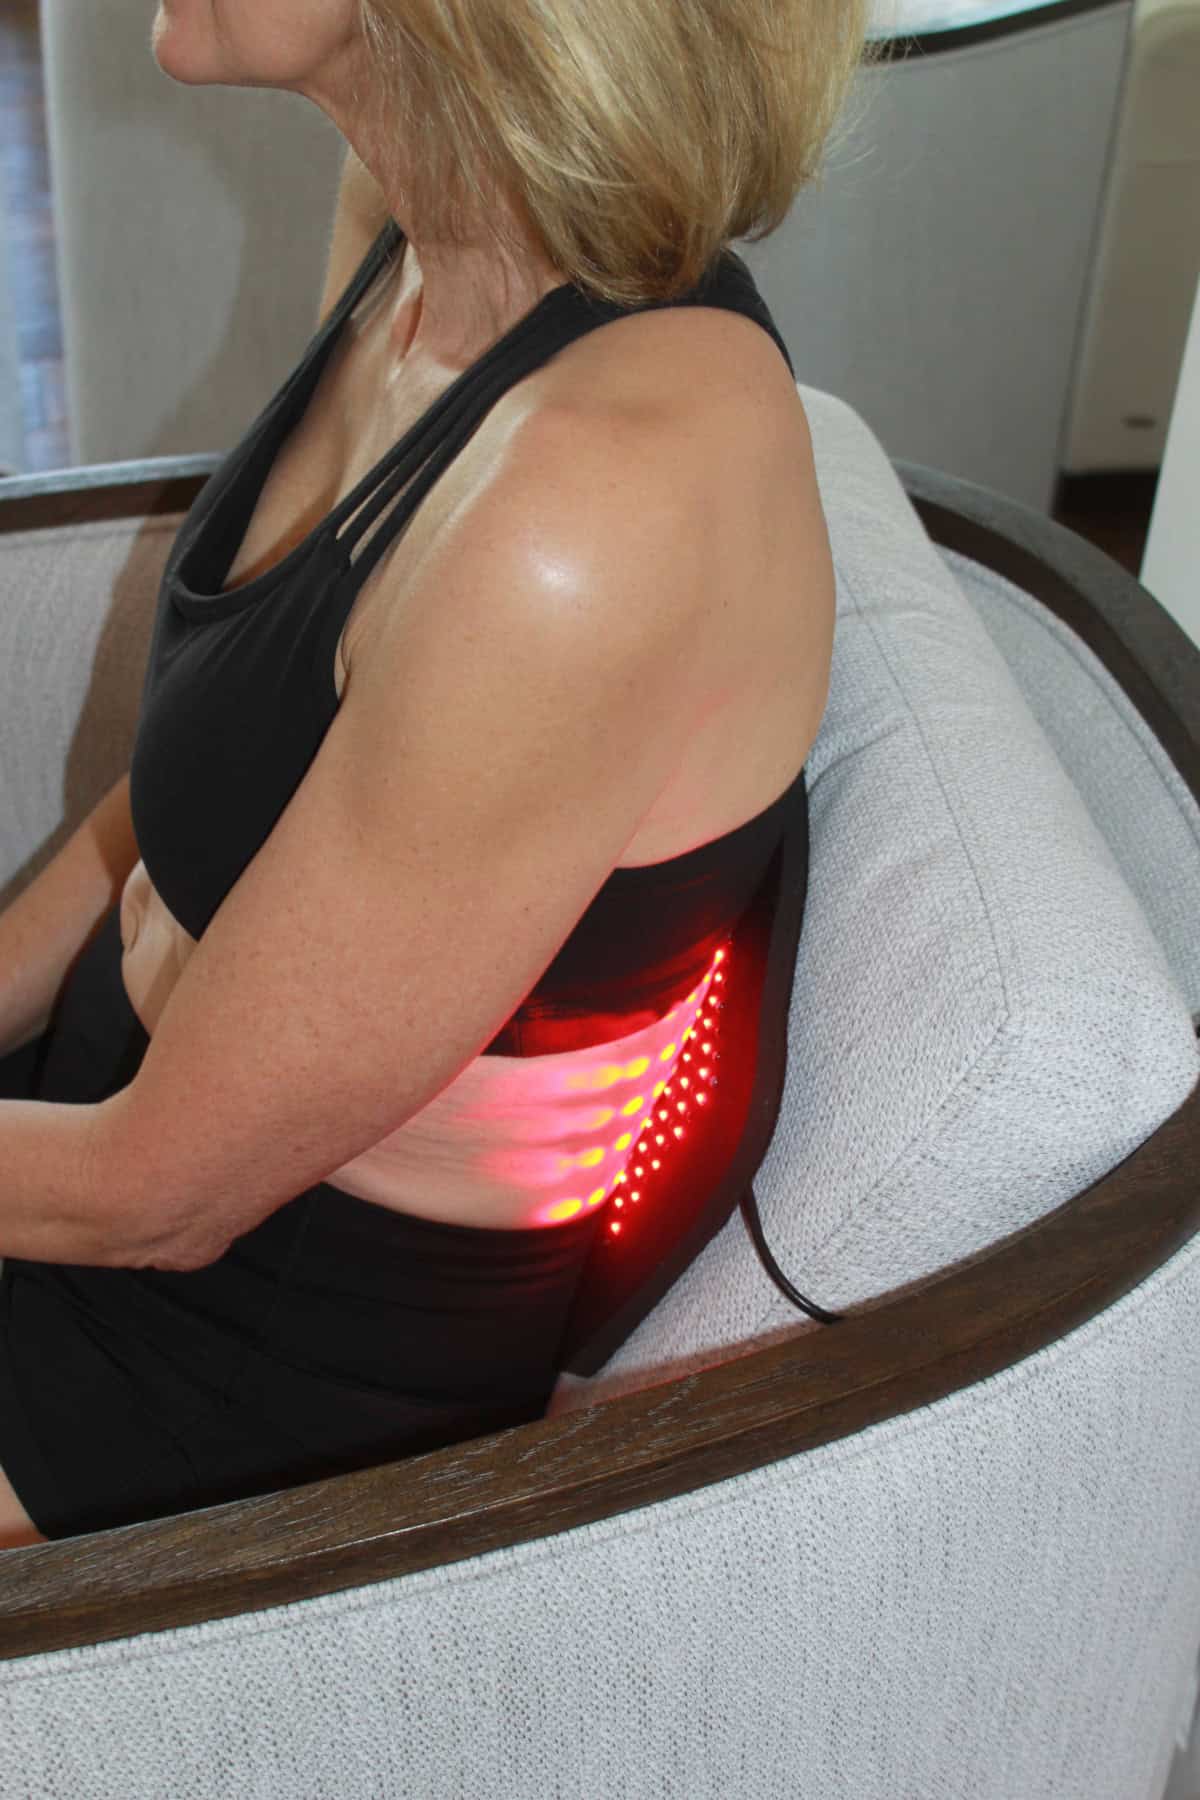
Most people buy a red light panel and just point it at their lower belly like it is a tanning bed. That mostly works for superficial tissue, but the pelvic floor sits pretty deep. I learned that the hard way after three months of doing nothing but heating my skin. The setup matters more than you think. I use a 660nm red wavelength combined with an 850nm near-infrared diode array, roughly 200 watts of total output, mounted on an adjustable arm so I can angle it under my lower pelvis rather than directly overhead. The angle lets the 850nm light penetrate through the abdominal wall without having to press the panel against your clothes or skin, which obviously would melt the plastic housing on most consumer units.
Red Light Therapy For Pelvic Floor: What Actually Happens
Here is the practical mechanism, stripped of the marketing language. 660nm red light gets absorbed by cytochrome c oxidase in your mitochondrial membrane, which nudges ATP production up locally. The 850nm near-infrared goes deeper, maybe two to three centimeters, and tends to affect vascular endothelial growth factor and nitric oxide release. Both of those pathways matter for pelvic floor tissue because chronic tension in that region often correlates with reduced microcirculation and a kind of low-grade ischemic fatigue in the levator ani complex. I know that sounds like a lot of jargon thrown at you, but the real takeaway is this: red light does not relax a hypertonic pelvic floor on contact the way heat from a hot pack does. It works slower, over weeks, by changing the metabolic environment of the tissue. You will not feel an immediate change. The first few sessions I did I thought I was wasting my time because nothing felt different. Then around week four I noticed I could hold a deeper squat without that familiar locking sensation in my perineum.
The Protocol I Actually Follow
I run about six to ten minutes per session, two to three times a week. Distance from the panel is roughly forty to fifty centimeters, which gives me an irradiance in the ballpark of forty to sixty milliwatts per square centimeter at the 660nm band. I do not exceed twelve minutes because after that point the diminishing returns kick in and the skin on my lower abdomen starts feeling dry and tight, which is annoying more than anything else. Timing matters less than consistency. I do it in the evening after work, mostly because that is when my pelvic floor feels most clenched from sitting all day. Some people prefer morning, and that works too, but if you pick a time you will actually stick to, do that instead of following someone else's schedule. One thing I forgot to mention at first: wear loose clothing or nothing below the waist during the session. I used to wear briefs and the fabric blocked a significant portion of the 850nm output. Switching to nothing cut my effective exposure time by maybe thirty percent because the light actually reached the tissue instead of heating cotton.
Get the Full Details

The Edge Case That Almost Made Me Quit
About six months in I hit a wall where the therapy seemed to stop helping. I had been dealing with a very specific issue: intermittent urinary urgency that flared up after long drives. I assumed red light would address it directly since urgency often traces back to pelvic floor overactivity, but it did not budged for weeks. What actually fixed it was combining the light therapy with daily diaphragmatic breathing drills before each session, not after. The breathing dropped my resting pelvic tone enough that the light could work on tissue that was no longer fighting against itself. I wish I had known that earlier. I need to be blunt about the limits here. Red light therapy for pelvic floor issues will not repair a pelvic organ prolapse. It will not fix stress incontinence caused by actual structural damage to the pubourethral ligament. It will not replace manual physical therapy if you have trigger points in your obturator internus or piriformis that need direct release. If your problem is neurological, like pelvic pain from pudendal neuralgia with actual nerve compression, this might help a little with circulation but it is not going to decompress the nerve. The best use case I have found is for chronic pelvic pain related to myofascial tension and poor local blood flow, especially in people who sit a lot and have never done targeted pelvic floor rehabilitation. Even then, it is a supporting tool, not a cure.
Buying Advice That Actually Helps
Do not buy the cheapest panel you find on a marketplace. I tried a sixty dollar unit that listed 660nm but measured closer to 630nm on a spectrometer app, and the penetration depth was noticeably worse. Look for a panel that provides independent irradiance data at both 660nm and 850nm, ideally from a third party. Mean Optical Power should be at least thirty mW/cm² at 660nm at your working distance. Anything below that is basically a fancy night light for tissue that needs real photon density. Also check the beam angle. A narrow beam gives higher irradiance but covers less area. A wide beam is gentler but spreads the photons thin. I settled on a panel with roughly a one hundred twenty degree spread because my pelvic floor area is wider than a single focused spot can cover comfortably.
Combined Approach That Works Better
The results I have seen consistently come from pairing red light with two other things: daily pelvic floor stretches like happy baby pose and child's pose held for two to three minutes, and magnesium glycinate supplementation at about two hundred milligrams before bed. The magnesium does not directly affect the pelvic floor in a dramatic way, but it helps with overall neuromuscular relaxation, which makes the light therapy more effective because the tissue is not in a constant state of sympathetic hold. I also stopped doing crunches and heavy deadlifts for a few months while I was running the light protocol. Those exercises tend to increase intra-abdominal pressure and push down on an already tense pelvic floor, essentially working against whatever the light was trying to improve. It felt weird to skip deadlifts, but the combination of reduced loading plus red light gave me faster relief than either one alone.
What to Expect Week by Week
Week one: probably nothing noticeable. Maybe a warming sensation during the session that fades within twenty minutes. Week two: some people report subtle changes in bowel movement comfort, others notice nothing. Week three to four: this is usually when I start seeing real shifts, especially around squat depth and perineal awareness. Month two onwards: the gains tend to plateau unless you adjust something, like increasing session frequency slightly or adding in the breathing drills I mentioned. If you are past month three with zero change, reassess your protocol. Check your distance, verify your panel's actual output, and consider whether your pelvic floor issue might have a structural component that light simply cannot address. In those cases, seeing a pelvic floor physical therapist is the move, not buying a second panel.