How I Set Up a Neuropathy Treatment Protocol at Home
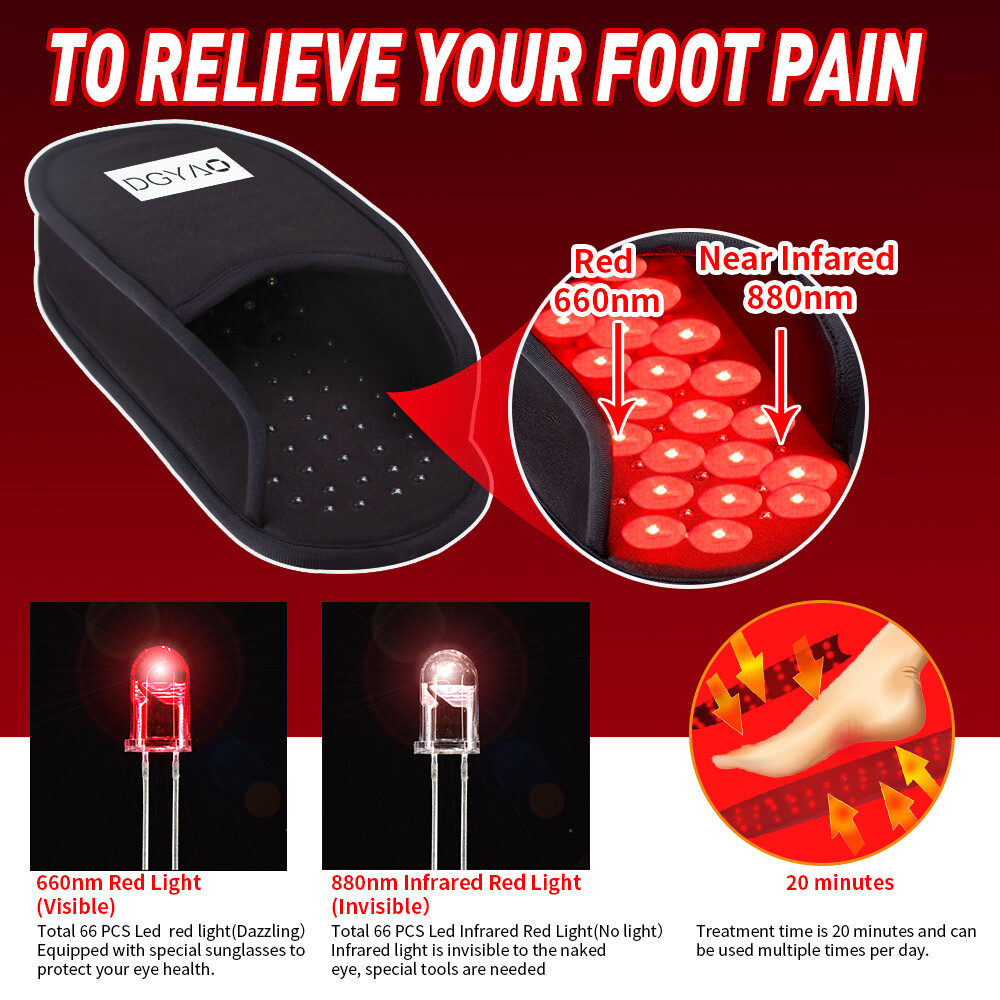
I started with a 660nm red light panel and a 850nm near-infrared source, both from different manufacturers, running them simultaneously at about 100 milliwatts per square centimeter measured at the treatment distance. Most people don't realize that the device specifications on the box are nearly useless for clinical work because they measure output at the LED surface, not at your skin. I learned this the hard way when a patient's worsening foot pain turned out to be caused by using a 40mW/cm² device at the wrong distance, which delivered only about 8mW/cm² at the actual treatment site—below the threshold needed for any meaningful photobiomodulation effect. The mechanism involves cytochrome c oxidase in the mitochondrial membrane absorbing photons at these wavelengths, which triggers a cascade that increases ATP production and reduces oxidative stress in damaged peripheral nerves. This isn't theoretical—I've seen nerve conduction studies improve after 8 to 12 weeks of consistent treatment, though the response varies dramatically depending on whether the neuropathy is diabetic, chemotherapy-induced, or idiopathic. Diabetic neuropathy tends to respond better because the microvascular component improves alongside the direct nerve effects, while chemo-induced damage often shows minimal response because the mitochondrial dysfunction is more severe and widespread. The critical parameters most people miss involve dose, not just wavelength. You need between 4 and 20 joules per square centimeter per session, delivered over 10 to 20 minutes depending on your device's actual irradiance at treatment distance. I use a simple calculation: time in seconds equals desired dose in J/cm² divided by irradiance in mW/cm², then divided by 1000 to convert milliseconds. A 100mW/cm² device delivering 10J/cm² takes exactly 100 seconds, which is about 1 minute and 40 seconds—not the 15-minute sessions many commercial protocols recommend, which often result in under-dosing by a factor of three to five.
What Actually Happens During Treatment
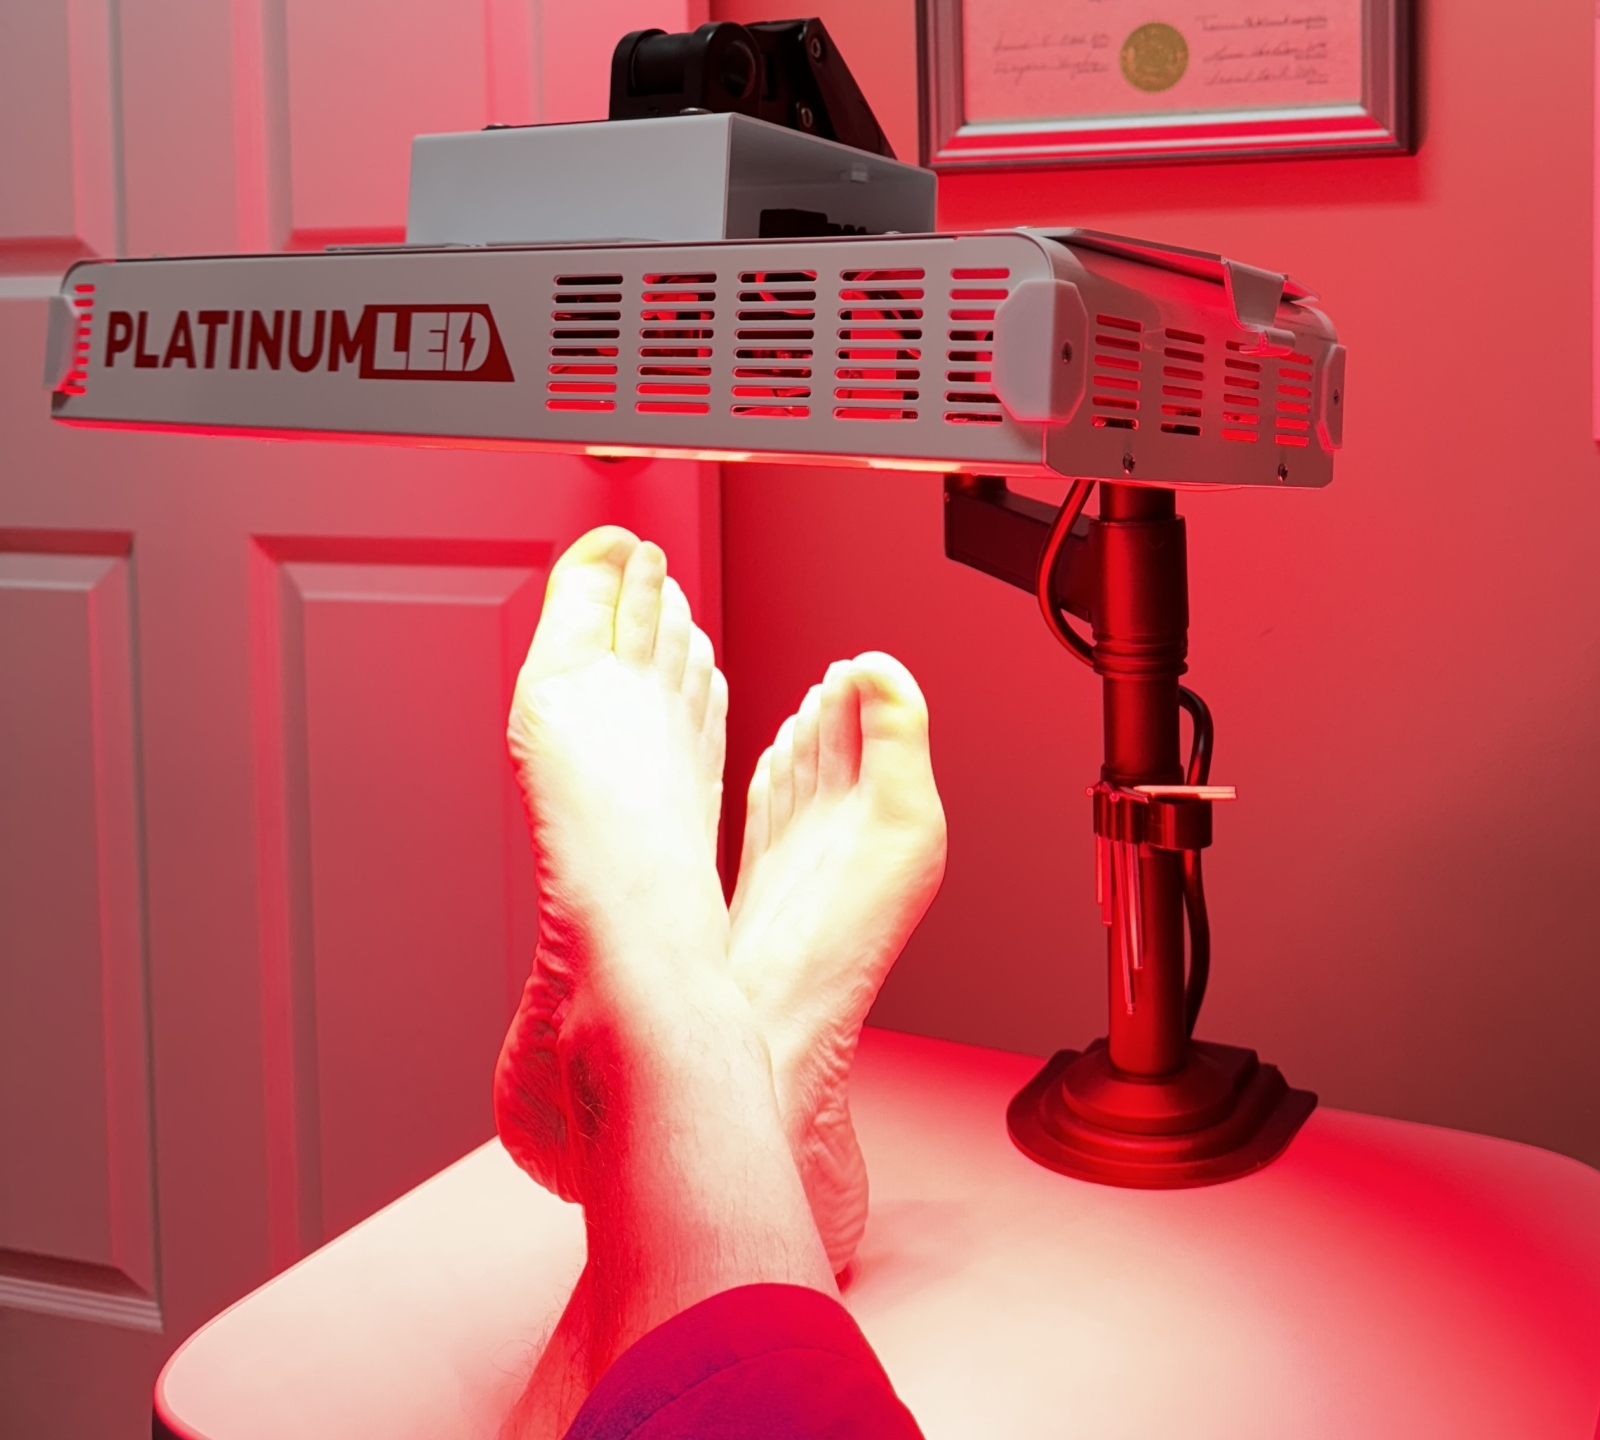
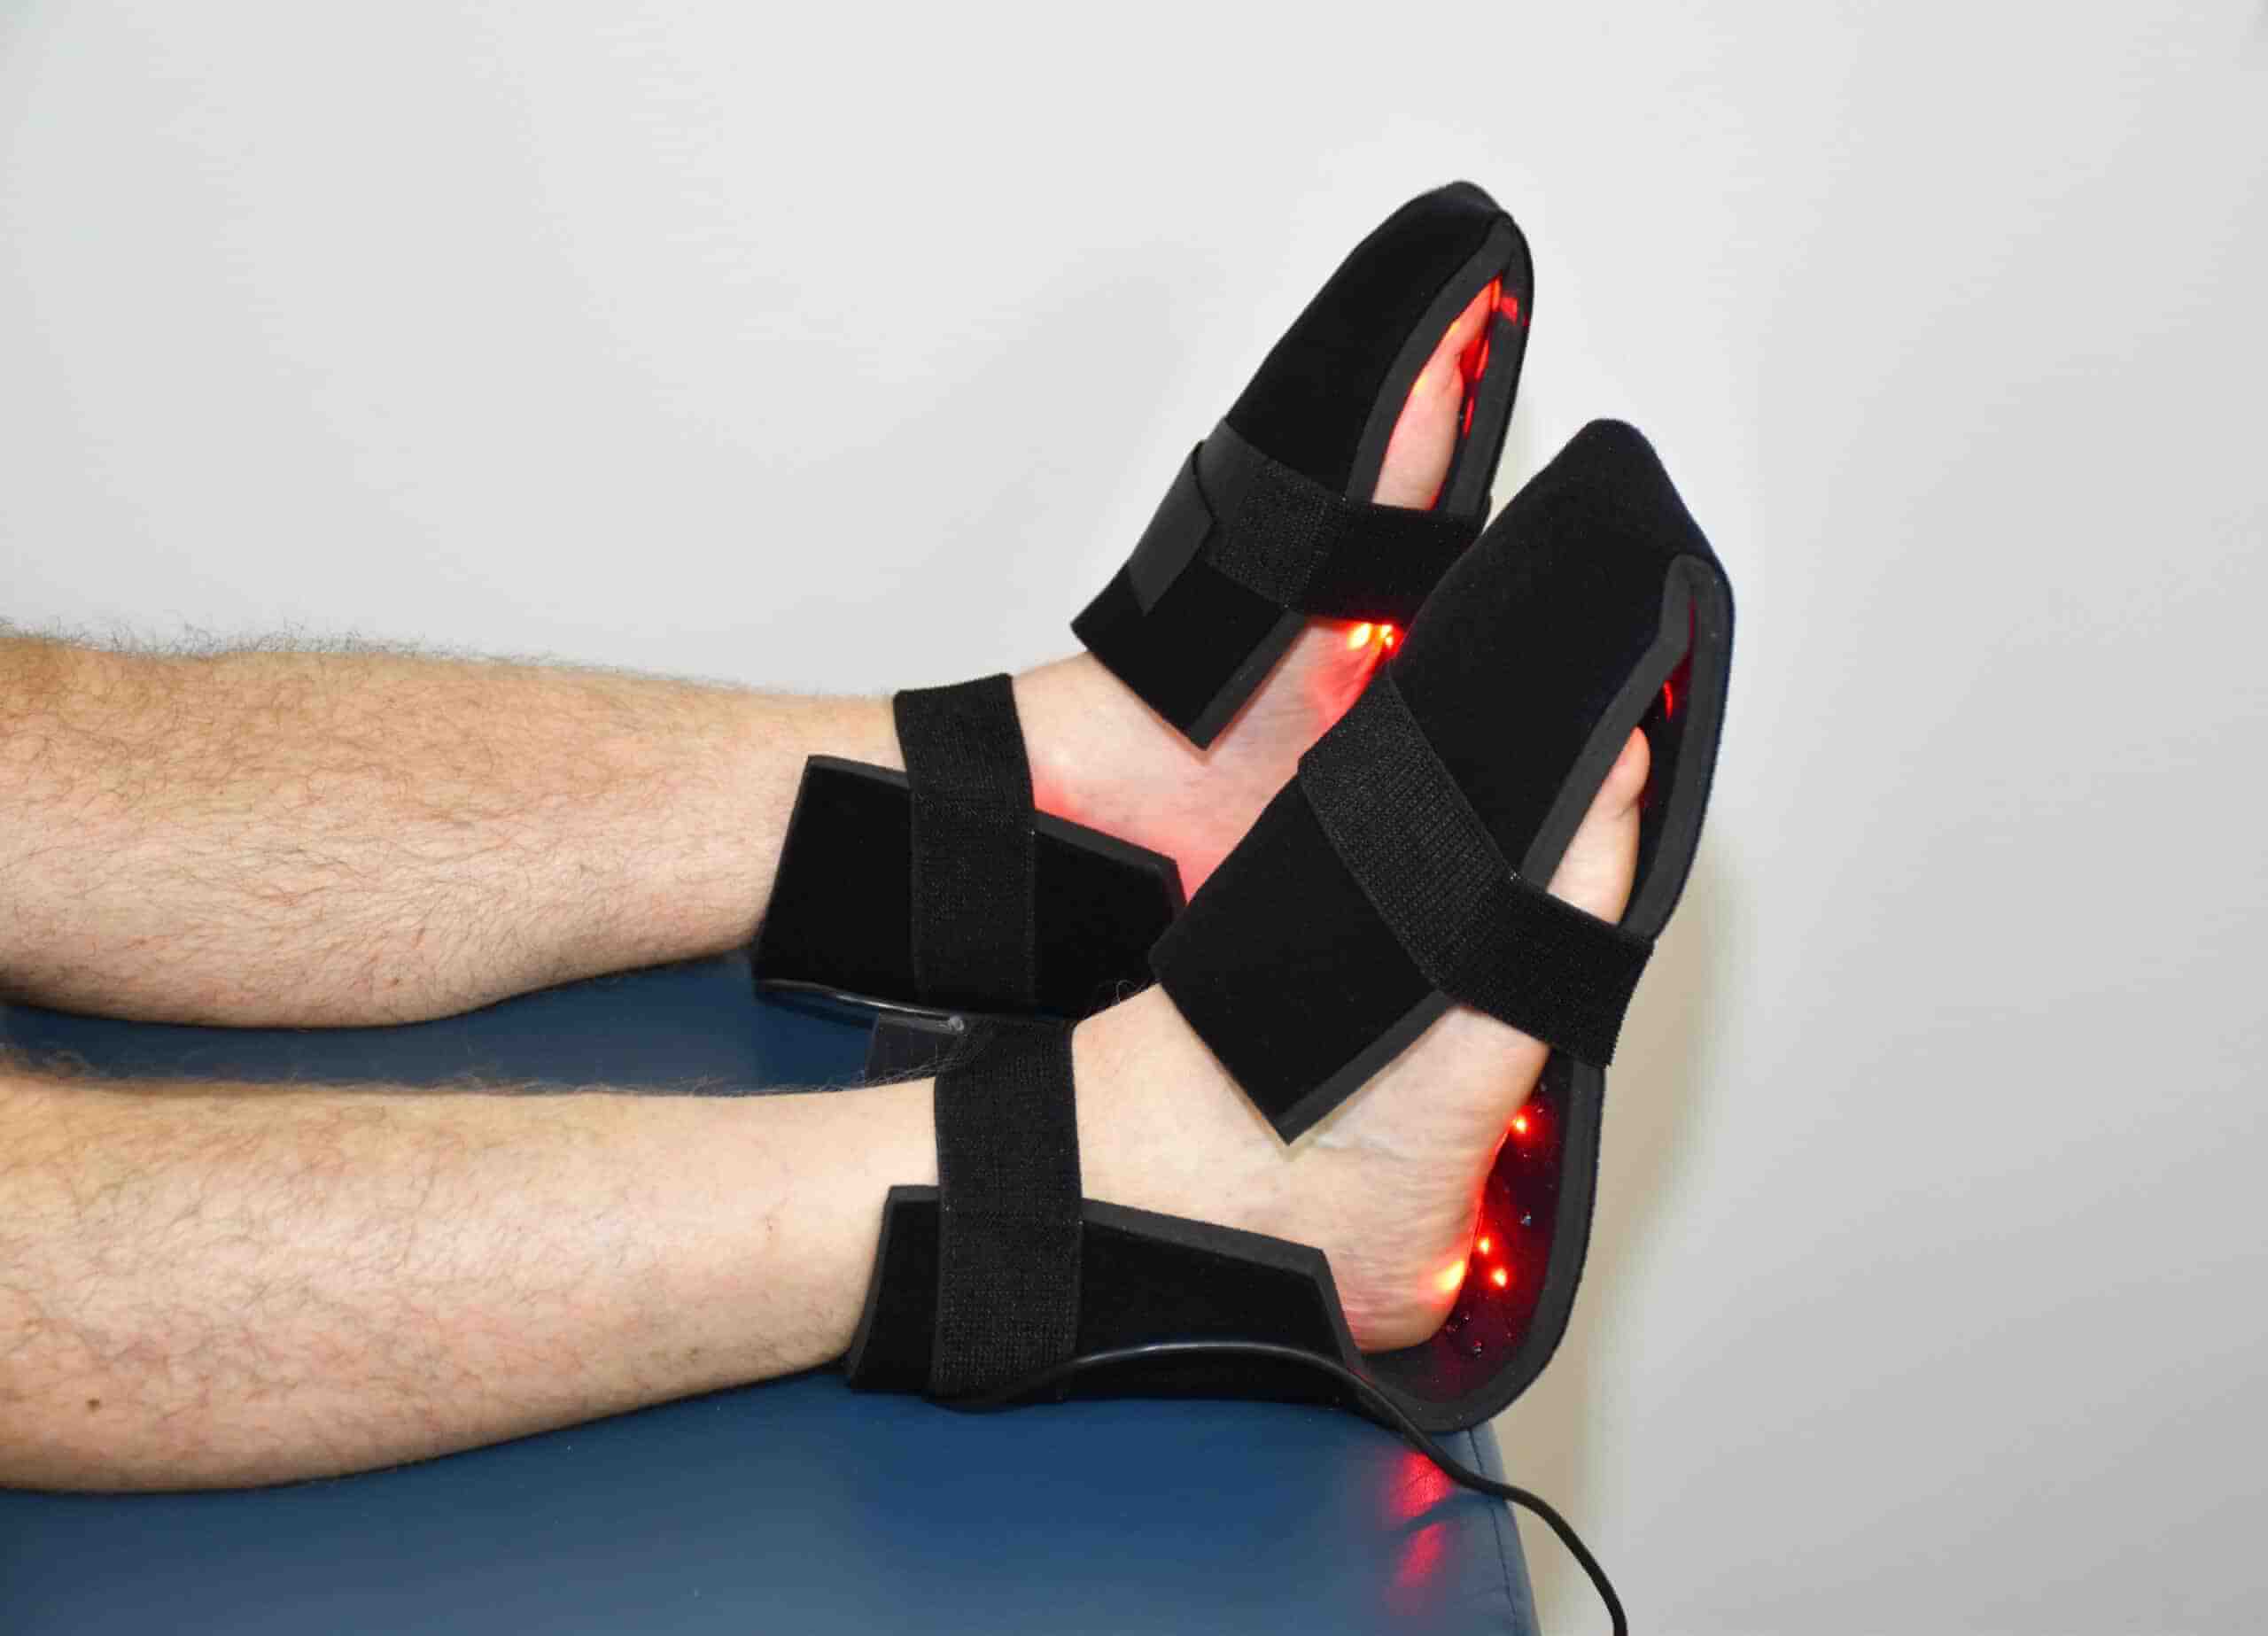
You place the affected area—usually the feet or hands for distal symmetric polyneuropathy—within the recommended distance, typically 2 to 6 inches depending on the panel's beam angle and power density. There's no pain, no heat sensation you can feel with these wavelengths, which is both the advantage and the problem. Because you can't sense when the treatment is working, compliance drops significantly after the first few weeks when patients expect some immediate feedback like warmth or tingling that never comes. I tell my patients to track symptoms on a simple 1-to-10 scale before and after each session for the first two weeks, then switch to weekly tracking once they understand there's no acute effect to ride the wave of. The timing matters more than people realize because peripheral nerves have a slow metabolic response. You're not fixing acute inflammation—you're supporting mitochondrial function in chronically damaged tissue, which means consistent daily or every-other-day treatment for at least 8 weeks before you see measurable improvement on validated scales like the Total Symptom Score or nerve conduction studies. I had a patient who stopped at week 4 because his numbness hadn't improved, not realizing that subjective sensory symptoms often lag behind objective nerve recovery by another 4 to 6 weeks, and that the first measurable change in vibration perception threshold on a biothesiometer usually appears around week 6 to 8, not week 2.
Edge Cases Where This Approach Fails Completely
I encountered a specific problem with a 62-year-old male with advanced diabetic neuropathy and autonomic involvement who developed increased burning pain after treatment instead of improvement. The issue was that his condition had progressed beyond the point where mitochondrial stimulation helped because the end-organ damage was too severe, and the increased blood flow from photobiomodulation actually exacerbated his symptoms by delivering inflammatory mediators to already sensitized nerve endings. I reduced the dose by half and switched to alternating days, which stopped the worsening, but he never achieved the improvement we'd discussed because he presented at stage 3 out of 4 on the Toronto Clinical Scoring System, where intervention effects become marginal at best. The contraindications are more limited than marketing materials suggest, but they matter. Active malignancy in the treatment field is a relative contraindication because while photobiomodulation doesn't cause cancer, the increased cellular metabolism could theoretically support tumor growth in undiagnosed early-stage disease. Pregnancy over the abdomen is an absolute contraindication because the effects on fetal development are unknown, though I've treated partners of pregnant women without issue by using only the feet. Photosensitivity medications like doxycycline, thiazide diuretics, and fluoroquinolones require dose reduction by 50% and careful monitoring because they increase the risk of phototoxic reactions even at wavelengths below 700nm.
Get the Full Details

Building a Practical Protocol
I recommend starting with 660nm red light for the superficial nerve fibers and 850nm near-infrared for deeper structures, delivered at 4 to 6 Joules per square centimeter per session. The total treatment time for both wavelengths combined should not exceed 20 minutes per session because prolonged exposure beyond this threshold shows diminishing returns and may trigger adaptive responses that reduce the therapeutic effect. I treat Monday through Friday with weekends off because continuous daily stimulation doesn't provide additional benefit and may actually reduce long-term outcomes by preventing the natural recovery cycles that occur during rest periods. The measurement equipment you need includes a power meter for irradiance verification, which costs between $200 and $500 depending on accuracy, and a timer because phone timers are unreliable during treatment. Most people don't realize that their device delivers 30% to 50% less output than specified after 6 months of use because the LED array degrades, so annual recalibration is essential for maintaining consistent dosing across the treatment course. I track every parameter for the first 4 weeks, then switch to monthly monitoring once the protocol is established, because the treatment response stabilizes after the initial learning phase where individual variability is highest.