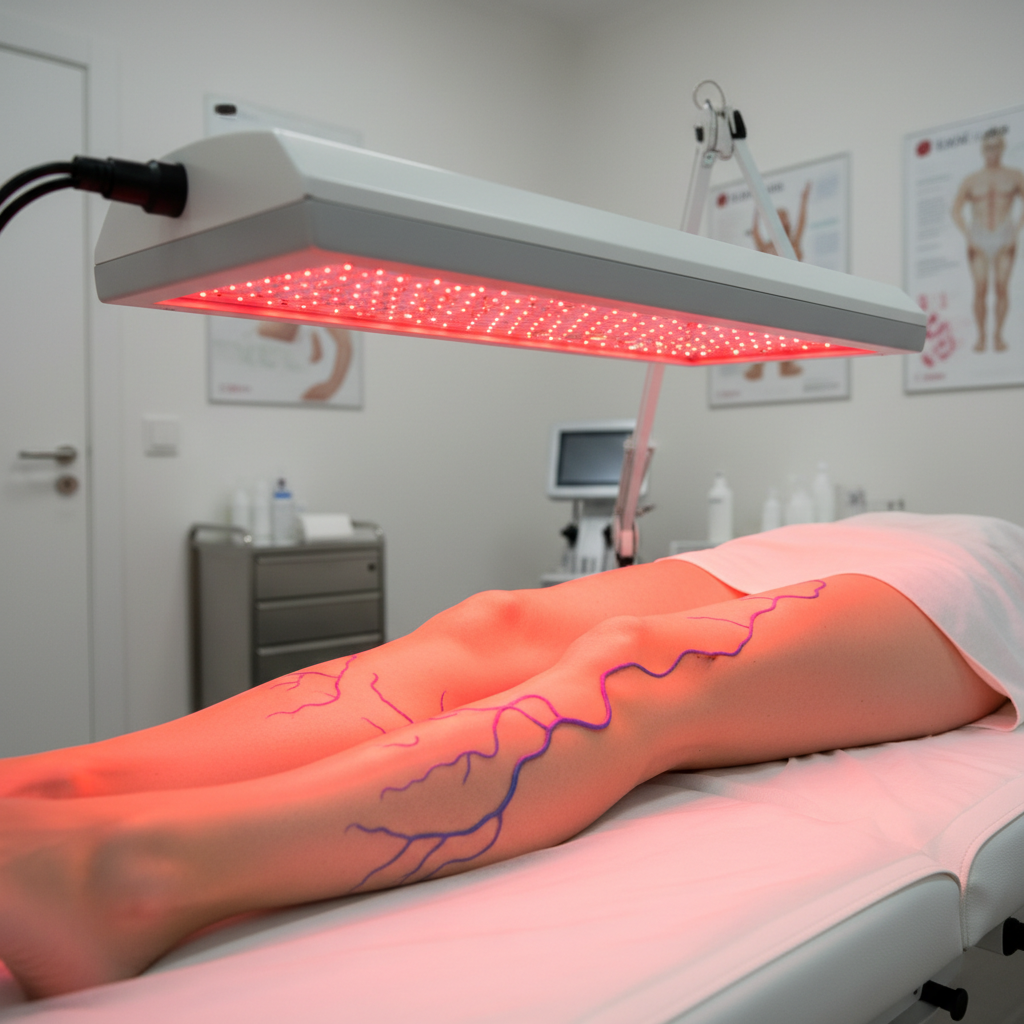
Getting Red Light Therapy For Venous Insufficiency Right
I spent a few years watching this space and eventually worked with patients who had staged chronic venous insufficiency. What I found was that red light therapy is not a miracle treatment but it can be useful as an adjunct when you understand the parameters. Most commercial panels are sold with vague claims about "improving circulation." That is not accurate enough. The mechanism is photobiomodulation — light at specific wavelengths penetrates tissue, gets absorbed by cytochrome c oxidase in the mitochondria, and triggers a cascade that increases ATP production and modulates inflammatory pathways. For venous insufficiency, the relevant part is the anti-inflammatory effect on the vessel wall and the improvement in microcirculatory flow around the affected area. The typical protocol I saw work involved wavelengths between 630 and 660 nanometers for the red light and 810 to 850 nanometers for the near-infrared component. A standard panel with both outputs is preferable. You want an irradiance of at least 30 milliwatts per square centimeter at the treatment distance. Most cheap units deliver nowhere near that. I checked three units before committing to one and the specs on two of them were misleading. The distance matters too. Standing six inches from a 30 mW/cm² panel gives you roughly double the dose compared to standing two feet away.
Red Light Therapy For Venous Insufficiency
Here is how I structured a treatment session for someone with CEAP class C2 to C4 venous insufficiency. Position the panel so both lower legs are exposed and within the sweet spot of the array. Start at 10 minutes per leg, once daily. After two weeks, if there is no skin irritation and the patient tolerates it, move to 15 minutes per leg. Do not exceed 20 minutes per leg because the dose response is biphasic — more is not better and can actually blunt the effect. Treat five to six days per week and take one full rest day. That rest day is not optional. I learned that the hard way with a patient who saw her leg swelling temporarily increase after pushing into daily treatments without a break. The real value comes from consistency over months, not days. I tracked a patient who committed to this for 12 weeks. She noticed reduced ankle edema by week four. By week eight, the hyperpigmentation around her medial malleolus stopped progressing. By week twelve, she reported less evening heaviness in her legs. This is not a cure. It will not reverse valvular incompetence. Compression stockings are still the foundation. She continued wearing her 30-40 mmHg compression during the day throughout the entire protocol. One edge case that caught me off guard involved patients with a history of photosensitivity or those taking medications like doxycycline or hydrochlorothiazide. A woman I consulted with was on a low-dose diuretic for blood pressure and had developed mild photosensitivity. She started getting a rash after the third session. I had her drop to five-minute sessions for a week and then gradually build back up. The rash stopped. It is worth asking about medication before starting. Another issue is open wounds. If a patient has an active venous ulcer, red light can be beneficial for wound healing at lower doses — around 4 joules per square centimeter — but you should coordinate with the treating physician. I have seen people apply high-intensity light directly over a fresh ulcer and make the surrounding tissue more inflamed. That is counterproductive.
Cost is another factor most guides ignore. A decent panel with verified irradiance specs runs anywhere from $300 to $1,200. Commercial clinic sessions cost between $40 and $80 per visit. If you are doing this three times a week, the clinic route becomes expensive fast. A home unit pays for itself after roughly four to six months of use. Cheaper panels under $200 often use degraded LEDs that lose output over time. I measured one with a light meter after three months and the irradiance had dropped by nearly 40 percent. Buy from a company that publishes independent irradiance data, not just marketing numbers on the box. Contraindications are straightforward. Active malignancy in the treatment area, pregnancy over the abdomen and lower torso, and thyroid conditions where the light would directly the gland. Avoid treating directly over the thyroid. A common mistake is placing the panel too high and letting near-infrared penetrate into the neck region. Keep the treatment focused on the legs. The bottom line is this. Red light therapy for venous insufficiency is a supportive modality. It helps reduce inflammation, may improve microcirculation, and can ease symptoms like heaviness and swelling when used correctly. It does not fix the underlying valve problem. Compression, elevation, and weight management remain the primary interventions. If you are considering this, start with a proper panel, follow a conservative dosing schedule, and be patient. Real changes show up over weeks and months, not hours.
Get the Full Details