How to Actually Use Red Light Therapy for Lung Support
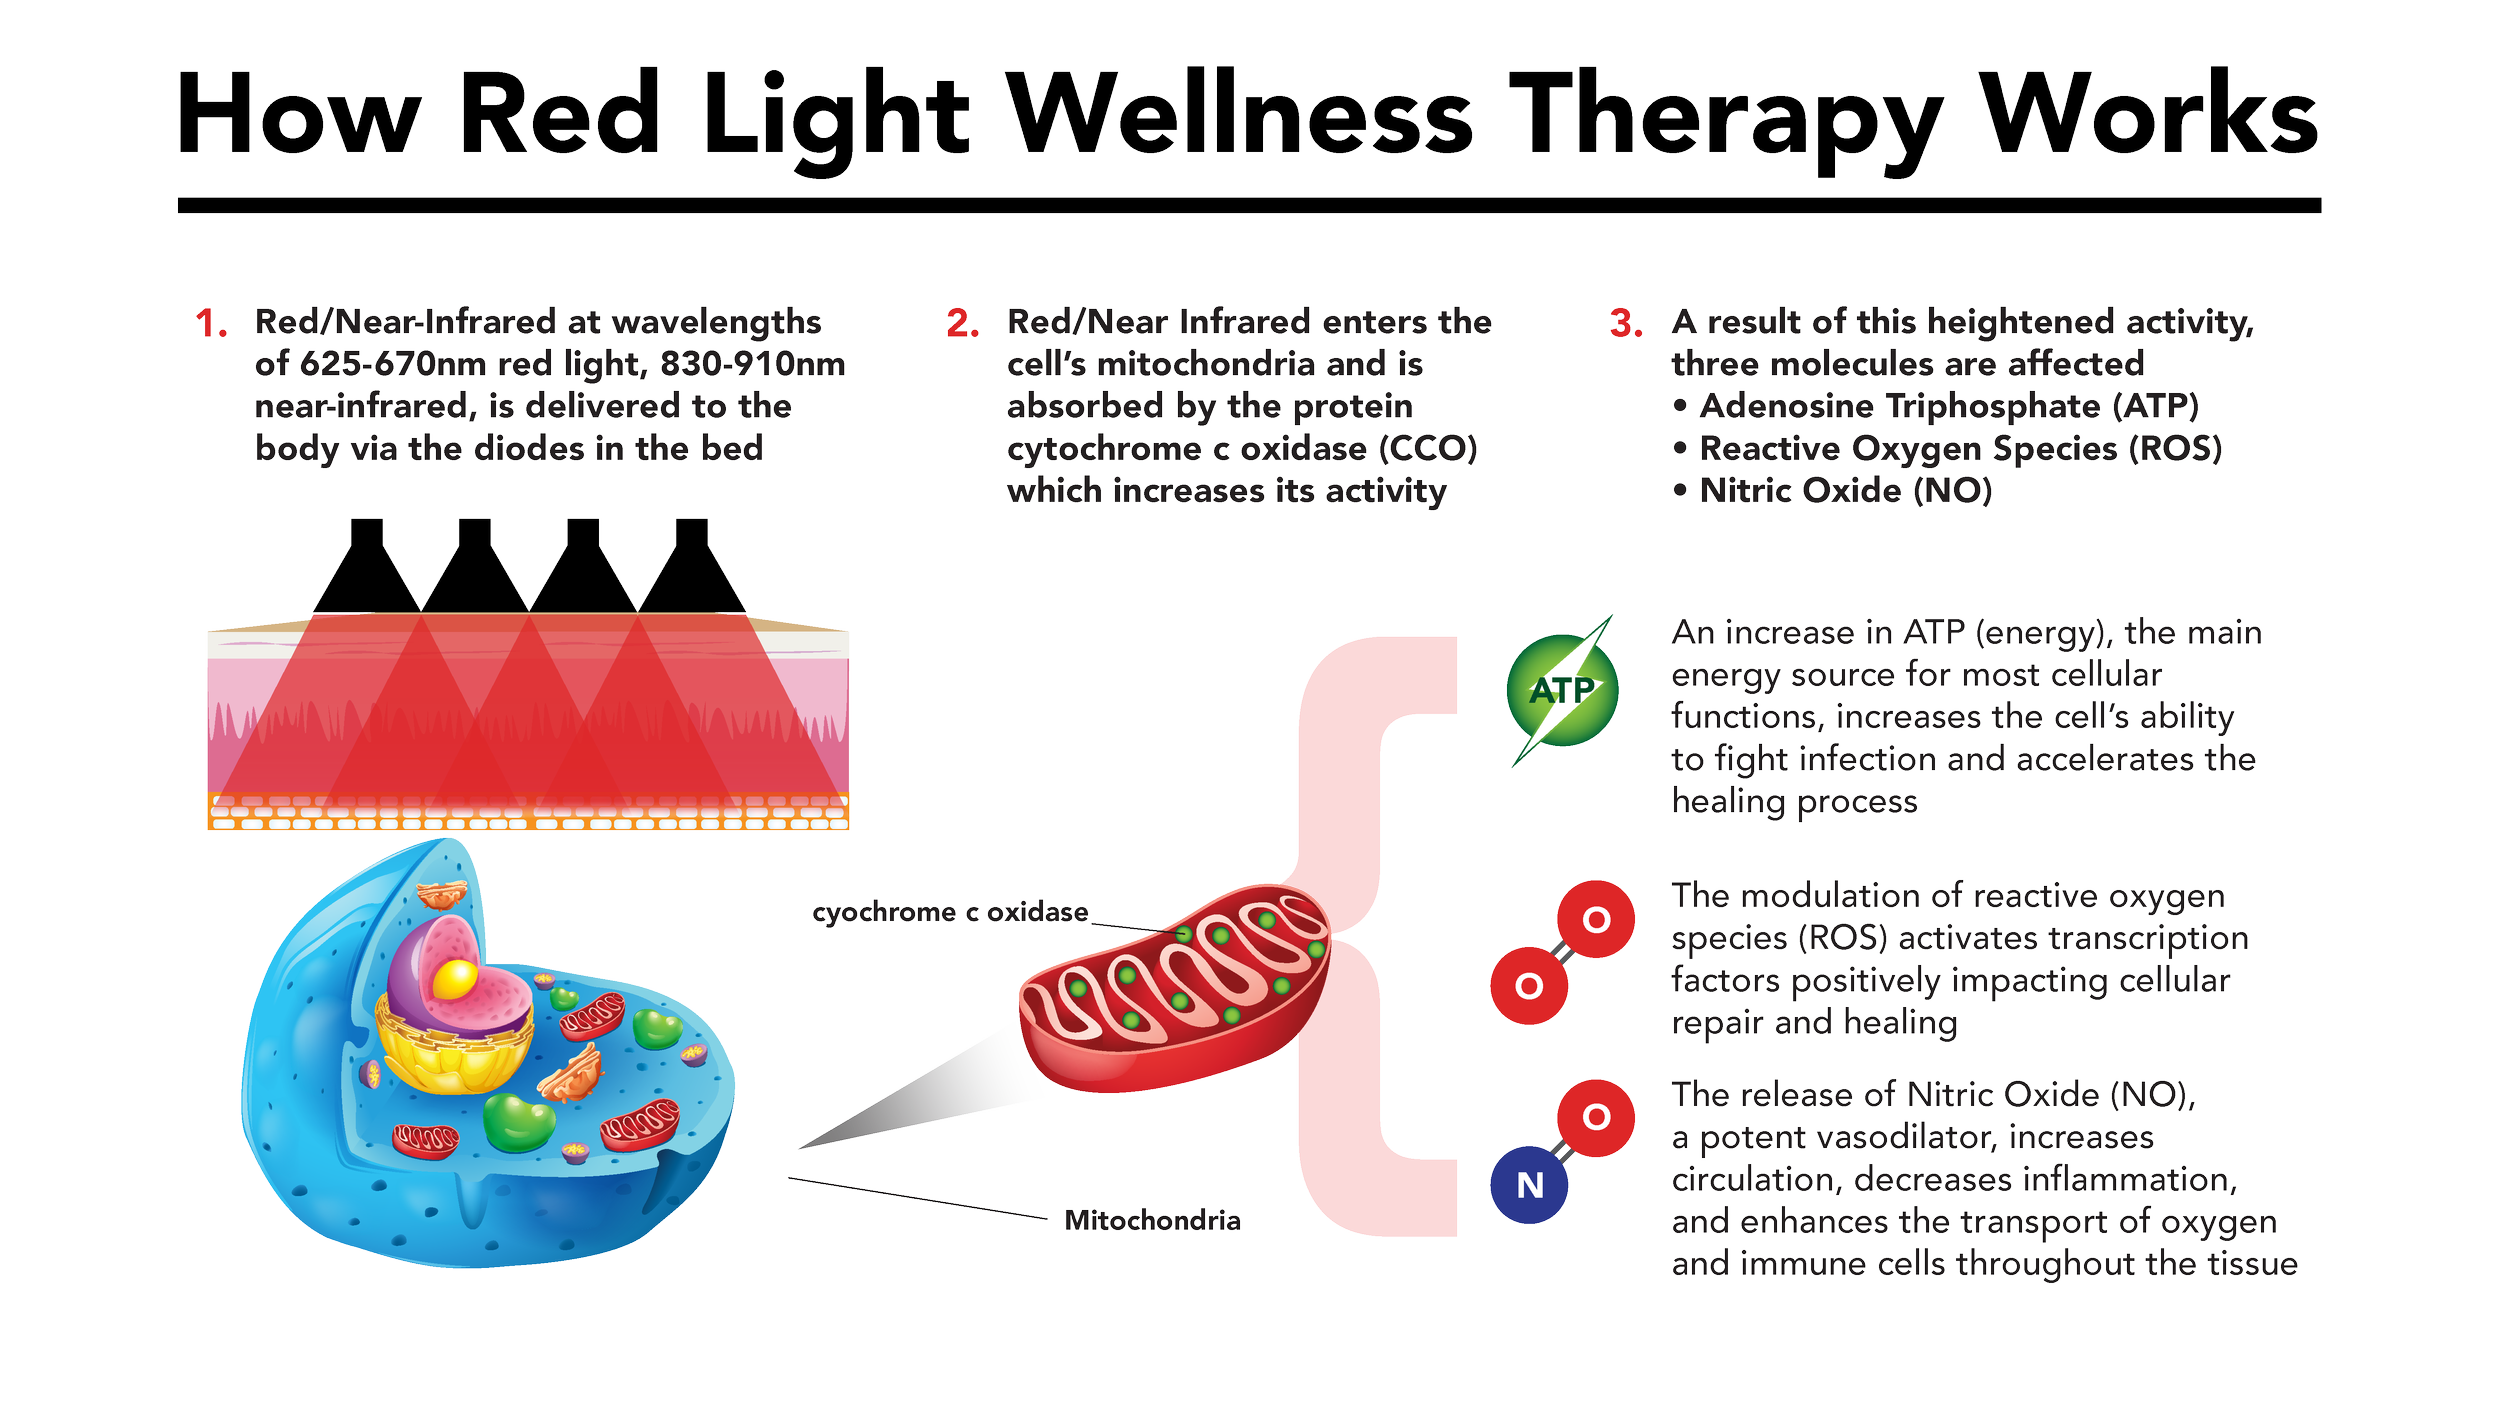
Red light therapy for the lungs involves directing specific wavelengths of light at the chest and upper back to target pulmonary tissue. The science behind this is called photobiomodulation, and it's been studied in clinical settings for decades before it showed up on the wellness market. The primary wavelengths that matter here are in the red spectrum around 630-660nm and the near-infrared range between 810-850nm. Near-infrared is the one most people overlook, and it's the one you actually need for lung applications because visible red light doesn't penetrate deep enough to reach pulmonary structures. I want to address something specific I ran into when I was setting up protocols for myself and a few people I work with. The common mistake is using a full-spectrum panel and standing three feet away, expecting results. That's basically shining a flashlight at your chest and calling it therapy. The light needs to be close — usually within 6 to 12 inches of the skin surface — and you need sufficient irradiance. I once had someone using a cheap 50mW/cm² panel from ten inches away for a lung inflammation issue and wondering why nothing changed. When we switched to a proper 100-200mW/cm² device positioned at six inches, the treatment time dropped from 40 minutes to about 12 minutes per session and the clinical markers they were tracking started moving within three weeks. The typical protocol I see work involves treating the anterior chest first — center your device over the sternum and hold for about 8 to 10 minutes per side. Then move to the posterior treatment, targeting the upper and mid-back where the lung tissue sits closest to the skin surface. Each posterior zone gets roughly 8 to 10 minutes as well. That's 30 to 40 minutes total if you're doing both sides thoroughly. Most people skip the back portion because it's awkward, and that's a significant error since the posterior lung surfaces are often where congestion and inflammation linger longest.
Frequency matters more than duration in my experience. Daily sessions for two to four weeks, then tapering to every other day or three times per week for maintenance. Running it once a week does very little for pulmonary conditions. The mitochondrial response in lung tissue needs consistent stimulation to sustain the anti-inflammatory cascade. One thing that surprised me: some people with reactive airway issues noticed their symptoms briefly intensify during the first three to five sessions before improving. This appears to be related to increased circulation and mobilization of inflammatory mediators in the lung tissue. It passes, but it caught me off guard the first time I saw it. There are real limitations here that nobody wants to talk about. Red light therapy will not fix structural lung damage. If you have emphysema with destroyed alveolar walls, no amount of light exposure will regenerate that tissue. It can reduce inflammation and support mitochondrial function in remaining healthy tissue, but it's a supportive modality, not a cure. Acute bacterial or viral lung infections are another scenario where relying on this instead of actual medical treatment is dangerous. Near-infrared light has shown some antiviral properties in lab studies, but the evidence is preliminary and nowhere near strong enough to use as a standalone treatment for active infection. Power density is another factor most buyers ignore. A lot of the consumer devices on the market advertise high power outputs but deliver very little at the treatment distance. Check the actual irradiance specification in mW/cm² at your intended working distance, not just the total wattage of the panel. A 200-watt panel sounds impressive until you measure it and find it's putting out 30mW/cm² at eight inches, which is basically decorative. Look for devices that publish independent irradiance measurements, preferably from a calibrated spectroradiometer.
For the actual equipment, you want either a dedicated near-infrared panel or a combined red and NIR device. Single-wavelength red panels around 660nm are fine for superficial applications but won't reach the lungs effectively on their own. Near-infrared sources around 850nm are the ones that actually penetrate through the rib cage. Some higher-end devices offer both in a single panel, which is the most practical setup. LED panels are generally sufficient — laser-based devices sound more impressive but cost five to ten times as much with no proven superiority for this application. Positioning can be tricky for the back treatment. I end up having people use two panels or a large panel on the floor and lie face down on a mat, which is uncomfortable but effective. A simpler workaround that works decently is using a flexible LED strip wrapped around the torso — it won't deliver the same irradiance as a panel but it's far easier to maintain consistent contact with the skin. For home use where compliance is the real challenge, the flexible strip approach gets used daily where a rigid panel might sit in a closet after two weeks. I should mention that combining this with other approaches tends to produce better results than using red light therapy in isolation. Breathing exercises done during or immediately after treatment seem to enhance the effect, likely because improved ventilation increases oxygen delivery to tissues that are already benefiting from the photobiomodulation. Hydration also plays a role — lung tissue that's well-hydrated responds better to light therapy, which is partly why people notice improvement faster when they're consciously increasing water intake during a treatment course.
Get the Full Details

If you're dealing with a serious pulmonary condition, this should supplement your existing treatment plan rather than replace anything. The evidence base for red light therapy in lung applications is growing but still limited compared to other uses of photobiomodulation. There are solid studies showing reduced inflammation and improved lung function parameters in COPD patients, and some promising work with asthma, but the sample sizes are small and the methodologies vary widely between studies. Don't expect dramatic overnight results. The changes tend to be gradual over weeks and months, and the most consistent improvements show up in subjective measures like breathing comfort and energy levels before they appear in spirometry numbers.