
Red Light Therapy for Melasma: What Actually Happens When You Use It
Melasma is stubborn. Everyone who deals with it knows that much. The pigmentation sits deep in the dermis and epidermis, responds poorly to the usual topicals, and returns the moment you stop treating it or get any sun exposure. Red light therapy is one of the few modalities that doesn't just sit there doing nothing, but it also isn't a cure. I've used it on clients and on myself for years, and here's the honest version of how it works in practice. The core mechanism is simple enough. Red light at around 630 to 660 nanometers and near-infrared at 810 to 850 nanometers penetrates the skin and gets taken up by cytochrome c oxidase in the mitochondria. That increases ATP production, which then triggers a cascade of anti-inflammatory signaling and modulation of melanocyte activity. In plain terms, it tells the melanocytes to calm down and reduces the inflammatory stimulus that drives melanin production. That's the part most guides skip because it sounds too clinical, but it's the entire reason this works at all.
Red Light Therapy Melasma: The Protocol That Actually Works
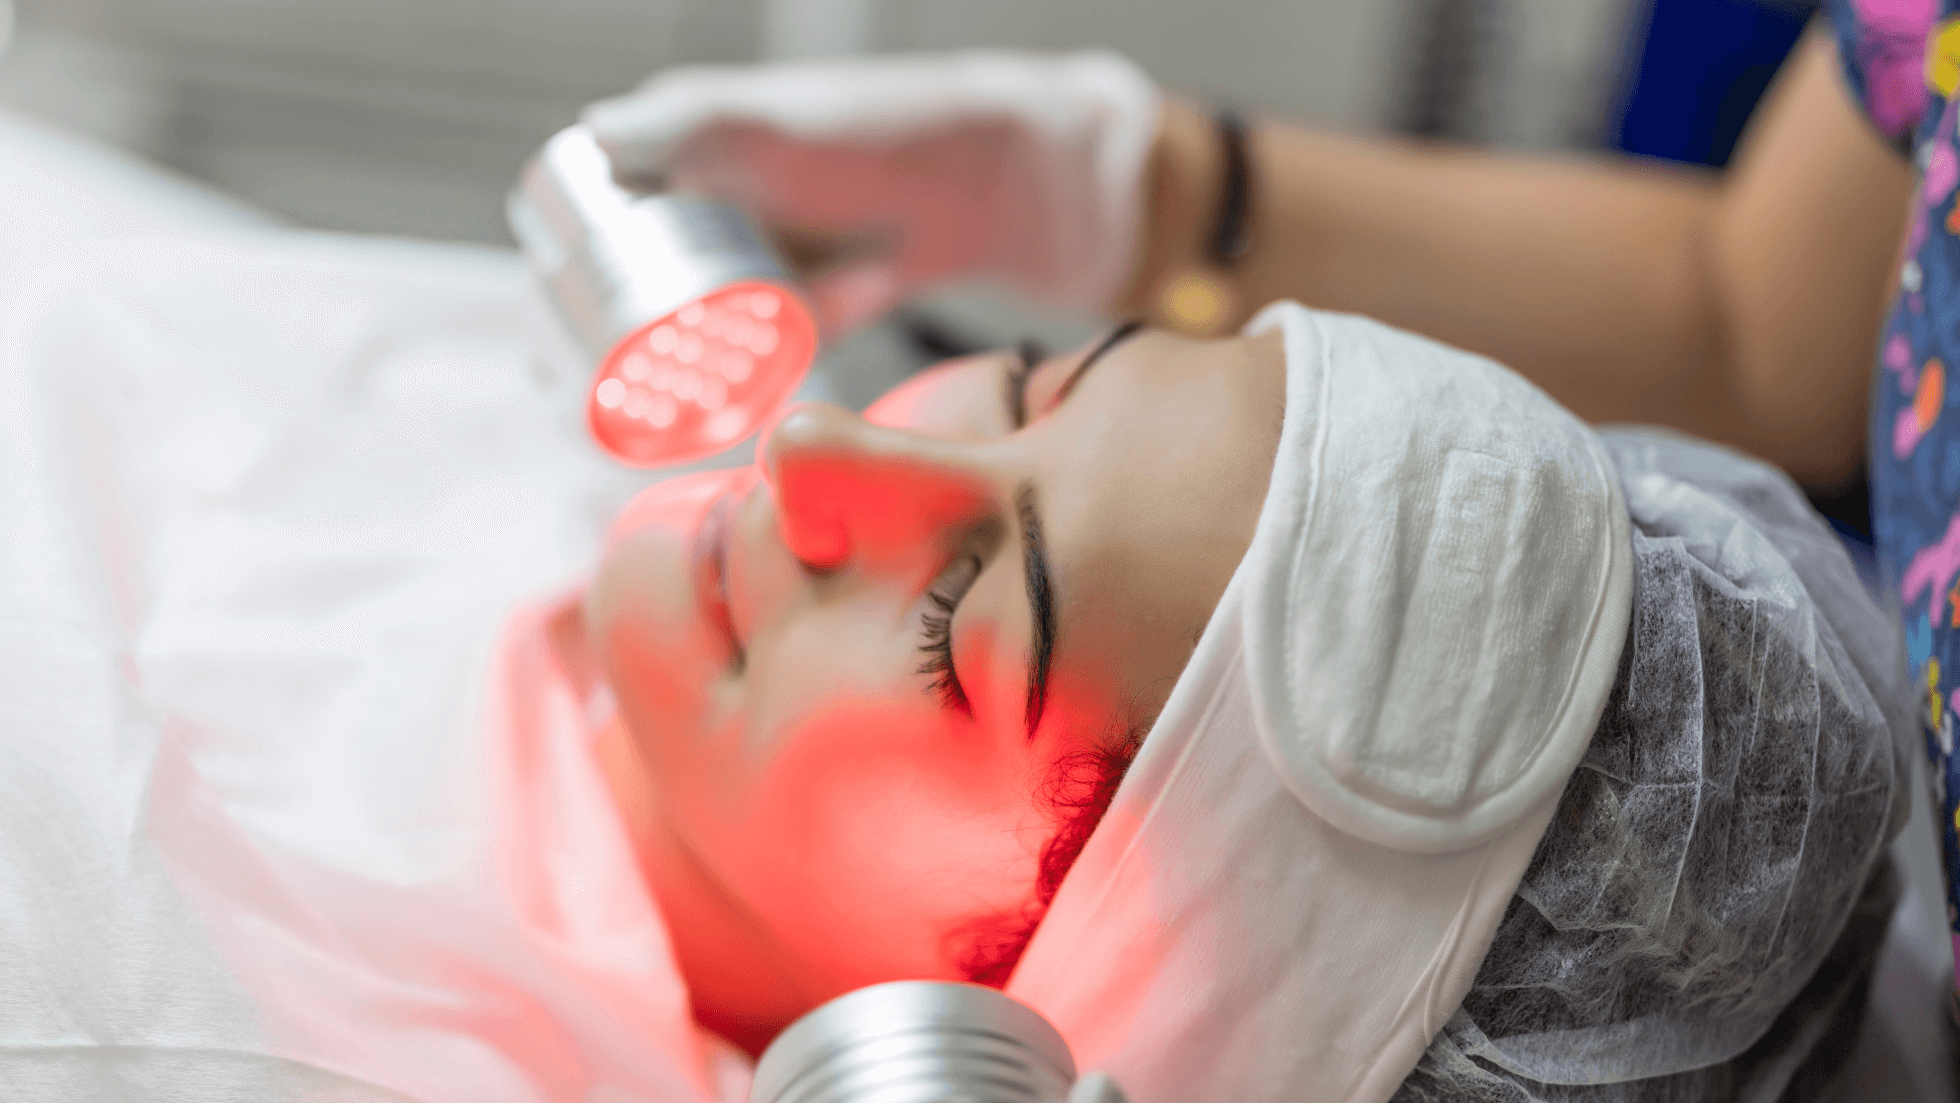
I run a standard protocol that looks like this: 630nm red light at 6 milliwatts per square centimeter, 810nm near-infrared at the same density, 10 minutes per treatment area, three times a week for eight weeks, then a maintenance schedule of once or twice a week. The device I use is a Miroptek panel with individual diodes, and I keep it at about 6 inches from the face. Anything closer and you start getting thermal effects that can actually worsen pigmentation in melasma-prone skin. That's the first counter-intuitive thing most people miss: heat is bad for melasma. Hot yoga, saunas, and running your device too close all feed the problem. I learned that the hard way. About six weeks into a protocol with a client who had severe melasma, her pigmentation actually darkened slightly. I had moved the panel from 6 inches to 4 inches because she wanted faster results, and the increased irradiance was generating enough sub-dermal heat to trigger a mild inflammatory response. We moved it back to 6 inches, dropped the session to 8 minutes, and it stabilized within two weeks. The takeaway is that melasma skin reacts to heat almost as aggressively as it reacts to UV. Treat it accordingly. There's another nuance that nobody talks about: the wavelength matters more than the power. A lot of cheap panels advertise high wattage but the actual output at 630nm is weak because the diodes are cheap Chinese clones with poor binning. I ran a spectrometer check on three popular consumer panels and the real irradiance at 630nm ranged from 4 mW/cm² to 18 mW/cm² despite all of them claiming 30 mW/cm² or higher. If you're going to invest in this, buy a device with independently verified output specs. SpectraLED and Light Sensei both publish their measured data, and Miroptek will provide a test report on request. Don't guess with melasma.
Combination therapy works better than red light alone. I pair it with topical tranexamic acid 3 to 5 percent and a strict broad-spectrum SPF 50+ that has iron oxides in it. The iron oxides are non-negotiable because they block visible light, and visible light at 400 to 700 nanometers is a known trigger for melasma in darker skin types. Sunscreen without iron oxides leaves about 20 to 30 percent of the visible spectrum unblocked. That's a meaningful gap for someone with active pigmentation. Here's where the limitations come in. Red light therapy for melasma will not remove established deep dermal pigment. If your melasma is primarily dermal on a Woods lamp exam, the results will be modest at best. Dermal melasma typically shows a 15 to 25 percent improvement after a full eight-week course, while mixed or epidermal melasma can see 40 to 60 percent clearance. The numbers vary by individual, but the pattern is consistent. If you have purely dermal melasma, you're better off looking at chemical peels like the TCA peel protocol or low-fluence Q-switched laser sessions spaced well apart, combined with red light as a supporting modality rather than the primary treatment. Another thing to factor in is the timeline. You won't see changes in the first two weeks. Maybe a slight reduction in redness if there's an inflammatory component. Real pigment lightening usually becomes noticeable around week 4 and continues through week 8. After that, you're in maintenance territory. Stopping completely almost always leads to recurrence within three to six months, which is why a weekly maintenance session is part of the protocol, not an upsell.
Get the Full Details
If you want to track progress, take photos under the same conditions every two weeks. Natural daylight facing north, no makeup, same distance from the camera. Phone cameras with auto-processing will lie to you because they shift saturation and contrast between shots. I keep a simple Google Sheet with the photo filenames, date, device settings, and a one-line note on how the skin looked that day. Over eight weeks that becomes useful data. Subjective memory is unreliable. One more thing: avoid combining red light therapy with retinoids on the same session. It's tempting to stack actives, but retinoids thin the stratum corneum and increase photosensitivity, and doing them together just adds irritation without adding benefit. Space them out. Red light in the morning, retinoid at night, or alternate days. The skin barrier has to be intact for the light to penetrate properly and for the anti-inflammatory effects to land.


