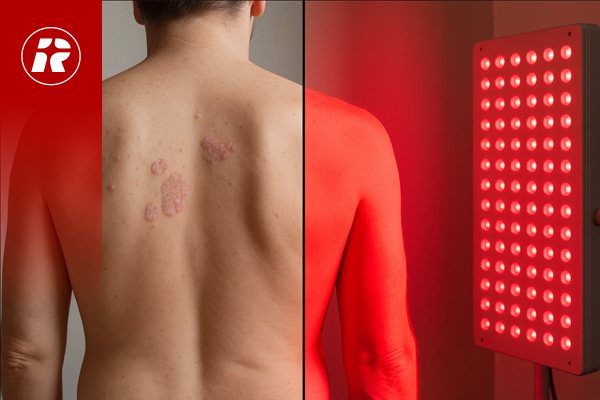
Red Light Therapy for Psoriasis: A Practical Guide
Red light therapy has become one of the more discussed home treatment options for psoriasis on Reddit, and for good reason. The basic mechanism is straightforward. Low-level laser therapy or LED panels emit specific wavelengths of red and near-infrared light that penetrate the skin. At 660 nanometers, red light targets the epidermis and dermis where psoriatic inflammation lives. At 850 nanometers, near-infrared goes deeper into tissue. The proposed mechanism involves increased mitochondrial ATP production, reduced oxidative stress, and modulation of inflammatory cytokines like TNF-alpha and IL-17. People on Red Light Therapy Psoriasis Reddit share mixed results. Some report meaningful plaque thinning within six to eight weeks. Others see nothing. Understanding why requires knowing how the technology actually works rather than relying on anecdotal success stories alone.
Choosing the Right Device
Not all devices are equivalent, and this is where most people make costly mistakes. Medical-grade devices from companies like Omnilux, Photonify, or Joovv use calibrated LEDs or low-level lasers with known power output per panel. Cheap generic panels from Amazon often list wattage but never specify irradiance, which is the actual power delivered per unit area measured in milliwatts per centimeter squared. Without irradiance data, you cannot determine whether the device delivers a therapeutic dose. Absence of published irradiance maps is the single biggest red flag in this market. Reputable manufacturers provide spectral emission data and irradiance measurements at various distances. Check before buying. The wavelength matters too. You want a device that emits primarily at 630 to 660 nanometers for red light and 810 to 850 nanometers for near-infrared. If the spectrum is broad and unfocused, much of the output falls outside the therapeutic window and gets wasted.
Setting Up Your Protocol
Start with a conservative approach. Expose affected areas for ten minutes at a distance of approximately twelve to eighteen inches from the panel, three times per week. Do not increase frequency or duration immediately assuming more is better. The biphasic dose response curve in photobiomodulation means that both underdosing and overdosing can reduce effectiveness. Once you establish a baseline tolerance, you can slowly increase exposure time by two-minute increments every two weeks until you reach twenty minutes per session. I discovered this the hard way during my first month of using a 660nm panel on my elbows and knees. I was running sessions for forty minutes daily because I had read aggressive protocols online. Within two weeks the plaques looked worse, more inflamed and slightly thicker. I cut the duration back to fifteen minutes every other day and the irritation resolved after about ten days. The lesson was simple. Psoriatic skin is already in a hyperinflammatory state, and excessive light energy can trigger additional stress responses that counteract the therapeutic effect. Consistency matters more than intensity. A moderate protocol followed consistently for twelve weeks will outperform an aggressive protocol followed sporadically for four weeks. Most studies on photobiomodulation for psoriasis use treatments spanning at least eight weeks before reporting significant outcomes. Anyone promising results in a week is selling something.
Get the Full Details

Combining with Other Treatments
Red light therapy works best as an adjunct rather than a standalone treatment. Topical corticosteroids, vitamin D analogues like calcipotriene, and topical retinoids remain the first-line treatments recommended by dermatologists. Phototherapy with narrowband UVB has stronger clinical evidence for psoriasis than red light therapy does. The advantage of red light is that it carries no UV radiation risk and can be used at home without specialized protective eyewear beyond the standard safety goggles most panels include. Some users combine red light therapy with coal tar or salicylic acid topicals applied after the session. The light may increase local blood flow and potentially enhance absorption of subsequent topical medications, though this has not been rigorously studied. Keep in mind that if you are on systemic medications like methotrexate or biologic agents, consult your dermatologist before adding any new treatment. There is limited data on interactions between photobiomodulation and immunomodulatory drugs.
What the Evidence Actually Says
The clinical literature on red light therapy for psoriasis is modest compared to narrowband UVB or excimer laser studies. A small number of randomized controlled trials have shown statistically significant improvements in the Psoriasis Area and Severity Index scores with LED therapy at 660nm, but the sample sizes are typically under fifty participants and the follow-up periods are short. Systematic reviews note potential benefit but call for larger, more rigorous trials. This is honest positioning. The evidence supports trying it, but it does not support treating it as a proven first-line intervention. One common mistake is placing the device too close. Some cheap units recommend sitting within six inches of the panel. At that distance the irradiance can exceed safe limits for extended exposure and cause thermal discomfort without providing additional therapeutic benefit. Another mistake is ignoring eye protection. Even though red and near-infrared light is not ionizing radiation, direct staring into high-power LED arrays can cause retinal strain and potential long-term damage. Use the goggles provided or get ANSI-compliant blocking glasses rated for the specific wavelengths you are using. A more subtle issue is the belief that clearing a plaque means stopping treatment. Psoriasis is chronic and immune-mediated. Maintenance sessions two to three times per week after the initial clearing phase are often necessary to sustain results. Stopping abruptly typically leads to rebound within weeks.
Red light therapy is not going to cure psoriasis. It will not replace systemic treatment for moderate to severe cases. But for people with mild to moderate plaque psoriasis who want a low-risk add-on option they can manage at home, it is worth a disciplined trial period of at least twelve weeks using a properly specified device and a conservative, consistent protocol. The community discussions on forums reflect that reality accurately. Most people who get value from it do so by treating it as a long-term management tool rather than a quick fix.




