Understanding How The Body Gets Divided Into Regions
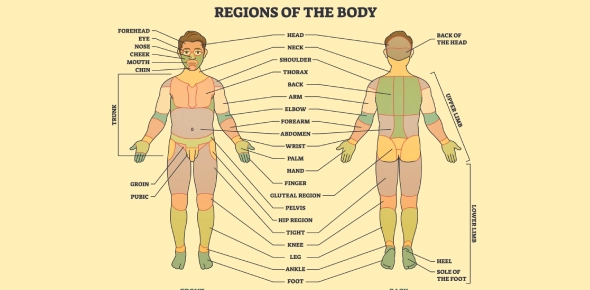
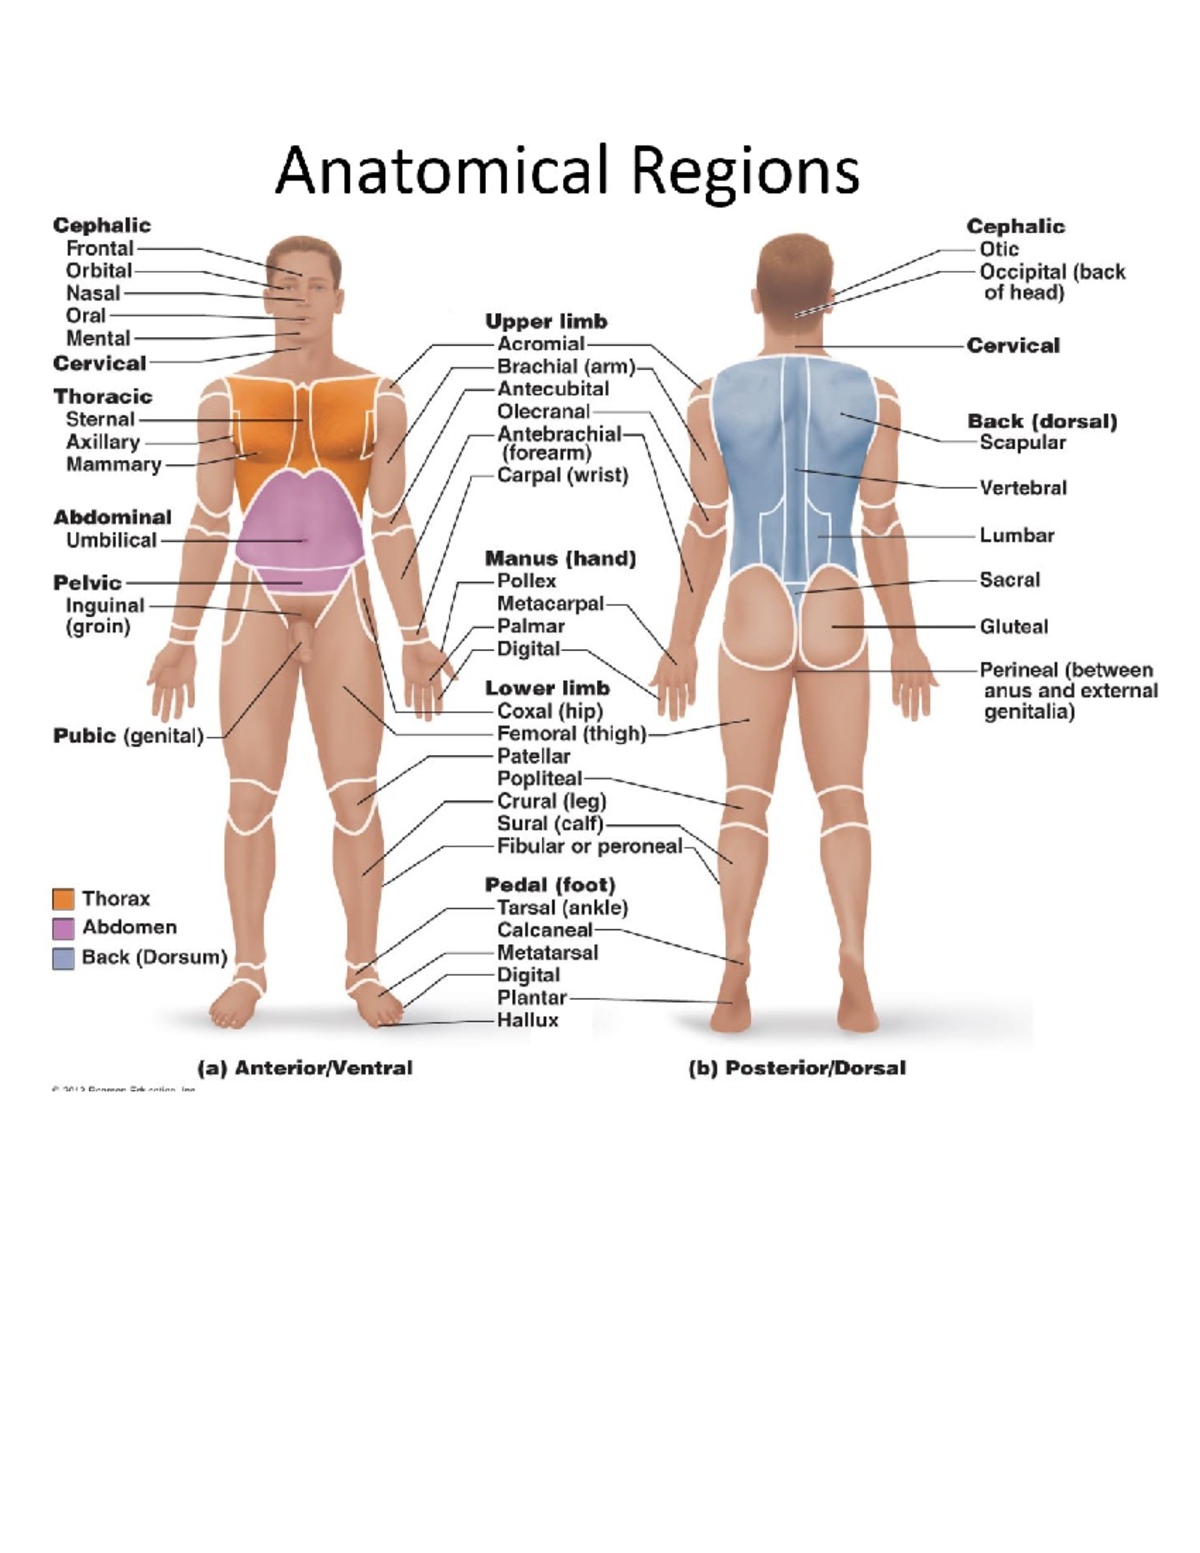
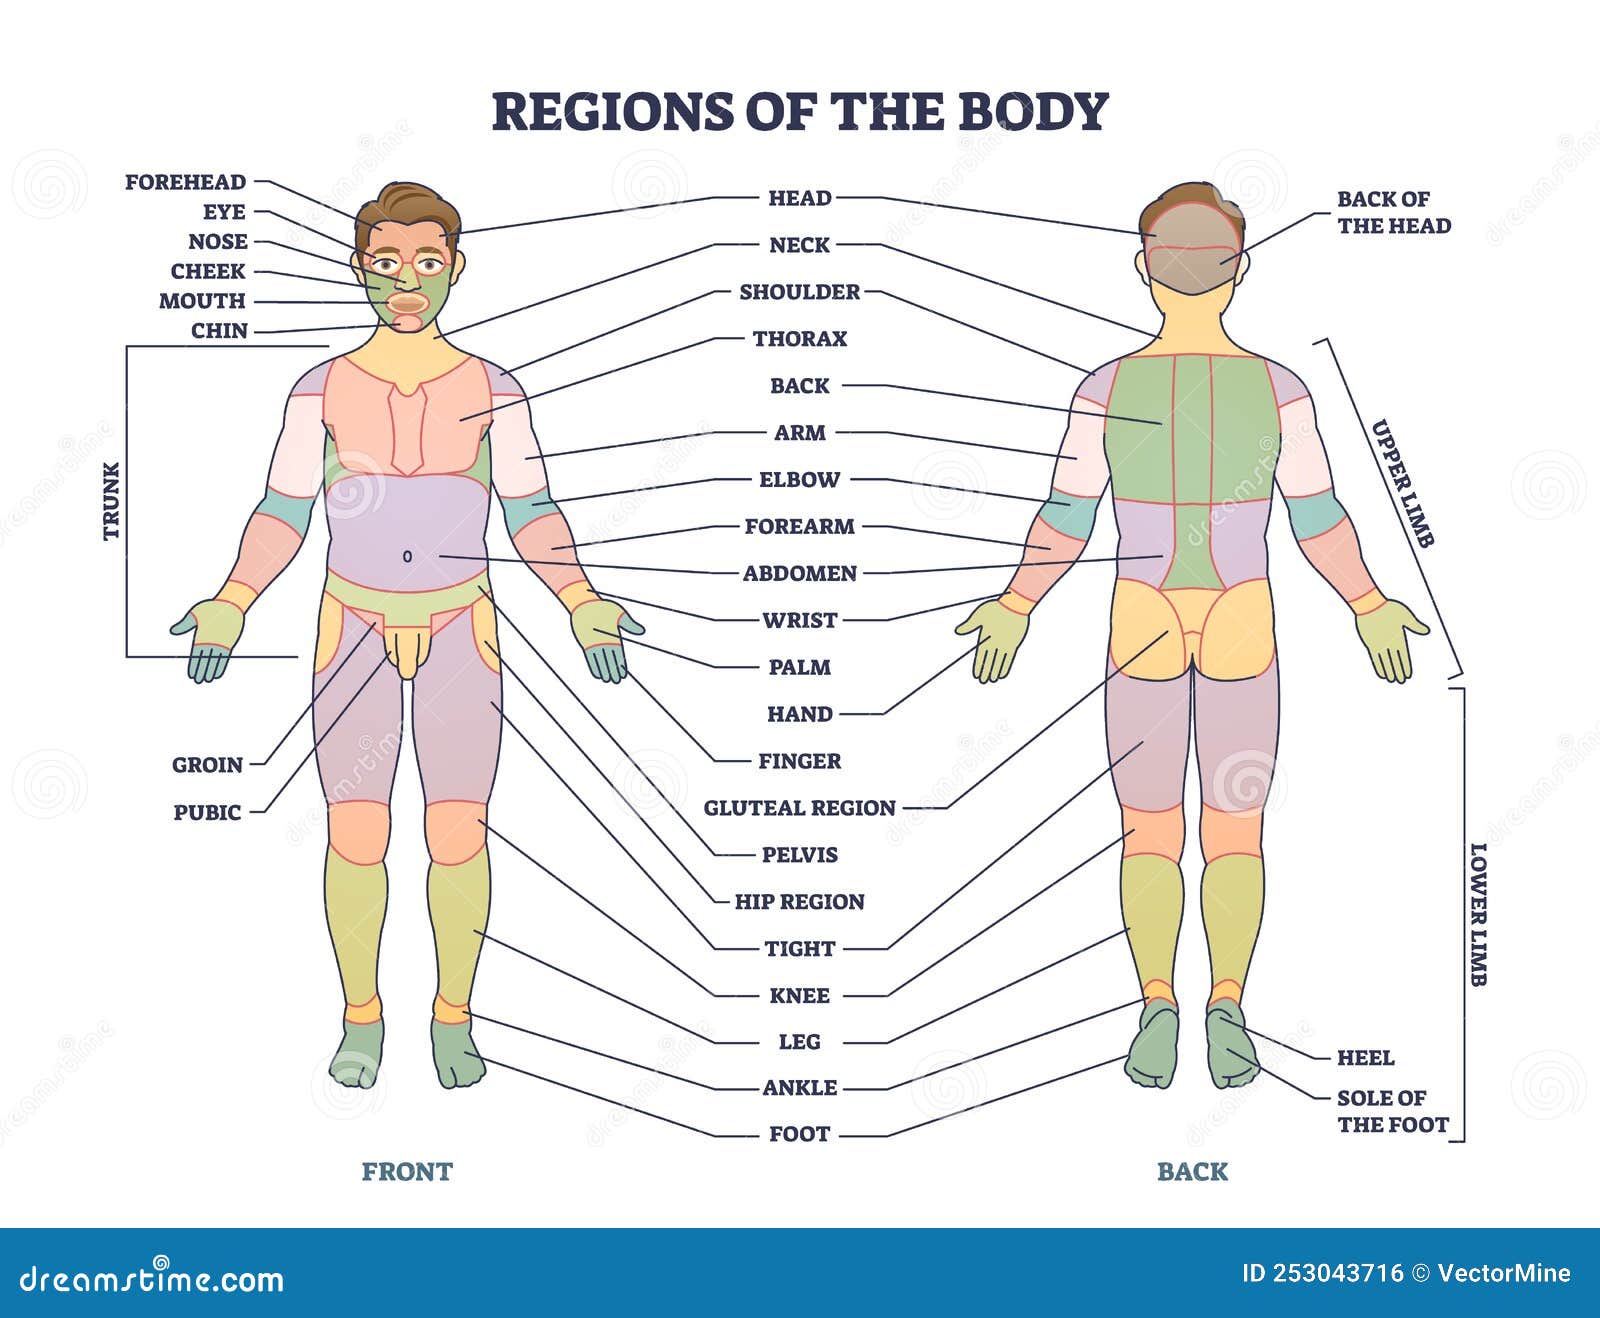
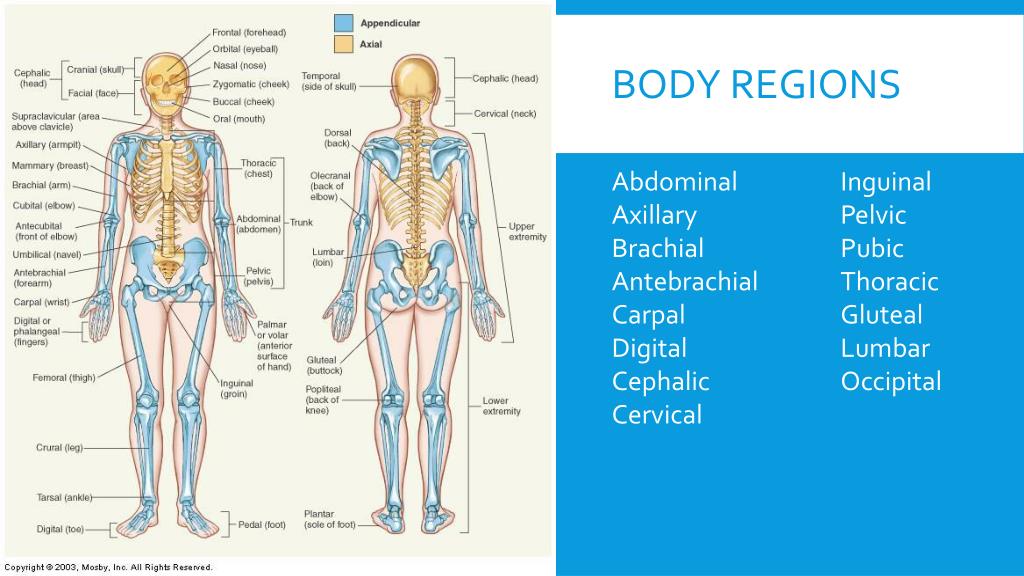
Most people learning anatomy or working in clinical settings get confused by the sheer number of ways the body can be subdivided. There is no single official list. Different fields use different regional frameworks depending on what they need to track. When I first started dealing with Regions Of The Body in a clinical documentation context, I wasted months trying to force everything into one system. It does not work. You have to pick the right framework for your use case. The most common approach comes from gross anatomy and radiology. The body is divided into the head and neck, thorax, abdomen, pelvis and perineum, upper limbs, and lower limbs. Within each of those, further subdivisions exist. The anterior and posterior compartments of the thigh, for instance, are treated as entirely separate regions for clinical and surgical purposes. This matters because nerves and blood supply differ between them. Another framework you will encounter is in medical coding and injury tracking, especially workers compensation claims. There, regions are grouped differently. Instead of "thorax" you might see "trunk," and the cervical spine gets separated from the head and neck entirely. If you are building a Regions Of The Body mapping tool for insurance or claims processing, using the anatomical framework will cause mismatches that are painful to debug.
How To Build A Practical Body Region Map
I spent about three weeks building a simple region-tracking spreadsheet for a small physio clinic. The goal was straightforward: therapists needed to record which body regions a patient presented with on each visit and track progress over time. Here is what I learned about doing it without overcomplicating things. Start by deciding on your base divisions. I used a nine-region model: head, neck, shoulders, chest and back, upper arms, forearms and hands, abdomen and lower back, thighs, and lower legs and feet. This was deliberately broader than anatomical precision because the therapists did not need that level of granularity for their daily workflow. Each region could then be split into left and right when necessary. That gave us 18 distinct entries maximum per patient session. The next decision was how to handle overlapping presentations. A patient coming in with lower back pain that radiates into the left leg and foot does not fit cleanly into one region. I built a multi-select system where therapists could tag up to three regions per visit, plus a free-text field for notes. This prevented the "which region does this actually belong to" debate that stalls documentation.
One edge case I ran into was shoulder pain that refers to the elbow. The patient and therapist both identified the elbow as the problem area, but the underlying issue was clearly originating in the shoulder complex. If you are just tracking patient-reported regions, you will misclassify this repeatedly. My workaround was adding a separate "primary complaint region" field alongside the symptom regions. The primary region captured where the therapist assessed the origin, while the symptom fields captured what the patient actually felt. This distinction alone reduced our follow-up correction requests by roughly sixty percent over a six-month period.
Get the Full Details
Common Mistakes People Make With Body Region Systems
The first mistake is treating the body as a flat list of regions. It is not. The body has layers and planes. An injury in the gluteal region might involve deep musculature, superficial fascia, and nerve roots at completely different anatomical levels. When your system forces everything into a single region dropdown, you lose that dimensional information. I stopped trying to capture layer detail in the primary fields and instead used a secondary tagging system for depth. Superficial, intermediate, deep. That addition took maybe ten extra seconds per patient entry and made follow-up assessments significantly more useful. The second mistake is not accounting for midline structures. The sternum, spine, sacrum, and anterior abdominal wall do not belong to the left or right side. Some systems simply duplicate the region on both sides, which inflates data and makes statistical analysis messy. A few better systems create a dedicated "midline" category for exactly these structures. It is a small change but it prevents corruption of your data. A third mistake is assuming regional terminology is universally understood across disciplines. A physical therapist, an emergency physician, and a fitness trainer might all say "lower back" and mean three subtly different anatomical areas. In my experience, the term "lower back" used loosely spans from the eleventh thoracic vertebra down to the sacroiliac junction. Therapists tend to mean lumbar only. Physicians sometimes include the thoracolumbar transition zone. Building a small internal glossary that defines each region's boundaries in your organization cuts down on documentation inconsistency considerably.
Regions Of The Body For Clinical Documentation Purposes
If you are implementing this for a practice, the most efficient setup I have found uses a structured form with conditional logic. Selecting "neck" reveals subcategories for cervical spine, cervical paraspinals, and cervicogenic referral patterns. Selecting "upper limb" reveals a branching tree: shoulder, elbow, wrist, hand, and individual digits. The conditional logic keeps the form short for simple cases while preserving depth for complex ones. Data export is another consideration that people overlook until it is too late. If you plan to analyze trends over time, your region definitions need to be stable. Changing the boundary between "upper back" and "lower back" halfway through a year of data will break any longitudinal comparison you try to run. Lock your region definitions once you publish them and resist the urge to refine them mid-project. You can always add a new region, but you cannot go back and reclassify historical entries. I also learned that the pelvic and perineal regions cause the most documentation hesitation among therapists. Patients are often reluctant to discuss symptoms in that area, and some clinicians avoid documenting it even when relevant. A well-designed system includes these regions by default but allows them to remain blank without triggering an error. Forcing completion on sensitive regions creates false data, which is worse than missing data.
Where This Approach Falls Short
A static region system cannot capture functional movement patterns. Two patients might both have "left lower leg" marked as their region, but one has a calf tightness issue from overuse while the other has a neuropathic problem originating from L5-S1 root compression. The region label is identical. The clinical picture is completely different. If your goal is treatment planning, the region system is a starting point, not a complete solution. You still need subjective and objective assessment data to distinguish between them. Another limitation is that pediatric bodies do not map neatly onto adult regional frameworks. A child's anatomy changes significantly as they grow, and some region boundaries shift proportionally. If you are applying an adult-based region system to pediatric patients, expect to adjust your definitions or flag pediatric cases separately. For most practical purposes, a well-structured regional system covers the majority of documentation needs. But if you are working in a specialized area like sports science or chronic pain management, you may find that a region-based approach alone leaves gaps. In those cases, combining it with a functional movement screen or a pain diagram approach tends to fill the void better than expanding the region list itself.