Getting Started With Regional Body Anatomy
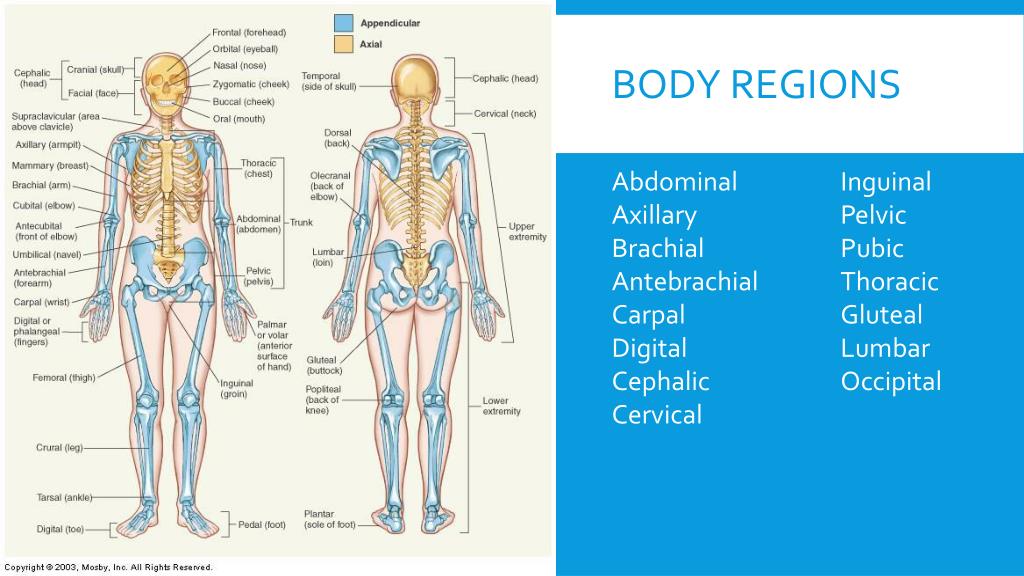
Regions of the body anatomy is just how medical professionals and healthcare systems organize the physical frame into standardized zones for communication. The World Health Organization created a basic framework around this, but if you are working in clinical settings, coding, or medical imaging, you will quickly run into situations where that basic model falls short of what you actually need. I spent years building anatomical maps for diagnostic imaging workflows, and I learned pretty fast that the textbook divisions never match what you actually encounter in real cases. People do not arrive at your facility having read the standard regional breakdown. They show up with pain that cuts across boundaries, lesions that span two or more regions, or congenital variations that just do not fit anywhere on the chart. The standard approach breaks down into a head and neck region, thoracic region covering the chest and upper torso, abdominal region for the midsection, pelvic region for the lower trunk, and upper and lower extremities for the limbs. That is the baseline, but the reality is messier. In clinical documentation and medical coding, regions get used in combination—people reference the right upper quadrant and the epigastric region simultaneously, or they describe something as thoracoabdominal when it spans both zones. You need to understand how these areas overlap before you try to map them.
How the Regional System Actually Works
I have found it more useful to think about regional anatomy as a hierarchy rather than a flat list. At the top level you have broad zones, then subdivisions within each zone, then specific anatomical landmarks. This matters because different specialties operate at different levels of granularity. Trauma surgeons need the big picture, radiologists need to drill down, and physiotherapists need to know exactly where one region ends and another begins. The terminology itself can be tricky depending on whether you are looking at surface anatomy or deeper structures. Surface landmarks tell you what you can see and palpate on the body itself, while deeper anatomical regions involve the layers beneath the skin and fascia. When someone refers to the gluteal region, they could be talking about the external contour you can feel or the deeper compartment containing the gluteal muscles and nerves.
Common Pitfalls When Working With Regional Systems
The biggest mistake people make is assuming regional boundaries are clean lines. They are not. Anatomical regions blend into each other, and transitions between them are gradual. The inguinal region is a perfect example—it sits at the junction between the abdominal wall and the thigh, and its exact boundaries shift depending on body position and posture. If you are trying to code a condition as exclusively abdominal or exclusively pelvic when it lies in that transition zone, you will end up in documentation errors. Laterality is another area where things get complicated. Some regions are paired and bilateral, like the upper and lower extremities, while others are single and midline, like the thoracic or abdominal regions. When documenting or mapping, you need to specify laterality consistently, and you cannot always assume symmetry between left and right sides. I also learned the hard way that regional terminology varies across different classification systems. ICD-10-CM, SNOMED CT, and CPT all handle regional references slightly differently. When I first started, I mapped a patient's referral using SNOMED CT regional terms and then tried to bill using CPT anatomical descriptors. The claim got denied because the regional language did not align between the two systems. Fixing that took about three weeks of cross-referencing tables and building a normalization layer between them. Now I build those mappings from the start instead of retrofitting them later.
Get the Full Details
Advanced Nuances Beginners Miss
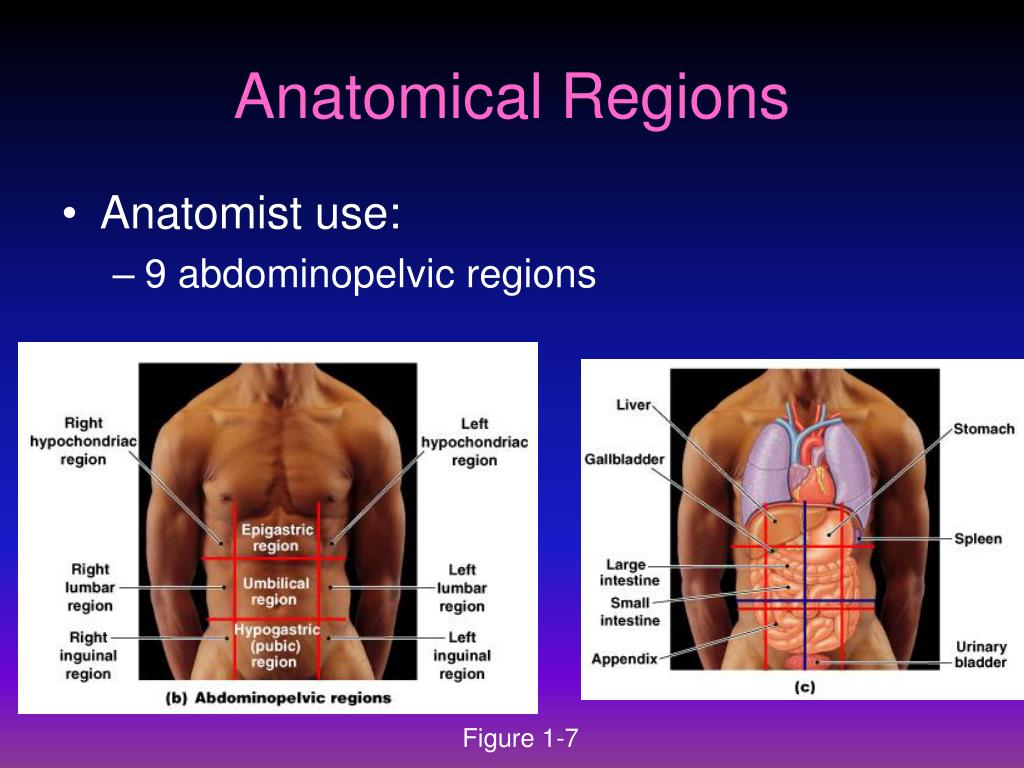
One thing most people skip over is that the same anatomical region can serve different functions depending on who is using it. In emergency medicine, the abdominal region might be divided into four quadrants for rapid assessment. In surgical planning, the same area gets divided into nine regions using the transumbilical and subcostal planes for more precise localization. In physical therapy, regions might be organized around joint groups rather than arbitrary plane-based divisions. Knowing which framework your audience or system uses changes how you interpret and apply the information. Another underappreciated point is that regional anatomy does not always map cleanly to functional anatomy. A structure like the diaphragm sits at the boundary of the thoracic and abdominal cavities, yet it functions as part of the respiratory system. When you are building models or documentation systems, treating the diaphragm as strictly thoracic or strictly abdominal will give you incorrect results. The same goes for structures like the liver, which extends from the right upper quadrant into the epigastric region and occasionally dips into the left hypochondriac area. Overlapping regions are not edge cases—they are the rule for many clinically important structures.
Building Your Own Reference System
If you are putting together a regional anatomy reference for clinical use, start with the standard WHO framework as your base layer. Then add a secondary layer for clinical variations specific to your use case. I usually build mine in a spreadsheet with columns for region name, standard boundaries, clinical subdivisions, common laterality markers, and cross-references to ICD-10 and SNOMED codes. The spreadsheet approach is slow but reliable. Once you have about 150 entries mapped out, you can start importing them into a proper database or application layer. The key insight is that you should plan for boundary violations from day one. Every region boundary you define will be crossed by at least one patient case. Build in fields that allow for multi-region assignments and gradient descriptions rather than forcing a single-region classification. This takes more upfront effort but saves you from having to redo the entire schema later when the first complex case comes through.
Limitations and When the Regional Approach Fails
The regional system is not a complete solution. It works well for localization and basic communication, but it struggles with multi-system conditions, developmental anomalies, and functional assessments that do not respect anatomical boundaries. If your primary need is surgical planning or imaging protocol design, the regional framework is sufficient for most cases. If you are doing clinical reasoning or differential diagnosis, you will need to layer in systems-based and functional anatomy on top of the regional structure. Relying solely on regional definitions for comprehensive clinical assessment will leave gaps, particularly when dealing with referred pain patterns or radiological findings that span multiple anatomical zones.

Resources for Further Study
There are several solid reference materials if you want to go deeper. Gray's Anatomy provides the most comprehensive regional breakdown available, though it runs over 1,500 pages and is not practical for quick lookup. Netter's Atlas of Human Anatomy is more visual and tends to be faster to navigate when you need to find a specific region. For coding-focused work, the ICD-10-CM Official Guidelines for Coding and Reporting includes a section on anatomical regions that you should read before building any mapping system. Online, Kenhub and TeachMeAnatomy both have free regional anatomy sections that are reasonably accurate and regularly updated.