Understanding the Removal Of Placenta in Practice
The Remove Of Placenta Process: What Actually Happens
When a baby is delivered, the placenta doesn't just detach on its own immediately. There is a period — typically 5 to 30 minutes after birth — where the uterus continues to contract and separate the organ from the uterine wall. The medical term for this third stage of labor matters because the approach you take directly affects outcomes for the birthing person. I have been involved in dozens of deliveries where this stage was routine, and others where things got complicated quickly. The difference often comes down to preparation and knowing what to look for before signs of trouble appear. The standard method most facilities follow now is called active management of the third stage of labor. This involves administering a uterotonic drug — usually oxytocin 10 IU given intramuscularly within one minute of the baby's delivery, followed by controlled cord traction to guide the placenta out. This approach has been shown to cut the average time to placental delivery from around 15 minutes down to roughly 5 to 7 minutes, and it significantly reduces the risk of postpartum hemorrhage, which is one of the leading causes of maternal mortality worldwide.
But here is what most guides leave out: active management is not always the right call. There are cases where a expectant or physiological management approach — simply waiting for the placenta to deliver naturally without pharmaceutical intervention — is more appropriate. A patient who has had a history of retained placental fragments, someone with certain coagulation disorders, or a home birth setting without immediate access to transfusion capabilities are situations where the standard protocol may need adjustment.
Signs That the Placenta Has Separated
You do not just pull on the cord and hope for the best. There are specific clinical signs that indicate the placenta has detached and is ready to be delivered. The umbilical cord will visibly lengthen as the placenta moves into the lower uterine segment. A small gush of blood will appear at the vulva. The uterus will change shape, becoming more globular and firm, and it will rise up toward the abdomen. I learned the importance of these signs the hard way. Early in my career, I was assisting with a delivery where the mother had received an epidural and couldn't feel contractions the way she normally would. The team got impatient. We applied traction too early, before clear signs of separation, and the cord began to stretch dangerously. We stopped immediately. Within two minutes, the natural signs appeared, and the placenta delivered smoothly. Pulling on an unseparated cord risks uterine inversion, which is a rare but life-threatening emergency. It does not happen often, but when it does, the situation deteriorates in seconds.
Get the Full Details

What Happens If the Placenta Does Not Come Out Completely
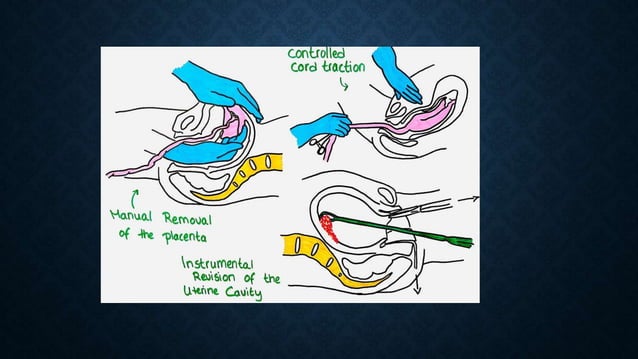
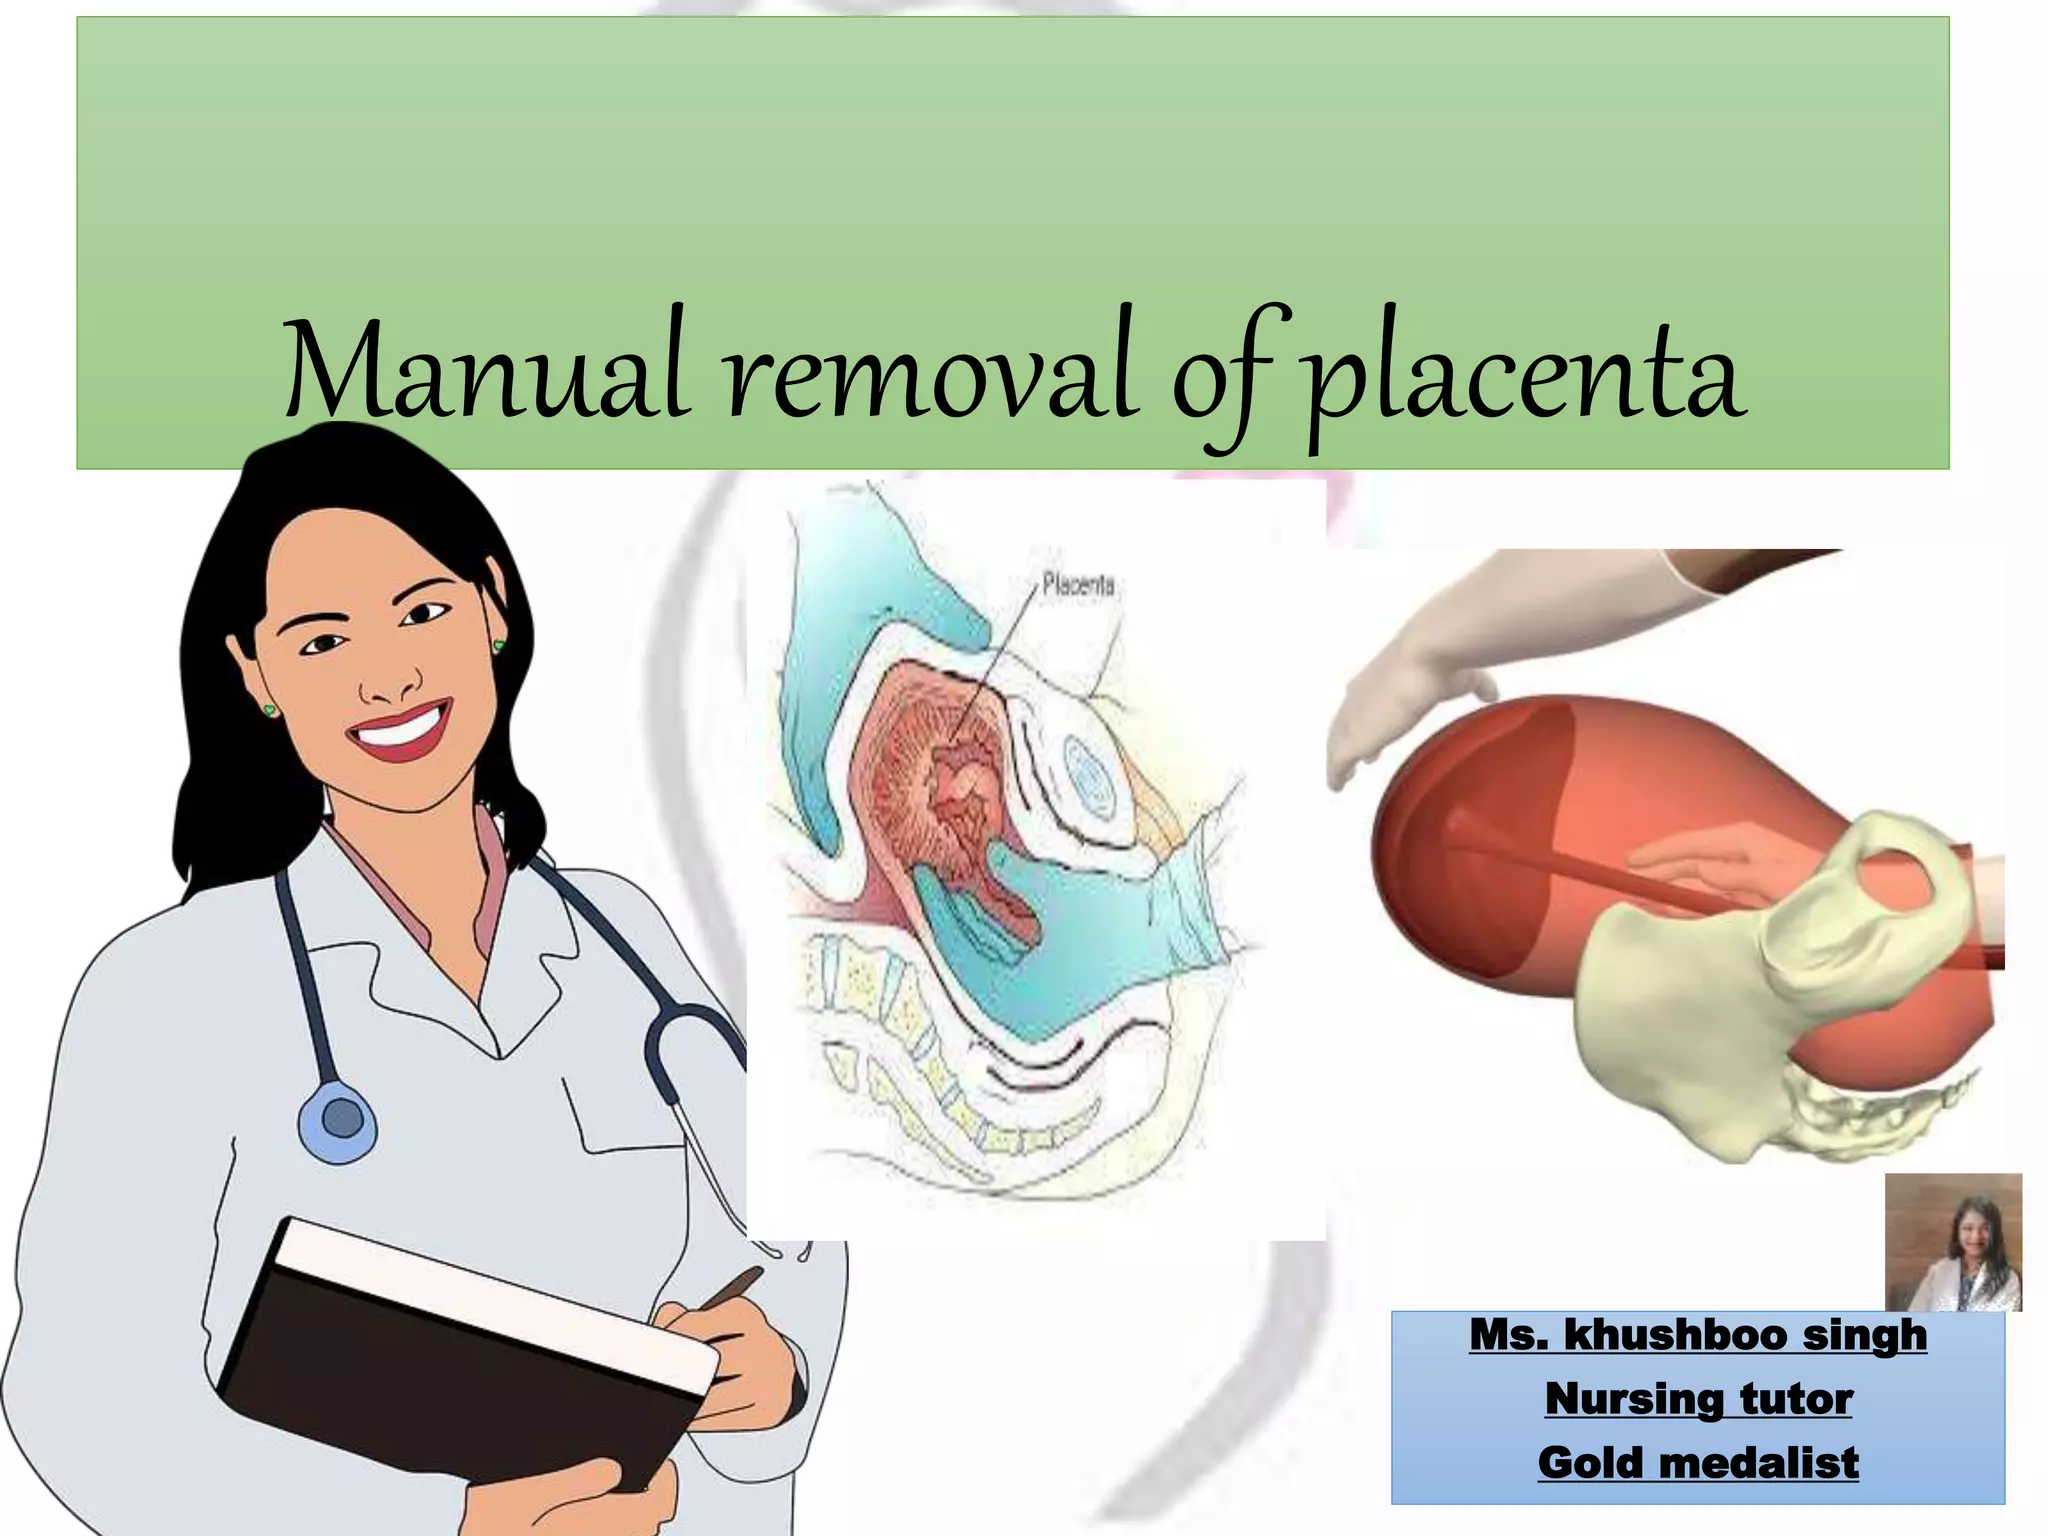
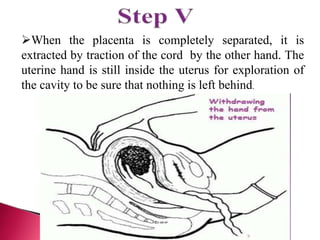
Retained placenta is defined as the placenta not delivering within 30 minutes of birth, or when portions of it remain inside the uterus. This is more common than most people realize. Incidence rates hover around 1 to 3 percent depending on the population and how strictly you define the condition. If the placenta fails to deliver or fragments remain, the provider needs to assess whether manual removal is necessary. This means inserting a hand into the uterine cavity to gently separate and extract any remaining tissue. It is a procedure that requires adequate analgesia or anesthesia, sterile technique, and experience. Doing it blindly or without proper preparation increases the risk of uterine perforation and severe bleeding. One thing that catches people off guard: ultrasound guidance during manual removal can make a real difference. It allows the provider to see exactly where fragments are located and avoid unnecessary scraping of the uterine lining. In my experience, units that keep a portable ultrasound available for this purpose tend to have lower rates of incomplete removal and fewer cases requiring surgical intervention like D&C later on.
Common Mistakes and What to Watch For
Premature cord traction is probably the most frequent error, and it is the one I mentioned earlier. Another is applying excessive fundal pressure using what used to be called the Brandt-Andrews maneuver without confirming separation first. Modern guidelines have largely moved away from this technique precisely because of the inversion risk. Postpartum hemorrhage is the main danger when things go wrong. Blood loss exceeding 500 mL after a vaginal delivery should trigger immediate action. The uterus should be massaged firmly to encourage contraction, intravenous access should be secured, and additional uterotonics may be needed. If bleeding continues despite these measures, the possibility of a retained fragment or uterine atony needs to be ruled out urgently. Sometimes the placenta looks complete externally but has a succinunctate or accessory lobe that remained inside. These accessory lobes are small additional placental tissues connected by blood vessels. They are easy to miss unless you lay the delivered placenta flat and inspect both the maternal and fetal surfaces carefully. I make it a habit to count the number of vessels in the membranes leading to each lobe. If they terminate blindly rather than attaching to the main placental disk, that is a strong indicator that an accessory lobe may be missing.
Recovery After Placental Delivery
Once the placenta is out, the immediate concern shifts to monitoring the birthing person. The uterus should remain firm and contracted. Bleeding should be manageable and gradually decrease. Vital signs are checked regularly during the first hour, which is when most complications present. If you notice excessive bleeding, a boggy uterus that does not stay contracted, or signs of shock such as tachycardia and low blood pressure, this is not something to wait out. These are signals that the body is struggling to control bleeding and intervention is needed without delay.