The Biology Is Less Romantic Than Textbooks Make It Sound
Most people think reproduction is just two cells meeting and some magic happens. I spent seven years working in reproductive endocrinology before leaving the field because the burnout was real. What follows is the actual mechanics, stripped of the poetic nonsense you see in wellness blogs.
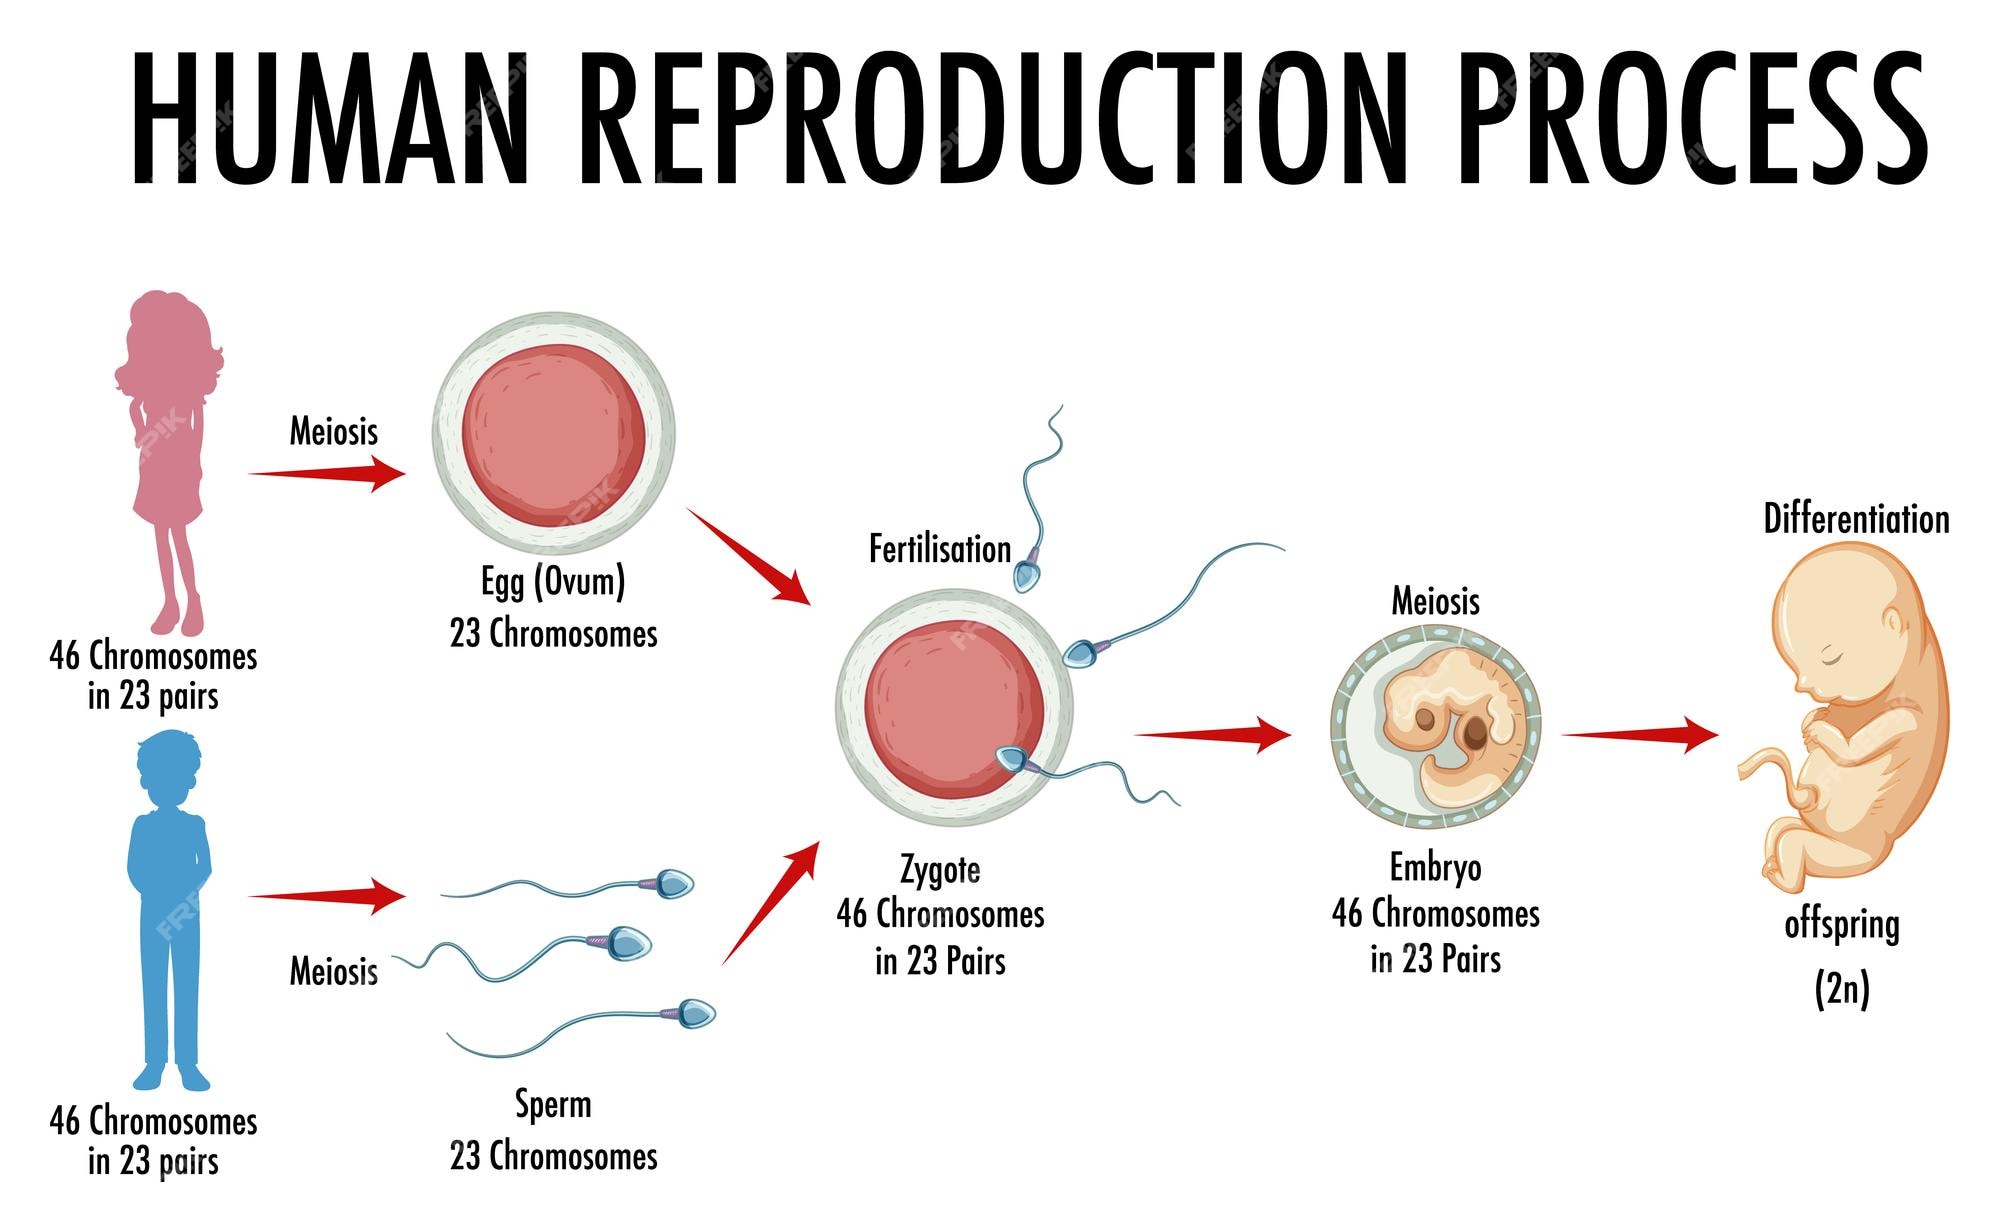
The fundamental process involves gamete production, fertilization, embryonic development, and birth. That is it. Four steps. But each step has failure modes that account for roughly 30% of attempted conceptions not resulting in live birth. You should know that before you start.
Reproduction Of A Human: The Actual Mechanics
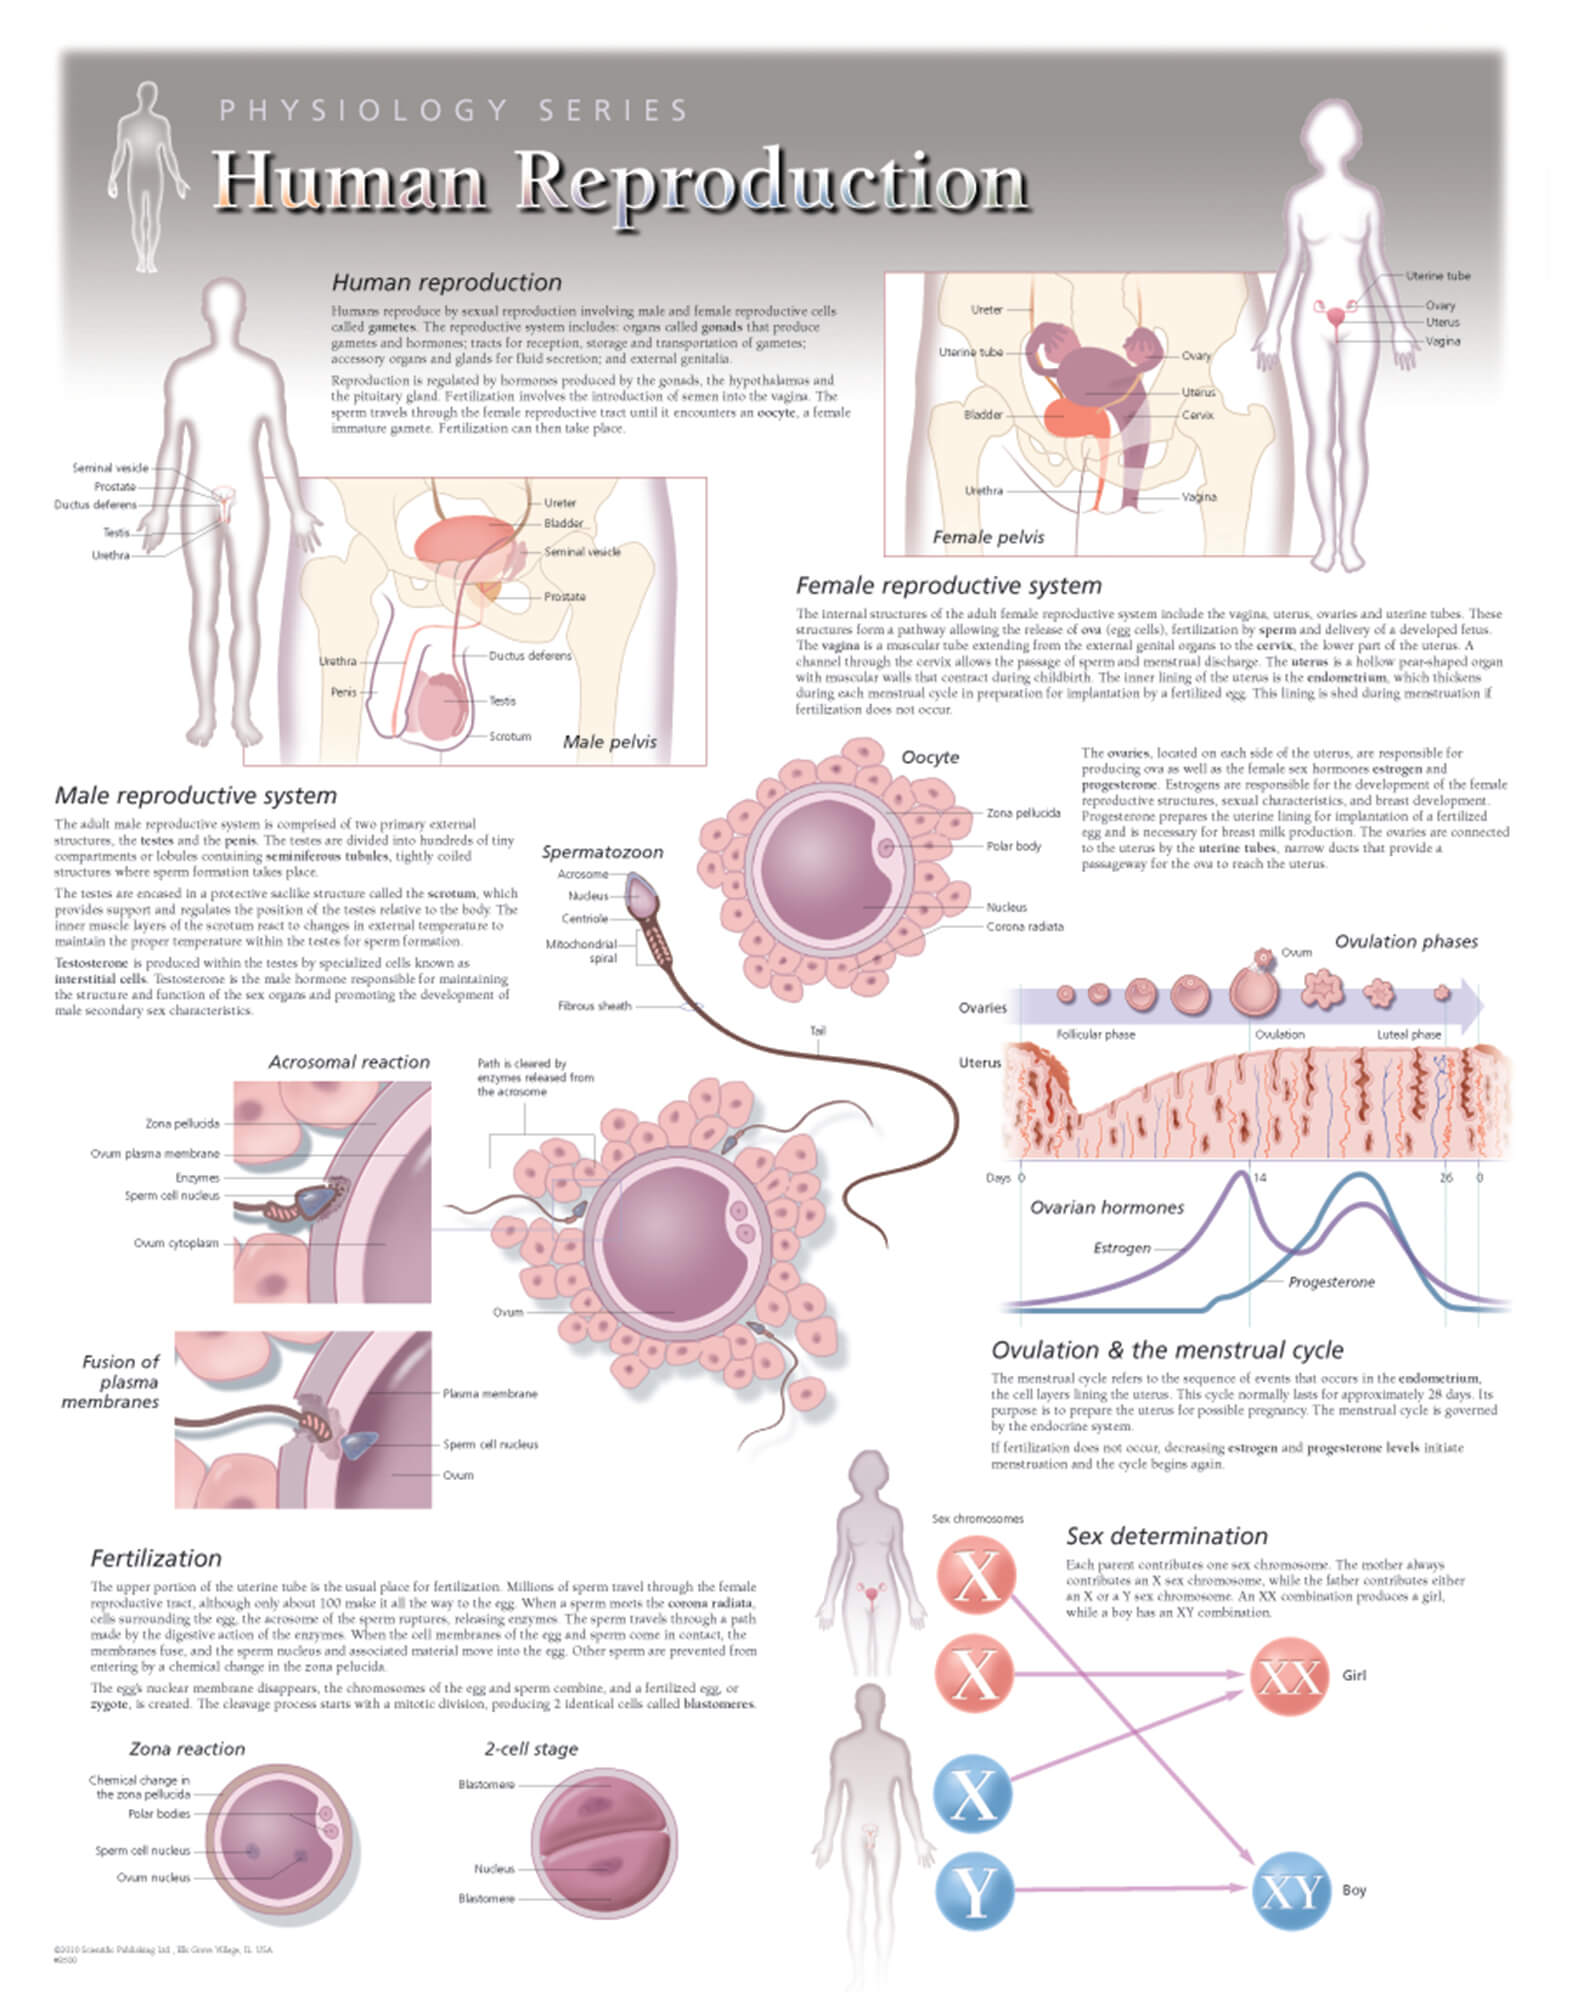
Gametogenesis happens in the gonads. Males produce sperm continuously after puberty through a process called spermatogenesis, which takes about 74 days from start to finished cell. Females are born with all the oocytes they will ever have, roughly one to two million at birth, declining to about 300,000 by puberty, and maybe 400 will actually be ovulated over a lifetime. The asymmetry here is brutal and most people do not appreciate it.
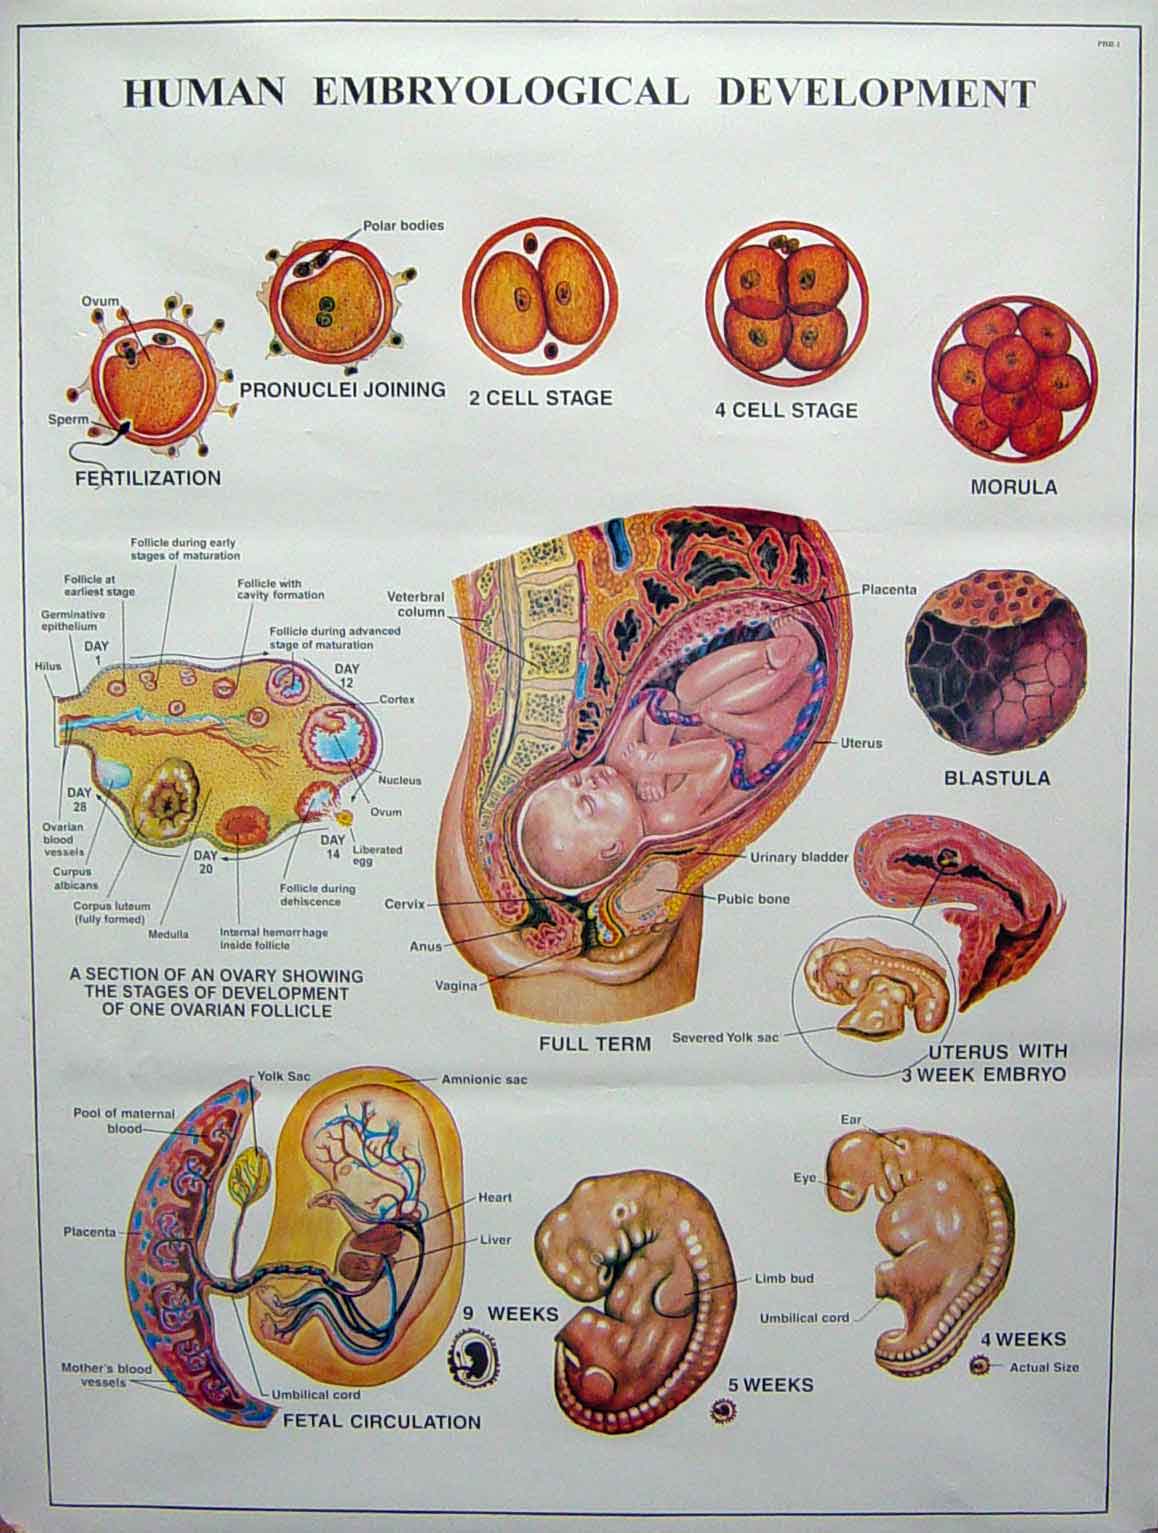
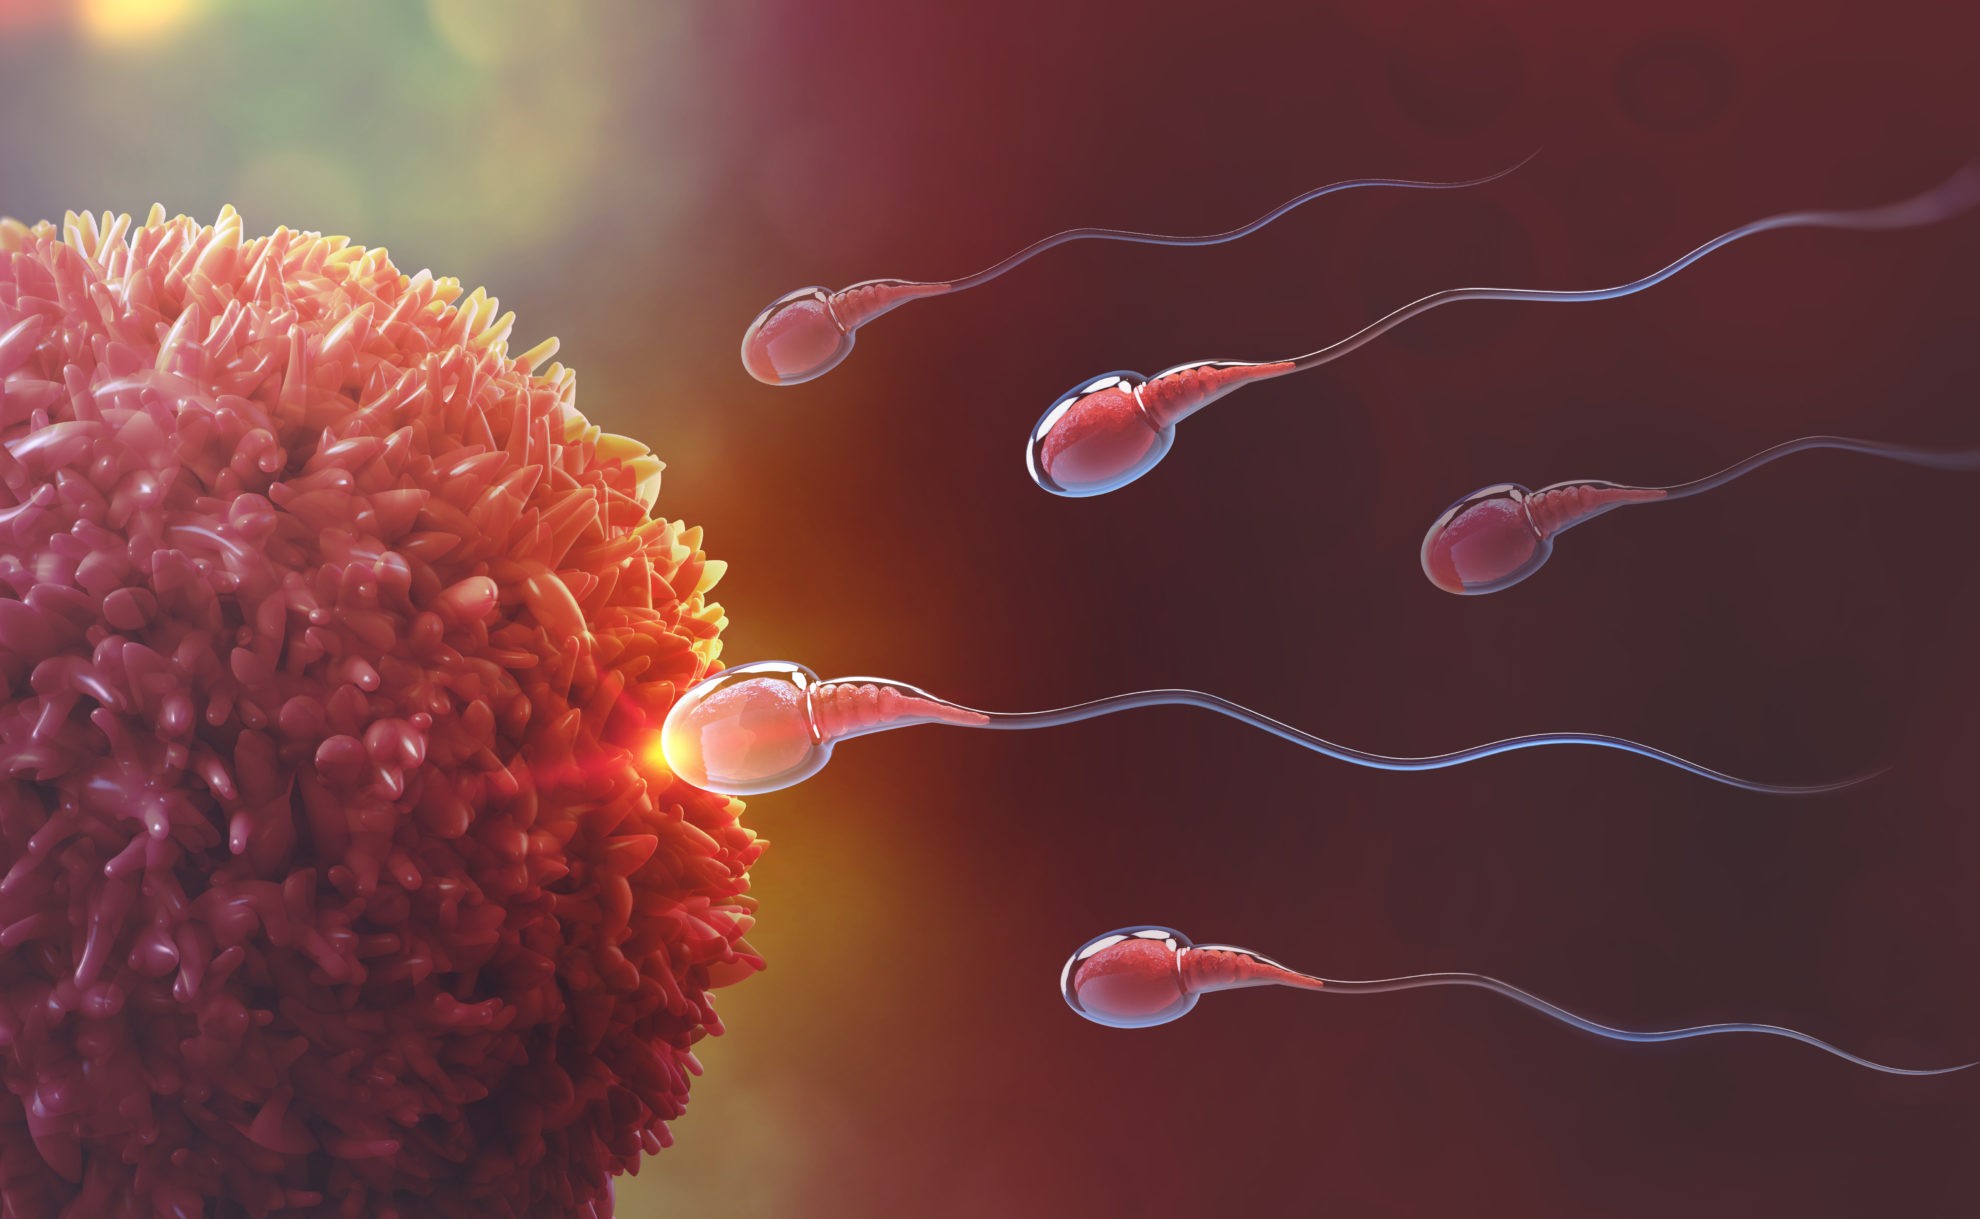
Fertilization occurs in the fallopian tube, usually the ampulla region. A single sperm penetrates the cumulus mass surrounding the oocyte, then the zona pellucida. Once one sperm gets through, the oocyte undergoes a cortical reaction that hardens the zona and prevents polyspermy. This is why IVF labs spend so much time on ICSI — when you bypass the natural barrier, you also bypass the quality control.
Implantation happens roughly six to ten days after fertilization. The embryo, now a blastocyst, hatches from the zona pellucida and adheres to the endometrial lining. Only about 30% of blastocysts successfully implant. The rest either fail to attach or get reabsorbed before anyone knows anything happened. This is why pregnancy tests can show false negatives in the first week.
The Hormonal Cascade Nobody Explains Well
Hypothalamus releases GnRH in pulses. Pituitary picks it up and secretes FSH and LH. Ovaries respond by developing follicles and producing estrogen. When estrogen peaks, it triggers the LH surge. The LH surge causes ovulation about 36 hours later. If sperm are present, fertilization occurs. If not, the corpus luteum degenerates, progesterone drops, and menstruation begins.
This cycle runs every 21 to 35 days in healthy adults. The variability matters. I had a patient who tracked her cycles for two years and still could not predict ovulation within a three-day window. Her cycle length ranged from 26 to 41 days. She eventually conceived through timed IUI after we identified she was ovulating later than her tests suggested.
The luteal phase — the time between ovulation and menstruation — is remarkably constant at about 14 days. It is the follicular phase before ovulation that varies. This means if you want to understand your fertile window, counting backward from your expected period is more reliable than counting forward from your last period.
Common Pitfalls and What I Actually Saw in Practice
The biggest mistake people make is assuming conception is a single event. It is not. It is a chain of about 40+ biological steps, and any single failure point ends the process. Sperm need to survive in the female reproductive tract for up to five days. The egg is viable for about 12 to 24 hours after ovulation. The embryo needs to divide correctly through cleavage stages. It needs to hatch from the zona. It needs to implant at the right depth and position. The maternal immune system needs to tolerate it rather than reject it. Any one of these can go wrong.
I saw a couple go through three failed IVF cycles before we realized the issue was not the embryos or the uterus. It was a subtle NK cell imbalance in the endometrium that was attacking the implanting blastocyst. We treated with intralipids and prednisone, and she conceived on the fourth transfer. That is the kind of thing standard protocols miss.
Another common error is the assumption that male factor is simple. Semen analysis looks at count, motility, and morphology. But sperm also need to undergo capacitation in the female tract, and the acrosome reaction needs to work properly. A man can have "normal" parameters and still have functional defects that prevent fertilization. This is why ICSI exists — sometimes you just need to physically inject the sperm into the egg.
The Numbers That Actually Matter
For a healthy couple under 35 having regular intercourse without contraception, the chance of conception per cycle is approximately 20 to 25%. That drops to about 15% between ages 35 and 40, and below 5% after age 45 for natural conception. These are cumulative numbers, not guarantees. Some people conceive in month one. Some try for twelve years.
Miscarriage occurs in roughly 10 to 20% of clinically recognized pregnancies. The number is likely higher when you include pregnancies that end before detection. About 50 to 70% of miscarriages are due to chromosomal abnormalities in the embryo, mostly random errors in meiosis. This is nature's way of weeding out nonviable pregnancies, and there is nothing you can do to prevent most of them.
Ectopic pregnancy affects about 1 to 2% of pregnancies. The embryo implants outside the uterus, usually in the fallopian tube. This is a medical emergency because the tube cannot stretch to accommodate growth. Early detection through serial beta-hCG testing and transvaginal ultrasound saves lives.
What I Would Tell My Younger Self
Reproductive biology is messy, inefficient, and often unfair. The human body is not designed for reproductive success in the modern sense. It is designed for survival in an environment that no longer exists. Our ancestors needed women to reproduce quickly and repeatedly because infant mortality was high. Modern medicine has decoupled reproduction from immediate survival, but the biology has not caught up.
If you are struggling to conceive, the standard advice is to try for twelve months before seeking help if you are under 35, or six months if you are over 35. I think this is reasonable but arbitrary. If you have known risk factors — irregular cycles, history of pelvic inflammatory disease, endometriosis, prior cancer treatment — seek evaluation sooner. Do not wait.
The emotional toll of reproduction problems is severe. It affects relationships, self-image, financial stability, and mental health. I watched strong people break under the pressure of repeated failures. Support systems matter. Therapy matters. Setting boundaries with well-meaning but insensitive friends and family matters.
Resources and Next Steps
If you want to understand your own reproductive health, start with basic tracking. Record cycle length, ovulation signs, and any symptoms. Apps like Clue or Flo can help, but do not trust them blindly. They are prediction engines, not diagnostic tools.
For clinical information, the American Society for Reproductive Medicine (ASRM) publishes patient-friendly guidelines at aspirative.org. The Endometriosis Foundation of America offers support and education at endometriosisafrica.org. For male fertility concerns, the Andrology Society of America has resources at andrologysociety.org.
I stopped practicing clinical reproductive medicine five years ago. The field has moved toward genetic screening of embryos, ovarian reserve testing, and increasingly sophisticated hormonal protocols. The science advances faster than most patients can process it. If you are navigating this yourself, bring a notebook to appointments, ask questions, and do not accept vague answers. You deserve to understand what is happening to your body.
Gallery Reproduction Of A Human
Human Reproduction - Scientific Publishing
Human Reproduction Diagram With Explanation
Human reproduction GCSE FULL UNIT | Teaching Resources
Human Reproduction and Fertilization - Biology Online Tutorial
Human Reproduction - Male and Female Systems, Fertilization, and Pregnancy