How The Human Respiratory System Actually Works
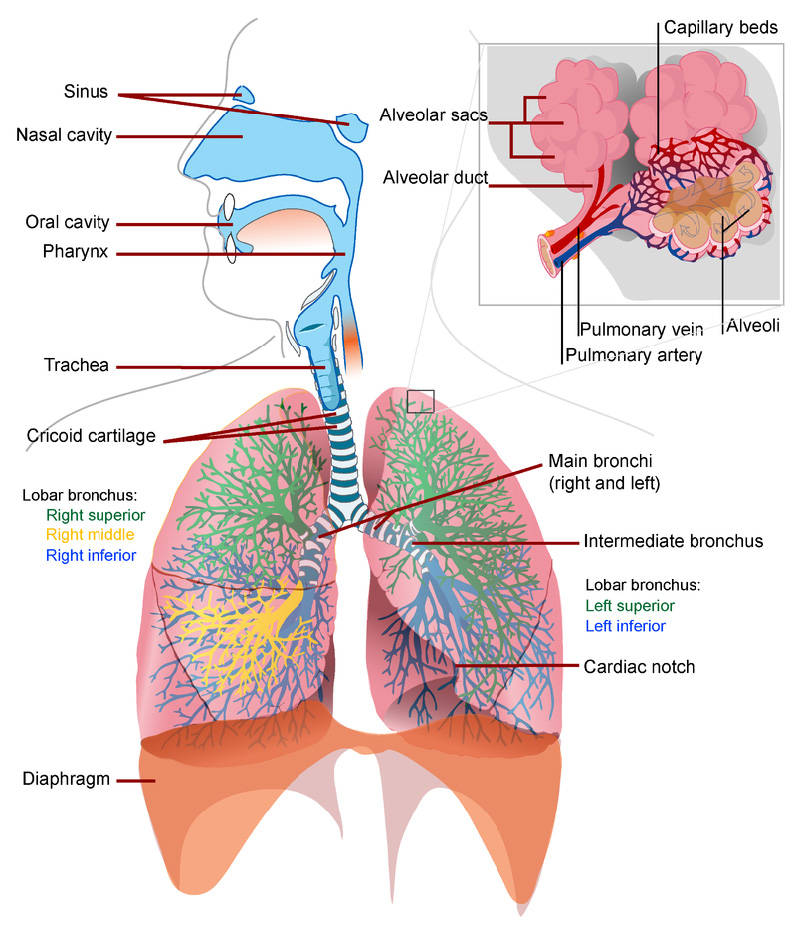
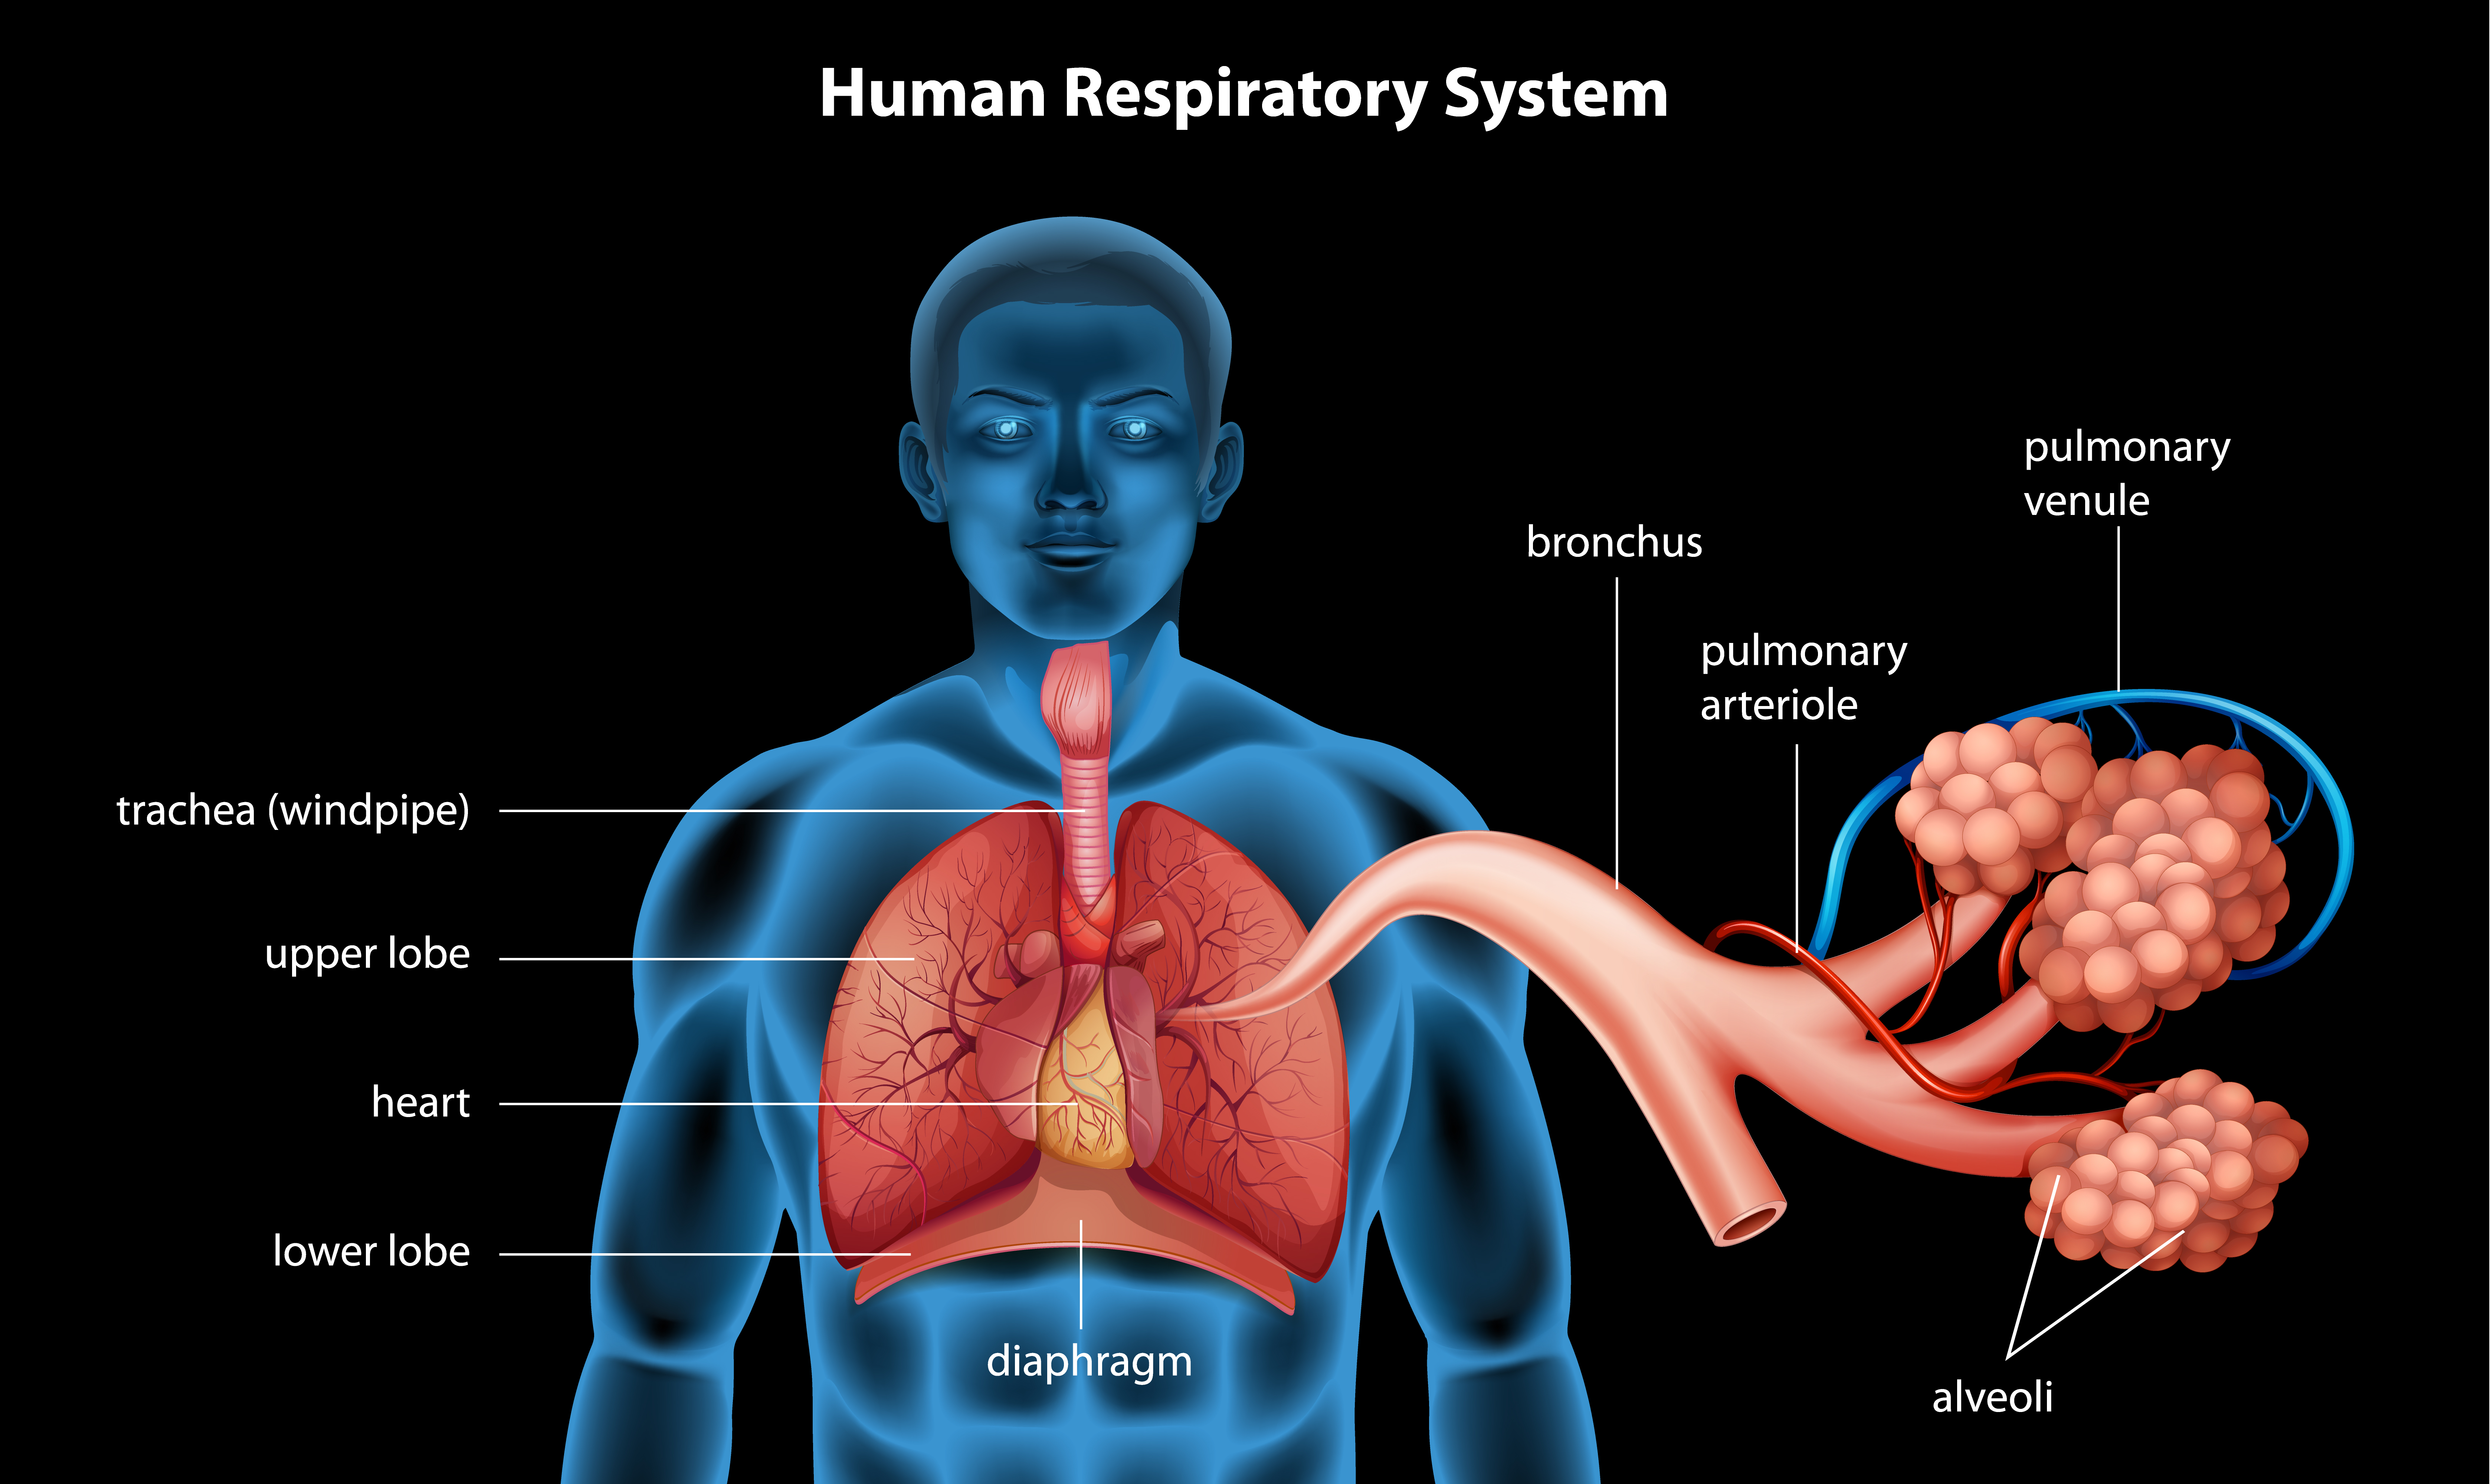
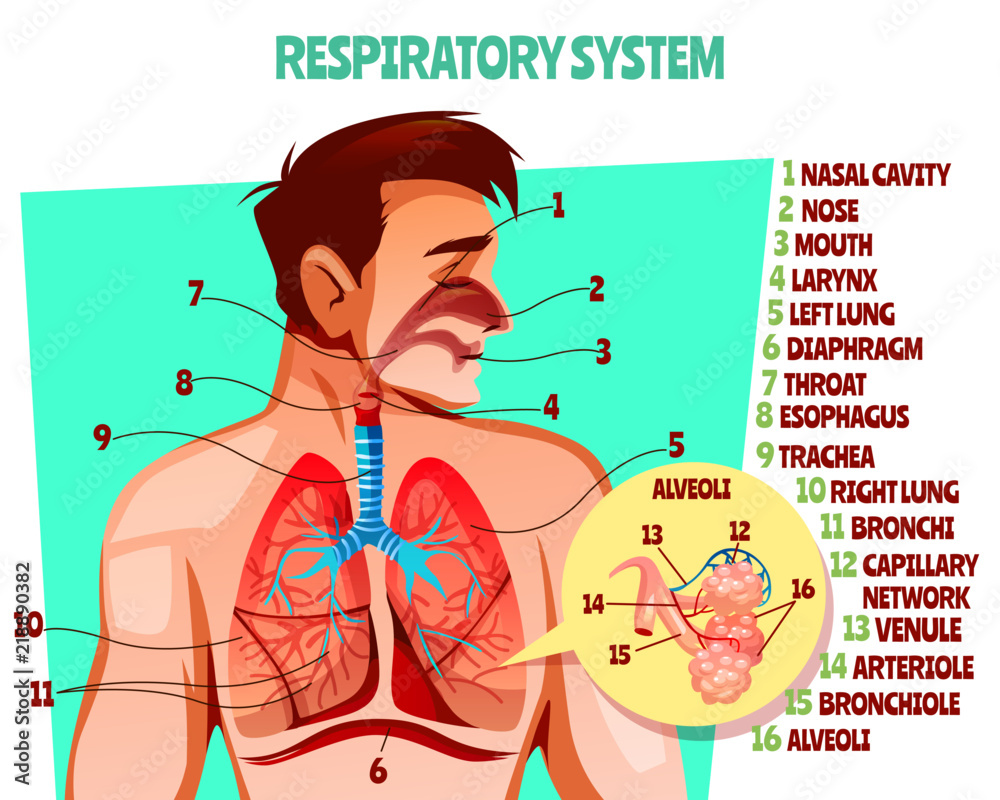
The respiratory organ of human is a gas exchange machine, not some mystical breathing thing. Air enters through the nose or mouth, travels down the pharynx, passes the larynx, and goes through the trachea before splitting into the two bronchi. From there it fans out into smaller and smaller bronchioles until it hits the alveoli, where oxygen actually crosses into the blood and carbon dioxide leaves it. That's the whole pipeline. I spent years working with pulmonary function data, and the thing most people miss is that the respiratory organ of human isn't just about the lungs. The diaphragm, the intercostal muscles, the upper airway resistance — they all matter. You can have perfectly healthy lung tissue and still have terrible ventilation if your diaphragm isn't firing right. I had a patient once who came in with what looked like asthma on paper. Spirometry showed obstruction, wheezing, the works. Turned out their phrenic nerve had been subtly compressed from a thyroid mass. Fix the thyroid, breathing fixes itself. So when you're troubleshooting respiratory issues, don't stop at the lungs.
Respiratory Organ Of Human: The Key Numbers
Tidal volume at rest is about 500 milliliters per breath for an average adult. That's the amount of air you move in a normal breath without thinking about it. Vital capacity, which is the max air you can expel after a max inhalation, runs roughly 4 to 6 liters depending on size, age, and sex. Total lung capacity sits around 6 liters. Dead space — air that stays in the conducting passages and never reaches alveoli — is about 150 milliliters. So with each breath, only about 350 milliliters actually participates in gas exchange at rest. The alveoli themselves are the business end. There are roughly 480 million of them in a pair of healthy lungs, giving a total surface area of about 70 square meters. That's roughly the size of a tennis court packed into your chest cavity. The blood-air barrier where gas exchange happens is somewhere between 0.1 and 0.5 micrometers thick. Thin enough that oxygen diffuses across it in under a second.
Common Problems People Get Wrong
One counter-intuitive thing: holding your breath longer doesn't come down to how much oxygen you have. It comes down to carbon dioxide buildup. Your brain's respiratory center is screaming at you to breathe when CO2 levels rise, not when O2 levels drop. This is why hyperventilating before a breath-hold dive is dangerous. You blow off CO2, your urge to breathe gets delayed, and you can black out from hypoxia before your body tells you to breathe. Shallow water blackout kills competent swimmers every year. Another thing beginners miss: lung volumes and capacities are not the same thing. Volumes are single measurements — tidal volume, residual volume, inspiratory reserve volume, expiratory reserve volume. Capacities are combinations of two or more volumes. Inspiratory capacity is tidal volume plus inspiratory reserve volume. Functional residual capacity is residual volume plus expiratory reserve volume. Mixing these up will mess up any calculation you're trying to do, whether you're reading a PFT report or doing research. I once reviewed a spirometry dataset where someone had been reporting FVC and VC interchangeably. In healthy subjects they're essentially the same number. In obstructive disease, FVC is lower than VC because air gets trapped during forced expiration. The difference between the two numbers is actually clinically useful for detecting dynamic hyperinflation, but nobody was tracking it because they didn't know the terms were distinct. Took me about three hours to reformat their output and flag the discrepancy. After that, the trend lines made a lot more sense.
Get the Full Details
What Actually Happens During Gas Exchange
Oxygen moves from alveoli into capillary blood because the partial pressure of O2 in alveolar air is about 104 mmHg, while deoxygenated blood coming into the pulmonary capillaries has a PO2 of only about 40 mmHg. Carbon dioxide moves the opposite direction — partial pressure of CO2 is about 45 mmHg in the blood and only about 40 mmHg in the alveoli. The gradient drives diffusion. Simple physics, no energy required on the lung side. The hemoglobin saturation curve is where it gets interesting. Hemoglobin at a PO2 of 100 mmHg is about 97.5% saturated. At a PO2 of 40 mmHg — normal tissue level — it drops to about 75%. That means hemoglobin is dumping roughly a quarter of its oxygen load at rest. During exercise when tissue PO2 can drop to 20 mmHg, saturation falls to around 35%, meaning hemoglobin releases over half its oxygen. The curve is sigmoid-shaped precisely because of cooperative binding. One oxygen molecule binding makes it easier for the next one to bind, and harder for it to let go when things get acidic or warm. I worked with a neonatal ICU team once who were puzzled by why their preemies needed so much more FiO2 than the standard tables predicted. The answer wasn't that the babies had worse lungs — it was surfactant deficiency. Without enough surfactant, alveolar surface tension stays high, the alveoli collapse at end-expiration, and you lose functional reserve. The alveoli that do stay open are overdistended, which actually impairs perfusion matching. The fix wasn't more oxygen, it was surfactant replacement therapy and continuous positive airway pressure to keep the alveoli open. Adding more FiO2 to that situation just risks oxidative damage to fragile lung tissue. I wish someone had told me that sooner. We lost a few patients before the team started thinking about surfactant rather than just cranking up the oxygen.
Practical Ways To Assess Respiratory Function
Pulmonary function testing is the standard. Spirometry measures how much air you can blow out and how fast. FEV1 is the volume exhaled in the first second. FVC is the total forced volume. The ratio of FEV1 to FVC is the key number. Below 0.7 suggests obstructive disease. Below 0.7 in a restrictive pattern means the volumes are small but proportionally similar. The trick is that the threshold isn't universal — you need predicted values based on age, height, sex, and ethnicity. Using a fixed 0.7 cutoff for everyone over 40 will misclassify a lot of normal aging as obstruction. The GLI-2012 reference equations are the current standard and they use a lower limit of normal rather than a fixed ratio. Body plethysmography measures total lung capacity and functional residual capacity more accurately than gas dilution methods, especially in obstructive disease where trapped air skews the results. Helium dilution and nitrogen washout tend to underestimate volumes in severe COPD because the trapped gas never mixes with the indicator. If you're reading research that uses gas dilution for a COPD cohort, factor in that the lung volumes are probably too low. Pulse oximetry is everywhere but it has blind spots. It can't distinguish carboxyhemoglobin from oxyhemoglobin, so a smoker with significant carbon monoxide exposure can read 98% saturation while their actual oxygen-carrying capacity is compromised. It's also less accurate at low perfusion states — cold fingers, shock, vasopressors. And it plateaus, meaning a reading of 90% could correspond to a PO2 anywhere between 60 and 70 mmHg depending on the curve. When I need reliable oxygenation data, I ask for an arterial blood gas. It's more invasive but it tells you PaO2, PaCO2, pH, and calculated bicarbonate all at once. Pulse oximetry alone is screening, not diagnosis.
Where The System Breaks Down
The respiratory organ of human has real limitations. Pulmonary fibrosis turns elastic lung into stiff scar tissue. The compliance drops dramatically, meaning you have to generate much higher pressures to move the same volume of air. Diaphragm effort skyrockets and fatigue sets in quickly. There's no good workaround besides transplant, and even that is limited by organ availability and rejection risk. Emphysema destroys the elastic recoil that keeps alveoli open during expiration. Airway collapse during exhalation traps air. The residual volume increases, the diaphragm flattens and loses mechanical advantage, and patients end up breathing at near-total lung capacity where the respiratory muscles are already at a disadvantage. These patients breathe out through pursed lips because the increased back pressure stents the airways open. It's a compensatory mechanism, not a treatment, but it reduces the work of breathing noticeably. One bottleneck people overlook is the matching of ventilation and perfusion. You can have perfect alveoli and perfect capillaries and still have hypoxemia if blood is flowing to areas that aren't being ventilated, or vice versa. Pulmonary embolism is a classic example — perfusion drops to zero in the affected region, creating dead space. In pneumonia, ventilation drops to zero in the affected area, creating a shunt. Neither is fixed by giving more oxygen alone. Shunts in particular are refractory to supplemental oxygen because the blood is simply bypassing ventilated alveoli. You have to treat the underlying cause — antibiotics for infection, thrombolytics for embolism, chest physiotherapy for atelectasis.
Bottom Line
The respiratory organ of human is mechanically elegant but fragile in practice. The alveolar-capillary interface is enormous and incredibly thin, which is exactly why it's vulnerable to toxins, infections, and inflammation. Understanding how the system works beyond the basic textbook model — the CO2 drive, the difference between volumes and capacities, the limitations of pulse oximetry, the ventilation-perfusion matching problem — makes a real difference when something goes wrong. Most respiratory issues aren't solved by looking harder at the lungs. They're solved by understanding the whole chain.


