What Actually Helps When You're Trying to Manage RLS Through Food
Most people who come to me about Restless Leg Syndrome And Diet have already tried everything that appears on a Google search result. They cut caffeine, they stretch before bed, they run hot baths, and the legs still feel like something is crawling under their skin at 2 AM. The diet angle is one of those things that sounds simple but is genuinely complicated because the mechanisms are not fully mapped out. Here is what I have learned from working with people who actually stuck with dietary changes for at least six months, which is long enough for the body to settle into whatever new baseline it finds. Iron deficiency is the single most documented dietary link to RLS severity, but the way people approach it is usually backwards. They check their serum ferritin, see it at 45 nanograms per milliliter, and assume they are in the clear because the reference range typically starts around 15. It does not. For RLS patients, ferritin levels below 75 often correlate with symptom worsening, and some neurologists will treat proactively once you drop below 50. I had a patient who ran ferritin around 60 and insisted her labs were fine. She started oral iron supplements at 65 milligrams of elemental iron daily, split into two doses taken away from calcium and coffee, and within three weeks her nighttime symptom score dropped from an 8 to a 3 out of 10. Six months in, her ferritin was sitting at 110 and she had not taken a single prescription dopamine agonist. That is not a universal outcome but it is the kind of thing that goes unmentioned in general health articles. The problem with oral iron is compliance and side effects. Constipation affects roughly a third of people on standard ferrous sulfate, which makes sticking with it hard. I recommend switching to ferrous bisglycinate or heme iron polypeptide if the standard stuff causes GI distress. Absorption rates are better and the stool issues are far less common. Blood work should be repeated after six to eight weeks to see where ferritin actually landed. The number matters more than how you feel because people adapt to mild constipation and stop noticing it.
Magnesium is not a magic bullet but it helps some people
Magnesium glycinate at 200 to 400 milligrams before bed is the version I suggest most often because it is gentle on the stomach and does not cause the diarrhea that magnesium oxide triggers in nearly everyone who tries it. The evidence for magnesium and RLS is thin, but there is a subgroup of people whose symptoms seem tied to muscle hyperexcitability rather than pure dopaminergic dysfunction, and magnesium helps that type. I have seen it work in about a third of the people who try it consistently for four weeks. The rest notice nothing. Expecting dramatic results from magnesium alone is realistic only if you have a confirmed deficiency to begin with. I once worked with someone who took magnesium oxide because it was cheaper and available without a prescription. He dropped out after four days with severe cramping and loose stools that made his RLS feel worse because he was losing sleep. Switching him to glycinate fixed the GI issue entirely and he started getting actual relief after about ten days. The difference between the two forms is significant enough that it is worth paying the extra cost for the bisglycinate or glycinate version.
Practical dietary shifts that matter more than supplements
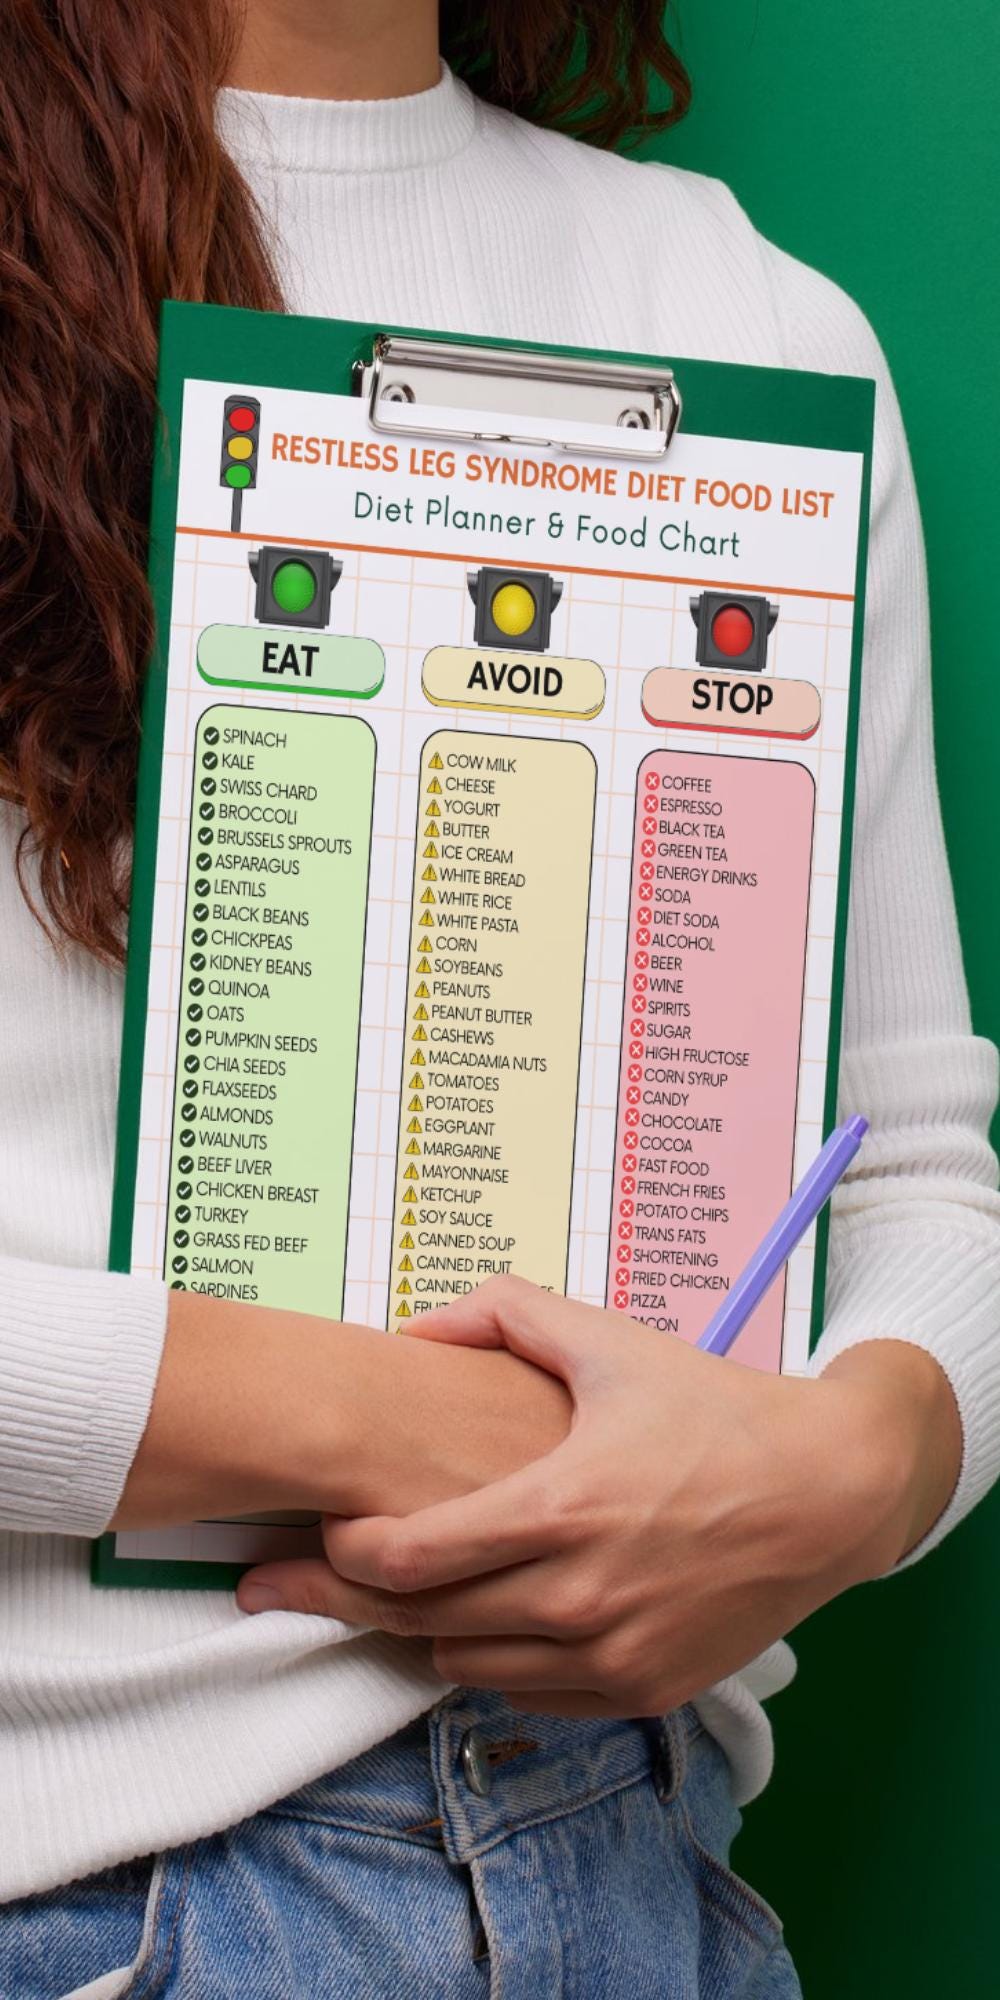
Whole food sources of iron and magnesium tend to produce steadier results than isolated supplements because absorption is modulated by the food matrix itself. Dark leafy greens, legumes, pumpkin seeds, and red meat in moderation are practical daily options. The tricky part is timing. Iron from food is absorbed more efficiently when taken away from compounds that block absorption, which means keeping tea, coffee, and dairy at least two hours apart from iron-rich meals. Most people do not think about this and then wonder why their ferritin is not moving despite eating spinach and drinking red juice or taking supplements alongside their morning latte. That combination reduces iron absorption by roughly 60 percent according to multiple studies, and it is one of the most common mistakes I see. Gluten and dairy sensitivity appear in a small but real subset of RLS patients. I do not recommend an elimination diet for everyone because the data is weak on a population level, but if someone has bloating, brain fog, or unexplained fatigue along with their leg symptoms, removing gluten for four weeks and then reintroducing it can be revealing. In my experience, about 5 to 10 percent of RLS patients report noticeable symptom improvement after cutting gluten, and the mechanism may involve low-grade inflammation affecting nerve sensitivity rather than celiac disease itself. Same logic applies to dairy for some people, though the response rate is lower.
Get the Full Details

What does not work and why people keep trying it
Detoxes, juice cleanses, and extreme elimination diets are harmful for RLS patients because they often drop iron and zinc levels while creating stress on the body that worsens dopaminergic function. Zinc in particular is worth mentioning because low zinc has been linked to RLS in a few studies, but mega-dosing zinc to fix it causes copper deficiency and can make neurological symptoms worse. The safe upper limit is 40 milligrams per day from all sources, and testing a zinc level before supplementing is the only responsible move. I have seen three patients over the years who took 100 milligrams of zinc daily expecting relief and ended up with anemia and worsened RLS because their copper dropped below optimal range. That is a real and preventable pitfall. Alcohol is another obvious trigger that people underestimate. Even one glass of wine can disrupt sleep architecture and increase RLS severity for the next 24 to 36 hours in sensitive individuals. The mechanism involves adenosine receptors and dopamine disruption, not just dehydration. If someone drinks regularly and complains that their RLS is unmanageable, reducing or eliminating alcohol is usually the single highest-impact change they can make without touching a single supplement.
Building a sustainable approach
The realistic pathway involves checking ferritin, zinc, and vitamin D levels through blood work, addressing any deficiencies with targeted supplementation, making dietary adjustments around iron absorption timing, and tracking symptoms for at least eight weeks before judging whether anything is working. Symptom tracking does not need to be elaborate. A simple nightly note on a scale of 1 to 10 for restlessness, sleep disruption, and daytime fatigue is enough to spot trends. Most people give up around week three because they expect immediate results, but the nervous system adjusts slowly and the data only becomes meaningful after the fourth or fifth week of consistent tracking. Dietary intervention alone will not resolve moderate to severe RLS in most cases. It is a foundational layer that reduces symptom burden and makes pharmaceutical treatments more effective when they are needed. If your symptoms are severe enough to require medication, the dietary work still matters because it lowers the dose required and improves overall outcomes. I would recommend starting with the blood work and the iron optimization before investing heavily in any other approach because that is where the strongest evidence sits and where the fastest improvements typically occur. There is no download link or app that fixes this. The closest thing to a practical tool is a simple spreadsheet or notebook where you log ferritin trends, supplement types and dosages, dietary changes, and nightly RLS scores. That raw data is what lets you and your doctor adjust the plan intelligently instead of cycling through random remedies until something sticks by accident.