What Reticular Connective Tissue Actually Does
Reticular connective tissue is the scaffolding inside your lymph nodes, spleen, and bone marrow. It is made of type III collagen fibers produced by reticular cells, and it forms a delicate three-dimensional mesh that holds immune cells in place while letting them move through. Most people studying histology memorize that it is "supportive connective tissue" and move on. That definition is correct and completely insufficient for understanding how it works in practice. The main
Reticular Connective Tissue Function
is structural support combined with filtration. The reticular fiber network traps passing lymph or blood, allowing macrophages and other immune cells to scan for pathogens. In the spleen specifically, the reticular mesh acts as a mechanical filter for old red blood cells. In lymph nodes, it creates the compartments where antigen presentation happens. Without that framework, immune cells would just float around unorganized and inefficient.How It Works Under the Microscope
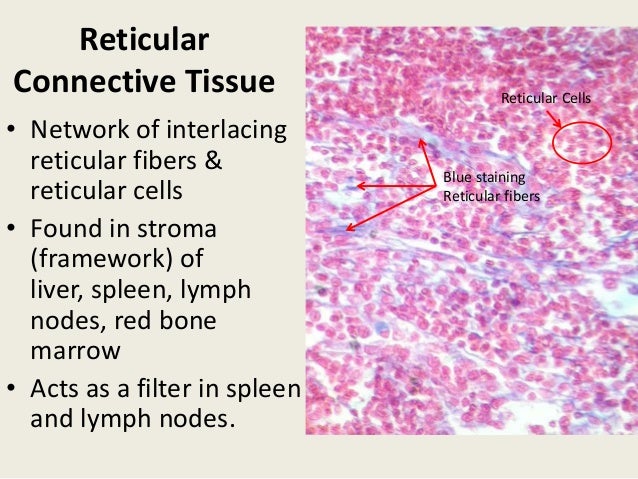
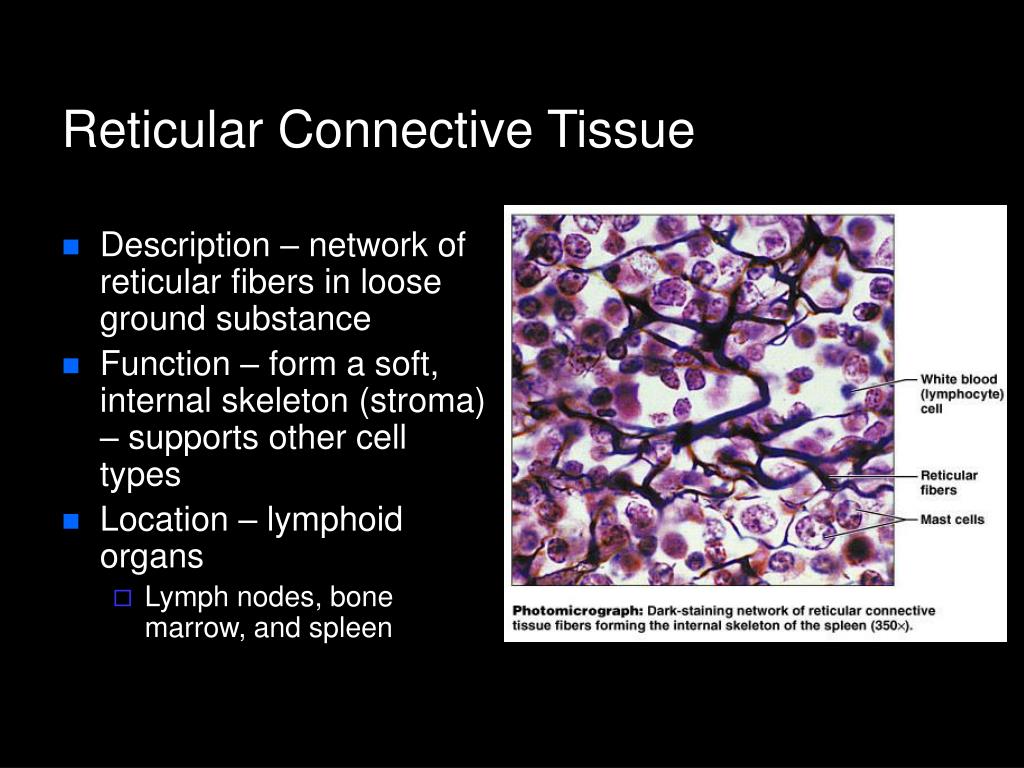
When you look at a standard H&E stained section of a lymph node, the reticular network is basically invisible. Type III collagen does not take up hematoxylin or eosin well. What you actually see are dark clusters of lymphocyte nuclei sitting in pale empty-looking spaces. Those pale spaces are where the reticular fibers are, but they washed out during processing or simply do not stain with routine methods. To actually visualize the network you need a silver impregnation stain like reticulin stain or Jones methenamine silver. The silver deposits on the type III collagen and turns the fibers black against a light background. This is not optional if you want to assess the architecture properly. I have seen pathologists miss follicular dendritic cell networks and early fibrotic changes in lymph nodes because they relied only on H&E and assumed the architecture was normal when the reticular scaffold was already disrupted.
The Part Nobody Tells You About
Reticular fibers are surprisingly fragile and they remodel continuously. Reticular cells respond to mechanical signals and cytokine cues by increasing or decreasing fiber production. During chronic inflammation you will see reticular fiber hyperplasia - the mesh becomes denser and more tangled. In certain lymphomas the neoplastic cells actually disrupt the normal reticular architecture in ways that are diagnostically useful but easily overlooked if you are not specifically looking for it. Here is a practical problem I ran into recently. I was reviewing lymph node biopsies from a case of Hodgkin lymphoma and the reticular fiber pattern was completely altered around the Reed-Sternberg cells. A junior pathologist called it reactive hyperplasia because the H&E appearance was ambiguous. The reticulin stain revealed that the normal nodular architecture was destroyed and replaced by irregular thickened bands of reticular fibers surrounding atypical cells. That single stain changed the diagnosis. I recommend making reticulin stain part of your standard workup for any lymph node with ambiguous architecture rather than waiting until something looks obviously wrong.
Get the Full Details
What Happens When It Fails
There are conditions where reticular connective tissue function is directly impaired. Primary immunodeficiencies involving defects in reticular cell development can lead to severe combined immunodeficiency presentations. The reticular stroma simply cannot form properly and lymphoid organs are hypoplastic. On the other end of the spectrum, reticulin fibrosis occurs in myeloproliferative neoplasms like primary myelofibrosis where the bone marrow reticular network gets replaced by dense type I collagen over time. This is a progressive process and once it advances beyond early reticulin deposition the marrow becomes functionally useless for hematopoiesis. Type III collagen mutations cause vascular Ehlers-Danlos syndrome. The reticular fibers throughout the body are weaker than they should be. Blood vessels rupture more easily. This is not a minor connective tissue variant. It is life-threatening and often goes undiagnosed until a catastrophic vascular event happens. Genetic testing for COL3A1 mutations is the only reliable way to confirm it.
Practical Takeaways
If you are studying this for an exam, understand that reticular tissue is specialized loose connective tissue dominated by type III collagen. Know which organs contain it. Know that it does not stain with H&E and requires silver methods for visualization. Know that it provides both structural support and a filtration framework for immune surveillance. If you are working in a lab or clinical setting, do not skip the reticulin stain when evaluating lymphoid tissue architecture. The information it provides cannot be reliably inferred from H&E alone. The staining protocol itself is straightforward - formalin-fixed paraffin-embedded sections treated with ferric ammonium sulfate and reduced with formalin - but interpretation requires experience. Normal reticular fibers appear as fine delicate black threads. Pathologic thickening or disruption is what matters clinically. The reticular connective tissue function is not dramatic. It does not contract or secrete hormones. It holds things together and filters what passes through. That is plenty important.