Working with the Reticular Layer Of Dermis: What Actually Matters
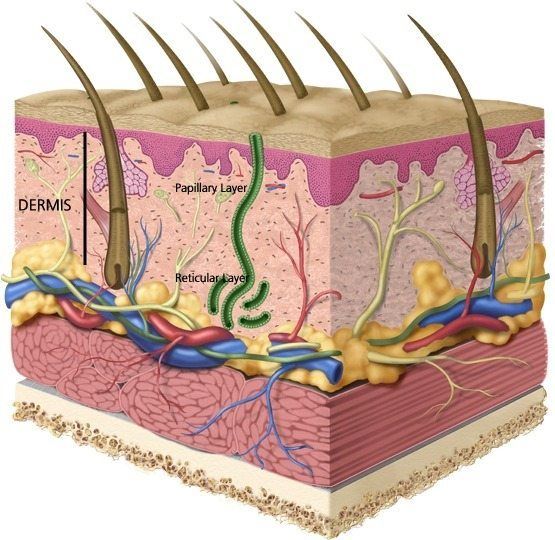
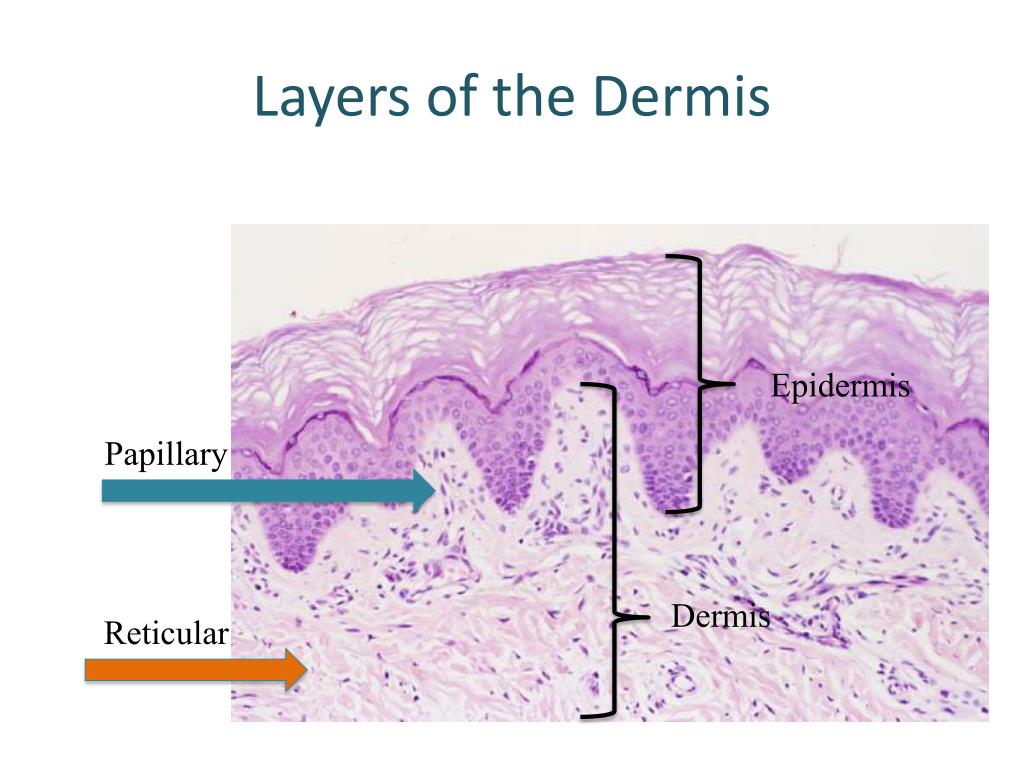
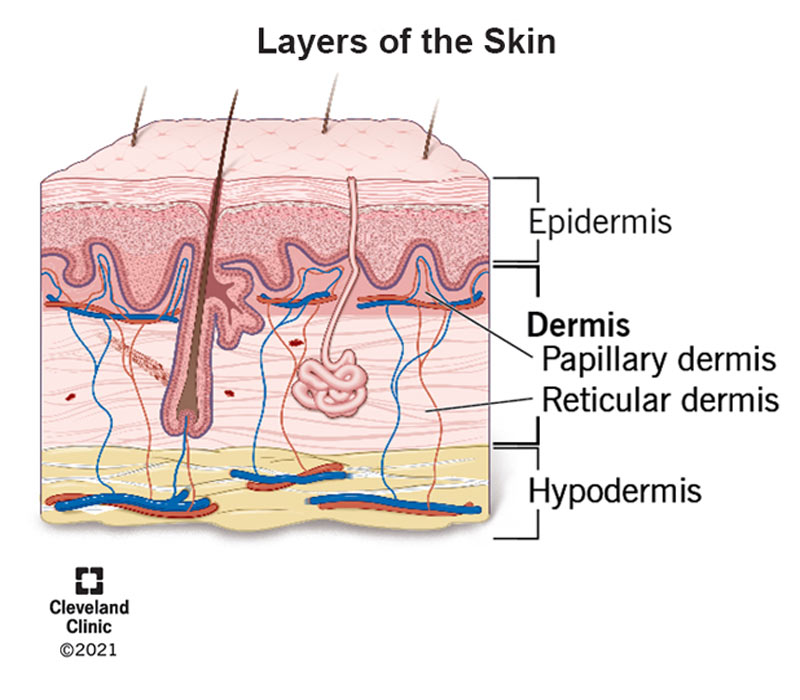
The reticular layer is the deeper, thicker portion of the dermis. It sits right below the papillary layer and extends down to the hypodermis. Most of the structural integrity of your skin comes from this region. If you're studying histology, surgical anatomy, or wound healing, this is where the real work happens. It's made primarily of dense irregular connective tissue. Collagen bundles are thick and woven in multiple directions, which gives the skin its tensile strength. Elastin fibers are scattered throughout but less concentrated than in the papillary layer. Fibroblasts are the main cell type, and they're responsible for maintaining that collagen and elastin matrix. You'll also find blood vessels, lymphatics, nerves, hair follicles, and sweat glands embedded here. The arrangement varies by body region. Skin on your back is much tougher than skin on your eyelids, and this layer explains why. I spent years doing reconstructive surgery and wound care, and I can tell you that understanding this layer changes how you approach closure. Most people learn it as a textbook diagram. The reality is messier.
Why It Matters Clinically
When a laceration goes deep enough to reach the reticular layer, you're no longer dealing with a simple superficial wound. This is where you start seeing significant bleeding because the vascular supply is much denser here. Capillaries from the subpapillary plexus extend downward, and there are larger terminal vessels running through this layer. Hemostasis takes longer. Healing takes longer. Scar formation is more likely. Collagen turnover in the reticular layer is slow. New collagen gets deposited during the proliferative phase, but remodeling can continue for months or even years. That's why mature scars are weaker than original skin—about 70 to 80 percent of the pre-injury tensile strength at best. Nothing else in the body repairs this way after major trauma.
A Problem I Ran Into During Suturing Work
I was working on a forearm laceration that extended well into the reticular layer. The patient was a construction worker, mid-fifties, heavy sun exposure over decades. The skin there was already significantly compromised by chronic photodamage. The collagen bundles were fragmented and disorganized from years of UV damage. What looked like a clean cut on the surface actually had a lot of hidden disruption underneath. The standard approach would have been simple interrupted sutures with 4-0 nylon. But the tissue quality was poor. Every time I pulled the suture through, the collagen was just tearing out. The sutures cut through within hours. I ended up switching to a buried continuous subcuticular closure using 5-0 Monocryl, placing each bite deeper into the relatively healthier reticular layer while leaving the outermost damaged zones free of tension. The wound edges approximated better and stayed closed. It added maybe twenty minutes to the procedure but saved a revision later.
Get the Full Details
Counter-Intuitive Things Beginners Miss
One thing that surprises a lot of people is that the reticular layer doesn't regenerate well after significant injury. When you lose a substantial portion of it, the body doesn't rebuild the same architecture. It lays down collagen in a more random, parallel pattern during scarring. That's why a deep scar feels different. It's less elastic, less supple, and the and sebaceous function in that area is permanently gone. Another common mistake is assuming that deeper wounds automatically mean worse outcomes. That's not always true. A narrow but deep puncture into the reticular layer may heal with less visible scarring than a wider superficial laceration that disrupts a large surface area of this layer. Surface area disruption matters more than depth alone for cosmetic outcomes.
Limitations and Where This Knowledge Falls Short
Here's the honest part. Knowledge of the reticular layer doesn't help much when you're dealing with patients who have conditions that affect collagen synthesis. Ehlers-Danlos syndrome, scurvy, chronic steroid use, advanced diabetes—these all change how the reticular layer responds to injury. In those cases, the standard wound care protocols based on normal reticular layer biology just don't apply. Sutures may hold technically but fail functionally because the tissue can't maintain the repair. I've seen diabetic patients where standard closure techniques failed repeatedly, and the only reliable approach was staged healing with wound vac therapy and delayed primary closure. Trying to force standard suturing in those situations just creates more tissue damage. If you're studying this for exams, focus on the collagen types involved. Type I and Type III collagen are both present in the reticular layer, with Type I making up the majority. The ratio changes during healing, which is relevant for understanding scar mechanics. For clinical practice, the takeaway is that the reticular layer determines how a wound behaves more than anything else above it. The histology is straightforward. The practical application is not.