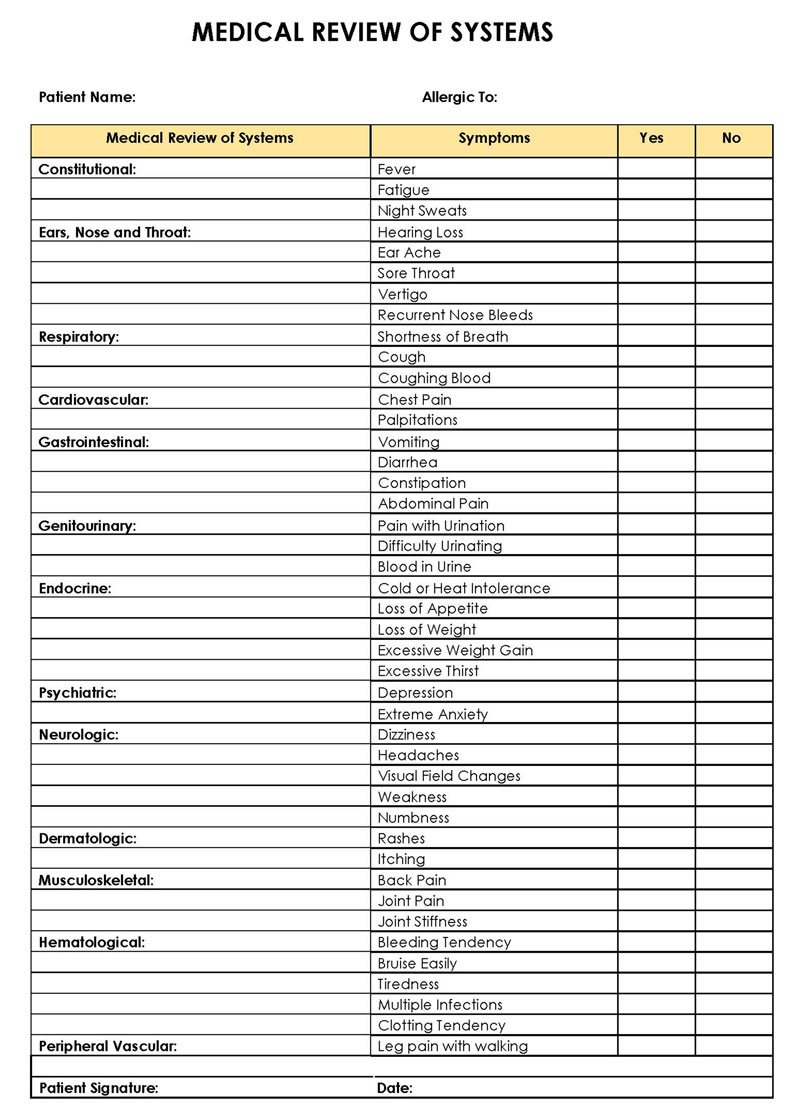
Understanding the Review Of Systems in Clinical Documentation
The review of systems is one of those things every medical coder and clinician has to deal with, but it's also one of the most inconsistently done parts of a clinical encounter. I've spent years watching people either over-document to the point of absurdity or under-document to the point of compliance headaches. Let me walk through how this actually works in practice. A review of systems isn't just a checkbox exercise. It's a systematic inquiry into each body system to uncover symptoms the patient may not have mentioned voluntarily. The standard template covers thirteen systems: constitutional, eyes, ears/nose/throat, cardiovascular, respiratory, gastrointestinal, genitourinary, musculoskeletal, neurological, psychiatric, endocrine, hematologic/lymphatic, and skin. You go through them in order, asking about key symptoms for each. For a moderate-complexity evaluation, you typically need at least ten systems reviewed. For a comprehensive exam, all thirteen are expected. The detail matters less than the consistency and the documentation of any abnormal findings.
I once had a patient who presented for a routine follow-up on hypertension. During the ROS, I asked about constitutional symptoms as a formality, and she mentioned she'd been having night sweats for two weeks. We ended up catching an early sign of a significant underlying infection that would have been missed if I had just checked a box. That's the point of doing this properly. Here's a concrete Review Of Systems Example. For a 45-year-old presenting with fatigue: Constitutional: positive for fatigue and low-grade fever. No chills or weight loss.
Eyes: no visual changes. No diplopia or photophobia. Cardiovascular: negative for chest pain, palpitations, or edema. Respiratory: denies cough, dyspnea, or hemoptysis.
Get the Full Details

Gastrointestinal: denies nausea, vomiting, diarrhea, or melena. Neurological: positive for mild headache and dizziness. No focal weakness or paresthesias. Psychiatric: denies anxiety or depression.
Endocrine: denies polyuria or polydipsia. Musculoskeletal: negative for joint pain or stiffness. Skin: no rashes or lesions.
Hematologic/lymphatic: denies easy bruising or bleeding. Genitourinary: denies dysuria or frequency. That gives you a solid twelve-system review with two positive findings. That's plenty for a high-level visit documentation.

One thing that catches people off guard is the difference between a problem-focused ROS and a complete ROS. A problem-focused review only requires systems relevant to the chief complaint. So if someone comes in with a sprained ankle, you don't need to document a genitourinary review. The complete ROS is what's needed for higher-level evaluations and procedures, and that's where most compliance issues arise. Another nuance that isn't well understood: the reviewer can be the patient or someone who can provide the history. In many cases, caregivers or family members are perfectly valid sources. I've seen coders reject entire notes because the ROS was obtained from a spouse rather than the patient. That's incorrect. The guidelines are clear on this. The biggest mistake I see is clinicians copying and pasting ROS templates and then leaving every system as "negative." Insurance auditors flag this pattern routinely. A truly negative ROS across all thirteen systems in a patient who's there for a chronic disease management visit is biologically implausible. At minimum, some systems should have positive findings or the note should reflect that the patient was asked and denied symptoms in each area with more specific language.
When documenting, use specific negatives rather than blanket denials. "Patient denies chest pain" is better than just writing "cardiovascular system negative." The former shows the question was actually asked. The latter looks like a checkbox. If you're building your own templates, keep them modular so you can adapt them to the visit type. I use a base template that covers all thirteen systems but with placeholder text that gets modified based on the encounter. This cuts documentation time from about twenty minutes down to roughly five minutes per note once you're comfortable with the flow.
Common Pitfalls and How to Avoid Them
The main trap is thinking that more systems automatically means better documentation. That's not true. Quality matters more than quantity. Fourteen systems with "denies all" written for each is worse than twelve systems with detailed positive and negative findings. Auditors look for evidence of actual inquiry, not volume. Another issue is inconsistency between the ROS and the history of present illness. If the HPI mentions headaches but the neurological ROS says "no headaches documented," that's a red flag. Keep those sections aligned. For telehealth visits, the ROS can still be performed and documented. You just need to note that it was obtained via telephone or video platform. Some providers skip it entirely in virtual visits, which is unnecessary and risky from a compliance standpoint.
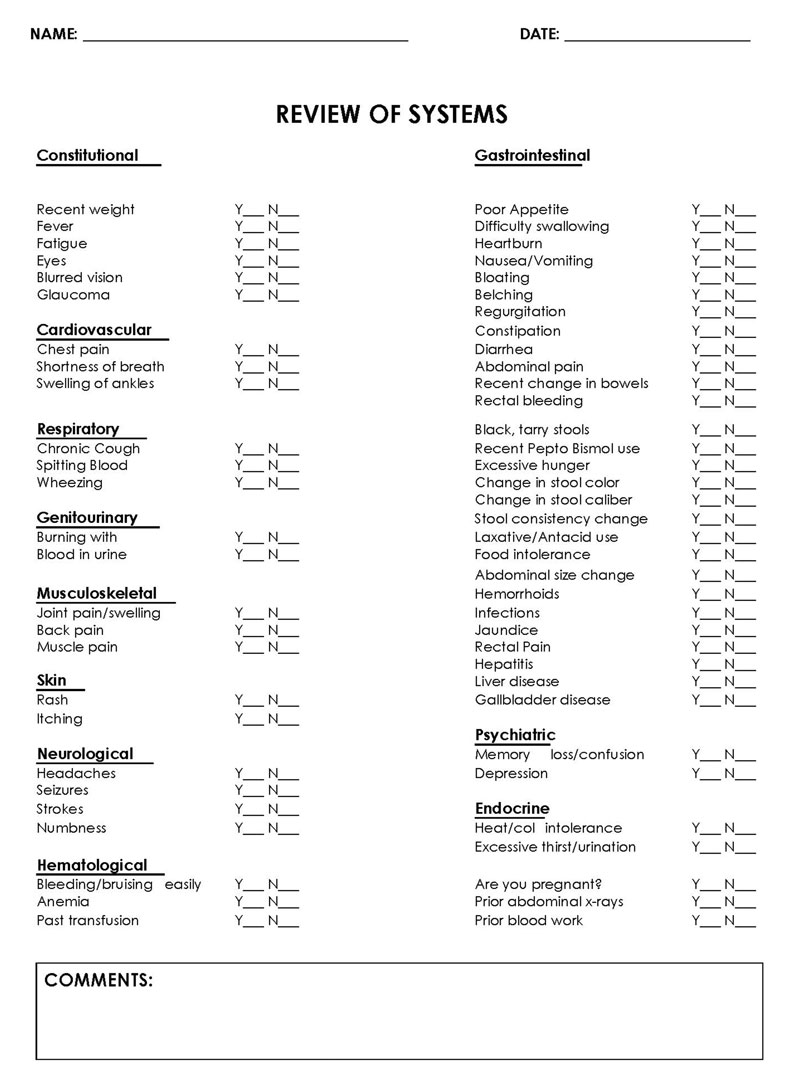
When in doubt about whether a symptom belongs in the ROS or the HPI, ask yourself this: is this the primary reason for the visit? If yes, it goes in the HPI. If it's a secondary or related symptom that came up during the systemic inquiry, it belongs in the ROS. The CPT guidelines don't require a specific format for the ROS. Bullet points, paragraphs, or structured templates are all acceptable. What matters is that the documentation reflects a thorough and organized review of the relevant systems for that particular encounter.


