Right-Sided Heart Failure Is Not What Most People Think It Is
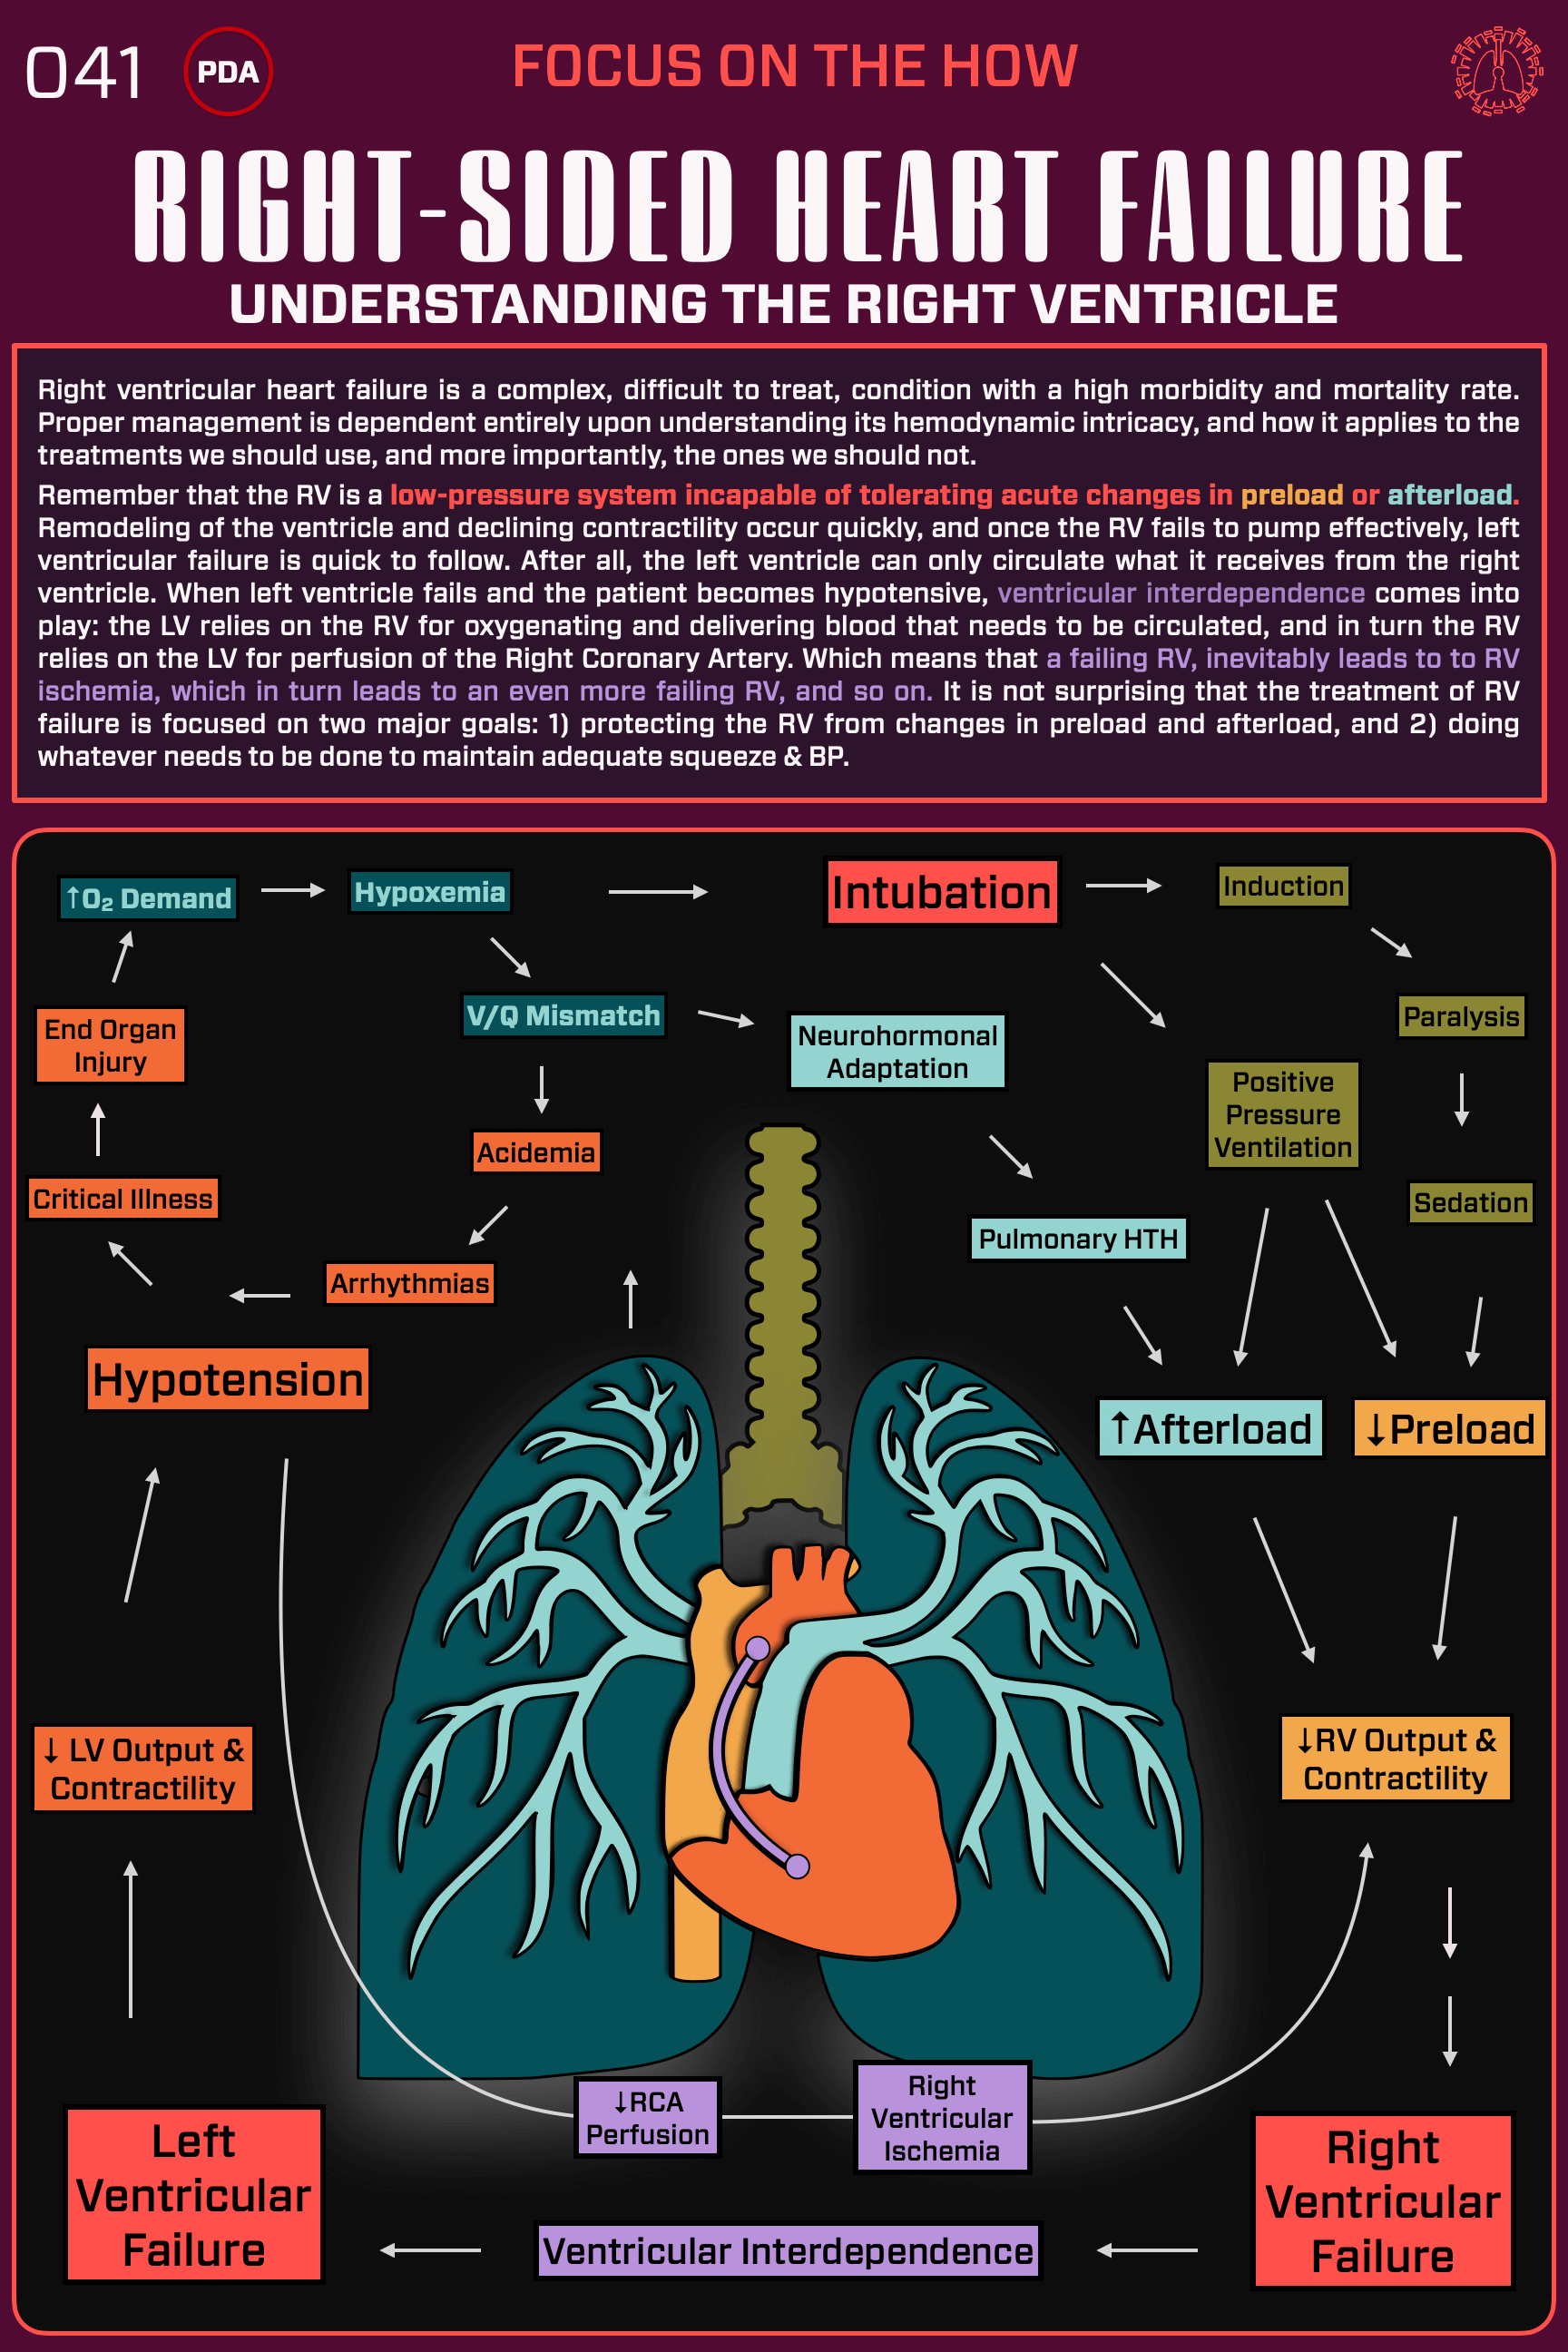
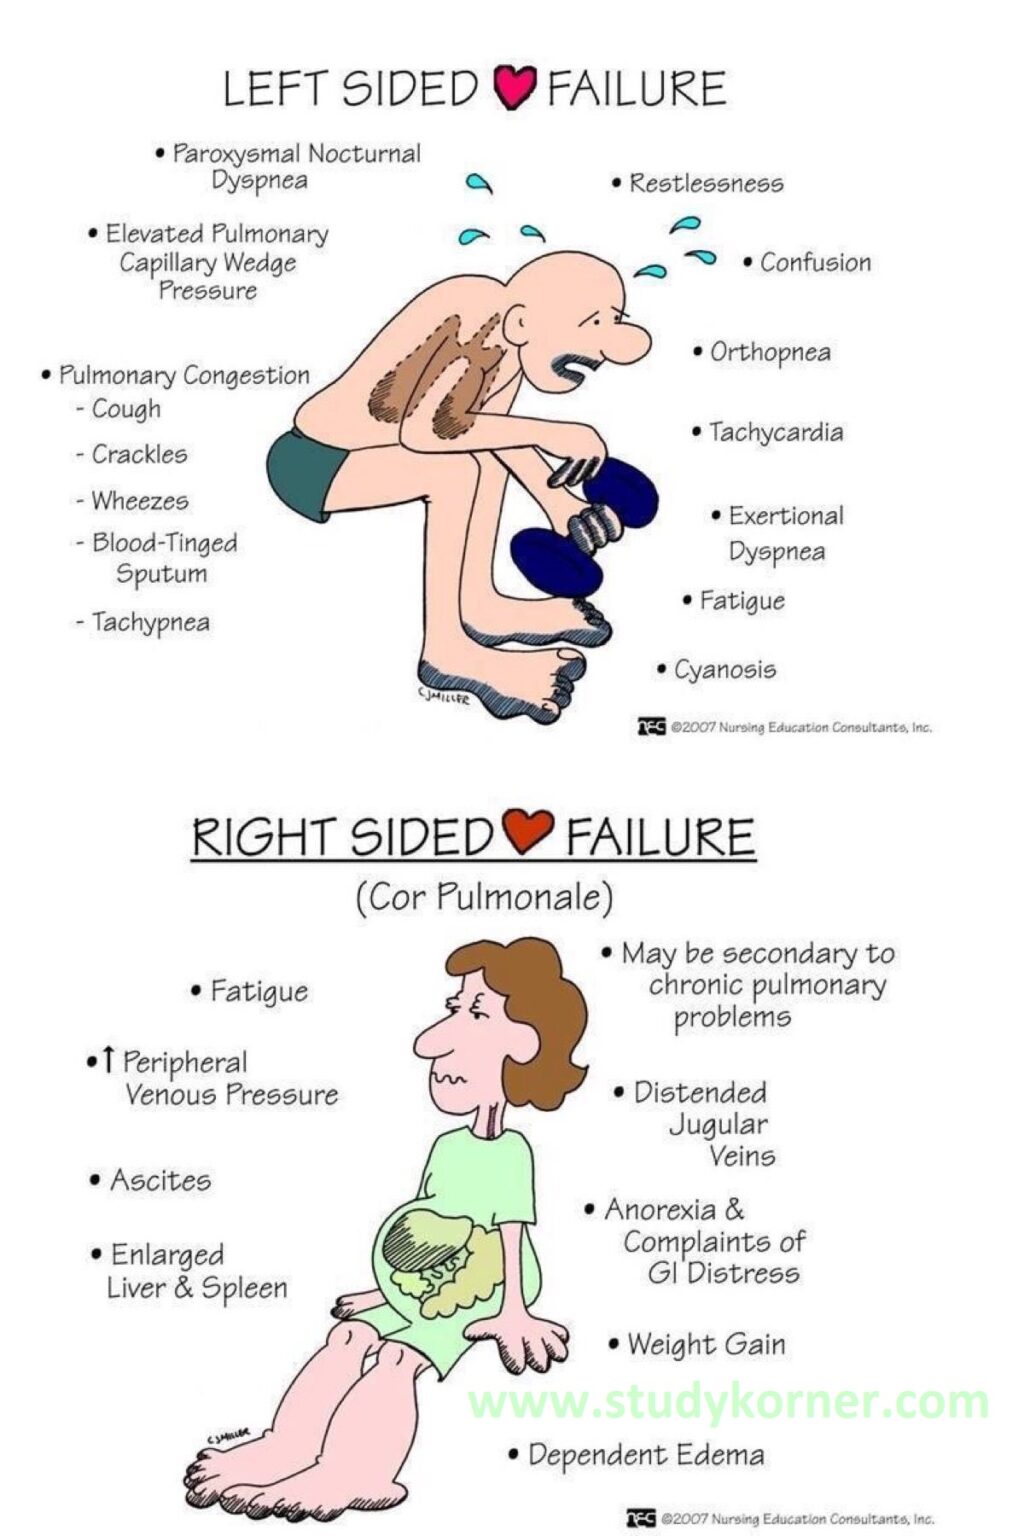
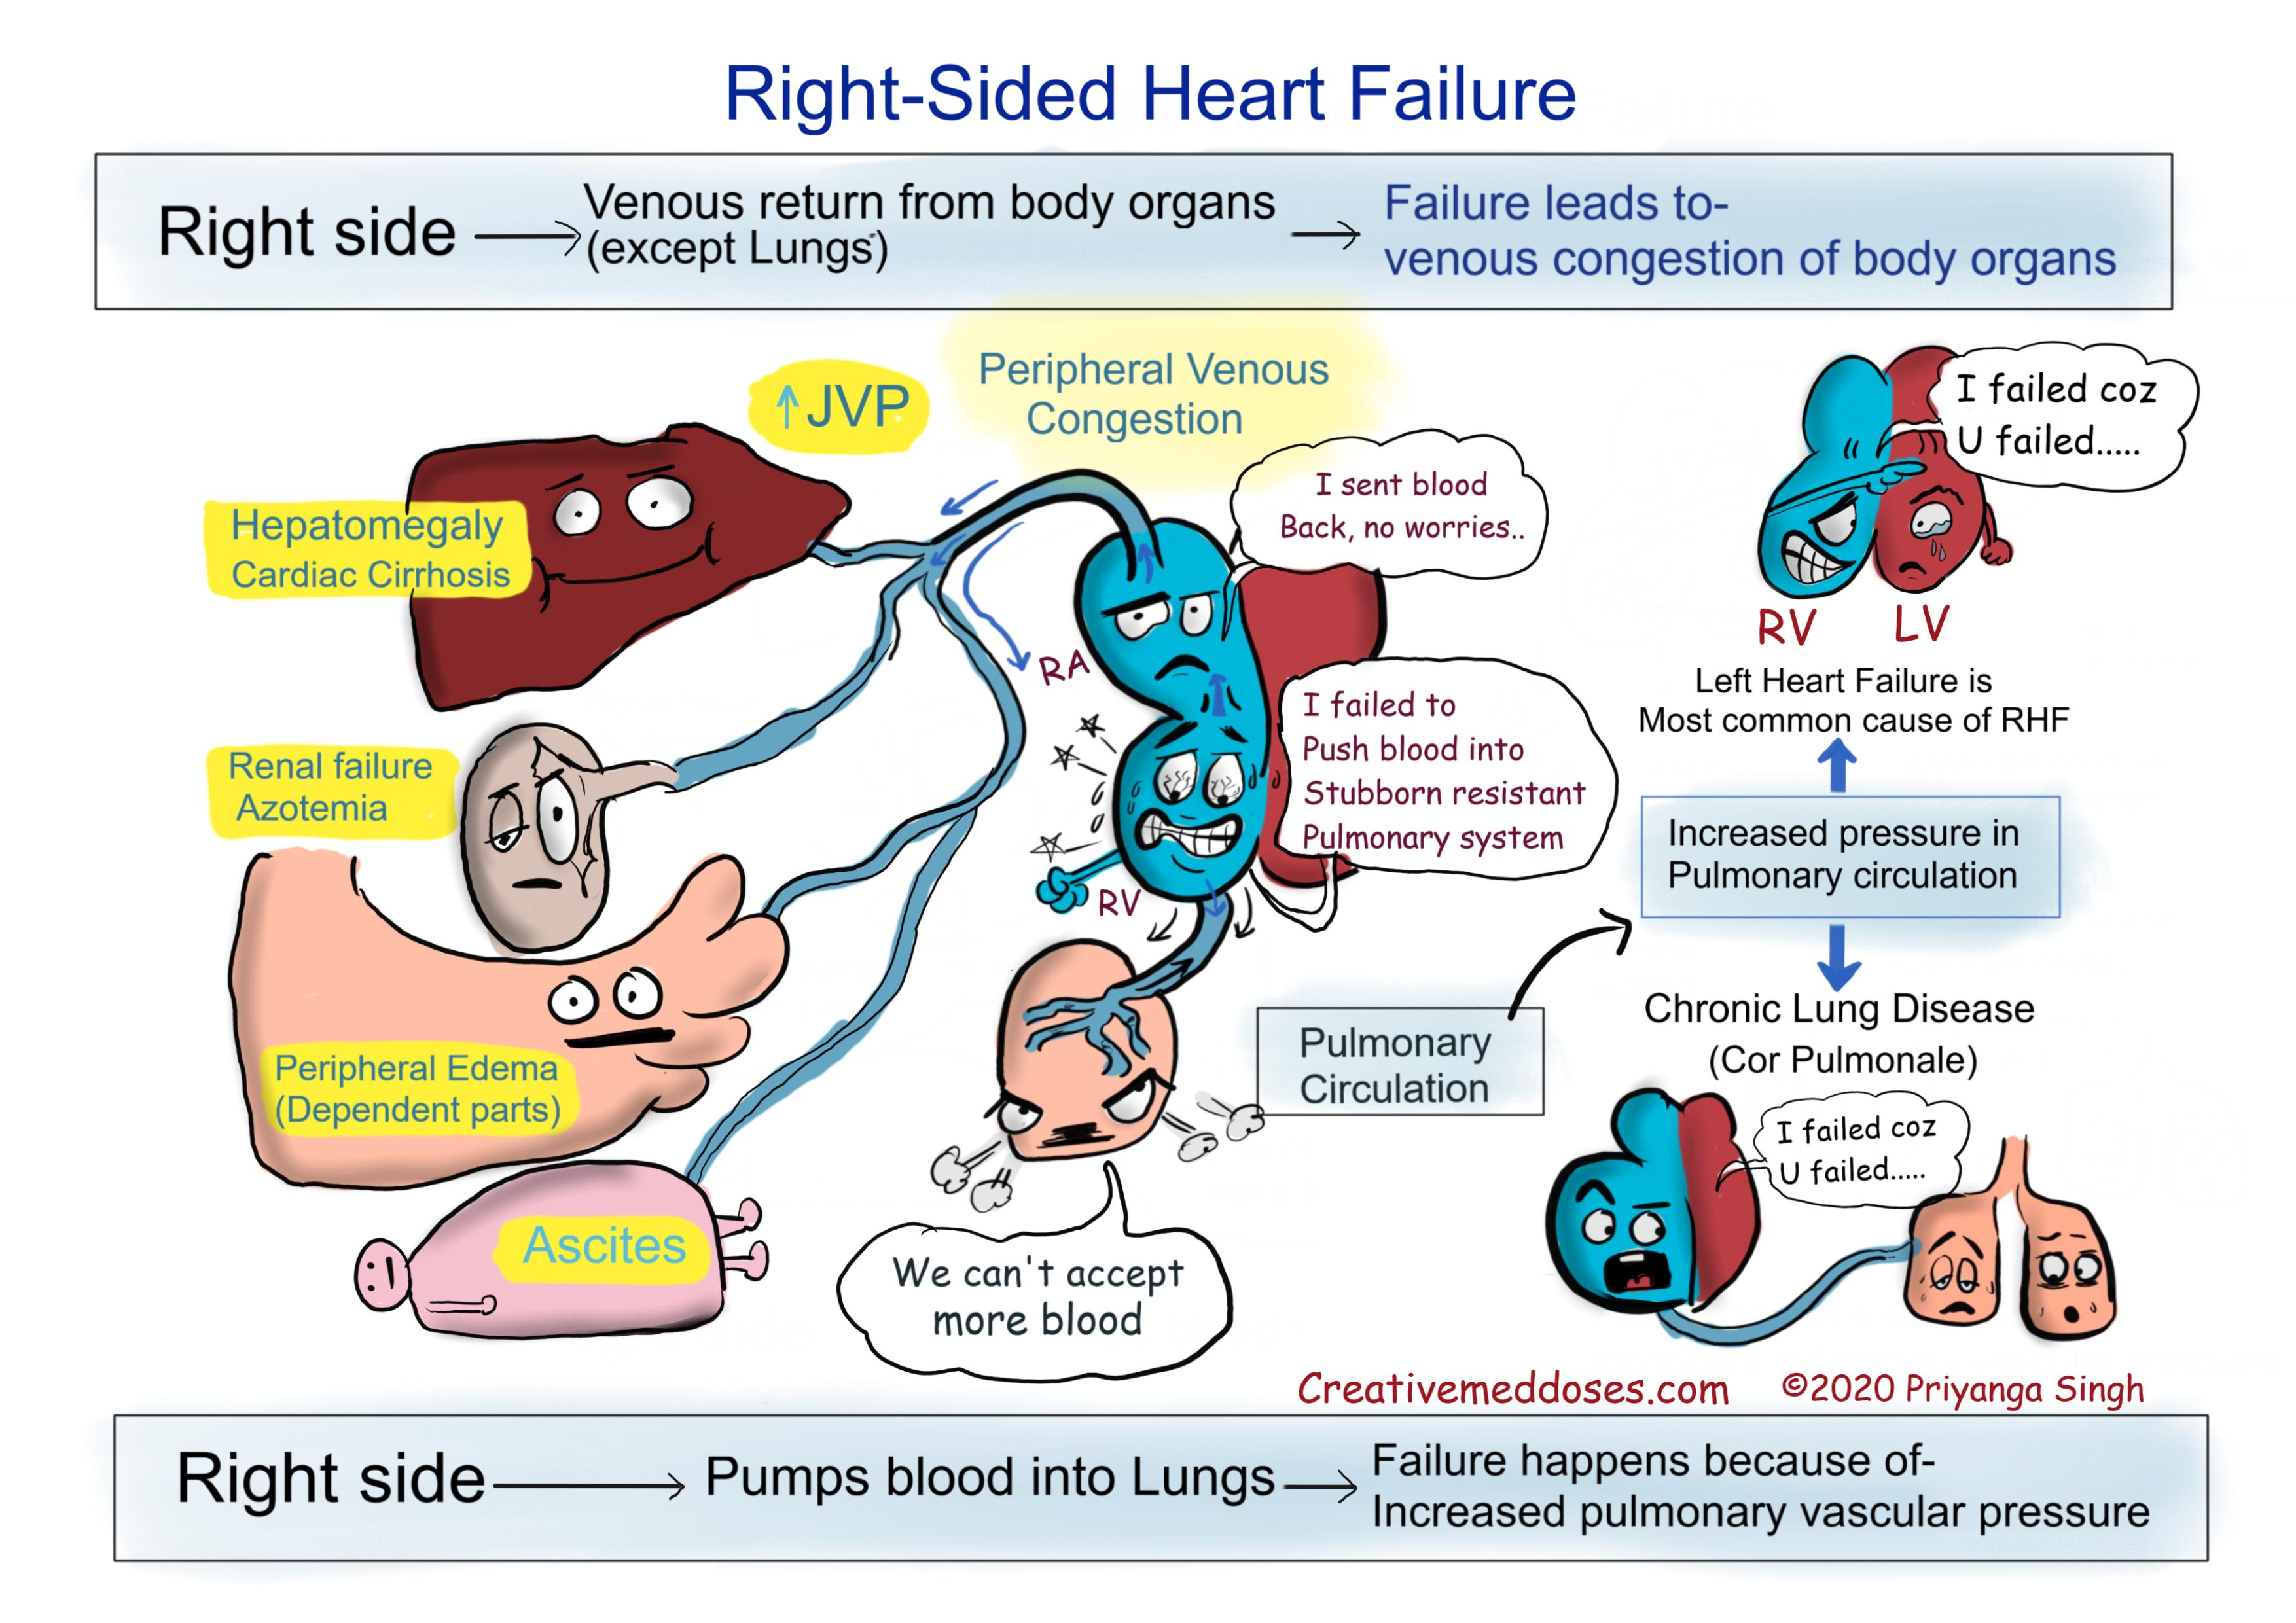
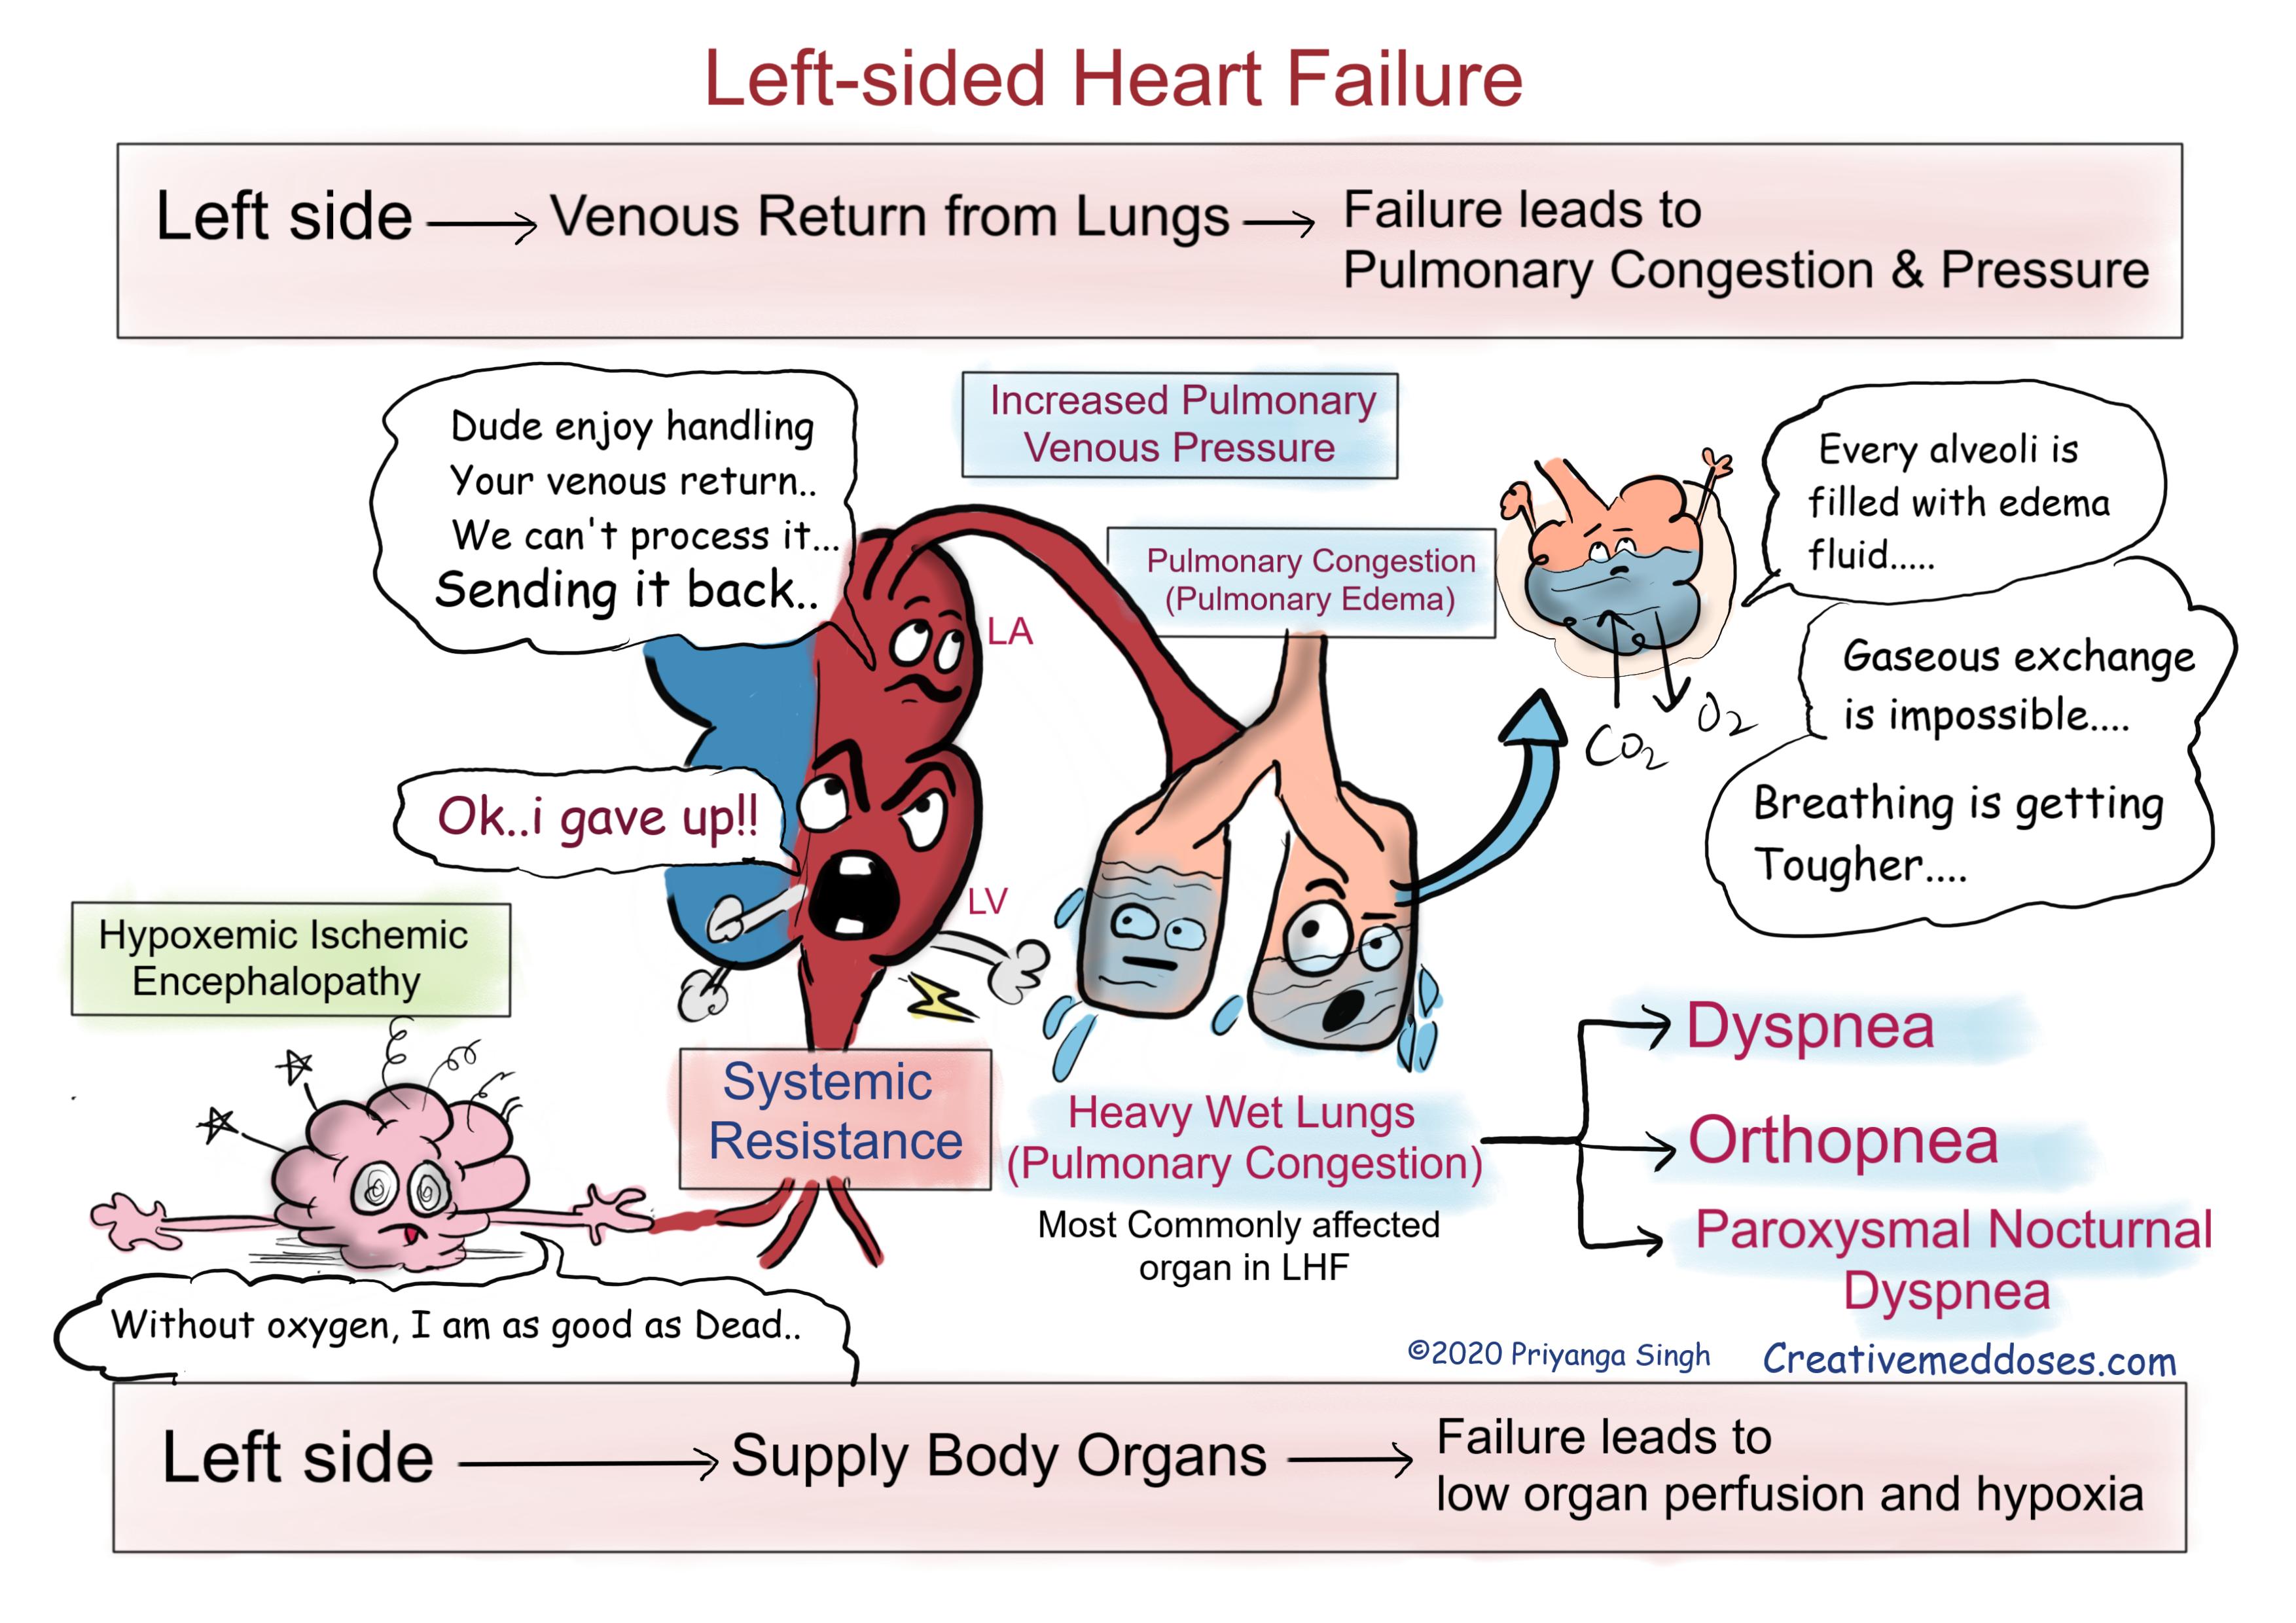
Right-sided heart failure is its own problem, and it is usually a consequence of something else going wrong upstream. When people hear "heart failure" they picture pulmonary congestion and shortness of breath. That is left-sided failure. Right-sided failure looks different because the right ventricle fails to push blood forward into the pulmonary circulation. The blood backs up into the venous system instead. The result is systemic venous congestion, not pulmonary congestion. I have seen this misdiagnosed repeatedly in clinical settings. A patient presents with leg swelling and fatigue, gets sent home with compression stockings and a prescription for a mild diuretic, and comes back three weeks later still swollen. The issue was never a venous insufficiency problem. It was right ventricular dysfunction that needed a proper workup.
What Actually Causes Right Sided Heart Failure
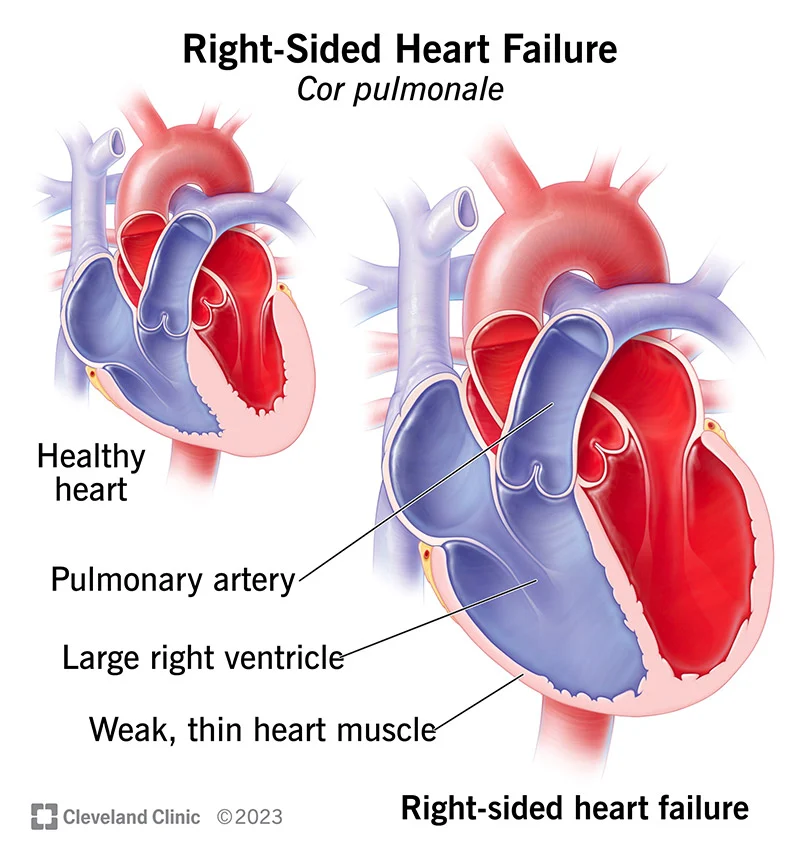
The causes fall into predictable buckets, and knowing which bucket a patient falls into changes your entire management approach. The biggest category by far is left-sided heart failure. When the left ventricle fails, pressure backs up into the lungs, pulmonary vascular resistance rises, and eventually the right ventricle cannot handle the afterload. This is the most common cause and accounts for roughly 90 percent of cases. You can think of right-sided failure as frequently being left-sided failure's shadow problem. The second major category is chronic lung disease leading to cor pulmonale. COPD is the usual culprit. Pulmonary hypertension from any cause puts sustained pressure on the right ventricle until it dilates and fails. Pulmonary embolism, whether acute or chronic thromboembolic, belongs here too. Obstructive sleep apnea is an underrated contributor that I see way too often missed in routine practice. Less common but important causes include right ventricular infarction, severe tricuspid or pulmonic valve disease, and primary cardiomyopathies. Congenital heart disease can also present as right-sided failure decades after initial repair. The point is that right-sided failure is almost never a primary diagnosis. It is a downstream event.
How It Actually Presents in Practice
The classic signs are peripheral edema that is pitting and symmetric, elevated jugular venous pressure, hepatomegaly with right upper quadrant tenderness, ascites in more advanced cases, and hepatic congestion that chronically elevates liver enzymes. You will see hepatjugular reflux when you press on the liver. Kussmaul's sign, a rise in JVP on inspiration, points toward constrictive pericarditis or restrictive cardiomyopathy as the underlying etiology rather than simple volume overload. One thing beginners consistently miss is that the lungs may be perfectly clear on examination in isolated right-sided failure. If a patient has massive bilateral leg edema, distended neck veins, and crackles throughout both lung fields, you are likely dealing with left-sided or biventricular failure, not isolated right-sided failure. The presence or absence of pulmonary findings is one of the fastest ways to narrow your differential. I encountered a particularly stubborn case a few years back where a patient had refractory ascites and peripheral edema that did not respond to standard diuretic doses. We cycled through furosemide up to 160 mg daily with minimal effect. The turning point came when we checked the liver ultrasound and noticed a prominent caudate lobe. That pointed toward constrictive pericarditis rather than simple right ventricular failure. The caudate lobe has direct drainage into the inferior vena cava, so it enlarges selectively when pericardial constraint is present. Once we confirmed constriction with cardiac MRI, the management changed completely. Diuretics were adjusted, but the definitive answer was surgical pericardiectomy. Treating the diuretic resistance as a medication dosing problem instead of a diagnostic clue would have wasted months.
Get the Full Details
Diagnostic Approach
Echocardiography is your first-line tool. You want to assess right ventricular size, systolic function, estimate pulmonary artery pressures, and evaluate the left ventricle simultaneously. Tricuspid regurgitation velocity gives you a rough estimate of pulmonary systolic pressure. A tissue Doppler measurement of the septal e' velocity lets you calculate the E/e' ratio and distinguish between pre-capillary and post-capillary pulmonary hypertension, which is critical for treatment decisions. BNP or NT-proBNP will be elevated, though levels tend to be lower than in left-sided failure because the right ventricle generates less wall stress. Troponin may be elevated if there is right ventricular strain or ischemia. A chest X-ray will show enlarged cardiac silhouette and prominent pulmonary vasculature, though in chronic cor pulmonale the heart size may appear normal or even small. CT pulmonary angiography is indicated when pulmonary embolism is in the differential. Right heart catheterization is the gold standard for confirming pulmonary hypertension and determining whether it is pre-capillary or post-capillary. Electrocardiogram often shows right axis deviation, right ventricular hypertrophy, and P pulmonale. These findings are not specific but they support the diagnosis when present alongside clinical evidence.
Treatment Strategy
Management centers on three principles: reducing venous congestion, treating the underlying cause, and avoiding interventions that decrease right ventricular preload excessively. Diuretics are the mainstay for congestion. Loop diuretics like furosemide or torsemide are first line. Torsemide has better oral bioavailability than furosemide, which matters when gut edema from congestion impairs absorption. I prefer torsemide in chronic right-sided failure patients specifically for that reason. A starting dose of 20 to 40 mg orally once daily is reasonable, adjusted based on response. Sodium restriction is non-negotiable. I tell patients to keep intake below 2 grams of sodium per day. Fluid restriction becomes necessary when hyponatremia develops, which is a marker of advanced disease and activates the renin-angiotensin-aldosterone system aggressively. For pulmonary hypertension secondary to lung disease, optimizing the underlying pulmonary condition is paramount. Oxygen therapy, bronchodilators, and in select cases pulmonary vasodilators. The vasodilators like sildenafil or bosentan require careful selection. They work in pre-capillary pulmonary hypertension but can worsen ventilation-perfusion mismatch and are contraindicated in post-capillary hypertension due to left heart disease. Giving a pulmonary vasodilator to a patient with untreated left-sided failure can precipitate pulmonary edema. This is one of the most dangerous pitfalls I see.
Rate control in atrial fibrillation is important because the right ventricle depends on atrial kick. Loss of coordinated atrial contraction can acutely decompensate a patient with right ventricular dysfunction. Anticoagulation should be considered based on stroke risk scores. Digoxin has a role in select cases for rate control and mild inotropic support, though it must be used cautiously given the narrow therapeutic index and renal clearance considerations. Inotropes like milrinone or dobutamine are reserved for acute decompensation with low cardiac output. Milrinone is particularly useful because it is a phosphodiesterase-3 inhibitor that provides both inotropic and vasodilatory effects, reducing pulmonary vascular resistance. The downside is that it can cause significant hypotension and arrhythmias, and it is renally cleared so dose adjustment is mandatory. I only use it in monitored settings.
Prognosis and Monitoring
Right-sided heart failure carries a worse prognosis than isolated left-sided failure when it is due to pulmonary hypertension. The 5-year survival for idiopathic pulmonary arterial hypertension remains around 50 percent despite advances in targeted therapy. When right-sided failure is secondary to left-sided heart failure, the prognosis tracks with the left-sided disease. Survival improves substantially when the underlying cause is correctly identified and treated, which is why the diagnostic workup matters more than any single medication choice. Regular monitoring should include weight tracking, assessment of edema and JVP, basic metabolic panels to check renal function and electrolytes, and periodic echocardiography. Patients should be educated to recognize early signs of decompensation: rapid weight gain, increased swelling, worsening shortness of breath, and decreased exercise tolerance. A weight gain of more than 2 pounds in a day or 5 pounds in a week is a red flag that warrants prompt diuretic adjustment. One limitation worth noting is that standard heart failure guidelines are built around left-sided and biventricular failure. There is comparatively less high-quality evidence from randomized controlled trials specifically for isolated right-sided heart failure. Most treatment recommendations are extrapolated. This means clinical judgment and attention to the underlying etiology carry more weight than protocol-driven approaches. If a patient is not responding to standard therapy, the question is rarely "what dose should I increase?" It is usually "have I correctly identified and treated the root cause?"