How to Actually Do a Risk Analysis Under the HIPAA Security Rule
A risk analysis under the Security Rule isn't a form you fill out and file. It's a process that evaluates potential risks to electronic protected health information across your entire system. The HHS OCR expects you to identify threats, assess likelihood and impact, then document mitigation steps. That sounds straightforward until you realize what counts as an "electronic system" in a modern clinic or practice. It considers everything that stores, transmits, or receives ePHI. That includes clinical workstations, billing servers, cloud-hosted EHR platforms, mobile devices used by staff, email gateways, backup systems, and even physical entry points to server rooms. You also need to account for human factors—phishing susceptibility, improper device handling, contractor access. The rule breaks this into three main areas: administrative safeguards, physical safeguards, and technical safeguards. Each one feeds into the overall risk picture. I spent about six months working through a compliance gap at a mid-sized orthopedic group that ran five satellite offices. What tripped them up wasn't the centralized EHR—that was well locked down. It was the ancillary systems. Lab reporting interfaces, a third-party scheduling portal, and roughly forty tablets that nurses used for medication administration in patient rooms. None of those were on the same network segment as the main EHR. When I mapped it out, I found that two of the satellite offices had no VPN or remote access controls at all. The tablets were running an outdated OS version with no MDM enrollment. That's the kind of thing that doesn't show up on a server inventory spreadsheet.
The Assessment Methodology
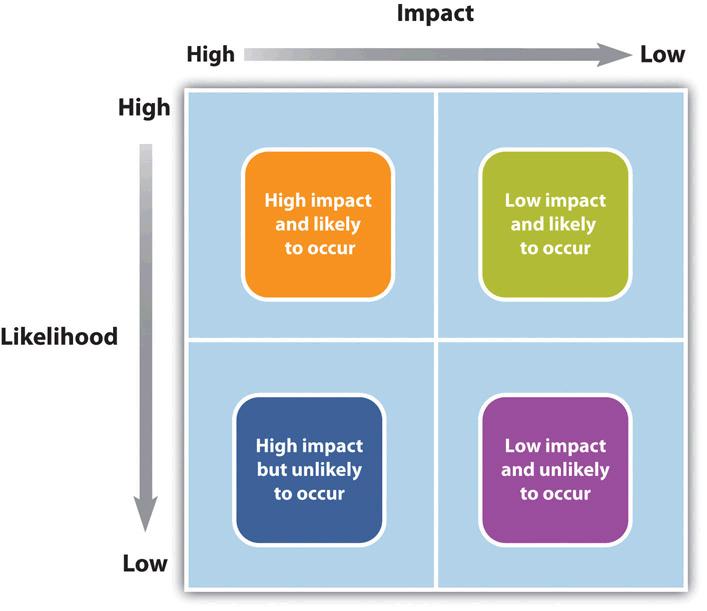
Most teams use a probability versus impact matrix. It's not fancy but it works if you calibrate it properly. For each identified threat, you assign a likelihood score—typically low, medium, or high—based on historical data, industry benchmarks, and current control effectiveness. Then you assign an impact score reflecting the potential harm to patient safety, operational continuity, and regulatory exposure if that threat materializes. Multiply or combine these to get a risk level. Anything rated medium or above triggers a mitigation requirement. The common mistake people make is inflating every threat to high likelihood because "it could happen." That dilutes the whole exercise. I use a stricter standard: likelihood must be supported by evidence. A failed login attempt from an external IP three times in a quarter is documented. A hypothetical ransomware scenario with no breach indicators gets marked as medium likelihood at most. You should be able to point to logs, incident reports, or third-party risk assessments that justify your scoring. Impact scoring tends to be more subjective. Here's a practical anchor: if an event would cause patient harm, it's high impact. If it would cause a temporary operational disruption but no clinical risk, it's medium. If it's purely administrative inconvenience with no data exposure, it's low. This keeps the analysis from becoming an endless debate about whether something is a three or a four on a five-point scale.
Documentation Requirements
You need to document the scope, methodology, findings, and risk mitigation plan. The documentation should be specific enough that an auditor can trace how you arrived at each risk determination. Vague entries like "risk assessed and mitigated" are not sufficient. Include the date of assessment, the systems reviewed, the personnel involved, and the specific controls evaluated. If you reuse a prior analysis, note what changed since that assessment and why the prior conclusions still hold. One thing I've learned the hard way is that the documentation itself becomes evidence during an OCR investigation. In 2022, a dental practice in Florida got a $75,000 settlement partly because their risk analysis document was dated two years before the actual breach and contained no updates despite a documented IT restructuring. OCR viewed that as a failure to conduct a reasonable and accurate assessment. The document needs to be a living record, not a checkbox exercise.
Get the Full Details

Common Pitfalls That Undermine the Process
The biggest problem I see is treating the risk analysis as a one-time annual event. The Security Rule requires ongoing analysis. New systems get deployed, staff change roles, cloud providers update their infrastructure, and threat landscapes shift. If you're doing this once a year on a set calendar date, you're probably missing things between cycles. I recommend quarterly reviews of high-risk systems and annual comprehensive assessments covering everything else. Another issue is scope neglect. People analyze their core EHR thoroughly and then skip the peripherals. But peripheral systems often have weaker controls and represent the easiest entry point for an attacker. A compromised printer management console, an unpatched Wi-Fi controller, or a shared service account used by a billing vendor can all lead to ePHI exposure. Map every touchpoint, even the ones you don't think matter. Vendor risk is another blind spot. If you use a business associate that processes ePHI, their security posture is your security posture in the eyes of the rule. I've seen practices assume that because their BA has a SOC 2 report, they don't need to evaluate it themselves. A SOC 2 report tells you about general IT controls, not specifically about how ePHI is handled. Review the BA's risk analysis directly or require a HITRUST certification that covers HIPAA-specific requirements. Otherwise you're flying blind on someone else's controls.
When Standard Approaches Fall Short
There's a specific edge case that comes up repeatedly: hybrid cloud environments where some ePHI lives on-premises and some in a public cloud provider. The risk profile changes depending on where the data sits. On-prem systems need physical security assessments and local access controls. Cloud systems need configuration audits, encryption-in-transit verification, and review of the provider's incident response capabilities. The complication arises at the boundary—where data moves between environments. Encryption keys, authentication handoffs, and API endpoints become critical risk points. I encountered this with a home health agency that used a cloud-based wound care documentation system integrated with their on-premises ADT feed. The integration used a shared service account with broad permissions. During a penetration test I commissioned, the service account had access to twenty-three different databases. The risk analysis initially classified this as low risk because the data was encrypted at rest. That was wrong. Encryption at rest doesn't address the risk of lateral movement once the account is compromised. We reclassified it as high risk and required role-based access restriction before the next audit cycle.
Practical Steps to Build a Defensible Analysis
Start by creating an asset inventory that includes hardware, software, data flows, and network topology. Don't rely on existing inventories—they're usually incomplete. Walk the floor. Check what's actually connected. Then identify all ePHI touchpoints across that inventory. Map the data flow from creation to deletion. Note where data is stored, where it's transmitted, and who has access at each point. Next, catalog existing controls against the NIST 800-66 guidance or the CCM framework. Be honest about what's actually in place versus what's documented. A policy saying "all laptops must be encrypted" means nothing if half the fleet doesn't have full disk encryption enabled. Verify the control effectiveness, not just its existence. Identify threats using a structured list. Natural disasters, insider threats, external attacks, system failures, and supply chain compromises cover the major categories. For each threat, assess likelihood and impact using your calibrated scales. Document the reasoning. Then determine whether the residual risk is acceptable or whether additional controls are needed. If additional controls are needed, document the mitigation plan with timelines and responsible parties.
This process typically takes two to four weeks for a small practice with a single location and straightforward infrastructure. A multi-site organization with complex integrations can take eight to twelve weeks. Budget accordingly. Rushing it produces a document that won't hold up under scrutiny.
Alternative Approaches and Their Trade-offs
Some organizations use automated scanning tools that claim to perform risk analyses. These tools are useful for vulnerability identification but they don't replace the analytical component. They can tell you that a server is missing a patch. They can't tell you whether that unpatched server processes ePHI, how likely exploitation is given your network segmentation, or what the clinical impact would be if it were compromised. Use automated tools as inputs to your analysis, not as the analysis itself. A more thorough approach involves engaging a third-party assessor with healthcare security expertise. This costs more upfront but can surface risks your internal team misses simply because they're too close to the environment. I generally recommend this for organizations with more than fifty endpoints or any cloud-based ePHI processing. The return on investment shows up during audits and, more importantly, during incident response when you need to know exactly what you're dealing with. The risk analysis process is imperfect by nature. It's based on estimates, not certainties. You will miss threats. Some risks will materialize that your analysis rated as low probability. That doesn't mean the analysis was wrong—it means risk management is probabilistic, not deterministic. What matters is that your methodology is sound, your documentation is defensible, and you're actively managing risk rather than ignoring it until something breaks.