So You Need to Do a Risk Assessment in Occupational Therapy
Risk assessment in occupational therapy isn't really a single thing you do. It's a cluster of overlapping processes that look at what could go wrong when someone tries to manage their daily life, and then figuring out what you can do about it before something bad happens. You'll hear different frameworks thrown around — some places use the CMOP-E, others lean on MOHO, and a lot of NHS teams just wing it with a combination of the two plus whatever template their manager approved last quarter. The actual work usually involves looking at three buckets: the person's health and cognitive status, their environment, and the demands of the activities they need or want to do. Then you cross-reference those against known risk indicators and decide on interventions. It's straightforward in theory. In practice, it's more like trying to nail jelly to a wall most of the time.
Risk Assessment Occupational Therapy in Practice
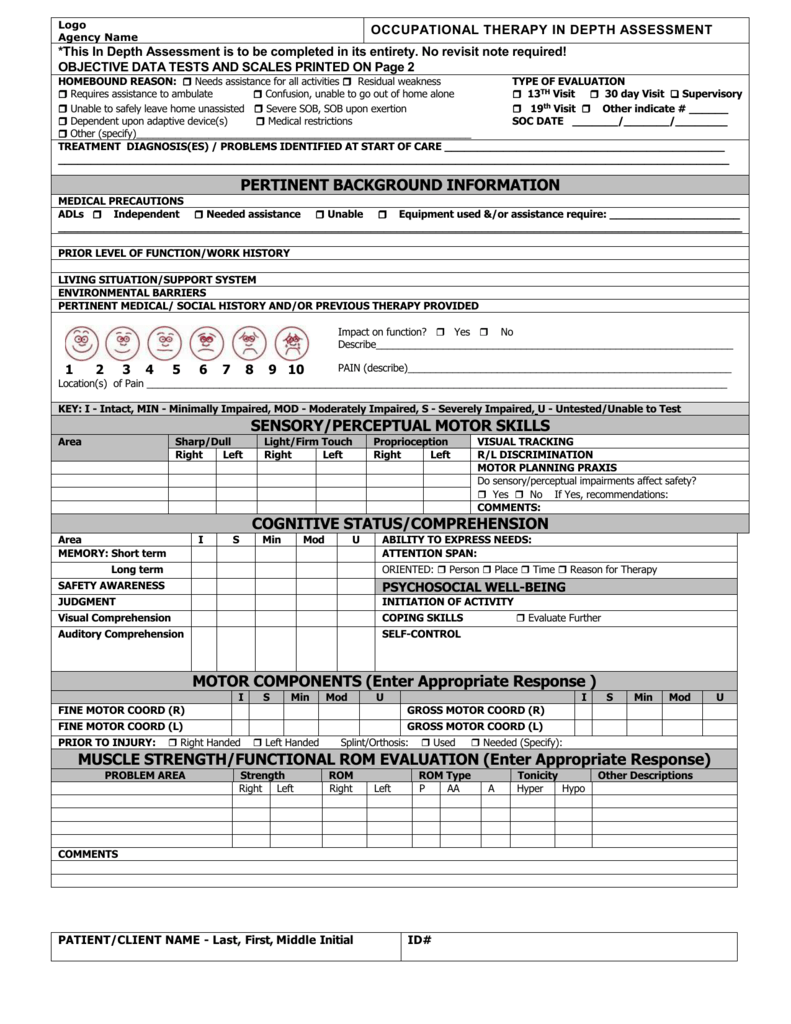
Here's how I actually approach it when I get a referral that involves risk. First, I check whether there's already a documented risk assessment from another service. A lot of the time there is — nursing, physio, social care, sometimes all of the above. The problem is each of them uses different scales and different definitions of what constitutes a risk. So before I write a single word, I do a quick reconciliation exercise. I map their findings onto my own framework so I'm not duplicating work or contradicting myself. For the OT-specific part, I focus on functional risk. That means looking at what the person can actually do, not what they're theoretically capable of doing in ideal conditions. Fall risk is the big one, obviously. But I also look at medication management risk, nutritional risk, fire safety risk, road crossing risk for people with visual or cognitive deficits, and social isolation risk which gets overlooked way too often. I use a mix of standardised tools and clinical judgment. The Morse Fall Scale is common but it's mainly designed for hospital inpatients. If you're assessing someone in their own home, the STAMP or the HOME Home Safety Assessment scale works better. For cognition-related risk, I'll pull in the MoCA or MMSE results if they're available, but honestly, watching someone try to manage their own routine for ten minutes tells you far more than any score.
The Toolkit You Actually Need
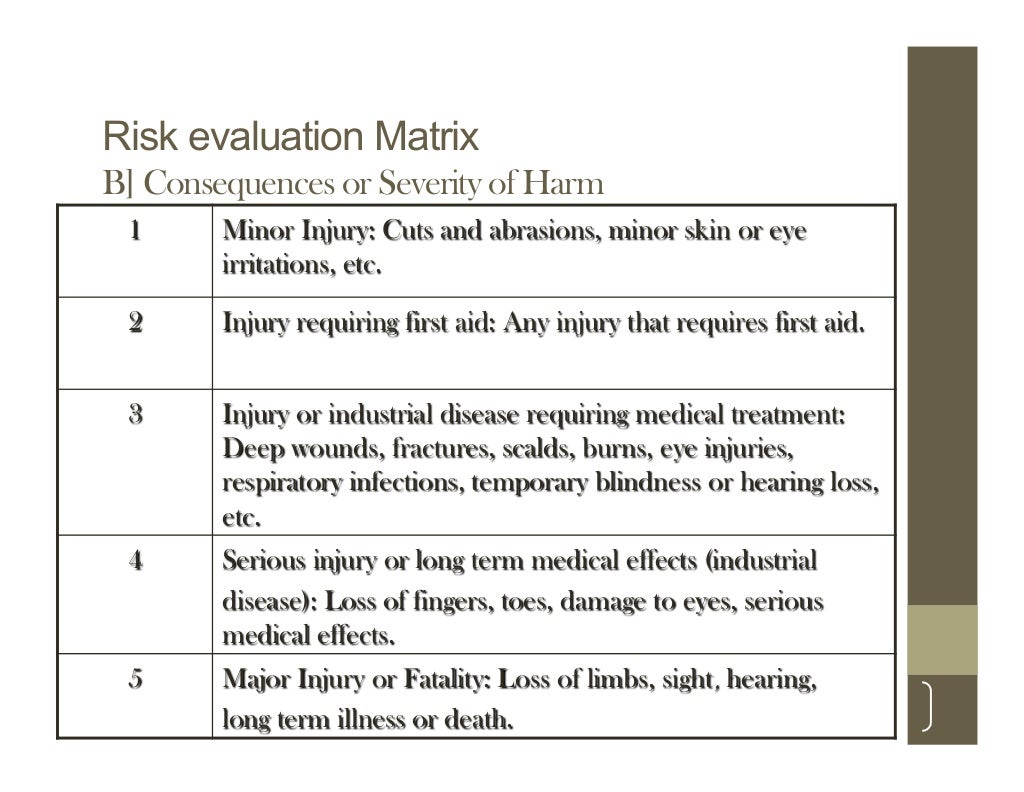
You don't need expensive software. Most of what I use is freely available. The WHO Home Assessment Protocol is open access and covers the basics of environmental risk. The Falls Risk for Older People – Community version (FROP-Com) is another solid free tool. For driving fitness, the Driver and Vehicle Licensing Agency has guidance documents that are worth reading even if you're not doing a full driving assessment. The ones I find most useful in day-to-day practice are the ones I've adapted over the years rather than bought. My current go-to is a simple matrix where I rate likelihood and severity for each identified risk, then assign a priority tier. High likelihood plus high severity gets you immediate intervention. Medium-medium gets you monitoring and a review date. Low anything gets noted but doesn't drive the care plan. Documentation matters more than people realise. A well-written risk assessment saves you when things go wrong, and in this field, things do go wrong. I keep it concise — problem statement, risk factors identified, evidence base for each, intervention proposed, risk level after intervention, review date. That's it. Anything longer tends to get unread and provides no legal protection.
Get the Full Details

A Problem I Ran Into and How I Handled It
Last year I was assessing a man in his seventies with early-stage dementia who lived alone. Standard fall risk tools scored him as low risk. He'd had no falls in the past year. He could negotiate stairs without difficulty. He even passed the Timed Up and Go test comfortably. So by every conventional measure, he was fine. But I'd noticed he kept leaving the stove on. Not dramatically — just a matter of forgetting to turn it off after making tea or warming food. The kitchen was small, gas hob, no automatic shut-off. Standard risk tools don't capture that. So I did an informal observation over two visits, tracking what happened when he cooked. On the second visit, I stayed for the full routine and measured how long the hob stayed on after he walked away. Average was eight minutes. Maximum was twenty-two. The workaround was straightforward but not obvious. I arranged for a kettle coin timer and a simple gas safety cut-off device — the kind that auto-shuts the gas supply after a set period. I also got his daughter to do a weekly check-in call. That reduced the actual risk from catastrophic to manageable without removing his independence. A purely scores-based assessment would have missed this entirely.
Things Nobody Tells You About This Stuff
The biggest pitfall I see is over-reliance on standardised tools without contextual interpretation. A patient scoring low on a cognition screen might still struggle with complex medication regimes because of executive function deficits that the test doesn't capture. Conversely, someone with a low score on a mobility assessment might navigate their actual home environment without issue because they've developed workarounds you wouldn't predict from the test alone. Another thing: risk assessment is never static. The moment you write "low risk" on a form, someone might read it as permission to do less. I've seen care packages get reduced because a previous assessment said the person was safe. The assessment needs to include a clear review timeframe and explicit language that the risk rating is conditional on current circumstances. The legal dimension is worth paying attention to. If you're working in the UK, the Care Quality Commission expects documented risk assessments as part of fundamental standards. In the US, CMS guidelines for skilled nursing facilities have their own requirements. Malpractice claims related to occupational therapy almost always involve either no assessment or an assessment that was clearly inadequate. Protection comes from process, not outcome. You can do everything right and someone still gets hurt. The question is whether you can demonstrate that you followed a reasonable process.
One more practical note — collaboration improves accuracy significantly. When I involve the patient's family, carers, and other professionals in the assessment conversation, I usually identify two to three additional risk factors that I'd have missed working in isolation. It takes longer upfront but reduces the chance of a serious incident later. Time invested in multi-disciplinary discussion typically pays for itself within a month.