Understanding Risk Assessment Tools in the NHS
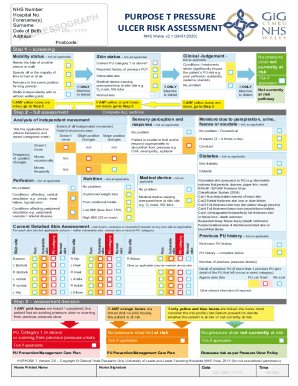
Risk assessment in the NHS isn't something you can wing. The framework is built around patient safety, clinical governance, and legal compliance, and the tools used to support that need to be robust enough to withstand scrutiny from multiple angles. There are different types of risk assessment tools depending on what area you are working in. Frailty assessments for elderly patients, medication risk evaluations, infection control screening, and workplace hazard evaluations all use different instruments. The main repository for NHS-approved risk assessment tools is the NHS Digital Library and the National Clinical Guideline Centre. You can also find validated tools on the NICE website and through the Health and Safety Executive's healthcare section. Most trusts also maintain their own internal tool libraries on the intranet, usually under the clinical governance or patient safety department pages. I spent about three weeks tracking down a specific pressure ulcer risk tool for a ward audit and found myself bouncing between four different portals before landing on the Braden Scale documentation, which was hosted on a trust intranet page that hadn't been updated since 2019. The tool itself was still valid, but the guidance around its implementation had drifted. I ended up cross-referencing it with the original Braden Scale publication from 1987 and the more recent WUN (Wound Universality Network) updates to make sure we were scoring correctly. That kind of effort is normal when you are pulling tools from fragmented sources.
Some tools are free and openly accessible. Others require a license or purchase through your trust's procurement department. The Waterlow score for pressure ulcer risk is widely used and freely available in most NHS trusts. The Morse Fall Scale is another standard tool that doesn't require payment. But things like certain mental capacity assessment frameworks or specialist oncology risk calculators may need you to go through formal procurement, which can add weeks to your timeline.
How to Implement a Risk Assessment Tool Correctly
Picking the right tool is only the first step. I have seen entire departments get it wrong by selecting a tool that didn't match their patient population. A tool designed for acute medical wards will not work reliably in a community palliative care setting. The scoring thresholds, the weightings, and the cut-off points are all calibrated for specific populations. Using them outside that calibration range gives you false confidence in the results. The process starts with a needs analysis. What kind of risk are you trying to capture? Who is your patient group? What decisions will the assessment inform? If you skip that step, you will end up with data that looks complete but doesn't actually guide clinical action. I once worked with a team that implemented a generic hospital-acquired risk tool across five wards. It took about four hours per patient on average to complete because the tool was overloaded with sections that weren't relevant to those wards. Staff started gaming the assessments just to clear the backlog. We had to pull the tool out within two months and replace it with a ward-specific version that cut completion time down to roughly forty-five minutes per patient. Training is where most implementations stumble. Sending a PDF to staff and calling it training doesn't work. You need structured sessions where people practice scoring with real cases and discuss where the grey areas are. I typically run a half-day workshop that includes about six practice scenarios with guided feedback. After that, you set up a two-week validation period where senior staff spot-check assessments and provide corrective feedback. This usually catches about thirty percent of scoring errors before they become embedded in the system.
Get the Full Details

Common Pitfalls and What Beginners Miss
One thing that catches people out is assuming that a higher score always means higher risk. Some tools use reverse scoring or have inverse relationships between certain domains. The Composite Acute Violence Risk Index is an example where a lower score in a particular subscale can indicate elevated risk. If you are building a reporting dashboard from these tools, you need to map the scoring logic correctly or your risk stratification will be backwards. Another oversight is treating risk assessment as a one-time event. Many tools are designed to be repeated at defined intervals. The NEWS2 score, for instance, is meaningless if it is only taken once. It is the trend over time that drives escalation decisions. I have seen EPR systems configured to store individual scores without calculating delta values or trend lines, which effectively neutralises the tool's clinical utility. Make sure your system can track changes across time, not just snapshot values. Integration with existing workflows is also critical. A risk assessment tool that requires staff to log into a separate system, navigate through five screens, and manually transfer data into another platform will not get used consistently. The best tools sit within the electronic patient record or clinical documentation system that staff already use. If you cannot integrate it, build a simple API bridge or a structured data export rather than accepting manual dual entry as normal.
Data Quality and Audit Readiness
When you are operating under NHS governance structures, your risk assessment data will be audited. CQC inspections routinely check whether assessments are being completed, whether they are completed accurately, and whether the outcomes are being acted upon. Your documentation needs to show the full audit trail: who completed the assessment, when, which version of the tool was used, the score, and what action followed. I encountered a situation where a trust was auditing fall risk assessments across twelve wards and found that seventeen percent of the tools being used were outdated versions that had been superseded by a revised scoring methodology. The tool itself looked identical on the surface, but the risk category boundaries had shifted. Patients who would have been flagged as high risk under the old version were classified as medium risk under the new one, and the care plans weren't updated to reflect that change. This is exactly the kind of thing that surfaces during inspection and creates immediate compliance findings. Keep a version log for every tool in your portfolio. Note when you adopted it, when it was last reviewed, and what changes were made. Most national tools publish update notices on the originating organisation's website. Subscribe to those alerts. It takes about five minutes a month and prevents exactly this kind of drift.
Limits and When Tools Fail
No risk assessment tool captures everything. They are structured instruments with inherent blind spots. A frailty assessment might flag a patient as low risk based on physical indicators while missing early signs of cognitive decline. A medication risk tool might account for drug interactions but not for a patient's ability to self-administer correctly at home. The tool gives you a score, not a diagnosis. Clinical judgment still matters, and any system that pretends otherwise is setting staff up to rely on false precision. There are also boundary conditions where tools simply break down. Complex patients with multiple comorbidities, learning disabilities, or atypical presentations often score unpredictably on standardised tools. I worked with a patient who scored in the lowest risk category on a sepsis screening tool despite having early signs of urosepsis, because his baseline white cell count was chronically elevated due to a separate condition. The tool's algorithm couldn't account for that baseline. We ended up relying on clinical observation and serial NEWS2 checks rather than the screening tool alone. For complex cases, the tool should inform rather than drive your decision-making. If you are building a risk assessment programme from scratch, start with the population and work backward to the tool, not the other way around. Validate it with a small pilot before rolling it out department-wide. Budget time for staff training and ongoing quality monitoring. And keep a clear record of what the tool does and does not do, because at some point someone is going to ask you to defend a decision that was based on its output.