Running a Risk Management Program That Actually Works
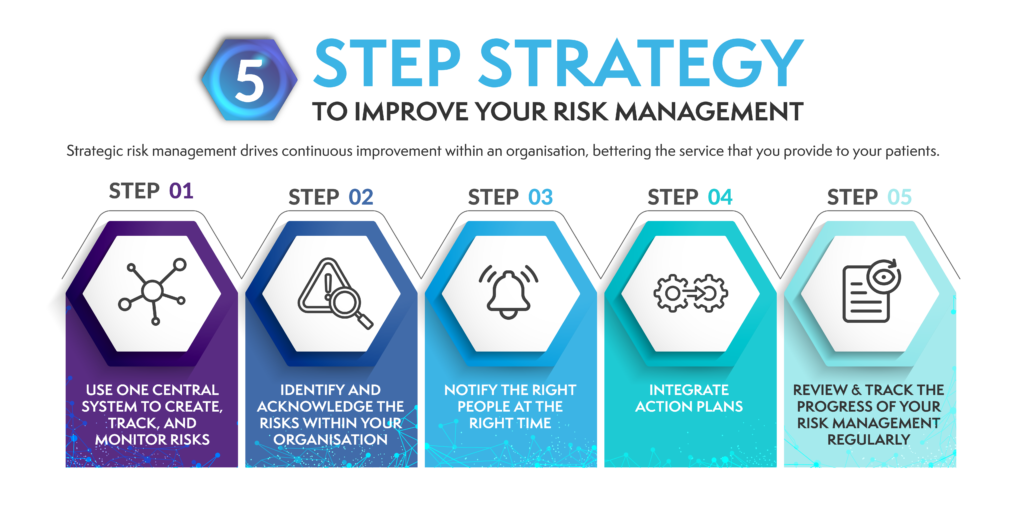
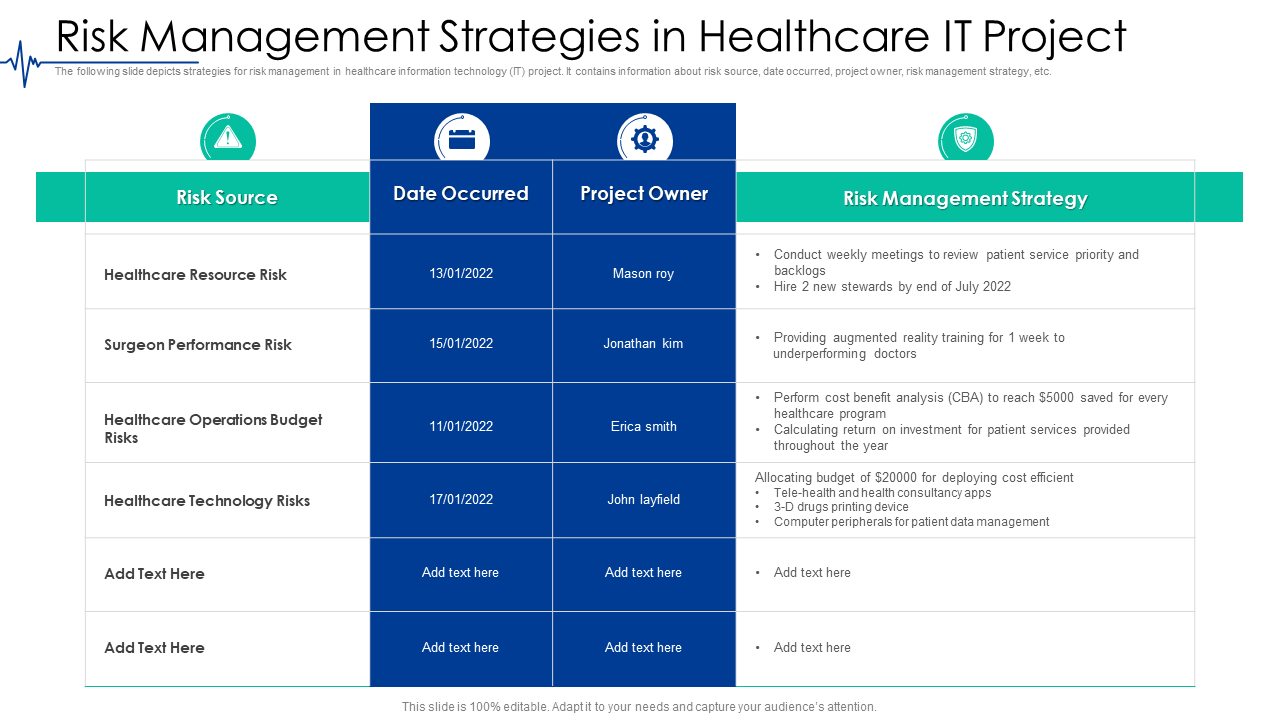
Most healthcare organizations treat risk management like a compliance checkbox. They stack up policies, run the annual training module, and file the reports. That approach leaves massive gaps. I watched a mid-size hospital system get blindsided by a supply chain failure that a proper risk framework would have caught months earlier. The root cause wasn't complex. Their incident reporting system was so buried under administrative overhead that frontline staff simply stopped filing anything meaningful.The problem starts with how most people define risk in healthcare. It isn't just patient safety or regulatory compliance. It's financial exposure, reputational damage, operational downtime, vendor reliability, cyber liability, and workforce retention rolled into one messy system. You can't manage what you can't categorize. Start by building a risk register that forces you to tag every identified risk with its domain. Clinical, operational, financial, technological, regulatory. If a risk doesn't fit one of those buckets, your taxonomy is incomplete. Here's how the actual process works when it's done right. I worked through a near-miss event where a pharmacy system update introduced a dosage calculation error that didn't trigger any alert. The integration team had tested the software in isolation but never validated it against the clinical workflow in a live environment. We didn't have a formal risk assessment for that change. What saved us was an informal handoff document between IT and pharmacology that had been sitting unused for two years. The workaround was straightforward: we required every system change, no matter how small, to go through a standardized risk impact checklist before deployment. It added about 45 minutes to the typical change request process, but it caught three subsequent issues before they reached the floor. The checklist takes this shape: The risk scoring part is where most organizations fail. They use vague labels like low, medium, high without defining the numerical thresholds. Write down exactly what each level means. Low should mean the cost of mitigation exceeds the expected loss. Medium should mean there's a credible path to reduce the risk below the low threshold. High should mean you either stop the activity entirely or implement controls immediately. I've seen teams assign "medium" to events with potential multi-million dollar liability because someone didn't want to raise alarms. Clear thresholds remove that ambiguity.
Most risk management frameworks treat risks as independent events. They aren't. In healthcare especially, risks cascade. A staffing shortage leads to overtime burnout. Burnout increases medication errors. Errors trigger adverse event reports. The reports strain compliance resources. Compliance pressure causes documentation shortcuts. Shortcuts create audit findings. Findings increase insurance premiums. Premiums force budget cuts that worsen the original staffing shortage. This is called risk convergence and it's why your risk register needs a dependency map. Link related risks together so that when one materializes, you can see what else is likely to follow within 30 to 90 days. Another counter-intuitive reality: exhaustive risk identification often produces worse outcomes than targeted identification. When I ran a full enterprise risk assessment across a 400-bed facility, we identified roughly 800 individual risks. The board reviewed maybe twelve of them. The rest sat in a binder nobody opened. The exercise took six weeks and cost approximately $47,000 in staff time. We then switched to a focused approach using real incident data from the previous 24 months, benchmarked against our specific payer mix and service lines. We identified 43 risks. We addressed 38 of them within six months. The focused method takes about three weeks and costs a fraction of the full assessment. Use historical incident data as your primary input. Supplement it with forward-looking scenario planning for areas where you have no track record yet.
Controls That Actually Reduce Risk
Risk treatment options fall into four categories: avoid, transfer, mitigate, or accept. Avoidance means shutting down the activity that creates the risk. Transferring means insurance or contractual shifts. Mitigation means implementing controls that reduce either the likelihood or the impact. Acceptance means acknowledging the risk and monitoring it. Most organizations overuse acceptance and underuse mitigation. That's a financial mistake. Take cyber risk as an example. Buying cybersecurity insurance transfers financial consequence but doesn't reduce the probability of a breach. A proper mitigation strategy for a hospital involves network segmentation, privileged access management, endpoint detection and response, and regular penetration testing. Each of those has a cost. Each of those reduces the likelihood of a successful attack. Insurance should be your last line of defense, not your first. I've seen organizations spend $200,000 annually on cyber insurance while running unpatched systems and reusing default credentials. The insurance payout covered part of a breach that cost them $3.2 million in total. Risk management is about reducing exposure, not buying a parachute and never learning to fly. For clinical risk, the strongest mitigation is often process standardization. Medication reconciliation protocols, surgical safety checklists, and handoff communication standards have all been shown to reduce adverse events by measurable margins. The Joint Commission requires some of these. The ones they don't require are usually where the biggest gains live. I implemented a structured handoff protocol in a trauma unit that reduced communication-related errors by roughly 31 percent over eight months. The protocol was simple: a standardized template, a mandatory read-back, and a designated verification window. It cost maybe $8,000 to set up and took two weeks to train. The reduction in near-miss events alone justified the investment within four months.
Get the Full Details

Vendor and Third-Party Risk
This area gets neglected until something breaks. Your EHR vendor, your medical equipment supplier, your billing processor, your cloud hosting provider — they all represent risk points. A ransomware attack on a third-party vendor can take down your entire operation. The 2020 change management incident at a major EHR platform affected over 100 hospitals and caused scheduled procedures to be cancelled for days. Organizations that had mapped their vendor dependencies and maintained manual workarounds recovered significantly faster. Build a vendor risk assessment that covers security posture, business continuity plans, financial stability, regulatory compliance history, and contractual terms around data ownership and breach notification. Require SOC 2 reports for technology vendors. Require evidence of disaster recovery testing for critical suppliers. Contractually bind them to notify you within 24 hours of any security incident affecting your data. The fine print matters more than people think. I negotiated a clause with a lab services provider that required them to cover the cost of alternative testing arrangements if their turnaround time exceeded 48 hours during a disruption. That clause saved us approximately $180,000 in one incident when their facility had a power failure that lasted three days.
Monitoring and Metrics That Matter
Risk management without measurement is just opinion. Track leading indicators, not just lagging ones. Leading indicators predict problems before they happen. Lagging indicators tell you what already went wrong. Both matter. Leading indicators include near-miss reporting rates, compliance audit scores, staff training completion, vendor risk assessment currency, and percentage of high-risk processes with documented controls. Lagging indicators include incident reports, adverse events, regulatory citations, claim denials, and breach notifications. A near-miss reporting rate that's too low is a red flag. It usually means the reporting system is broken or the culture discourages disclosure. I saw this at a facility where the near-miss count dropped 60 percent year over year. Leadership celebrated it as improved safety. The actual explanation was that staff had stopped filing reports because the incident management platform crashed for three consecutive months and nobody fixed it. The metric looked good. The reality was deteriorating. Fix the reporting system before you trust the numbers.
Common Pitfalls
The biggest mistake is treating risk management as a standalone department rather than a cross-functional responsibility. When risk ownership sits entirely with one team, everyone else assumes someone else is handling it. Assign risk owners for each category across every department. The CNO owns clinical risk. The CIO owns technology risk. The CFO owns financial risk. The COO owns operational risk. They report to a centralized risk committee that meets monthly. That structure forces accountability without creating bottlenecks. Another frequent failure is relying solely on annual assessments. Risk environments change constantly. A new regulations, a merger, a pandemic, a cyberattack on a peer organization — these shift the risk landscape overnight. Implement quarterly risk reviews at minimum. Pull recent incident data. Scan for emerging threats in your specific sector. Update your risk register. A dynamic register is worth more than a perfect annual one. There's also a blind spot around human factors. Technology controls fail. Process controls degrade. People are the constant variable. Staff fatigue, language barriers, hierarchical communication gaps, and turnover all affect risk exposure. I worked with a facility that had excellent policies on paper but a turnover rate of 28 percent annually in their nursing staff. No amount of policy refinement compensates for a workforce that's constantly rebuilding institutional knowledge. Investment in retention and onboarding is a risk mitigation strategy. It's just not the kind that shows up in a traditional risk register.

When Risk Management Fails
Be honest about the limits. Risk management cannot eliminate risk. It can only reduce it to an acceptable level, and "acceptable" is a judgment call that depends on your organization's risk tolerance, which should be defined by your board and leadership team. Some risks will materialize regardless of how well you prepare. A hurricane hits. A key vendor goes bankrupt. A pandemic emerges. Your framework should include contingency planning for low-probability, high-impact events. Business continuity plans, surge capacity agreements, and crisis communication templates are essential even though you hope you never activate them. Small rural hospitals face a particular challenge. They often lack the resources for dedicated risk management staff. The solution isn't to pretend the risk doesn't exist. It's to leverage regional collaborations, shared services arrangements, and state hospital association resources. One rural network in Oklahoma created a shared risk manager position across five facilities. The cost was split proportionally. Each hospital got access to expertise they couldn't afford alone. The approach works if the participating organizations commit genuinely to information sharing rather than using it as a cost-cutting exercise that leaves everyone worse off. The core principle is this: risk management in healthcare is a continuous process, not a periodic exercise. Document your approach. Measure your outcomes. Adjust based on what the data tells you. The organizations that treat it as a living system outperform those that treat it as a compliance chore.