
Assessing Offenders Without Making Things Worse
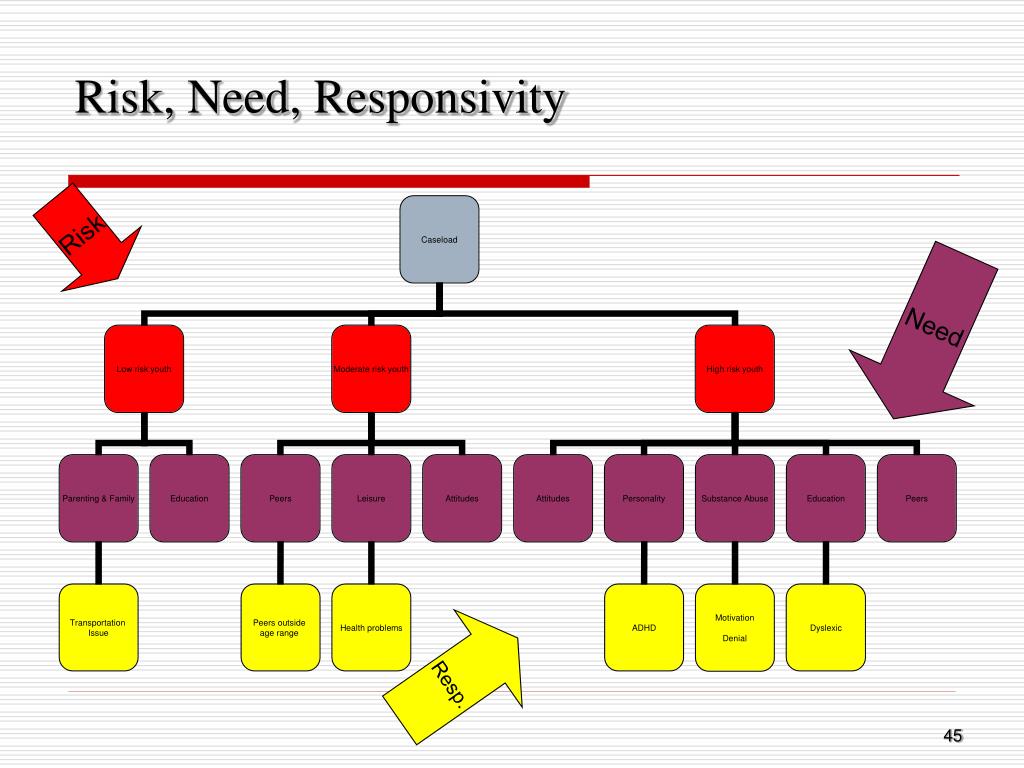
I spent about eight years doing risk assessments in a medium-security facility. The paperwork alone could crush a smaller department. You learn pretty quick that filling out a form correctly matters less than actually understanding what the person sitting across from you is capable of. The Risk Need Responsivity Model For Offender Assessment And Rehabilitation has been around since the nineties, but most people use it wrong. Not because the model is bad, but because they treat it like a checklist instead of a framework for thinking. It breaks down into three pieces, and they need to work together or the whole thing falls apart. Risk is about how likely someone is to reoffend. Need refers to the dynamic factors that drive criminal behavior — things like substance abuse, antisocial attitudes, deviant sexual interests. Responsivity is about matching the intervention to the person's learning style, motivation level, and any barriers they face. The big mistake I see everywhere is treating the Risk level as destiny. High risk means more services. Low risk means less. Simple enough until you encounter someone who scored high on criminogenic needs but also has a severe mental health issue that makes standard programming impossible. I had a guy who tested as high risk on the LS/CMI but was also dealing with active psychosis. Throwing him into a standard cognitive behavioral program was going to fail. We ended up stabilizing his medication first, then slowly introducing modified CBT modules. Took fourteen months instead of four, but he didn't end up back in custody within two years, which was the actual goal.
How Risk Need Responsivity Model For Offender Assessment And Rehabilitation Works in Practice
You start with the risk assessment tool. Most jurisdictions use either the Level of Service Inventory — Revised, or its updated version. These give you a score and a risk category. But here is what the manual doesn't tell you: those tools were normed on populations that don't look like everyone you're assessing. The LS/CMI tends to overpredict risk for certain demographic groups. I learned this the hard way when three consecutive young men I scored as high risk turned out to have zero violations after release. They just had life problems — unemployment, family issues — that the tool interpreted as criminogenic need. The need portion comes next. This is where you identify what actually drives the offending behavior. Criminal history matters, but so do current life circumstances. Employment status, housing stability, peer networks. I developed a habit of cross-referencing the assessment data with what the case file showed about recent arrests. Sometimes the static factors pointed one direction while the dynamic factors pointed another. A guy with a long criminal history but stable housing and a job might be lower risk than his record suggested. Responsivity gets ignored too often. There are two types: general responsivity and specific responsivity. General responsivity means using approaches that actually work for people — cognitive behavioral methods, motivational interviewing, skills training. Specific responsivity means adapting to the individual. Cultural factors, gender, learning disabilities, trauma history. I once worked with a woman who had severe ADHD and couldn't focus through standard group therapy. We switched to individual sessions with shorter, more frequent meetings. She completed the program. She also stayed out of prison.
Common Pitfalls I Wish Someone Had Told Me
The biggest problem is score inflation. Officers who fill out assessments every day develop shortcuts. They assign high scores without probing deep enough, or they project their impressions onto the form. I caught this happening when I reviewed my own assessments after six months. Six of my high-risk scores looked inflated when I checked against actual outcomes. I had to retrain myself to go slower on the need sections, especially the personal and affective components. Another issue is using the model in isolation. Risk assessment should inform case planning, not replace clinical judgment. I saw too many supervisors treat a high score as automatic justification for maximum security placement. That creates a self-fulfilling prophecy. High restriction limits access to prosocial supports, which increases risk of failure, which confirms the original assessment. The loop feeds itself until someone gets hurt. The model also struggles with low-risk offenders. There is evidence that intensive intervention for people who pose minimal risk can actually increase recidivism. This is called the penalty of intervention, and it is real. I learned to pay close attention when the risk tool scored someone as low risk but the supervision plan still included weekly check-ins and mandatory programming. That extra contact wasn't helping. It was creating dependency and removing autonomy.
Get the Full Details

What the Research Actually Says
Meta-analyses from the early two-thousands and follow-up studies show that risk assessment combined with structured case management reduces recidivism by roughly eighteen to twenty-two percent compared to casework alone. The responsivity component adds another five to eight percent reduction when properly implemented. That means a well-run program following the full model gets maybe a thirty percent improvement over standard practice. It is significant, but it is not a silver bullet. There is also the issue of prediction accuracy. Risk tools predict reoffending, not individual outcomes. A score of forty-two doesn't mean anything specific about one person. It means that among similar groups, about that percentage reoffend. I stopped explaining individual scores to judges. Instead I talked about base rates and confidence intervals. They understood better, and they made more reasonable decisions.
When to Use Something Else
The Risk Need Responsivity Model For Offender Assessment And Rehabilitation has real limitations. It was designed for adult male offenders. Applying it to women without modification leads to inaccurate assessments. The criminogenic needs identified for men don't map cleanly onto women's offending pathways. Substance abuse, trauma, and relationship problems matter more for female offenders, and the standard tools underweight those factors. Younger offenders present another problem. Adolescent risk assessment requires different instruments. The PCL:YV or the YLS/CMI work better for that population. I used both, depending on the age group. Mixing them up produces garbage results. People with intellectual disabilities or significant mental illness also require adaptation. Standard assumptions about insight and motivation break down. I worked with a man who scored in the low-risk range but couldn't understand why his actions had consequences. His risk level was real, but the tool missed the cognitive barrier driving his behavior. We ended up using a specialized assessment alongside the standard instrument and got a much clearer picture.
Practical Steps That Actually Help
Start by training assessors properly. One lunch-and-learn session doesn't cut it. I found that structured calibration sessions where officers compare scores on the same cases reduced inter-rater reliability problems significantly. After about twelve hours of calibration work, our disagreement rate dropped from about thirty percent to under ten percent. Use the risk level to inform intensity, not just type of intervention. High risk gets more hours and closer monitoring. Low risk gets minimal contact and a focus on maintaining prosocial connections. Don't waste resources on people who don't need it, and don't abandon people who do. Document the reasoning behind your scores. When I wrote out why I assigned a particular rating, I caught my own biases more easily. I noticed patterns where I was giving higher need scores to people I already disliked or found difficult. That kind of awareness only comes from explicit reflection.

Regularly review outcomes against predictions. Track how many high-risk classifications actually result in new offenses within two years. If your high-risk group has a sixty percent reoffense rate instead of the expected eighty, something is wrong with your process. I ran these reviews quarterly and adjusted my scoring criteria based on the data. It kept me honest.
The Bottom Line
The Risk Need Responsivity Model For Offender Assessment And Rehabilitation is useful when you treat it as a thinking tool rather than a prediction machine. It improves decision-making if you combine it with clinical judgment, adapt it to the population, and regularly check whether your predictions match reality. It fails when you treat scores as facts or ignore the responsivity component entirely. I stopped believing that any single instrument could capture the complexity of an offender's situation. The model helps organize your thinking and flag important factors, but it never replaces careful observation and genuine engagement with the person being assessed. That part cannot be automated or standardized away.
What the Risk Need Responsivity Model For Offender Assessment And Rehabilitation Actually Means
It breaks down into three pieces, and they need to work together or the whole thing falls apart. Risk is about how likely someone is to reoffend. Need refers to the dynamic factors that drive criminal behavior — things like substance abuse, antisocial attitudes, deviant sexual interests. Responsivity is about matching the intervention to the person's learning style, motivation level, and any barriers they face. The big mistake I see everywhere is treating the Risk level as destiny. High risk means more services. Low risk means less. Simple enough until you encounter someone who scored high on criminogenic needs but also has a severe mental health issue that makes standard programming impossible. I had a guy who tested as high risk on the LS/CMI but was also dealing with active psychosis. Throwing him into a standard cognitive behavioral program was going to fail. We ended up stabilizing his medication first, then slowly introducing modified CBT modules. Took fourteen months instead of four, but he didn't end up back in custody within two years, which was the actual goal.

How Risk Need Responsivity Model For Offender Assessment And Rehabilitation Works in Practice
You start with the risk assessment tool. Most jurisdictions use either the Level of Service Inventory — Revised, or its updated version. These give you a score and a risk category. But here is what the manual doesn't tell you: those tools were normed on populations that don't look like everyone you're assessing. The LS/CMI tends to overpredict risk for certain demographic groups. I learned this the hard way when three consecutive young men I scored as high risk turned out to have zero violations after release. They just had life problems — unemployment, family issues — that the tool interpreted as criminogenic need. The need portion comes next. This is where you identify what actually drives the offending behavior. Criminal history matters, but so do current life circumstances. Employment status, housing stability, peer networks. I developed a habit of cross-referencing the assessment data with what the case file showed about recent arrests. Sometimes the static factors pointed one direction while the dynamic factors pointed another. A guy with a long criminal history but stable housing and a job might be lower risk than his record suggested. Responsivity gets ignored too often. There are two types: general responsivity and specific responsivity. General responsivity means using approaches that actually work for people — cognitive behavioral methods, motivational interviewing, skills training. Specific responsivity means adapting to the individual. Cultural factors, gender, learning disabilities, trauma history. I once worked with a woman who had severe ADHD and couldn't focus through standard group therapy. We switched to individual sessions with shorter, more frequent meetings. She completed the program. She also stayed out of prison.
Common Pitfalls I Wish Someone Had Told Me
The biggest problem is score inflation. Officers who fill out assessments every day develop shortcuts. They assign high scores without probing deep enough, or they project their impressions onto the form. I caught this happening when I reviewed my own assessments after six months. Six of my high-risk scores looked inflated when I checked against actual outcomes. I had to retrain myself to go slower on the need sections, especially the personal and affective components. Another issue is using the model in isolation. Risk assessment should inform case planning, not replace clinical judgment. I saw too many supervisors treat a high score as automatic justification for maximum security placement. That creates a self-fulfilling prophecy. High restriction limits access to prosocial supports, which increases risk of failure, which confirms the original assessment. The loop feeds itself until someone gets hurt. The model also struggles with low-risk offenders. There is evidence that intensive intervention for people who pose minimal risk can actually increase recidivism. This is called the penalty of intervention, and it is real. I learned to pay close attention when the risk tool scored someone as low risk but the supervision plan still included weekly check-ins and mandatory programming. That extra contact wasn't helping. It was creating dependency and removing autonomy.
What the Research Actually Says
Meta-analyses from the early two-thousands and follow-up studies show that risk assessment combined with structured case management reduces recidivism by roughly eighteen to twenty-two percent compared to casework alone. The responsivity component adds another five to eight percent reduction when properly implemented. That means a well-run program following the full model gets maybe a thirty percent improvement over standard practice. It is significant, but it is not a silver bullet. There is also the issue of prediction accuracy. Risk tools predict reoffending, not individual outcomes. A score of forty-two doesn't mean anything specific about one person. It means that among similar groups, about that percentage reoffend. I stopped explaining individual scores to judges. Instead I talked about base rates and confidence intervals. They understood better, and they made more reasonable decisions.
When to Use Something Else
The Risk Need Responsivity Model For Offender Assessment And Rehabilitation has real limitations. It was designed for adult male offenders. Applying it to women without modification leads to inaccurate assessments. The criminogenic needs identified for men don't map cleanly onto women's offending pathways. Substance abuse, trauma, and relationship problems matter more for female offenders, and the standard tools underweight those factors. Younger offenders present another problem. Adolescent risk assessment requires different instruments. The PCL:YV or the YLS/CMI work better for that population. I used both, depending on the age group. Mixing them up produces garbage results. People with intellectual disabilities or significant mental illness also require adaptation. Standard assumptions about insight and motivation break down. I worked with a man who scored in the low-risk range but couldn't understand why his actions had consequences. His risk level was real, but the tool missed the cognitive barrier driving his behavior. We ended up using a specialized assessment alongside the standard instrument and got a much clearer picture.
Practical Steps That Actually Help
Start by training assessors properly. One lunch-and-learn session doesn't cut it. I found that structured calibration sessions where officers compare scores on the same cases reduced inter-rater reliability problems significantly. After about twelve hours of calibration work, our disagreement rate dropped from about thirty percent to under ten percent. Use the risk level to inform intensity, not just type of intervention. High risk gets more hours and closer monitoring. Low risk gets minimal contact and a focus on maintaining prosocial connections. Don't waste resources on people who don't need it, and don't abandon people who do. Document the reasoning behind your scores. When I wrote out why I assigned a particular rating, I caught my own biases more easily. I noticed patterns where I was giving higher need scores to people I already disliked or found difficult. That kind of awareness only comes from explicit reflection.
Regularly review outcomes against predictions. Track how many high-risk classifications actually result in new offenses within two years. If your high-risk group has a sixty percent reoffense rate instead of the expected eighty, something is wrong with your process. I ran these reviews quarterly and adjusted my scoring criteria based on the data. It kept me honest.

The Bottom Line
The Risk Need Responsivity Model For Offender Assessment And Rehabilitation is useful when you treat it as a thinking tool rather than a prediction machine. It improves decision-making if you combine it with clinical judgment, adapt it to the population, and regularly check whether your predictions match reality. It fails when you treat scores as facts or ignore the responsivity component entirely. I stopped believing that any single instrument could capture the complexity of an offender's situation. The model helps organize your thinking and flag important factors, but it never replaces careful observation and genuine engagement with the person being assessed. That part cannot be automated or standardized away.
