What Actually Happens During Decompression
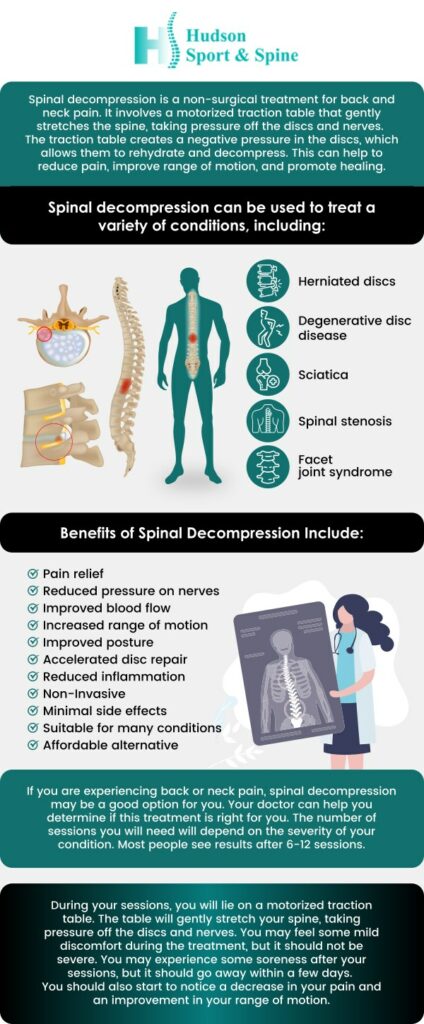
Spinal decompression therapy uses a motorized table to apply controlled traction forces to the spine. The goal is to create negative intradiscal pressure and reduce pressure on nerve roots. The machine cycles through pull-and-relax phases, typically holding tension for 10 to 30 seconds at a time, repeated over a 30-minute session. Commercial devices like the DTS or Centriplex claim to target specific spinal levels through software algorithms, but the biomechanics underneath are fairly straightforward: you're pulling the spine apart just enough to reduce mechanical load on the discs and surrounding structures. Force settings are usually calculated as a percentage of body weight, with lumbar protocols running around 25 to 45 percent and cervical protocols significantly lower, often 10 to 20 pounds. The idea is that once you overcome the gravitational and muscular resistance, you can achieve unloading without causing reflexive muscle guarding. That last part is where things get complicated, as I found out working in a clinic setting.
Risks Of Spinal Decompression Therapy
The serious complications are relatively rare but they exist. Here is what can go wrong, ranked roughly by likelihood: Nerve root irritation or worsening radiculopathy. This is the most common issue I see. If the traction force is miscalculated or applied at the wrong angle, you can actually increase pressure on an already inflamed nerve. A patient coming in with a L5 radiculopathy from a foraminal stenosis might experience increased shooting pain down the leg after a session if the facet joints are being compressed rather than the disc being unloaded. This happens more often with cervical decompression than lumbar, mostly because the cervical canal is tighter and the anatomy is more variable. Muscle soreness and spasms. Most patients will experience some degree of post-treatment soreness, similar to what you'd feel after a deep tissue massage or an intense stretching session. This usually resolves within 24 to 48 hours. However, I've seen patients with pre-existing myofascial trigger points develop significant flare-ups that lingered for a week. The counterforce straps across the hips and pelvis can also cause bruising or skin irritation, especially in elderly patients with thinner skin.
Disc herniation progression. While decompression is supposed to help bulging discs retract, there are case reports of herniations actually worsening during treatment. This typically occurs when the traction force exceeds what the surrounding ligamentous structures can tolerate, causing a nucleus pulposus to push further against a weakened annulus fibrosus. The risk is higher in patients with large sequestered fragments that are already free-floating in the spinal canal. Ligamentous laxity and joint instability. Repeated decompression sessions without addressing the underlying stabilization deficits can lead to progressive ligament stretching. I worked with a patient who came in for what was marketed as a 12-session course but ended up needing 24 because the initial protocols weren't holding their condition. By session 18, she was developing noticeable segmental hypermobility at L4-L5 that wasn't present at her first visit. She had to transition to a stabilization-focused program instead of continuing decompression. Contraindicated conditions that can become emergencies. This is where proper screening matters. Decompression should never be performed on patients with abdominal aortic aneurysms, spinal fractures, malignancies, advanced osteoporosis, spinal infections, or progressive neurological deficits like cauda equina syndrome. I saw a case where a patient with an undiagnosed L1 compression fracture from undiagnosed osteoporosis was placed on a lumbar decompression table. Within two weeks of treatment, she developed acute back pain and imaging revealed the fracture had progressed from a stable anterior wedge to a complete burst fracture. That patient required surgical fixation. It could have been prevented with a simple standing X-ray before the first session.
Get the Full Details

Pacemaker and metal implant considerations. Most modern decompression devices don't use electrical stimulation, so pacemakers aren't a direct concern. However, if the device includes any TENS or electrotherapy components, those can interfere with certain cardiac devices. Spinal hardware like rods, screws, or cages doesn't necessarily contraindicate decompression, but it changes how forces distribute across the spine, and protocols need to be modified accordingly. I had a patient with a prior TLIF at L4-L5 who reacted poorly to standard decompression settings—the instrumented level didn't move, so the forces transferred to the adjacent segments, causing new-onset pain at L3-L4 that took three weeks to settle.
Who Should Not Try This
Beyond the hard contraindications, there are population groups where the risk-to-benefit ratio tilts against treatment. Pregnant women should avoid lumbar decompression after the first trimester due to the positioning requirements and the unknown effects of traction forces on uterine blood flow. Elderly patients with sarcopenia and frail musculature may not be able to maintain the relaxed state needed for the therapy to work properly, making the sessions less effective and potentially more irritating. Pediatric patients are rarely appropriate candidates simply because discogenic back pain is uncommon in children under 16, and when it does occur, the underlying etiology is usually different and requires a different approach. I had a 14-year-old referred for what was presumed to be a disc bulge, but the real issue was spondylolysis from a stress fracture. Decompression made the pain significantly worse because it was loading the already compromised pars interarticularis.
A Practical Problem I Encountered
One thing that never gets discussed in the marketing materials is patient positioning variability. The whole premise of decompression depends on the force vector being directed along the long axis of the spine at the target level. If the patient is rotated even 5 to 10 degrees on the table, a significant portion of the traction force is lost to lateral shear rather than axial separation. In practice, I've measured force delivery efficiency dropping from the advertised 85 to 90 percent down to 55 to 65 percent when patient positioning is suboptimal. This means a session that should be delivering therapeutic decompression is instead just pulling on soft tissue and irritating the paraspinal muscles. The workaround I developed was straightforward: I started using a laser level and measuring tapes to mark consistent reference points on the table and patient's anatomy before each session. It added about 90 seconds to setup time but made a dramatic difference in outcome consistency. Patients who previously had variable responses started showing steady improvement across sessions.

Cost and Accessibility
Most clinics charge between $60 and $150 per session, with typical protocols calling for 12 to 20 sessions over 4 to 8 weeks. Insurance coverage is inconsistent and often requires pre-authorization with documented failure of conservative care. Some plans cover it under mechanical traction codes, while others classify it as experimental. Out-of-pocket costs for a full course can easily reach $1,500 to $3,000, and there is no guarantee of success. Home units exist but come with their own set of problems. They're significantly less powerful than clinic machines, the force calibration is often questionable, and without professional supervision, patients tend to either underdose (using too little force for any effect) or overdose (pushing too hard and causing irritation). I generally don't recommend home units unless a patient has excellent clinician oversight and proper screening.
Bottom Line
Spinal decompression therapy can be appropriate for select patients with discogenic pain, particularly acute or subacute lumbar radiculopathy without neurological deficits. It is not a cure-all, it does not work for everyone, and the risks are real even if serious complications remain uncommon. Proper patient selection, adequate screening imaging, correct force settings, and attention to positioning are non-negotiable. If a clinic is pushing a full course of decompression without a thorough examination and imaging review, that is a red flag worth walking away from. For many patients with chronic mechanical back pain, a structured rehabilitation program focusing on core stabilization and movement retraining will produce better long-term outcomes at lower cost and with fewer complications.



