
Using the Revised Pain Assessment Tool in Clinical Practice
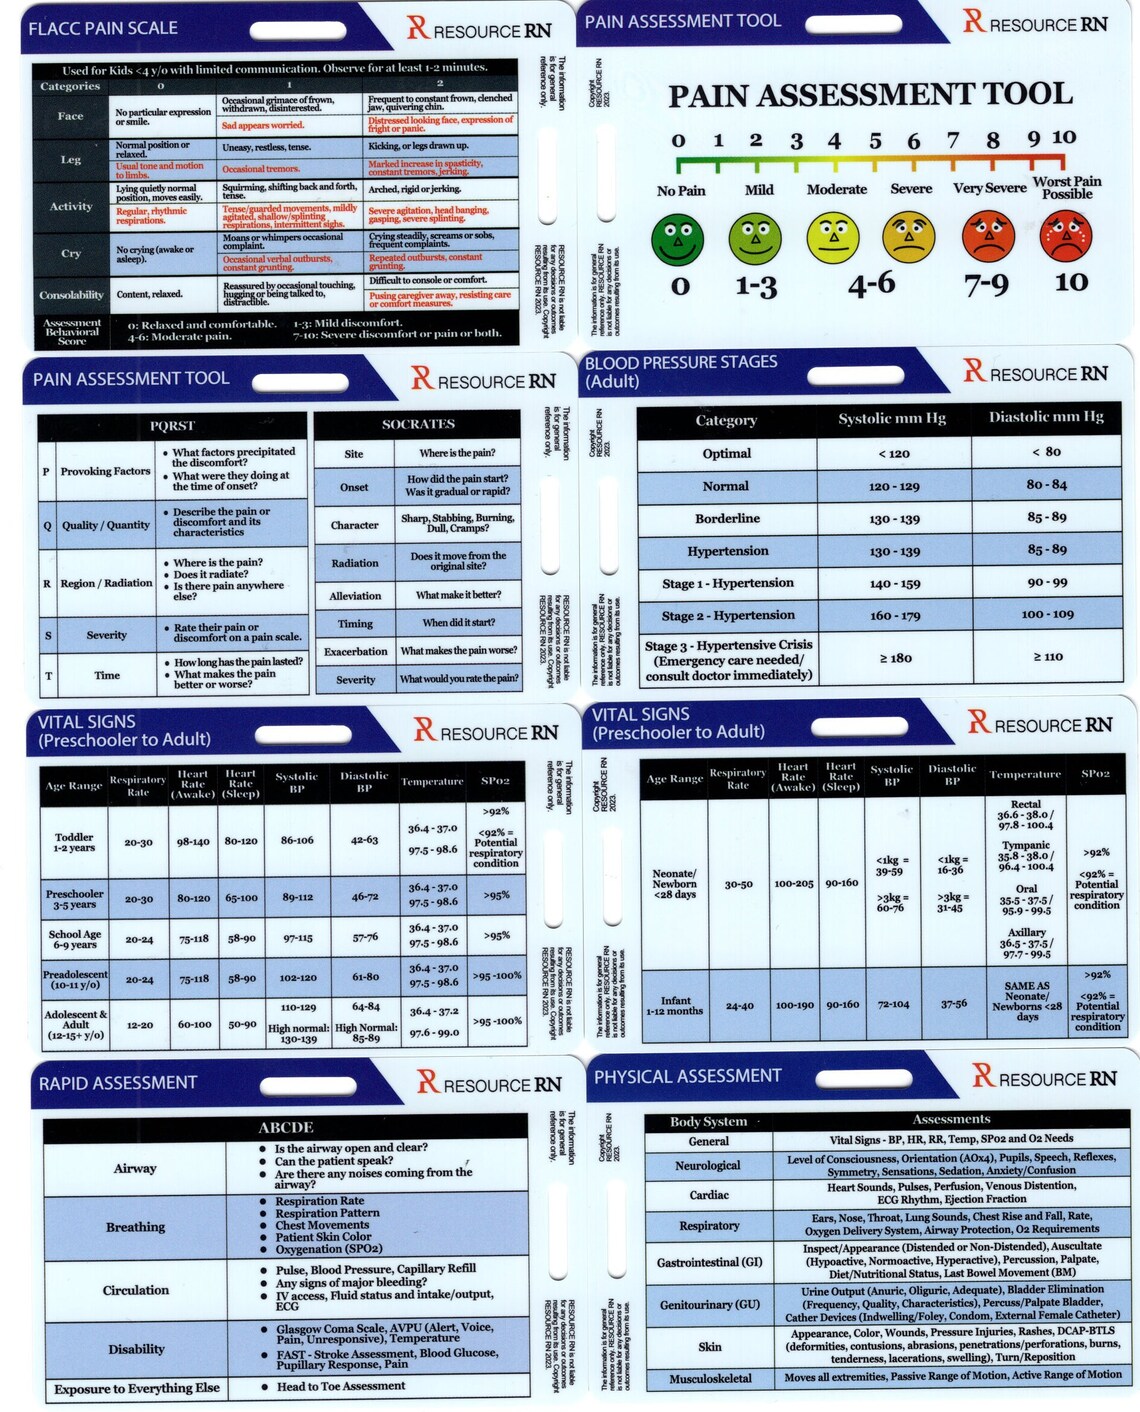
The RN Pain Assessment 2.0 is the updated framework most hospitals have rolled out to standardize how nurses evaluate patient discomfort. It replaced the older single-scale approach with a multi-dimensional tool that forces you to look at more than just a number on a scale. When I first started using it, I thought it was extra paperwork. It is not. It is genuinely better for catching things you would otherwise miss. The tool breaks pain down into several categories: intensity, location, quality, timing, and functional impact. Each category has specific prompts and rating options built in. You do not just ask "how bad is the pain." You ask where it is, what it feels like, when it started, what makes it better or worse, and how it is affecting the patient's ability to move, breathe, or sleep. That last part — functional impact — is where the old system fell apart for me repeatedly. I had a post-surgical patient who rated his pain a 2 out of 10. He said he was fine. But the functional section of the assessment revealed he had not taken a single deep breath since surgery and was sitting on the edge of the bed rather than lying back. The number was misleading. The full assessment caught what the number missed. He had significant atelectasis developing. We caught it early because the tool made you look beyond the score.
How to Work Through the Assessment Step by Step
Start with the intensity question. Ask the patient to rate their current pain using the standard 0 to 10 scale, where 0 is no pain and 10 is the worst pain imaginable. Record it. Then move through the remaining sections without skipping ahead. For location, have the patient point to or describe where the pain is. One area or multiple. Is it radiating? Note that. For quality, give them options like sharp, dull, burning, aching, throbbing, or cramping. Patients often struggle here, so offer the choices rather than asking an open-ended question. Timing covers onset, duration, and frequency. Is it constant or does it come and go? What were you doing when it started? The functional impact section is the most important and the most commonly rushed. Ask about sleep, mobility, breathing, appetite, and mood. A patient might have a moderate pain score but be completely unable to walk to the bathroom or take a full breath. That changes the clinical priority dramatically.
Finally, document any interventions already tried and their effect. This helps you track whether the current plan is working or needs adjustment.
Get the Full Details
Where the Tool Falls Short
The biggest issue I have found is that the standardized options sometimes do not fit certain patient populations. Non-verbal patients, those with advanced dementia, or people with cognitive impairments require you to rely entirely on behavioral indicators and caregiver input. The form does not have a clean pathway for that. I ended up creating a shorthand notation next to the functional section — noting facial grimacing, guarding behavior, restlessness, or verbalizations — and attaching it to the assessment. It is not ideal, but it keeps you from filling in blanks that do not apply. Another problem is time pressure. In a busy unit, working through every section thoroughly can take four to six minutes per patient. If you are charting ten pain assessments in a shift, that is forty to sixty minutes of focused documentation time on top of everything else. The workaround is to use the assessment actively during your physical exam rather than going back to the computer afterward. You gather the data as you interact with the patient and fill it in in one pass. It cuts the documentation time roughly in half.
Common Mistakes I See Every Day
Nurses treat the intensity number as the only thing that matters. They document a score and move on. The rest of the assessment becomes a formality. This defeats the entire purpose of the tool. A pain score of 7 means nothing without context about function and quality. Another mistake is asking leading questions. "Your pain is better today, right?" puts the patient on a path to give you the answer they think you want. Just ask neutral questions and let them answer. The third common error is failing to reassess. Documenting an intervention without a follow-up evaluation makes the assessment incomplete. You should set a reasonable timeframe for reassessment based on the intervention given — thirty minutes for IV medication, two hours for oral medication — and actually go back to re-evaluate.
When to Supplement with Other Tools
Rn Pain Assessment 2 0 works well for most adult patients in acute care settings. It is less useful for pediatric populations, where tools like the FLACC scale or Wong-Baker FACES scale remain the standard. For patients with chronic pain, the intensity scale alone is inadequate and you may need to incorporate a pain diary or a quality-of-life measure alongside the formal assessment. In palliative care settings, the focus shifts from functional improvement to comfort, which changes how you interpret the results entirely. The tool itself does not replace clinical judgment. It structures it. Use it as a checklist that ensures you are not overlooking critical information, but trust your instincts when the assessment points somewhere unexpected. That post-surgical patient I mentioned would have been missed if I had only looked at the pain score. The assessment gave me the framework to dig deeper, which is exactly what it is designed to do. Download versions of the tool are typically available through your hospital's intranet or policy manual. If your facility has not adopted it yet, request a copy from your nurse educator or charge nurse. Most units have both printed pocket cards and electronic versions in the charting system. Neither is significantly better. Pick the one you will actually use consistently, because the tool only helps if someone fills it out thoroughly and acts on what it reveals.



