The Preperitoneal Space Is Where It All Happens
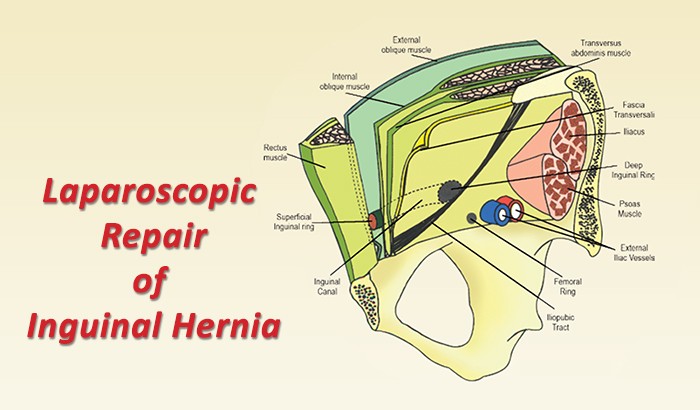
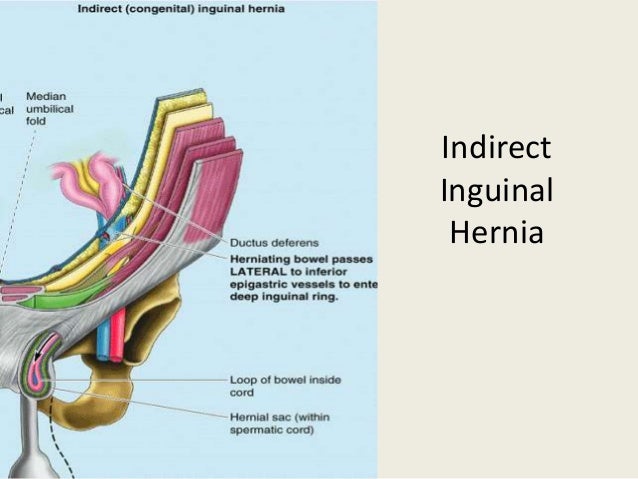
The robotic approach to inguinal hernia repair lives and dies on how well you understand the preperitoneal anatomy. Most people learn this from diagrams, which is fine until you're inside the space and everything looks like a confusing mess of fat and fascia. I've been doing this for years across both TAPP and TEP platforms, and the core truth is simple: if you don't know where Cooper's ligament is, you're flying blind. Let me walk through what actually matters in the robot. The key landmarks you need to identify first are the internal inguinal ring, the vas deferens, the gonadal vessels, and the epigastric vessels. Everything else branches from there. Your dissection in the preperitoneal plane should stay deep to the peritoneum but superficial to the extraperitoneal fat and the psoas muscle underneath. Get that wrong and you either enter the peritoneal cavity when you didn't mean to or you dig into the muscle and create bleeding that obscures your view for ten minutes.
Robotic Inguinal Hernia Repair Anatomy
Inside the preperitoneal space, the critical triangles and borders define your safe zone. Hesselbach's triangle sits medially, bounded by the rectus abdominis anteriorly, the inferior epigastric vessels laterally, and Cooper's ligament inferiorly. Direct hernias bulge through here. The triangle of pain sits laterally—it contains the lateral femoral cutaneous nerve and the femoral branch of the genitofemoral nerve. The triangle of doom is more medial and deeper, and it houses the external iliac artery and vein along with the deep circumflex iliac vein. Your mesh needs to cover the myopectineal orifice, which means it has to extend from the vas deferens and gonadal vessels medially to the iliac crest laterally, and from the pubic symphysis superiorly down to Cooper's ligament inferiorly. The mesh overlap requirements are standard: at least 3 to 4 centimeters of normal tissue beyond the defect on every side. This isn't optional. A mesh that's too small leads to recurrence, and I've seen it happen multiple times with hernias under two centimeters where someone got lazy with placement. The robotic view makes it easy to be sloppy because everything looks bigger and clearer on the screen. That's a trap. One thing people miss is the relationship between the iliopubic tract and the inferior margin of the internal ring. The iliopubic tract runs horizontally along the pelvic brim and it's your lateral landmark for dissection. If you go lateral past it, you're entering the extraperitoneal space near the iliac vessels unnecessarily. If you go medial past it without identifying Cooper's ligament, you risk injury to the bladder or the medial umbilical ligament. I learned this the hard way on a case where the patient had a large sliding hernia with the colon forming part of the sac wall. The anatomy was distorted, and I initially mistook the colon for preperitoneal fat during my initial dissection. I backed off, switched to lower energy settings on the cautery, and used suction irrigation to gently peel the peritoneal layer away from the underlying structures. It took longer but it prevented a bowel injury that would have complicated things significantly.
The vas deferens and the testicular vessels are the structures you need to identify and preserve. They cross over the external iliac vessels and run toward the internal ring. In a standard case, you trace them from the internal ring back to their origin. In revision cases or obese patients, these structures can be buried in fibrous tissue and fat, making identification much harder. When that happens, I use the robotic needle driver to gently probe and separate planes rather than cutting blindly. Energy use should be minimal here. Bipolar cautery on low settings works better than hook electrocautery for this region because you get far less lateral thermal spread. Femoral hernias are another anatomical consideration that matters more than people realize. They occur below and lateral to Cooper's ligament through the femoral canal. If you only address the direct and indirect spaces and ignore the femoral ring, you're leaving a gap. A properly placed mesh in the preperitoneal space should cover the femoral ring, but you need to deliberately sweep your dissection inferiorly and laterally to ensure the mesh overlaps that area. In some cases, especially with large femoral defects, I place additional tacks or glue in the femoral region specifically because the mesh alone doesn't always conform well to that concave space. The epigastric vessels are your anterior boundary and they're also a source of bleeding if you nick them. They run on the posterior surface of the rectus abdominis muscle. When you're dissecting the preperitoneal space from a TAPP approach, you enter through the peritoneum and then reflect it downward. The epigastric vessels should become visible as you move laterally. If you're doing TEP, you're already in the preperitoneal space and these vessels are anterior to your dissection plane. Either way, knowing where they are prevents bleeding that clouds the camera view and slows everything down.
Get the Full Details
A counter-intuitive point about mesh fixation: most modern guidelines and studies suggest that for primary hernias, tacking may not be necessary if the mesh is placed correctly with adequate overlap. The preperitoneal space has natural adhesions that form over weeks, and the mesh typically stays in place on its own. Over-tacking, especially near Cooper's ligament or the iliopubic tract, causes chronic pain that patients complain about months later. I tack sparingly now—maybe one or two points near the pubic bone if the mesh seems mobile, and I avoid the triangle of pain entirely. For recurrent hernias or larger defects, I'm more likely to use a few additional fixation points, but even then, I prefer fibrin glue over tacks when possible. The robotic system gives you wristed instruments and a magnified 3D view, which helps with delicate dissection around the spermatic cord structures. But the lack of haptic feedback means you have to rely on visual cues—tissue tension, color changes, subtle movement—to gauge how much force you're applying. I've seen colleagues tear the peritoneum or nick the bladder because they were pulling too hard without realizing it. Slow, deliberate movements matter more on the robot than they do laparoscopically. Port placement differs between TAPP and TEP but the anatomical targets remain the same. For TAPP, three or four ports are typically used in a standard configuration with the camera port at or above the umbilicus. For TEP, you work entirely in the preperitoneal space without entering the peritoneal cavity, which means the learning curve is steeper and the working space is more limited. Both approaches are valid, and the anatomical knowledge required is essentially identical. The main difference is how you get to the preperitoneal space.
If you're just starting out with this, I'd recommend mastering the anatomy on cadaver lab or simulation first before taking patients. The difference between a good outcome and a complication often comes down to whether you could identify those key structures before you started cutting. A poorly visualized Cooper's ligament or an unrecognized femoral hernia can turn a straightforward case into an emergency conversion fairly quickly.