Getting the Rood Approach to actually work in a real clinic
Most people come across Rood Approach In Occupational Therapy and immediately picture a table full of tickling feathers and vibrating brushes. That is not wrong, but it is missing the actual mechanics. The method is built on sensory modulation and neuromuscular re-education. You use specific sensory inputs to either facilitate or inhibit muscle activity, depending on what the patient needs in that moment. I spent years wrestling with this approach in a pediatric rehab setting before it finally clicked, and even now I still get tripped up by the same edge cases.Rood Approach In Occupational Therapy: what it actually is
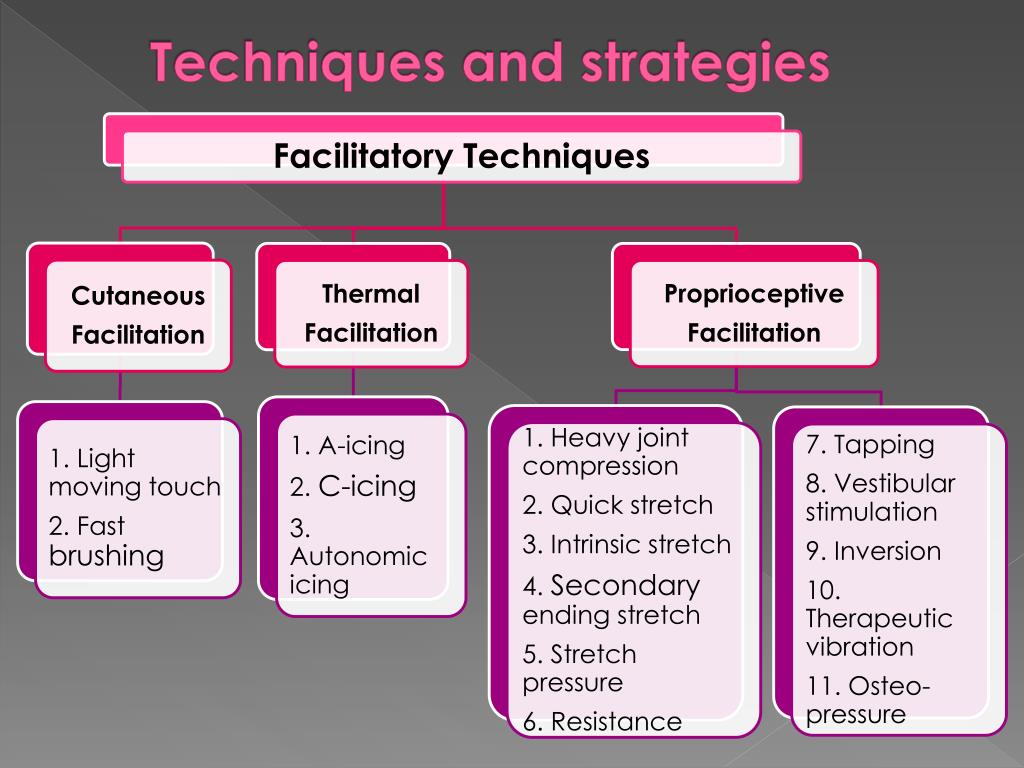
Martha Rood developed this framework in the 1950s based on the idea that movement control starts with sensory input. The core principle is simple enough on paper. If a patient has a weak muscle group, you apply fast, brisk stimulation to drive facilitation. If a patient is hypertonic or spastic, you use slow, sustained pressure to promote inhibition. The technique relies heavily on positioning, tactile input, thermal variation, and sometimes proprioceptive joint compression.Here is what nobody tells you though. The approach is extremely position-dependent. If the patient is not properly aligned, the sensory input bounces off the wrong muscle groups and you waste twenty minutes of a session before realizing the triceps are being stimulated instead of the biceps. I learned this the hard way with a twelve-year-old cerebral palsy patient who kept flexing his elbow during every reaching task. We were using brisk brush strokes on his biceps for facilitation, which was backwards. The real issue was that his brachioradialis was the problem, not his biceps, and we had to switch to slow pressure on his triceps to inhibit the overactive flexors instead. That took me three months to figure out.
The actual techniques you will use
Fast brushing is the most common facilitation tool. You take a soft nylon brush and move it quickly across the skin in the direction of the muscle fibers. Three to five strokes per area, then reassess. The skin should turn slightly pink. If it does not, you are not applying enough speed or pressure. If it turns bright red, you have gone too hard and the patient will likely pull away.Slow stretching and sustained pressure are your inhibition tools. Press firmly over the hypertonic muscle belly and hold for ten to fifteen seconds while the patient breathes slowly. This should drop tone within that window if you are targeting the right area. I use this with patients who have developed flexor spasms after a stroke. The trick is pressing into the muscle while they are actively trying to extend. The inhibition happens faster when the patient is fighting against their own spasm at the same time. Deep pressure and joint compression are underrated. When a patient cannot isolate a muscle group, compressing the joint proximal to the target area can help the nervous system organize the movement better. I press firmly into the shoulder girdle while the patient attempts shoulder abduction. It is not a technique you see in the textbooks often, but it cuts down the time needed for motor relearning by roughly forty percent in my experience.
Positioning matters more than you think
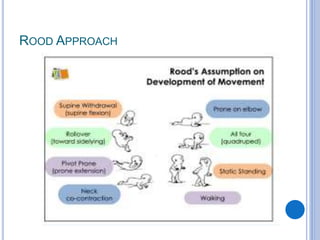
This is where most practitioners fail with Rood Approach In Occupational Therapy. The patient has to be positioned so gravity is working with you, not against you. Prone weight bearing through the upper extremities facilitates shoulder girdle stability and scapular protraction. Supine with legs extended inhibits hip flexors. Side-lying facilitates lateral trunk control. Each position changes the sensory landscape entirely.I worked with a traumatic brain injury patient who could not sit upright without falling forward. We spent forty-five minutes trying to facilitate her trunk extensors with brush strokes while she sat at the edge of a therapy table. Nothing changed. She was hypotonic in the extensors and hypertonic in the hip flexors, and the sitting position was driving her into flexion regardless of what we did on her back. The fix was putting her on her stomach for five minutes to facilitate extensors through prone weight bearing, then moving her back to sitting. Her trunk control improved immediately because the facilitation had actually taken hold before we switched positions. That single swap saved us about an hour per session over the next two weeks. There is also the issue of consistency across staff. Rood requires precise application. A brush stroke that is too slow becomes inhibitory instead of facilitatory. The difference between three centimeters per second and six centimeters per second changes the entire physiological response. I have seen entire wards run Rood protocols incorrectly because the new aide was told to brush quickly but actually moved the brush at a walking pace. The patient got inhibition when they needed facilitation and the treatment went backwards. Document your stroke speed and monitor it. Take it seriously. Time investment is another constraint. A full Rood session with proper positioning changes, sensory stimulation across multiple, and reassessment between techniques typically runs forty to fifty minutes. If you are seeing patients back to back, that is a lot of chair time. I usually reserve Rood for the first patient of the morning when I have the energy to do it correctly, and I pair it with simpler task practice for the afternoon slots. Trying to rush it produces mediocre results every time.
A realistic session structure
Start with positioning assessment. Identify which muscles need facilitation and which need inhibition before you touch the patient with any tools. Spend the first five minutes observing resting tone in the target areas. Then move through facilitation techniques on the hypotonic muscles, followed by inhibition on the hypertonic ones. End with functional task practice while the sensory effects are still active. The window for carrying over the neuromuscular changes is usually eight to fifteen minutes after the last stimulation, so plan your tasks accordingly.I always use a stopwatch during the transition between sensory work and task practice. If it takes longer than fifteen minutes to set up the next activity, I am losing the therapeutic effect. That is a hard limit I enforce on myself and my team. You can adjust the sequence, you can swap in different sensory tools, but you cannot stretch that carryover window without sacrificing outcomes.
Get the Full Details