Why Most RCA Teams Miss the Real Problem
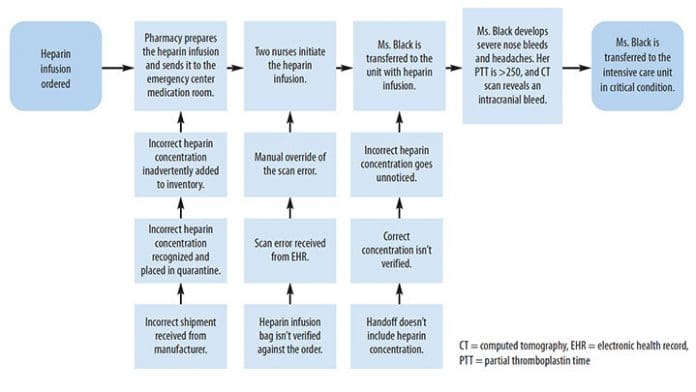
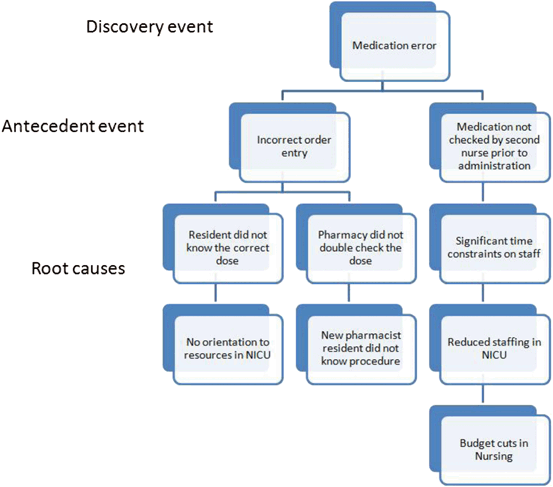
I spent eight years on a hospital quality improvement committee, and I watched some very smart people waste hours on RCA sessions that went nowhere. The method itself is straightforward, but the execution is where things fall apart. Root Cause Analysis In Nursing is supposed to be a systematic way of figuring out what actually caused an adverse event, not just confirming what everyone already suspected. Here is how it works when you do it right. You start with the event timeline. Not the ideal timeline. The actual one. Write down every action, every communication, every delay. I once worked a case where a patient received double the prescribed dose of heparin. The chart said the second dose was "verified" by the bedside nurse. But when I pulled the smart pump logs and the MAR timestamps, the second dose had actually been entered by the charge nurse at 14:03, printed onto a new strip at 14:05, and administered at 14:07. The bedside nurse had documented verification because the policy required it, not because she actually double-checked that specific dose. That gap between policy documentation and actual behavior is the kind of thing most RCAs gloss over. The standard approach involves forming a multidisciplinary team. This means clinicians, pharmacists, and often risk management personnel working together. You then map the sequence of events using a timeline or flowchart. After that, you ask "why" repeatedly until you hit something systemic rather than individual. The common mistake here is stopping at the first human error you find. Blaming the nurse who missed a calculation does nothing to prevent the next similar event. The real root cause is usually a process flaw, a design issue, or a communication breakdown.
Root Cause Analysis In Nursing: The Practical Steps
First, confirm the event actually happened and gather all relevant documentation. Medication administration records, nursing notes, pharmacy orders, pulse ox readings, incident reports. Everything. Do not skip the incident report even though they are often incomplete and poorly written. They still contain useful chronological data points. Second, assemble your team. I recommend no more than six people. Anything larger and the discussions fragment. You need someone who knows the clinical details, someone who understands the system workflows, and someone who can ask uncomfortable questions without being defensive about departmental processes. Third, build the timeline. This is the most important step and the one most teams rush through. I typically spend two hours on this alone for any significant event. You are looking for the exact moment decisions were made, when information was available or unavailable, and where the chain of reasoning broke. A medication error that looks like a simple dosage mistake might reveal itself as a communication failure if the timeline shows the provider changed the order but the nurse never received notification of the change.
Fourth, identify contributing factors. These are the conditions that allowed the error to occur. Staffing ratios during that shift, similar product packaging from different manufacturers, interrupted workflows, unclear policies. Contributing factors are not excuses. They are the actual environment in which the error happened. Fifth, determine the root causes. A root cause is a condition that, if corrected, would prevent the event from recurring. Not reduce the likelihood. Prevent it. This is a higher bar than most teams hold themselves to, and it is why so many RCA reports feel unsatisfying when you read them. Sixth, develop and implement action items. Each root cause should have at least one corrective action. The action needs to be specific, measurable, and assigned to a person with authority to make the change. "Increase awareness" is not an action item. It is a wish.
Get the Full Details

The tool I use most often is the fishbone diagram, also called the Ishikawa diagram. You draw the problem statement at the head of the fish and branch out categories like people, processes, equipment, environment, and materials. It forces the team to look beyond individual performance. Another useful tool is the five whys technique. You ask why the error occurred, then why that cause occurred, and keep going until you reach something you can actually change. The five whys is deceptively simple. It is also the one most teams abuse by accepting superficial answers. One counter-intuitive insight that took me years to learn: the most dangerous events are often the ones where no one got hurt. A near miss with a high-alert medication like insulin or potassium reveals more about system vulnerabilities than a fully realized adverse event. When someone actually gets harmed, the investigation shifts toward legal and liability concerns. The focus moves from understanding the system to assigning blame, even when the team claims otherwise. Near misses stay in the quality domain where they belong. Another thing beginners consistently miss: timing matters more than you might expect. An event that occurs at 3 AM on a weekend with two nurses covering a full unit tells you something fundamentally different than the same event at 10 AM on a Tuesday with full staffing. Documentation of acuity levels and patient-to-nurse ratios during the event is essential context, not optional detail. Without it, your analysis is incomplete.
The biggest limitation of Root Cause Analysis In Nursing is that it is backward-looking by definition. You are analyzing something that already happened. It cannot predict what will go wrong next. For that, you need prospective risk assessment tools like FMEA, Failure Mode and Effects Analysis. I recommend running FMEA on high-risk processes before errors occur, and using RCA only after an event has taken place. Using RCA as your only risk management tool is like only fixing your roof after it starts leaking inside. Another practical limitation: RCA findings often die in a binder somewhere. If your organization does not track implementation of corrective actions and verify their effectiveness, the entire process is theater. I have seen RCAs produced for events that were three years old by the time the final report was distributed. Corrective actions listed in those reports had either not been implemented or had been abandoned within months of the original recommendation. When an RCA hits a wall, and it will, the workaround is usually to bring in someone from outside the department who has no allegiance to existing relationships. A clinical nurse educator from a different unit, a pharmacist from another service line, sometimes even a patient safety specialist from a neighboring hospital system. Fresh eyes cut through the institutional blindness faster than any analytical framework can.
The documentation itself should be factual and concise. I aim for three pages maximum for the narrative summary. Any detail that does not directly support a finding or recommendation belongs in an appendix. Long reports get skimmed. Skimmed reports generate no action. If you are starting this process for the first time in your organization, begin with a single event. Not the worst event. A moderate one with clear documentation. Learn the process, identify the friction points, then scale up. Do not attempt a complex RCA on a sentinel event as your first experience. That is a recipe for producing a report that satisfies the regulatory requirement but changes nothing on the floor.