Why Most RCA Methods Fail Before They Start
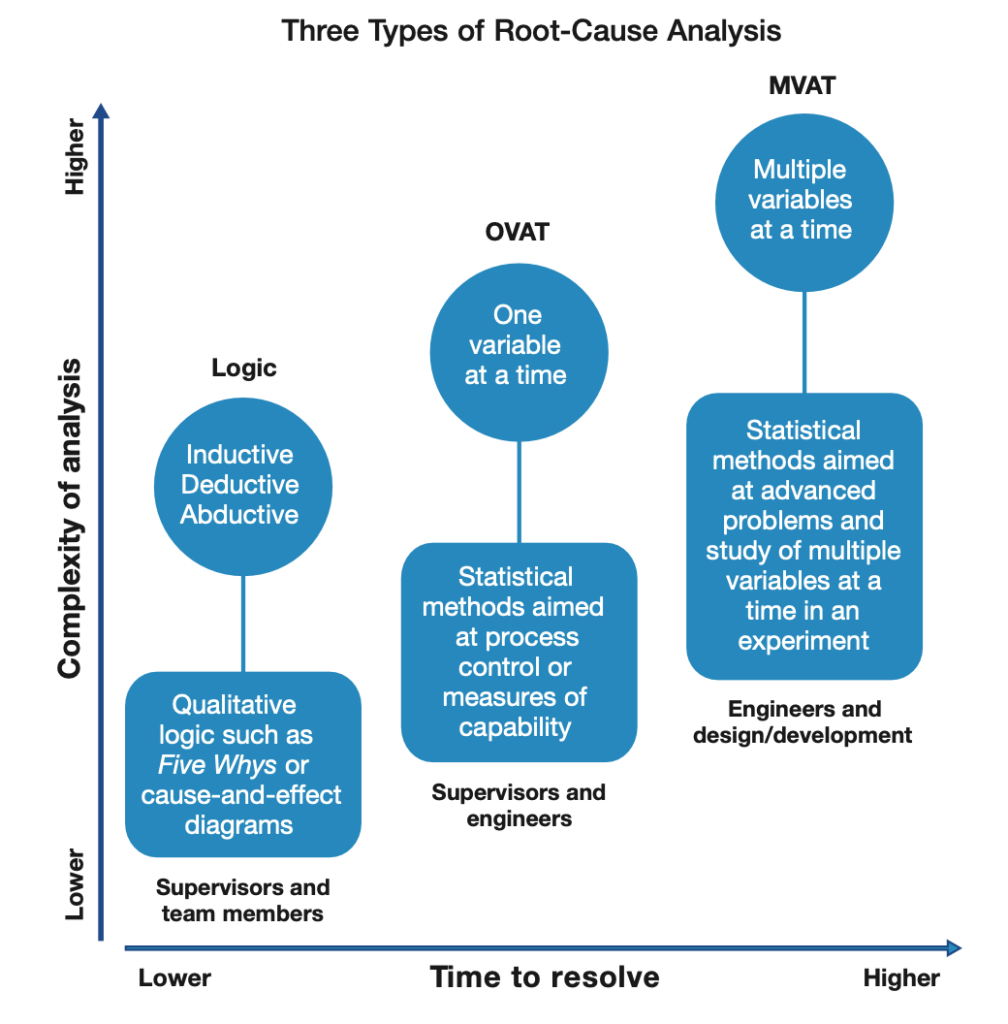
I spent three years watching engineers pick the wrong root cause analysis methods and then wonder why their fixes never stuck. The problem isn't that these techniques are complicated. It's that people apply them blindly without understanding what each type is actually good at, and that's where everything goes sideways. Root Cause Analysis Types cover a lot of ground, but they fall into roughly five categories that matter in practice. The rest is academic padding.
When to Use Each Root Cause Analysis Types Approach
Start with the Failure Mode and Effects Analysis, commonly called FMEA, before you do anything else if you're dealing with hardware or manufacturing. It forces you to map every possible way something can break and rate each failure mode by severity, occurrence, and detection. That gives you a risk priority number that actually helps you decide what to investigate first instead of guessing. I once had a team waste two weeks chasing a recurring pump seal failure on a distillation unit. We should have run an FMEA first and spotted that the seals were being underspecified for the vibration profile they were seeing. The root cause wasn't installation error or seal quality. It was a mismatch between the pump's actual operating envelope and the seal's design limits. FMEA would have flagged that in a single afternoon. Then there is the Fault Tree Analysis, or FTA, which works best when you have a known top event and need to trace backward through logical combinations of failures. It uses Boolean logic gates to show how multiple smaller failures can combine to cause a bigger one. This is standard in aerospace and nuclear industries. The downside is that it gets unwieldy fast. Once your fault tree has more than about fifty basic events, reading it becomes nearly impossible and you start missing important paths. I've seen teams hit that wall on reactor safety reviews and basically give up halfway through. If you are building a fault tree and it starts looking like a plate of spaghetti, stop and simplify. Split it into sub-trees or switch to a cause-and-effect diagram instead. The Ishikawa diagram, also called a fishbone or cause-and-effect diagram, is the most misunderstood tool in this space. People treat it like a brainstorming template and then dump every possible cause onto it without any filtering or prioritization. That produces a diagram with eighty bones and zero actionable insight. The version that actually works requires you to constrain the categories first. Manufacturing contexts usually stick with the six Ms: method, machine, material, measurement, man, and mother nature. Service industries might swap those for the four Ps: policy, procedure, people, and plant. Once you have your categories locked, you only add causes that you have evidence for, not guesses. I learned that the hard way on a packaging line where we filled a fishbone with twelve possible causes for a filling volume. Half of them were speculation. The one that mattered was a worn metering valve that only caused the under high throughput conditions. We caught it by running targeted tests against the evidence-backed causes instead of testing everything on the board.
For software and complex system problems, the 5 Whys technique gets a bad reputation because most people use it wrong. They ask five questions and land on a human error answer like operator forgot to reset the flag. That is not a root cause. That is a description of a symptom. The real method involves pushing past the obvious answer every time and asking whether the system allowed that mistake to happen. I worked on a deployment pipeline where our staging environment started rejecting requests with connection timeout errors every Thursday. We ran the 5 Whys once and got "the monitoring script consumed too much memory." Fixing the script didn't help because the failures were periodic. We went back and ran it again with a tighter frame: why did the script consume too much memory only on Thursdays. That led us to the backup job that ran Thursday nights and was competing for the same I/O resources. The root cause wasn't the script. It was resource contention that the pipeline's SLA didn't account for. The 5 Whys worked only because we forced it deeper than the first answer. Finally, there is the Change Analysis method, which is useful when a system was working fine and then suddenly stopped. Instead of looking for what broke, you look for what changed. Compare the working state against the failed state and isolate the differences. This works remarkably well for infrastructure outages where someone pushed an update, rotated credentials, or modified a firewall rule. The method is simple but it requires you to have clean baselines. If you do not know what the working state looked like in detail, change analysis becomes guesswork. I handled a case where a database started returning corrupted result sets after a middleware patch. The team assumed the patch damaged the data. Change analysis showed the patch had actually changed the connection pooling behavior, which caused queries to reuse stale connections under load. The data was fine. The behavior was wrong. That distinction mattered because rebuilding the database would have been a week-long disaster.
Get the Full Details

Practical Limits That Nobody Talks About
None of these methods are reliable when you lack data. A fault tree built on assumptions is just a story you tell yourself, and it is often a convincing one. I have seen senior engineers spend days constructing elaborate causal chains that fell apart the moment someone checked the actual logs. Always verify at least one branch of your analysis against hard evidence before investing more time. It usually takes ten minutes to check and can save you hours of wasted investigation. Another thing that goes unmentioned is that some problems do not have a single root cause. Complex systems generate cascading failures where multiple small issues interact in ways that none of these methods capture well. FMEA handles multiple failure modes but struggles with their interactions. Fault trees handle interactions through gates but become unreadable. In those cases, a combination approach works better than any single method. Run a quick change analysis to narrow the scope, then use an Ishikawa diagram to organize the candidates, and finally apply targeted tests to validate. That sequence took me from a four-day investigation on a network latency issue down to two hours when we stopped treating it as a single-cause problem. The biggest mistake I see is treating Root Cause Analysis Types as a menu you pick from rather than a toolkit you combine based on the problem. The method should follow the problem, not the other way around. FMEA for hardware risk, FTA for safety-critical systems, Ishikawa for manufacturing variation, 5 Whys for procedural issues, and change analysis for sudden regressions. When those don't fit cleanly, mix them and validate aggressively.