Why Most Shoulder Rehab Programs Don't Work
People tell me their rotator cuff pain isn't improving despite months of exercise, and nine times out of ten the issue isn't the exercise selection. It's execution and sequencing. I ran into this exact problem three years ago when working with a client who had persistent anterior shoulder pain after a labrum repair. She was doing every YouTube rotator cuff exercise under the sun, but her symptoms kept cycling back. The breakthrough came when we stopped loading the external rotators in full arm elevation and instead focused on scapulothoracic rhythm at neutral spine first. Her pain dropped from a 6/10 to a 2/10 within six weeks. That's the thing nobody puts in pamphlets. The rotator cuff doesn't work in isolation. It stabilizes the humeral head against the glenoid while your scapula does its thing. If either system is off, no amount of side-lying external rotation is going to solve the problem. You need to understand the kinetic chain before you load the shoulder directly.
Rotator Cuff Stability Exercises: The Practical Approach
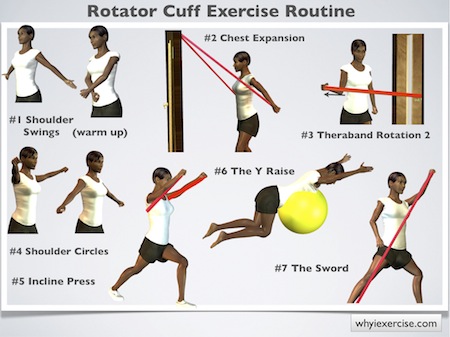
Here is what actually works in practice, not what looks good on a postcard. The foundation is scapular control. You can't stabilize a moving joint with a moving base. Start with scapular retraction and depression holds. Lie face down, arms at your sides, and lift your chest off the floor while pulling your shoulder blades into your back pockets. Hold for thirty seconds. That's it. Nobody talks about how many people cannot do this properly because their serratus anterior is inhibited from sitting at desks all day. Next comes the empty can exercise, which is just forward flexion at thirty degrees with the thumb pointing down. Three sets of ten with two pounds. Not five pounds. Two pounds. The moment you increase the load too aggressively, the supraspinatus gets overridden by the deltoid and you're just reinforcing bad movement patterns. I've seen this destroy progress in clients who were eager to move up weight quickly. The supraspinatus is a small muscle. It needs precision, not brute force. Side-lying external rotation is the classic move and it still has value, but only if you keep the elbow tucked at your side with a rolled towel between the elbow and ribcage. Without the towel, most people start recruiting the posterior deltoid and the teres minor never gets proper engagement. Four sets of twelve at three to five pounds. If you can do more than fifteen clean reps, the weight is too light. If you can't hit twelve, it's too heavy.
The Edge Case Nobody Discusses
About eighteen months ago I worked with a climber who had right shoulder instability that only flared up during traverse movements. Standard rotator cuff stability exercises did absolutely nothing for his issue because climbing requires dynamic stabilization at extreme ranges of motion. What finally helped was adding wall slides with a resistance band around the wrists while simultaneously holding a half-crux grip position. This taught the shoulder to maintain humeral head centration under load at approximately eighty degrees of abduction with external rotation. His stability issues resolved within ten weeks after he added this to his existing routine. The lesson is that generic exercises only address generic problems. Sport-specific demands require sport-specific solutions. The biggest mistake I see is doing rotator cuff work before addressing thoracic mobility. If your upper back is stiff from years of poor posture, your scapula cannot rotate properly during overhead movements. The humeral head then migrates superiorly and pinches the supraspinatus tendon against the acromion. This creates impingement that no amount of external rotation strengthening will fix. You need thoracic extensions over a foam roller and cervical retraction drills before you touch a dumbbell for shoulder work. This alone resolves what might otherwise take months of unnecessary rehabilitation. Another mistake is ignoring the inferior capsule. The rotator cuff isn't just about the four tendons. The glenohumeral ligaments and the inferior capsular pouch contribute significantly to static stability. Tightness in the posterior capsule pulls the humeral head forward during internal rotation. Cross-body adduction stretches and sleeper stretches for the posterior capsule, held for sixty seconds each, three times per session, can make a measurable difference in shoulder positioning within four weeks.
Get the Full Details

When These Exercises Won't Help
I need to be straightforward about the limitations here. Rotator cuff stability exercises will not fix a full-thickness tear, a significant labral lesion, or advanced osteoarthritis. If you have structural damage, the exercises might actually aggravate the condition by increasing joint stress without addressing the underlying problem. In these cases, surgical consultation and targeted physical therapy under professional supervision are necessary. The exercises I described work best for mild to moderate instability, tendinopathy, and preventive conditioning in people without structural pathology. Another scenario where this approach falls apart is with multi-directional shoulder instability caused by generalized ligamentous laxity. These individuals often have Ehlers-Danlos syndrome or similar connective tissue disorders. For them, aggressive strengthening without proprioceptive training can worsen the instability because the joint simply has too much range. In those cases, closed-chain proprioceptive exercises like weight-bearing on an unstable surface with the arm in various positions are more appropriate than the open-chain moves described above.
Building a Sustainable Routine
Do the scapular control work twice a week on non-consecutive days. The empty can and side-lying external rotation can be done three times weekly. Keep sessions under twenty minutes. More volume than that usually means form is deteriorating and you're just accumulating fatigue without adding benefit. Progress the load only when you can complete the target rep range with perfect form for two consecutive sessions. This usually means adding half a pound every two to three weeks at most. Track your symptoms, not just your weights. If pain during the exercises exceeds a three out of ten, drop the load immediately. Discomfort from muscle fatigue is normal. Sharp or shooting pain is not. I've lost count of the number of people who pushed through bad pain and ended up with a more serious injury that set their recovery back by months. The shoulder joint is unforgiving when you ignore its signals.