What EBP Rounding Actually Looks Like in a Busy Hospital
I used to run evidence-based practice rounding on a 28-bed medical-surgical unit, and honestly, most places do it wrong from the start. They treat it like a compliance checkbox instead of a clinical coaching tool, and then wonder why staff disengage within three months. Here is how it actually works when you stop treating it like paperwork and start treating it like what it is: a brief, structured conversation between a clinical leader and frontline staff about specific practices that have proven outcomes. The model itself is straightforward, which is part of why it gets botched. A unit leader — typically a nurse manager, charge nurse, or an EBP champion — rounds directly with bedside staff in short, focused sessions. The purpose is not to audit. The purpose is to identify whether specific evidence-based protocols are being applied correctly, notice barriers in real time, and reinforce adherence through immediate feedback rather than after-the-fact chart reviews. The standard session runs about ten to fifteen minutes. You pick a focus area tied to your unit's priority outcomes. For us, it rotated between pressure injury prevention, early mobilization for post-surgical patients, and appropriate antibiotic timing for surgical prophylaxis. You pick one area per rounding cycle. You ask direct questions about what is happening on the floor right now, not what the policy document says should happen. Then you document the finding and close the loop with a concrete action if something was off.
How to Set It Up Without Ruining It
The biggest mistake I see is trying to round on everything at once. Pick two or three evidence-based practices that align with your measurable outcomes data. If your hospital has high CAUTI rates, start there. If readmissions are climbing, focus on discharge planning protocols. The practice you choose should have clear, observable behaviors that a runder can verify in five minutes of conversation. You also need to schedule it in a way that does not conflict with the actual work. I tried morning rounding during shift change and watched it devolve into staff pretending to listen while simultaneously trying to finish medication passes. That was useless. We moved to mid-afternoon rounds on non-peak hours, and engagement jumped from roughly thirty percent to over eighty percent within six weeks. Documentation matters, but keep it simple. I used a one-page tracking sheet with the date, the staff member, the focus area, the finding, and the corrective action taken. That is it. If your form requires five pages of checkboxes, you will get five pages of rubber-stamped futility.
A Specific Problem I Ran Into and How I Fixed It
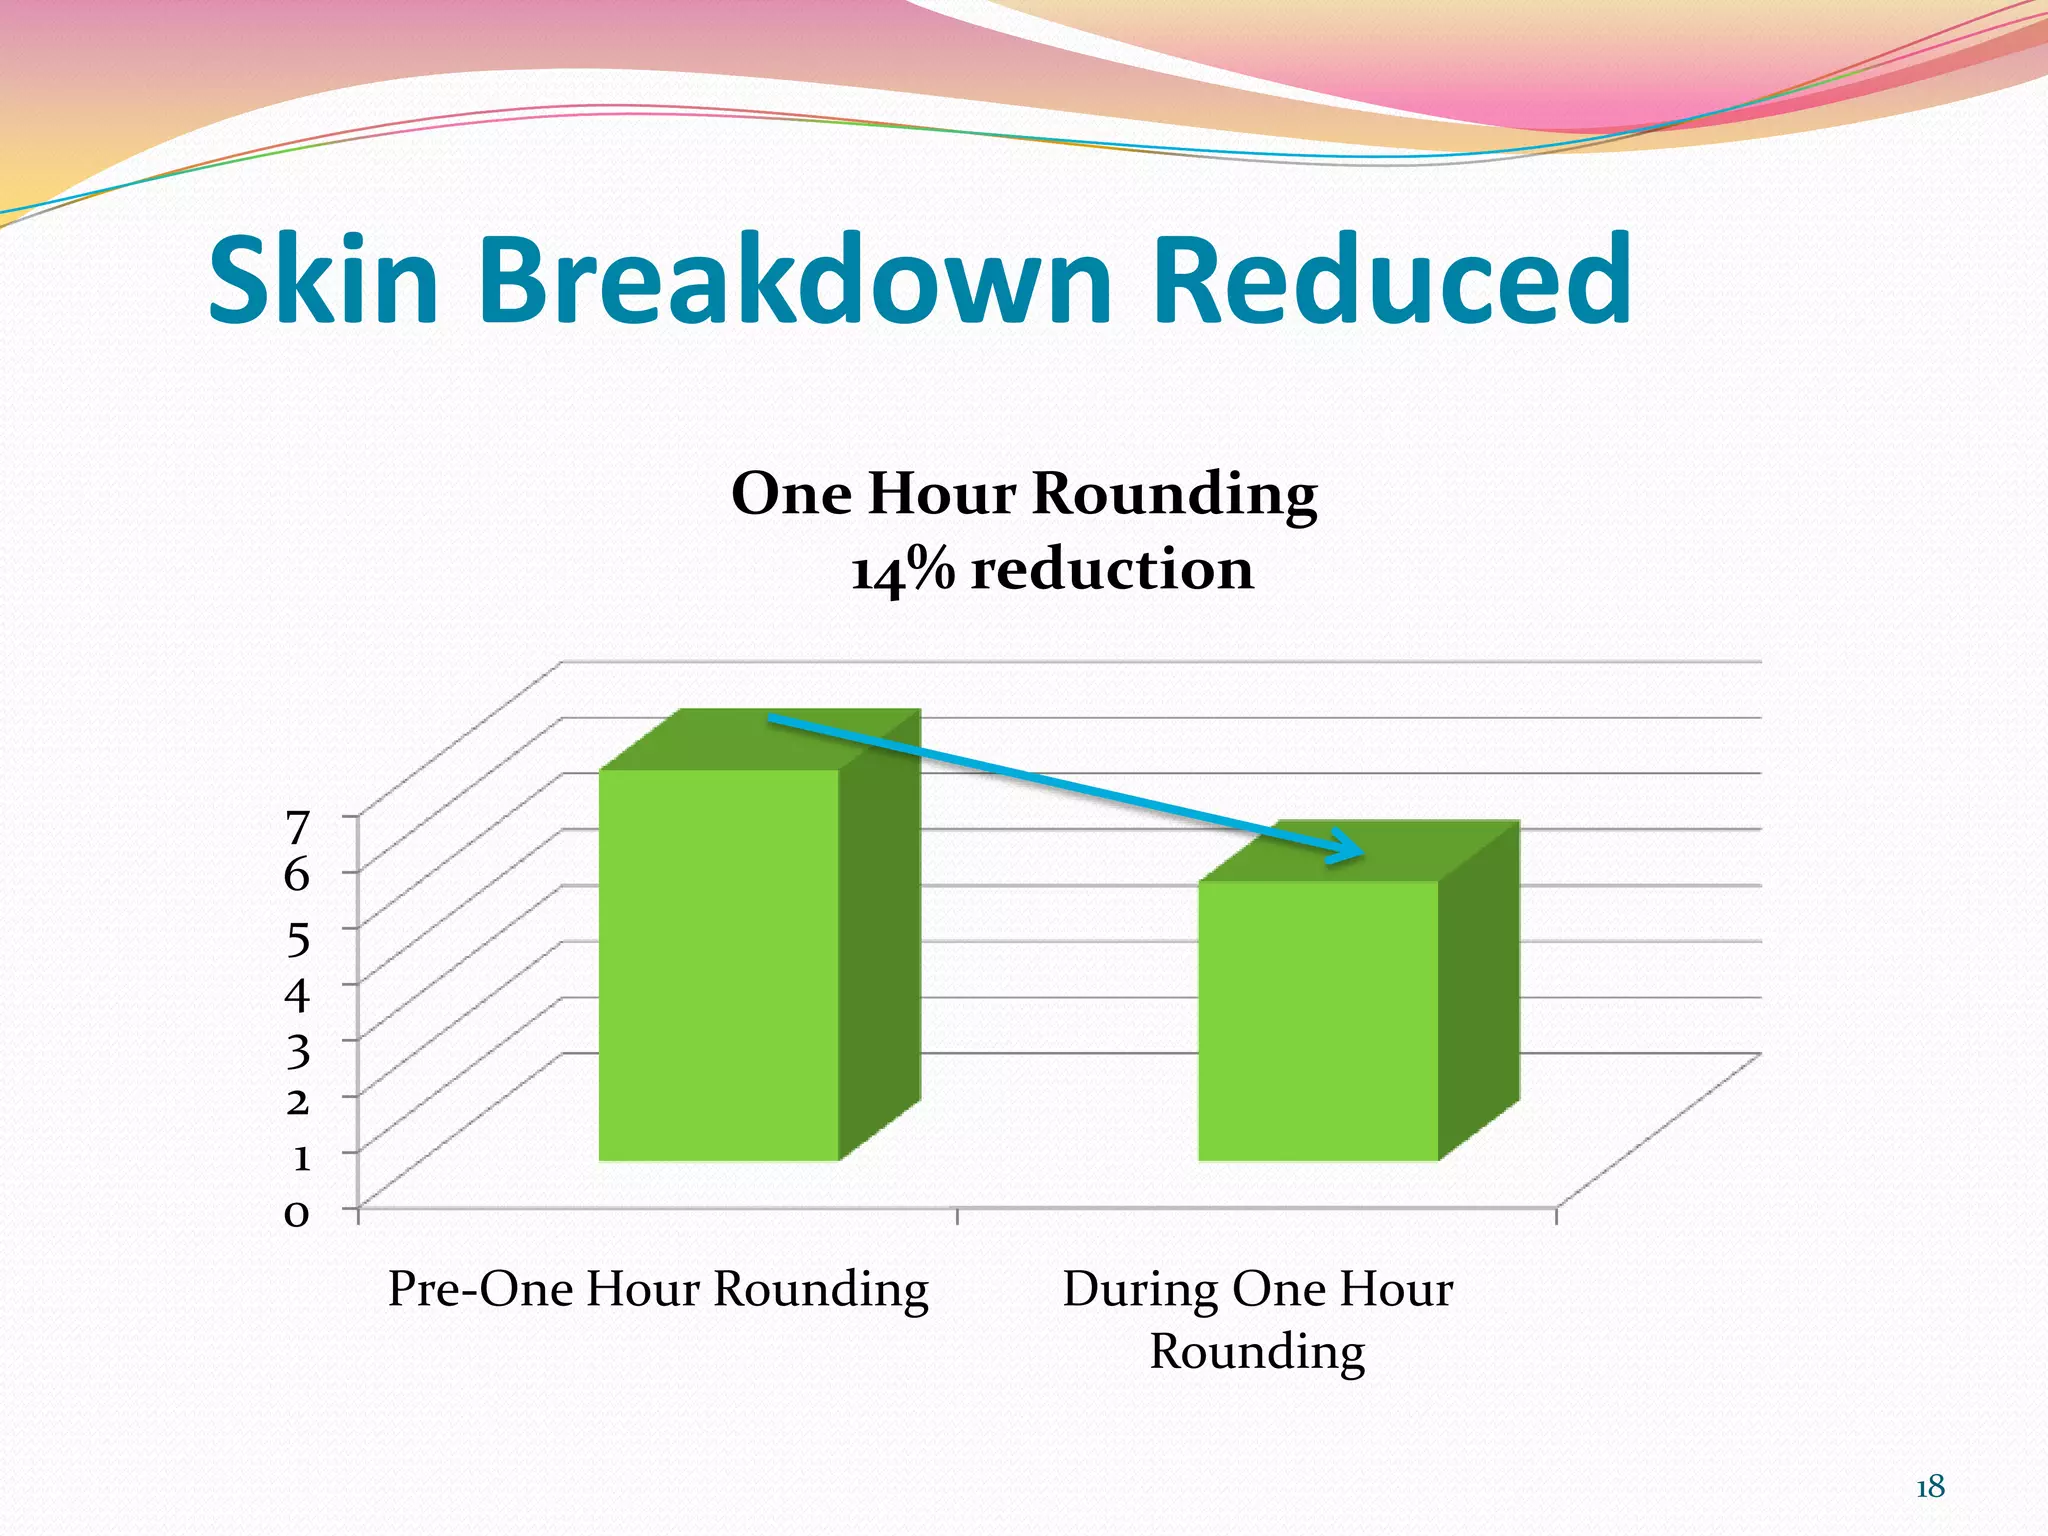
About eight months into our program, I noticed a consistent gap that had nothing to do with staff knowledge and everything to do with supply placement. The evidence-based practice we were rounding on was timely repositioning for high-risk pressure injury patients, mandated every two hours. The charting said it was happening. The stories from staff said otherwise. Turns out the specialized repositioning wedges had been moved to a different supply closet during a facility renovation six months prior, and nobody had updated the supply location on the rounding checklist or notified the floor staff. Staff were saying they did not have the equipment available when they actually just could not find it. The workaround was immediate. I added a supply availability verification step to the rounding template — a simple question: "Do you have everything you need to perform this protocol right now?" Within two weeks, that question surfaced three other hidden barriers, including an insulin pump model that had been discontinued without replacement communication. Rounding on the practice alone would never have caught this. You have to round on the conditions that enable the practice, not just the practice in isolation.
Get the Full Details

Counter-Intuitive Things Nobody Tells You
First, staff will tell you what they think you want to hear unless you create genuine psychological safety during the conversation. I learned this the hard way when a staff nurse finally admitted during a private moment that she had been skipping the early mobilization protocol for certain post-op patients because the order set did not include clear vital sign stability parameters. She was afraid of being blamed for a fall. The rounding process itself was fine. The culture around it was not. We fixed it by revising the order set to include explicit clearing criteria and then looping back to that same nurse three weeks later to confirm she felt comfortable using it. That follow-up conversation meant more than every rounding session before it. Second, rounding data looks better than reality. Chart documentation and staff self-report will inflate your compliance numbers by twenty to thirty percent compared to direct observation. If you want accurate data, someone needs to watch the behavior happen, not just read about it afterward. This is why occasional unannounced observational rounding beats scheduled educational rounding for measuring true adherence.
When This Approach Fails Completely
EBP rounding does not work if leadership treats it as punishment. I watched a unit where the manager started recording non-compliance findings with employee names and sharing them in staff meetings. Compliance numbers technically went up for six weeks, then plummeted below baseline because everyone stopped reporting honestly and started covering for each other. The data became garbage. The practice stopped improving. Turnover on that unit spiked within a year. It also fails when the evidence-based practice itself is stale. We had to phase out one of our focus areas after a major systematic review came out that directly contradicted our protocol. Staff had invested credibility in following the old guideline, and keeping it on the rounding list felt like asking people to keep obeying a rule everyone knew was wrong. We retired that practice from the rotation, published the new evidence to the unit, and retrained. That took two weeks of lost rounding time but prevented months of quiet non-adherence.
Downloading a Practical Rounding Template
I built our working template over fourteen months and refined it through constant use. You can grab a copy of the final version here: [Download EBP Rounding Template]. It includes the focus area rotation guide, the supply availability check I mentioned, and a section for logging follow-up actions with expected completion dates. Nothing fancy. Just what survived contact with an actual unit.

The Bottom Line
EBP rounding works when it is treated as a real-time quality improvement mechanism, not a reporting exercise. It will surface problems you did not know existed, and it will also reveal problems your data was hiding. The people doing the rounding need clinical credibility, not just administrative authority. And you need to be willing to change the practices you are rounding on when the evidence changes. Sticking to an outdated protocol because it is easier to measure is worse than measuring nothing at all.