How Drugs Actually Get Into the Body
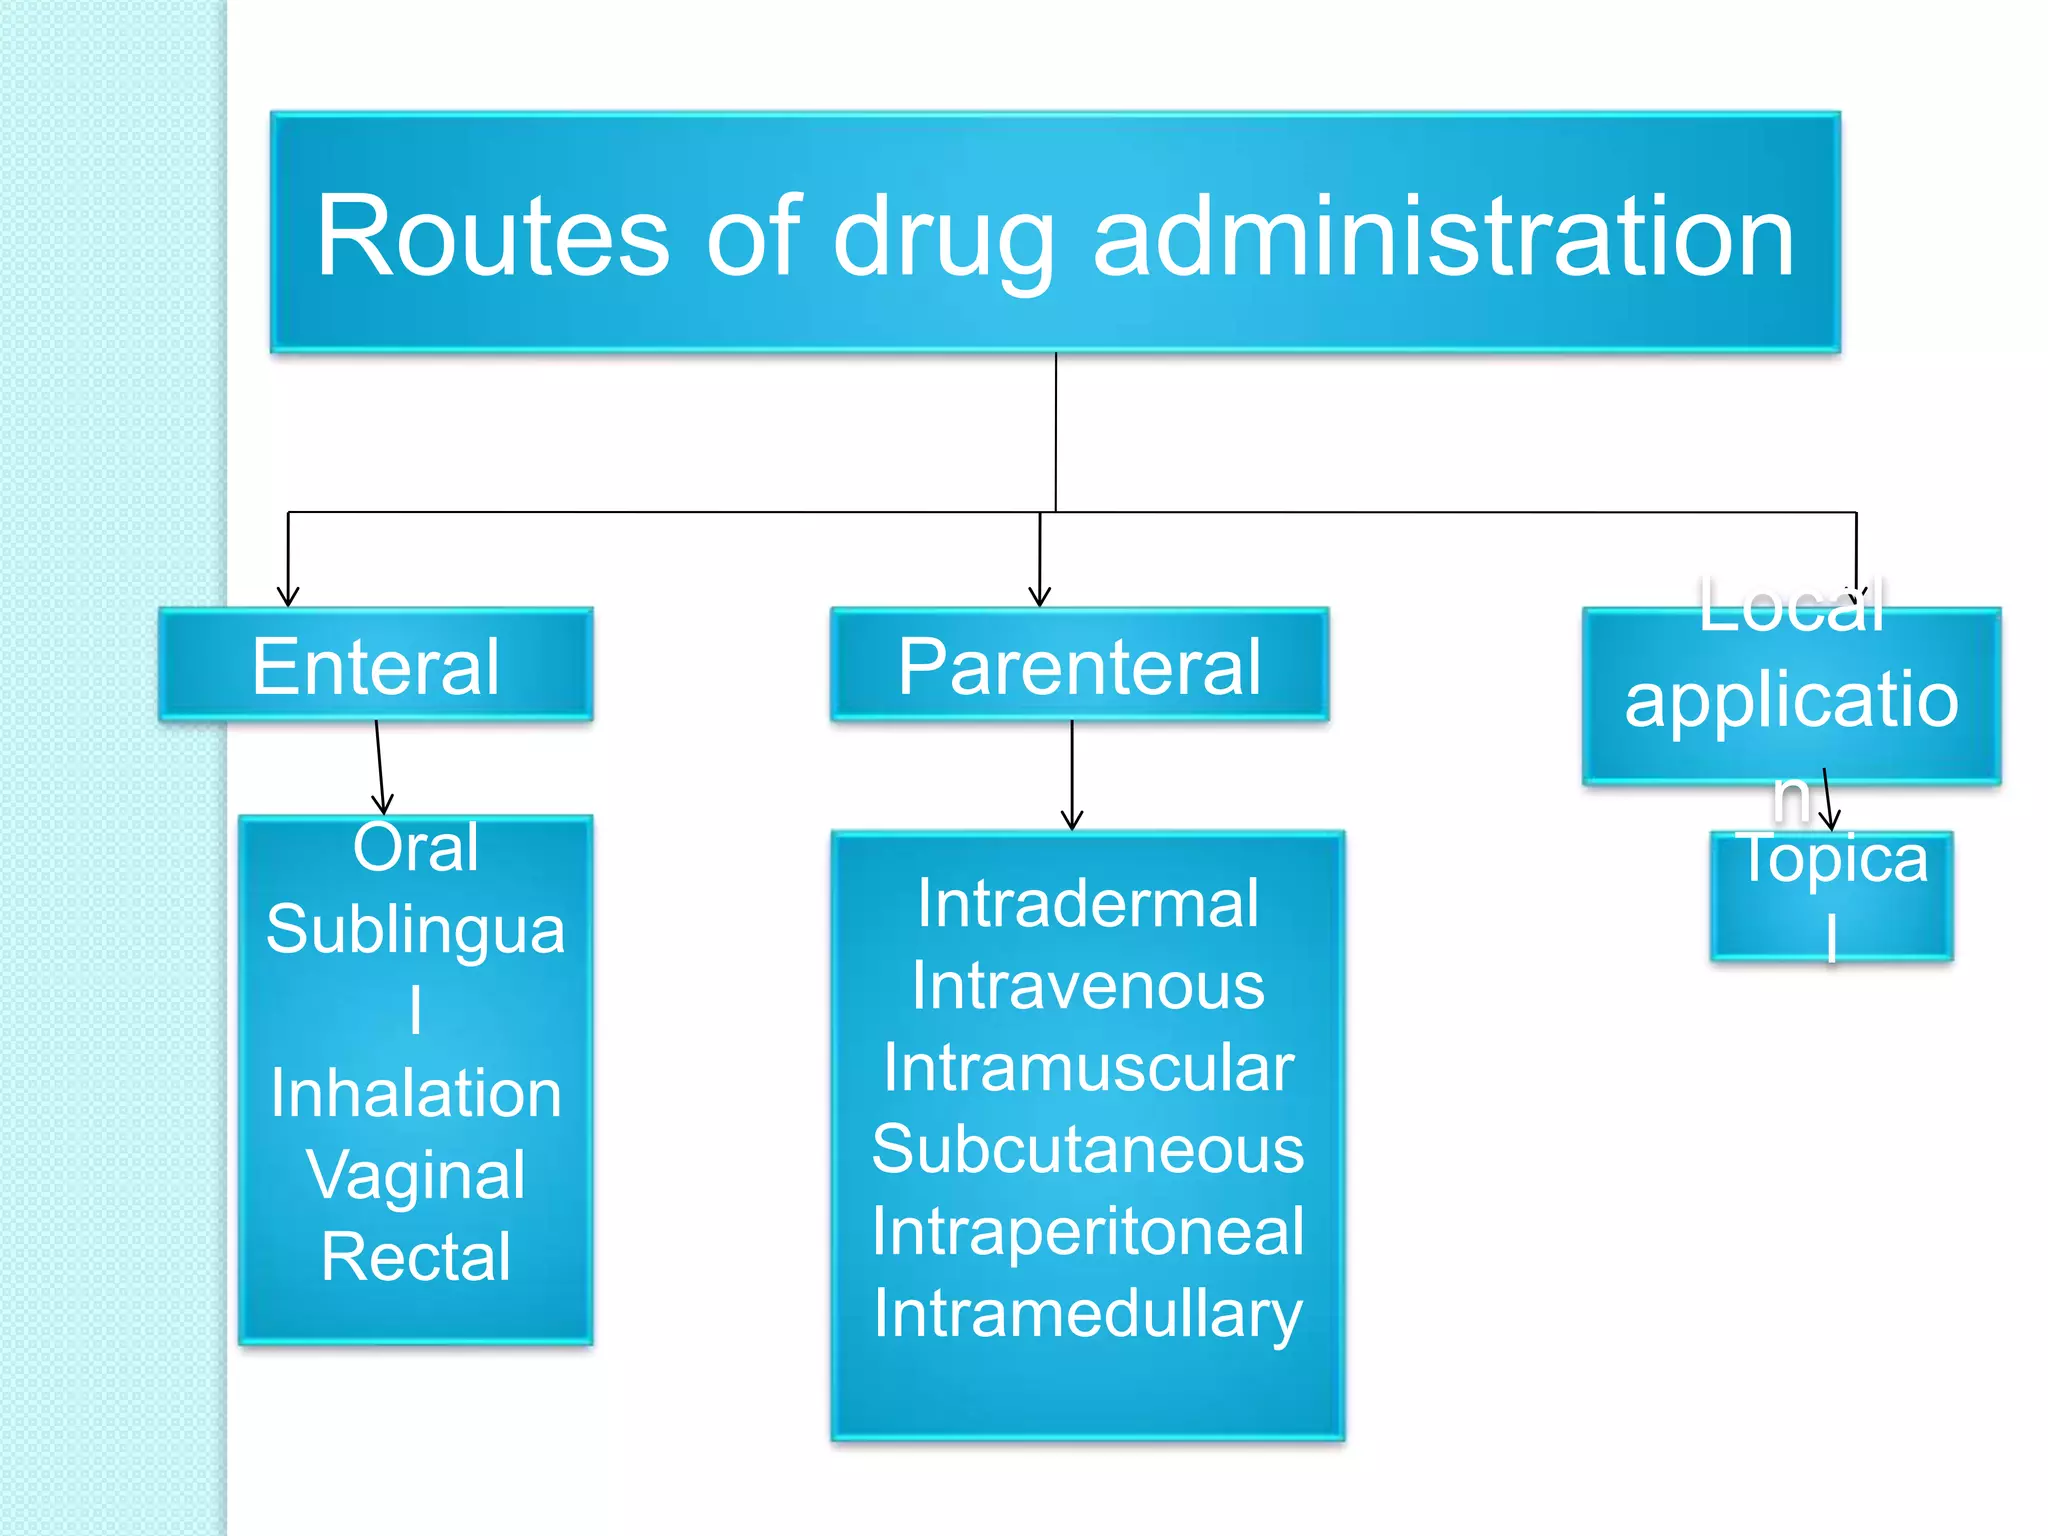
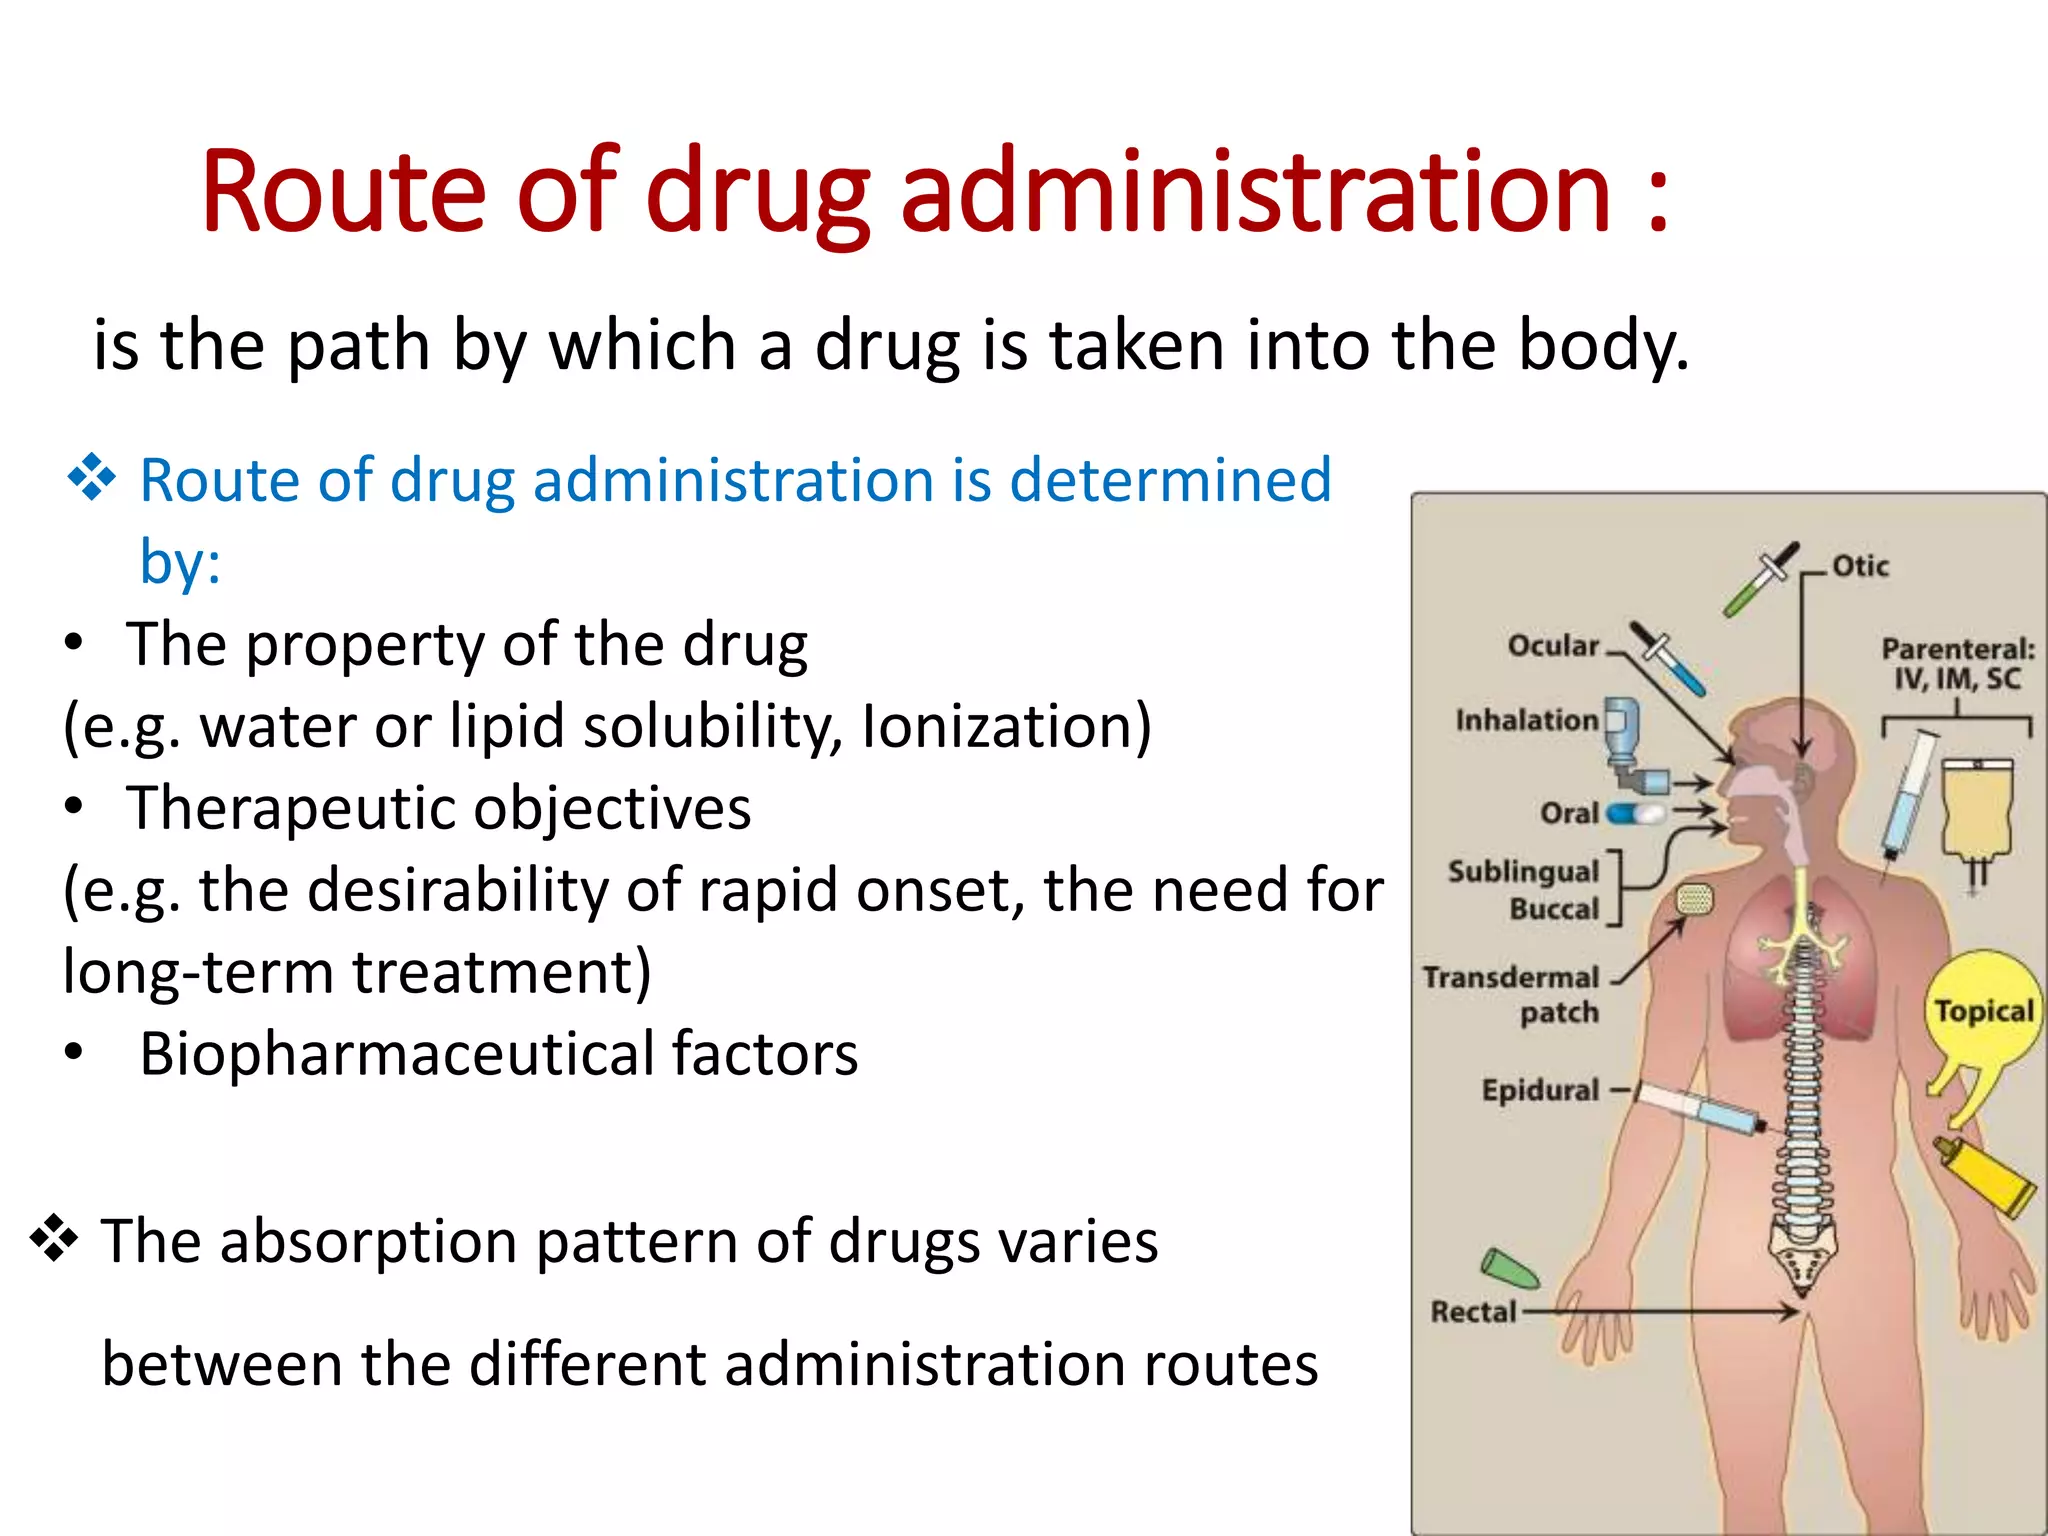
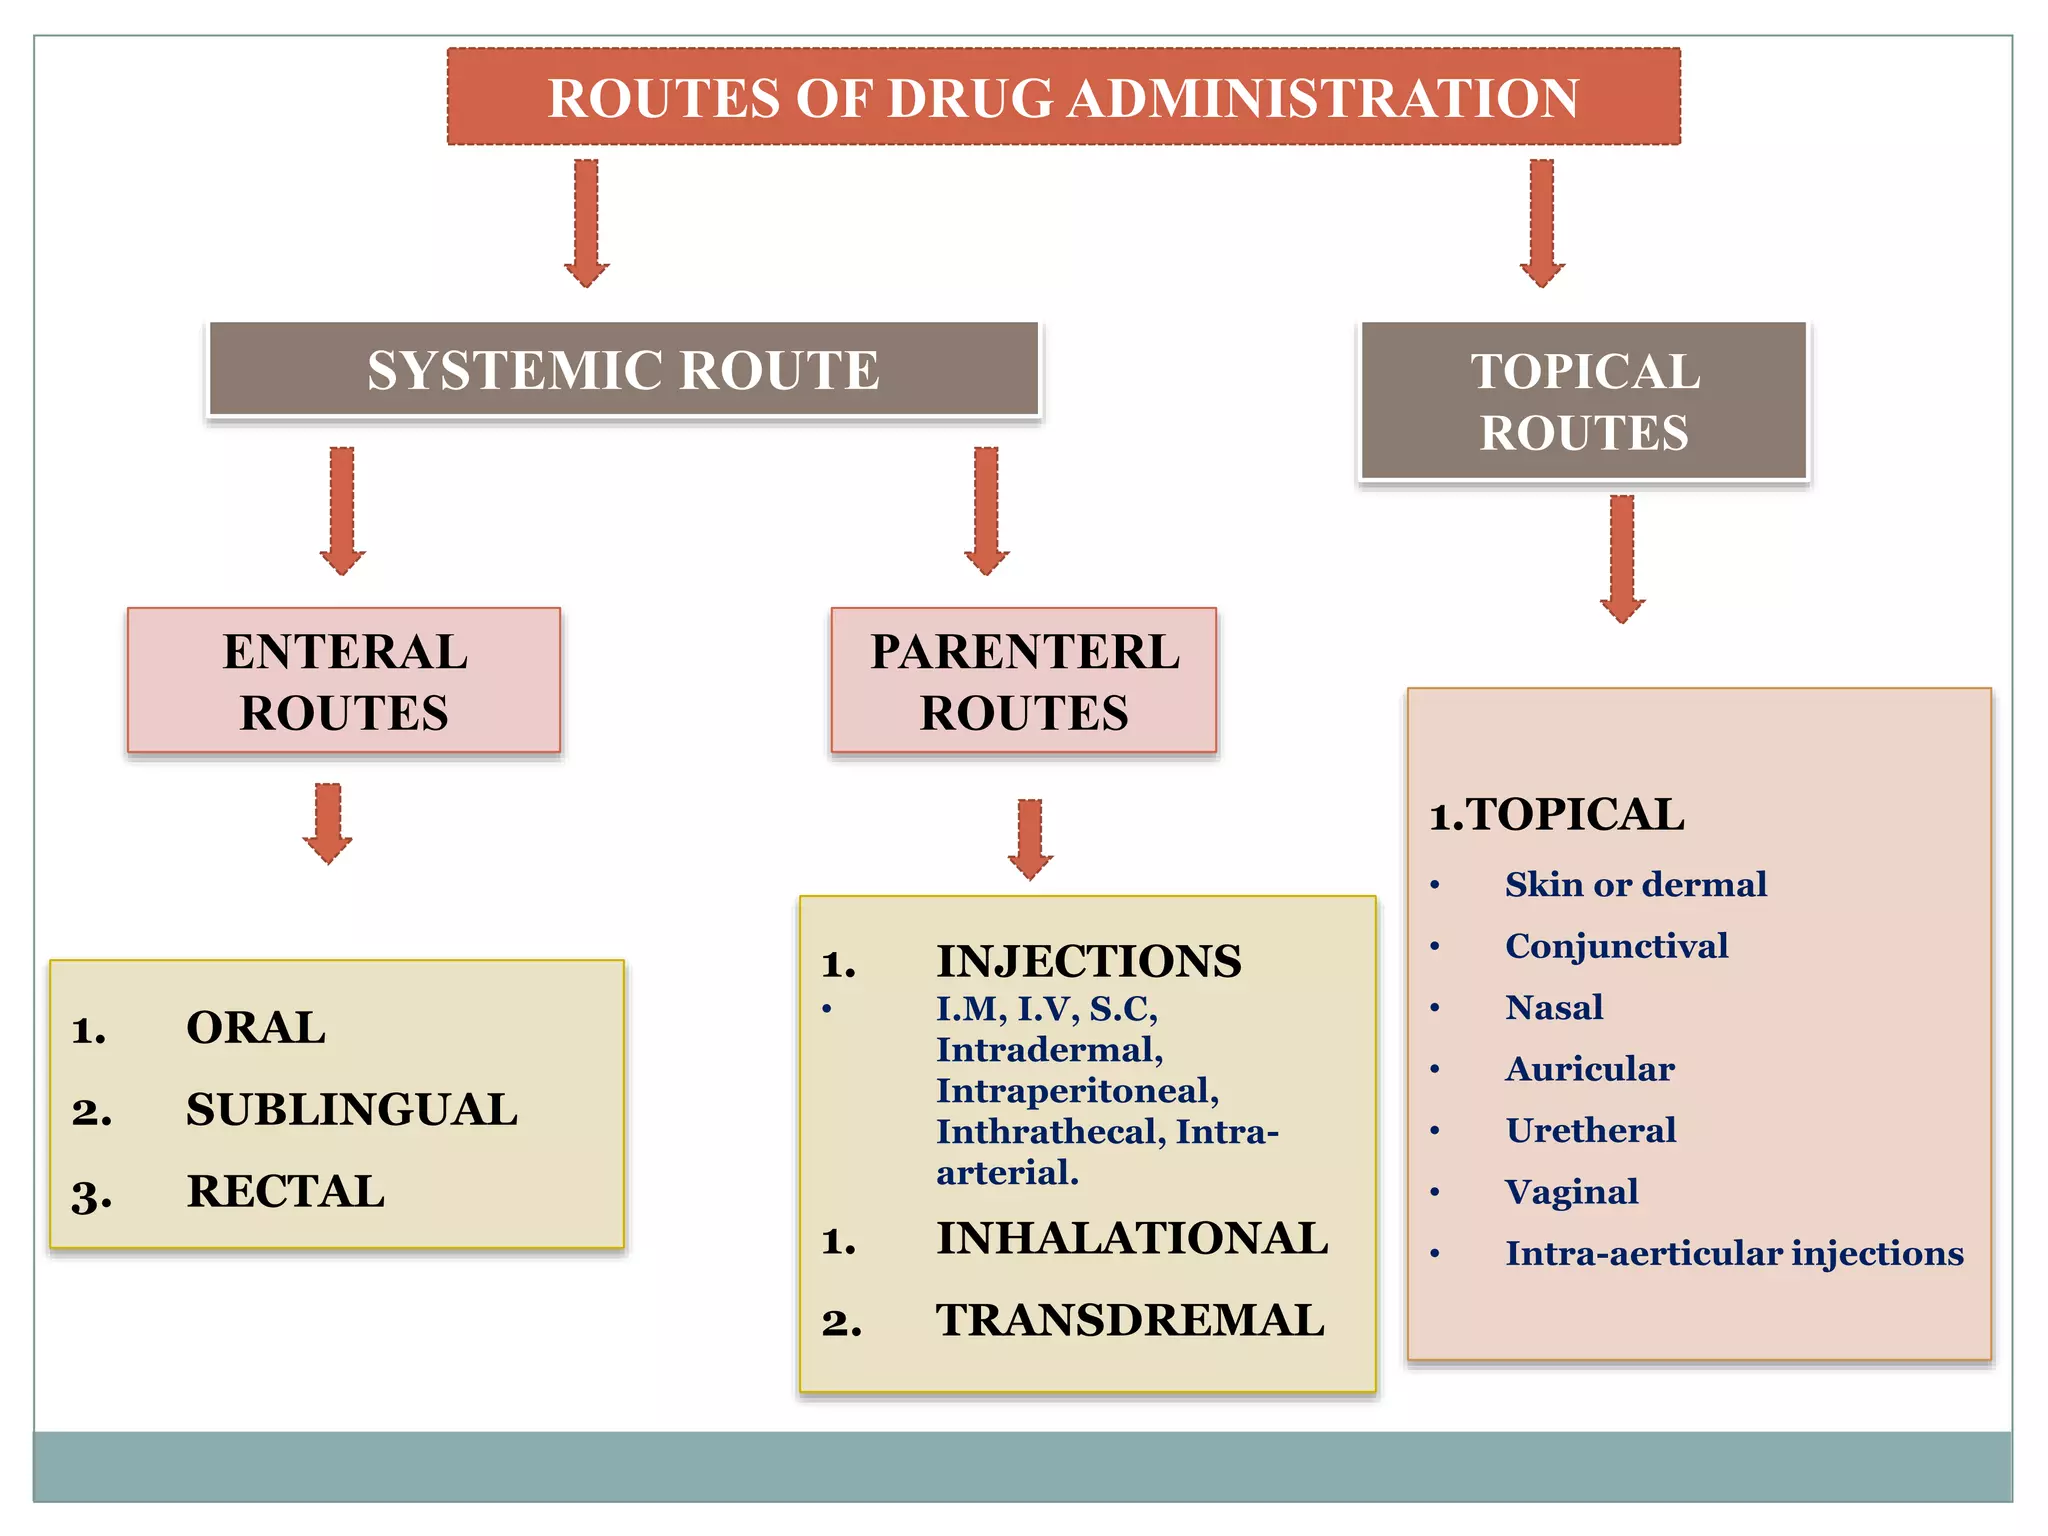
I spent about three years watching formulation scientists try to get the same molecule to work properly across different delivery methods. The part nobody tells you is that the route you pick doesn't just change how fast the drug works — it changes the chemical itself. What goes into a tablet is rarely what reaches the bloodstream, and figuring out the gap between those two things is where most failures happen. The Routes Of Drug Administration framework is simpler than people make it, which is probably why it gets botched so often in practice. You have enteral, parenteral, topical, and a few outliers like inhalation. Each one has tradeoffs that matter more than the textbook versions admit.
Oral Administration: The Default That Isn't
Oral is the first choice because it's easy. Swallow something, hope it survives the stomach. But about forty percent of new molecular entities fail here simply because they get destroyed by gastric acid or can't cross the intestinal membrane. I watched a perfectly valid compound get written off because the researchers didn't account for first-pass metabolism in the liver. The drug worked fine in vitro. It did nothing in vivo after oral dosing because the liver extracted ninety-five percent of it before it ever reached systemic circulation. The workaround isn't fancy. We switched that compound to sublingual delivery, which bypasses the hepatic first pass entirely. Bioavailability jumped from five percent to around sixty percent. Same molecule, different route. The lesson is basic but easy to ignore when you're focused on the pharmacology and not the delivery physics. Enteric coating helps with acid-sensitive drugs, but it adds another failure mode. If the coating doesn't dissolve at the right pH in the intestine, you get zero absorption. I've seen batches where a two-degree shift in coating formulation made the difference between therapeutic and placebo-level exposure.
Parenteral Routes: Precision With Higher Risk
Intravenous administration gives you one hundred percent bioavailability by definition, since the drug goes straight into the bloodstream. That sounds ideal, and for some drugs it is. But IV also means zero margin for error. Wrong dose, wrong rate, wrong patient, and there's no absorbing tissue to buffer the mistake. The onset is immediate, which is why it's the standard for emergencies, but the offset is equally immediate, which is why some drugs that work fine IV become useless the moment you stop the infusion. Subcutaneous and intramuscular routes sit somewhere between oral and IV in terms of speed and reliability. SC absorption depends on blood flow at the injection site, which is why epinephrine for anaphylaxis goes IM into the thigh rather than SC into the arm. Same drug, dramatically different absorption kinetics based on where you put it. One thing beginners consistently miss: not all parenteral formulations are interchangeable. A drug in saline solution behaves differently than the same drug in an oil-based suspension, even if the active molecule is identical. I dealt with a case where switching from a aqueous IV formulation to an oil-based IM version of the same corticosteroid was supposed to be a simple convenience change. It wasn't. The peak concentration dropped by half, the time to peak shifted from hours to days, and the therapeutic window narrowed enough that the dosing schedule had to be completely rewritten.
Get the Full Details

Topical and Transdermal: The Local-versus-Systemic Divide
Topical application is for local effect. Cream on skin, ointment on a wound, drops in the eye. The drug isn't supposed to go anywhere else. Transdermal is different — the goal is systemic absorption through the skin, and the skin is really, really good at keeping things out. Only about one in a thousand molecules can cross intact skin effectively. That's why most transdermal patches contain vehicles or enhancers that disrupt the stratum corneum temporarily. Fentanyl patches work because fentanyl is highly lipophilic and potent at microgram doses. Try putting that same approach on a hydrophilic drug at milligram doses and you'll spend months fighting absorption that simply won't happen. I once worked with a team that spent six months trying to get a polar peptide drug through transdermal delivery. The patch looked fine. The drug was stable in the matrix. It just never crossed the skin in meaningful amounts. We ended up going with a nasal spray instead, which gave us reasonable systemic absorption in two weeks of work. The moral is that route selection should happen early, not after you've built a delivery system that turns out to be anatomically impossible.
Inhalation and Mucosal Routes: The Overlooked Options
Inhalation delivers drugs to the lungs, where the surface area is enormous and the blood flow is dense. It's the fastest route after IV for systemic delivery, and it's the only practical route for local pulmonary treatment. But particle size matters enormously. Particles bigger than ten microns deposit in the oropharynx and get swallowed. Particles smaller than 0.5 microns get exhaled before they deposit. The sweet spot for alveolar absorption is between one and five microns, and hitting that range consistently in manufacturing is harder than it sounds. Nasal and buccal routes sit between enteral and parenteral in terms of absorption speed. The nasal mucosa is highly vascular, and drugs absorbed there bypass first-pass metabolism. I've used intranasal midazolam for seizure breaks when IV access wasn't available, and the onset was within minutes. Buccal administration, like the sublingual example above, avoids the GI tract entirely. Nitroglycerin for angina works this way because oral administration would destroy most of the dose.
Practional Considerations That Matter More Than the Theory
Route selection isn't just about pharmacokinetics. Patient compliance is a huge factor. A drug with perfect IV bioavailability is useless if the patient can't or won't return to the clinic every eight hours for an infusion. Oral formulations dominate the market not because they're pharmacologically optimal but because they're the only route most patients will actually use consistently over months or years. Cost and infrastructure matter too. Parenteral drugs require sterile manufacturing, which is exponentially more expensive than tablet production. Topical formulations need penetration enhancers or specialized carriers that add complexity. Inhalation devices need precision engineering. Every route beyond oral adds a layer of cost and failure risk. The route also determines the dosage form, which feeds back into stability, shelf life, and regulatory classification. A drug approved as an oral tablet can't simply be re-formulated as an IV injection without going through an entirely new clinical program. The molecule is the same, but the regulatory pathway is completely different because the risk profile changes when you remove the gut as a barrier.
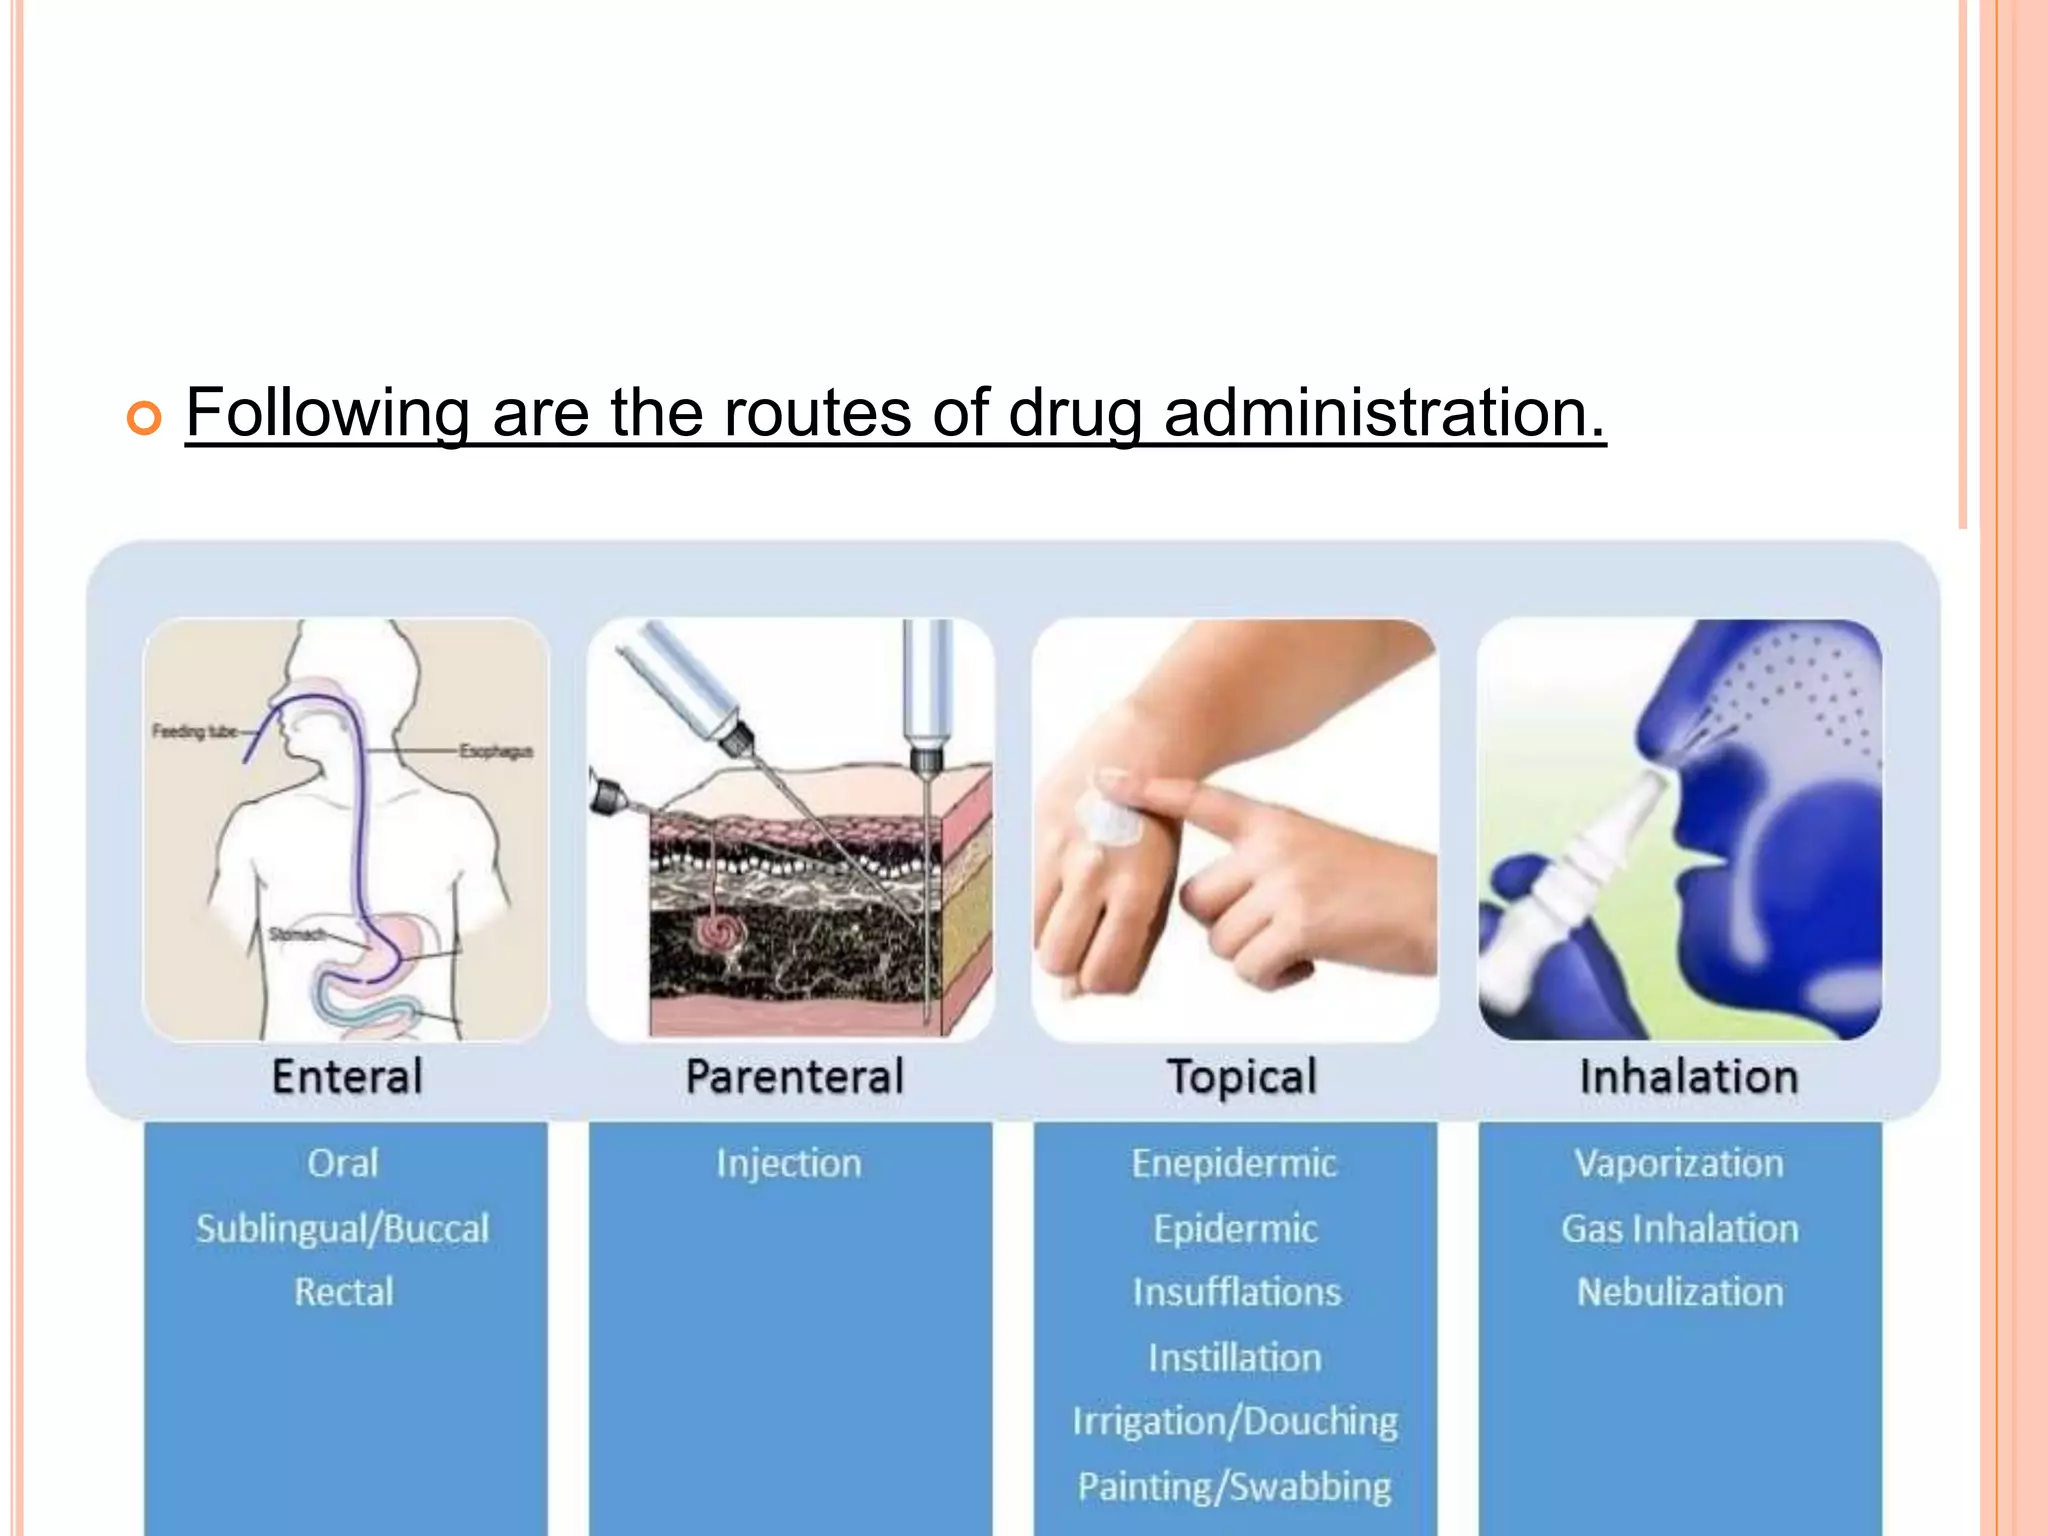
There's no universal answer to which route is best. It depends on the drug's physicochemical properties, the disease being treated, the required onset and duration of action, the patient population, and the manufacturing and regulatory constraints. The framework exists to help you think through those variables systematically, not to give you a single right answer.