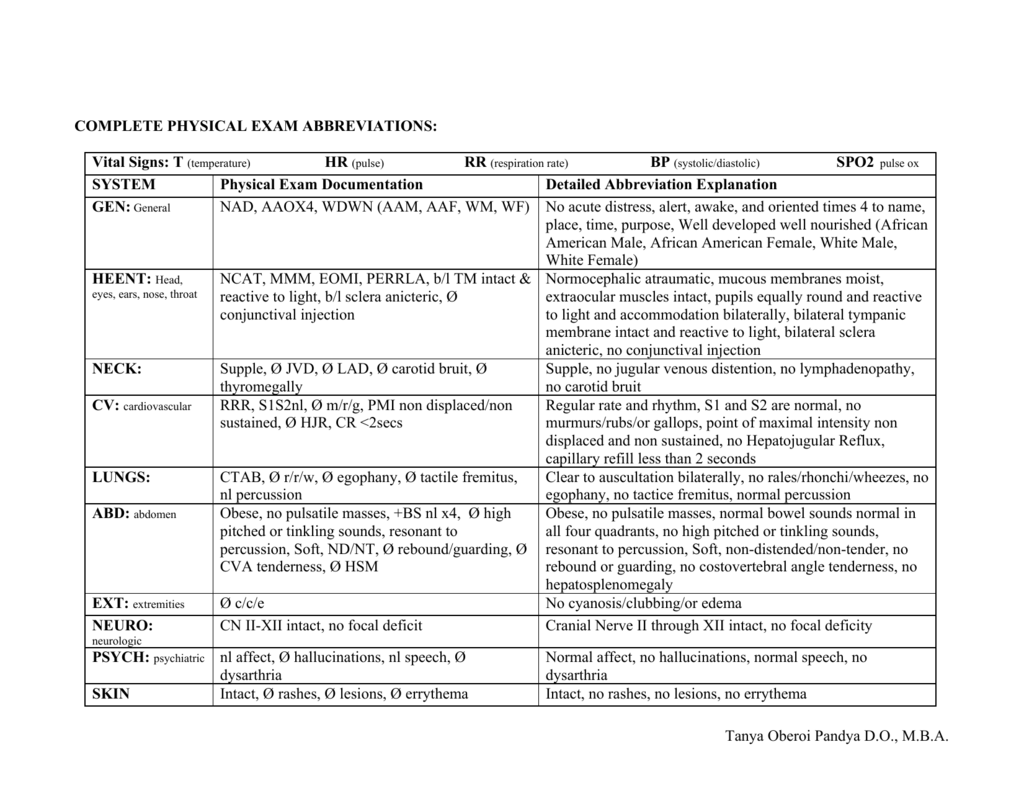
Understanding RRR in the Physical Exam
RRR stands for Regular Rate and Rhythm. You will see it everywhere in clinical notes, especially in the cardiovascular section of a physical exam. It means the clinician listened to the heart and found a normal sinus rhythm with no irregularities. That is it. Nothing more profound than that. The abbreviation saves time. Doctors write it so they do not have to compose a full sentence every time they document a normal cardiac exam. It shows up in progress notes, discharge summaries, operative reports, and pre-op clearance forms. I have seen it scrawled in so many hand-written charts that it became one of the first abbreviations any medical student learns.
The Rrr Medical Abbreviation Physical Exam in Practice
Here is how it actually works during an exam. The physician places the stethoscope on the precordium, usually starting at the aortic, pulmonic, tricuspid, and mitral areas. They listen for each valve region for at least 30 to 60 seconds. If the heart sounds are consistent in tempo and spacing, if there are no extra sounds like S3 or S4 gallops, no murmurs, and the pulse rate is within normal range, they write RRR. But writing RRR is not the hard part. The hard part is knowing when you should not write it. I spent weeks in internal medicine rotations early in my career thinking a quick listen was enough. My attending pulled me aside after I documented RRR on a patient who had a subtle irregularity. It turned out the patient had frequent premature atrial contractions that only showed up during certain respiratory phases. A thirty-second listen missed it entirely. A full minute of continuous auscultation would have caught it. That changed how I approach every cardiac exam after that. Now I listen for at least two full respiratory cycles at each location. I also correlate the apical pulse with the radial pulse simultaneously. If there is a discrepancy between the two counts, that is a pulse deficit, and RRR is simply wrong regardless of what the heart sounds like through the stethoscope. I have caught atrial fibrillation this way more than once when the rhythm sounded almost regular through the chest wall.
What RRR Does and Does Not Tell You
One thing most people miss is that RRR tells you almost nothing about heart function. A patient can have a perfectly regular rhythm and still be in heart failure. The rate could be sixty beats per minute and the rhythm completely regular, and the ejection fraction could be twenty percent. RRR does not capture systolic function, diastolic function, valvular competence, or wall motion abnormalities. It only describes timing. Another counter-intuitive point: RRR is not the same as normal heart sounds. You can have regular rate and rhythm with significant murmurs or pericardial rubs. The rhythm is regular even when the underlying pathology is serious. I have seen residents write RRR and then stop documenting the rest of the cardiac exam because they thought they were done. That is a documentation gap that leads to missed diagnoses. Always document the full findings. RRR belongs in a complete note, not as a substitute for one. The abbreviation also creates a dangerous shorthand culture. I worked in a hospital where a new resident wrote RRR on a post-operative cardiac surgery patient who was actually in atrial flutter with variable block. The rhythm was regular enough in short bursts that it looked RRR on quick inspection, but a full twelve-lead ECG told a different story. The attending physician almost missed it because the prior nursing note already said RRR and nobody felt the need to re-evaluate. We now require an ECG on file before anyone documents RRR for post-operative cardiac patients. It is a policy change born from that exact error.
Get the Full Details
Common Pitfalls and When RRR Is Misleading
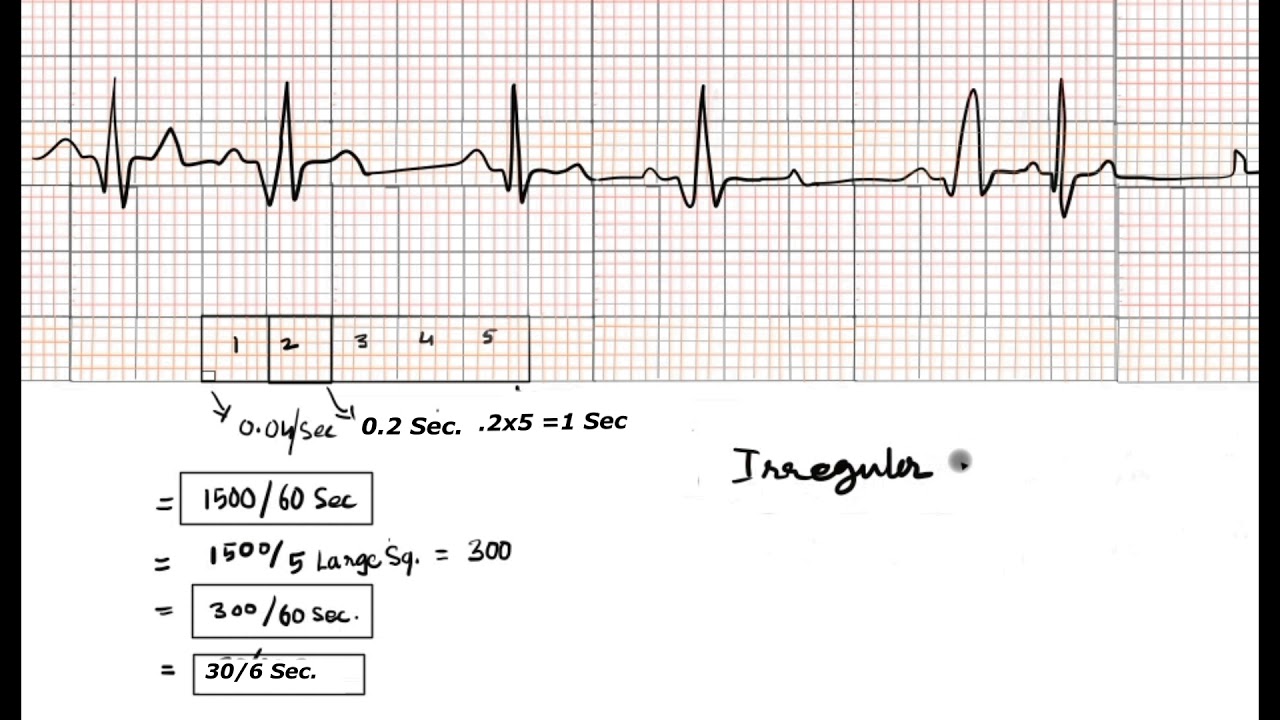
Regular rate and rhythm does not rule out arrhythmia in several specific scenarios. Sinus arrhythmia is a normal variant, especially in younger patients, where the heart rate varies with respiration. The rhythm is technically irregular but physiologically normal. Some clinicians still write RRR in these cases because the variation is mild and the rate is normal. Others write NSR with sinus arrhythmia noted. There is no universal standard, and both approaches exist in the wild. Another scenario where RRR fails you is second-degree heart block type I, also known as Mobitz type one. The PR interval lengthens progressively until a beat is dropped, then the cycle resets. To a casual listener, this can sound almost regular, especially if the Wenckebach cycles are long and the dropped beats are sparse. I once charted RRR on a patient who turned out to have high-grade AV block that required a pacemaker. The error only showed up when I reviewed the telemetry strip the next morning. Now I double-check any borderline case against the telemetry before finalizing the note. If you need a reliable reference for standard physical exam documentation, the Bates Guide to Physical Examination and History Taking remains the closest thing to a gold standard. Most hospital electronic health record systems also have built-in templates that prompt you to document more than just RRR. Using those templates is one practical workaround for the impulse to abbreviate too much.
There is also a push in certain institutions to move away from RRR entirely and require full phrases like "regular rate and rhythm" or to document the exact heart rate and rhythm description instead. The reasoning is that abbreviations contribute to communication errors, especially when notes are handed off between providers who may interpret them differently. Whether that movement is worth the slowdown in documentation speed is something the medical community is still debating.