Drug Reference Tools and Why Most People Use Them Wrong
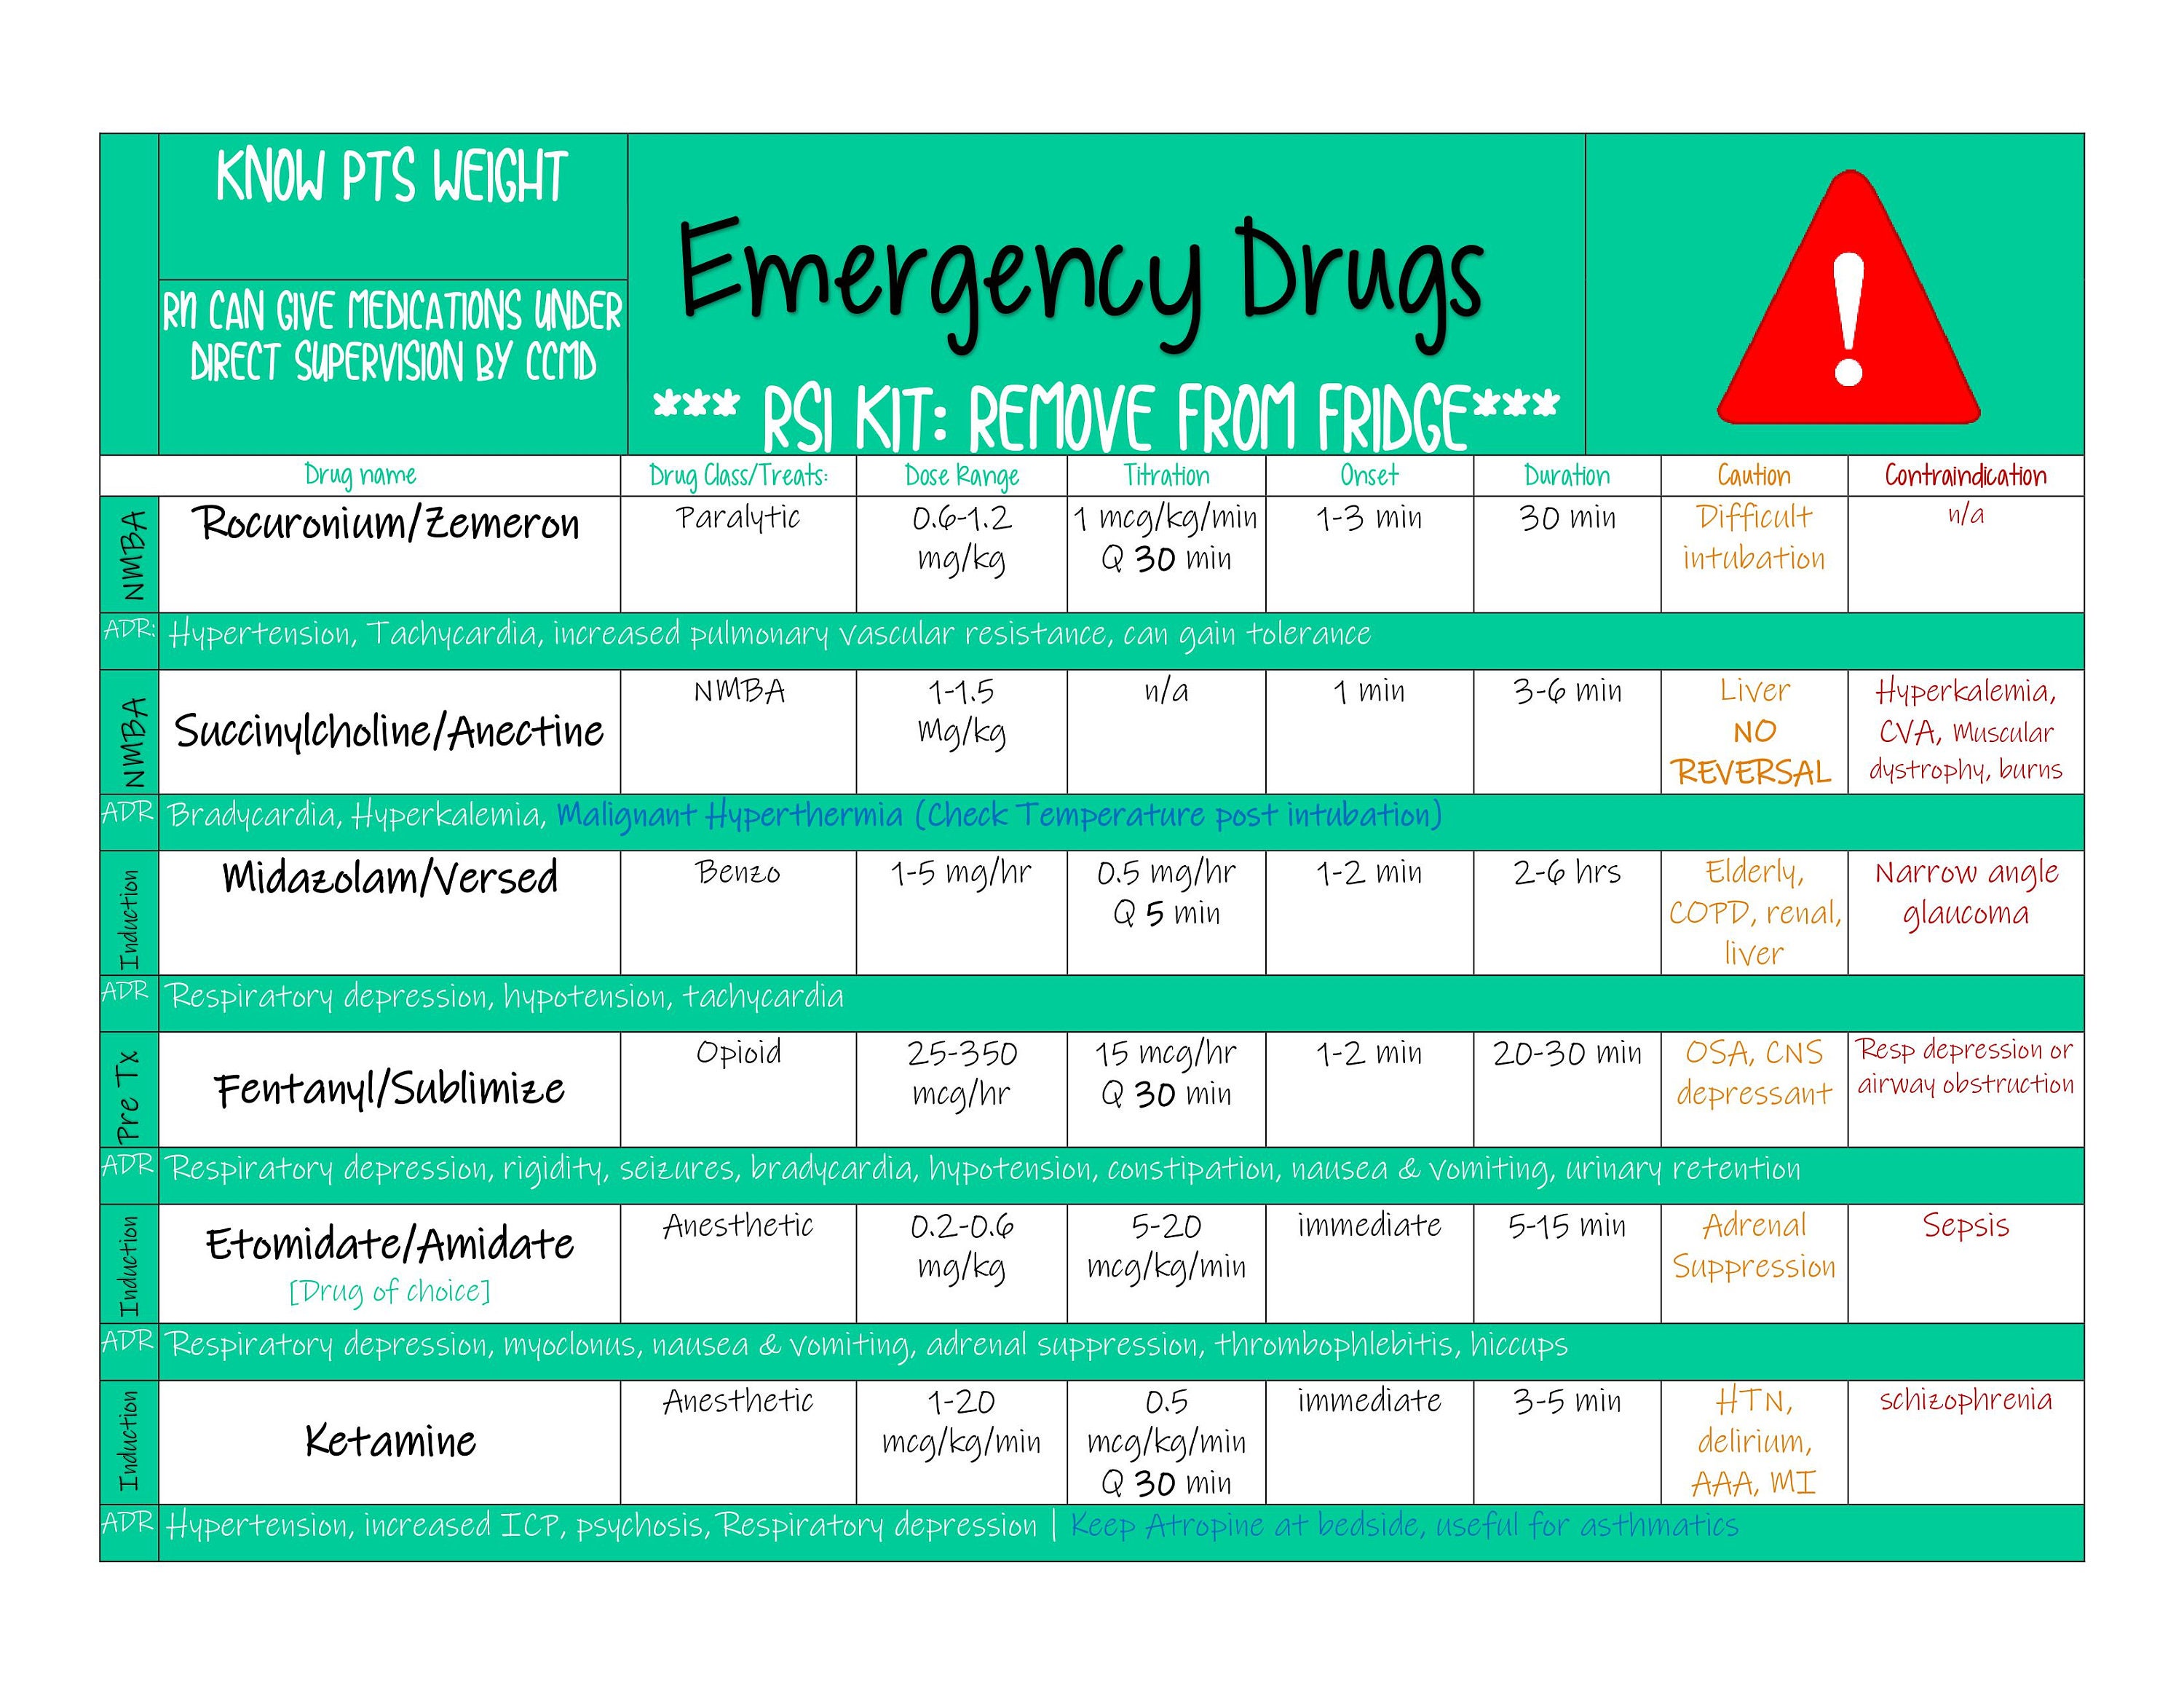
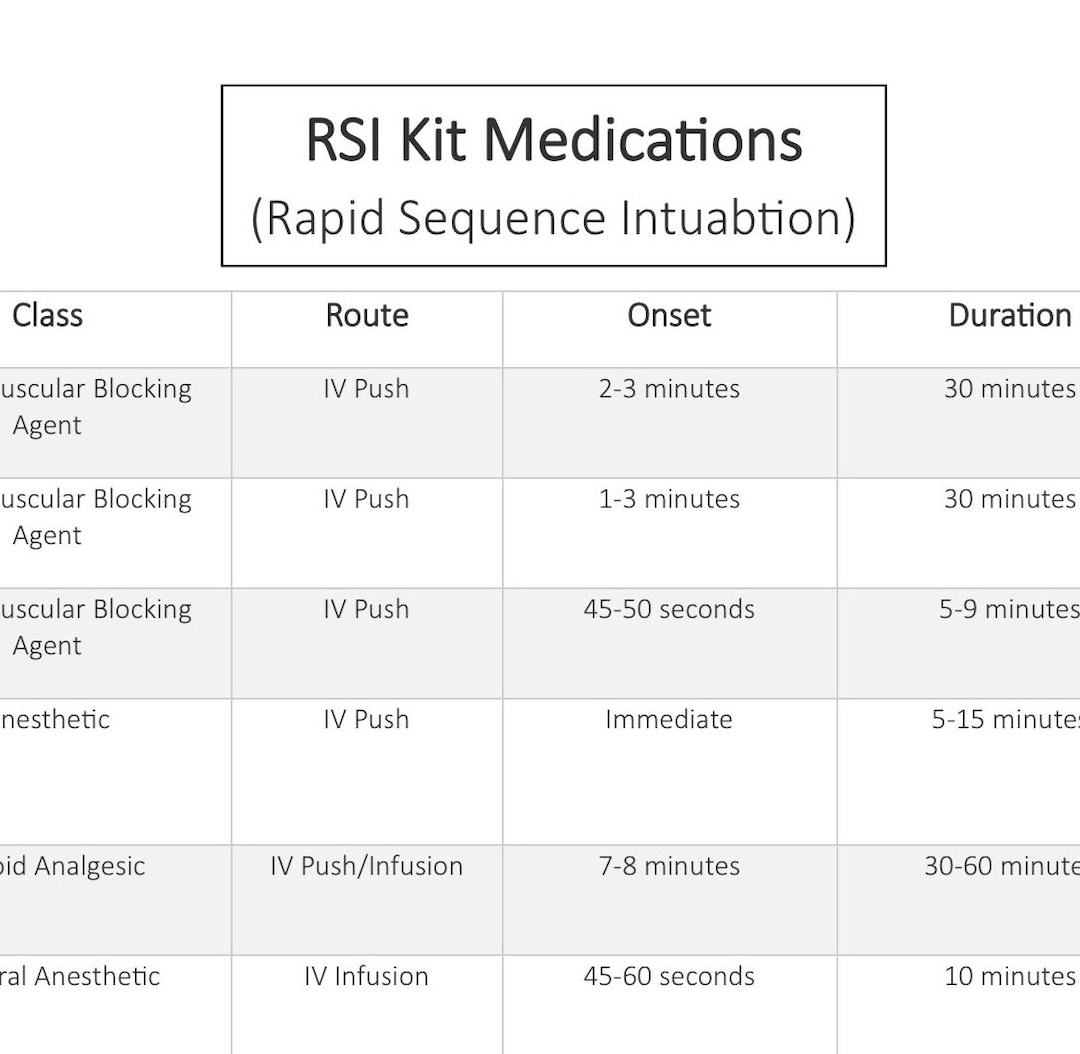
I spend a lot of time looking at people's workflow around drug interaction checking, dosing references, and similar quick lookup systems. The term Rsi Drugs Cheat Sheet comes up occasionally in pharmacy and med-study circles, usually pointing to condensed reference material meant to speed up quick decisions during clinical practice or exam prep. What I can tell you from direct experience is how these materials actually perform in the field versus how they get marketed. Most cheat sheets in this space are one to three pages covering high-yield drug interactions, dosing adjustments for renal or hepatic impairment, and common adverse effect patterns. The useful ones are organized by organ system or drug class, not alphabetically. Alphabetical layout looks clean but slows you down when you are under time pressure. I found this out the hard way during a residency rotation when I was constantly flipping through a poorly organized document and nearly missed a significant CYP3A4 interaction involving a macrolide antibiotic and a statin. That mistake stayed with me. The practical workaround was to reorganize the material myself into a two-column format with drug classes on the left and interaction categories on the right. I added color coding for life-threatening interactions in red and monitoring-only situations in yellow. This cut my lookup time from roughly two minutes per query down to about fifteen seconds for the majority of cases.
If you are looking for a downloadable version, most of these cheat sheets circulate through medical education forums, pharmacy student groups, and independent pharmacology resources. I do not host or distribute copyrighted reference material, and I cannot verify the accuracy of versions floating around online. The ones from professional organizations or peer-reviewed journals tend to be more reliable than files shared on random study sites. Always cross-reference with a primary source before making clinical decisions. Here is a nuance most beginners miss: cheat sheets excel at surface-level recall but fail at edge cases. They will tell you that warfarin interacts with amiodarone. They will not tell you how to adjust dosing when the patient has moderate renal impairment and is also on a PPI. For those situations you need a full reference like Lexicomp or Micromedex, or you need to run the case through a proper clinical decision support tool. A cheat sheet is a starting point, not a replacement for thorough evaluation. Another counter-intuitive point is that the more comprehensive a cheat sheet claims to be, the less useful it often becomes. A fifty-page drug reference loses its value because you cannot scan it quickly. The best ones I have used are deliberately sparse. They force you to know where to look and what to ignore. I keep mine to about two pages double-sided, and I update them once per semester. Anything larger becomes a scrolling nightmare on a phone or tablet, which is where most people actually use these materials now.
There are real limitations to relying on any condensed drug reference. The information becomes outdated quickly. New drug approvals, black box warnings, and revised guidelines appear constantly. A cheat sheet printed or saved six months ago may already contain obsolete dosing information. I learned this when a colleague referenced an older version during a case conference and suggested a dose that had been flagged in a recent FDA communication. We caught it before administration, but it was close. Always check the publication date and compare critical entries against current sources. For students, the best use of a cheat sheet is active recall practice, not passive reading. Cover one side and try to recite the interactions or dosing adjustments from memory. Then check. This method takes more time initially but improves long-term retention significantly compared to simply highlighting or re-reading. I saw this pattern repeat with dozens of students over the years, and the ones who used active recall consistently scored higher on pharmacology sections of board exams. If you want alternatives, consider building your own from trusted primary sources. Start with the FDA labeling, cross-check with the latest clinical guidelines, and distill only what you actually need for your practice setting or exam. A custom-made reference tailored to your specific workflow will always outperform a generic download, no matter how polished it looks. The effort of creation is where the real learning happens anyway.
Get the Full Details