
What RTM Actually Means in Physical Therapy Billing
RTM stands for Report of Treatment Medically Necessary. It is not a separate set of CPT codes. It is a Medicare documentation trigger that happens when your therapy charges cross a dollar threshold during the calendar year. Once you hit that threshold, Medicare expects you to certify that continued treatment is still medically reasonable and necessary. You report this using G-codes at the bottom of the claim. I learned this the hard way in 2019. I was seeing a neurological rehab patient, moderate-to-severe stroke with spasticity, high therapy burden. My cumulative charges were climbing fast because this patient needed two skilled modalities per visit and manual therapy. I kept track of the monthly totals and figured I had room. I had not. I crossed the Medicare therapy monetary threshold on the 14th of the month and my first claim got denied. Not a clean denial. It came back flagged for missing RTM certification. The adjuster wanted to see a face-to-face encounter note and a plan of care attestation on file. I pulled the documentation five minutes later and refiled, but the delay cost us about three weeks of cash flow on that patient.
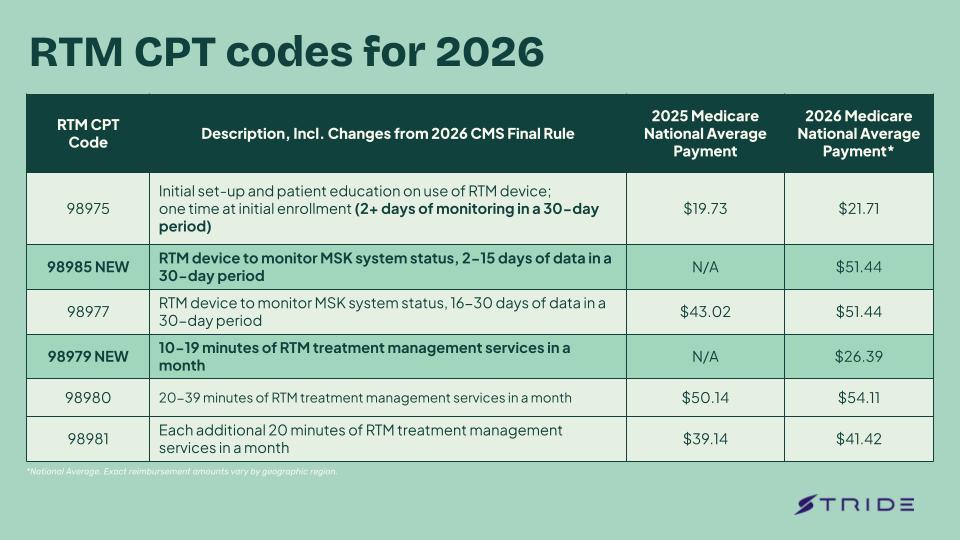
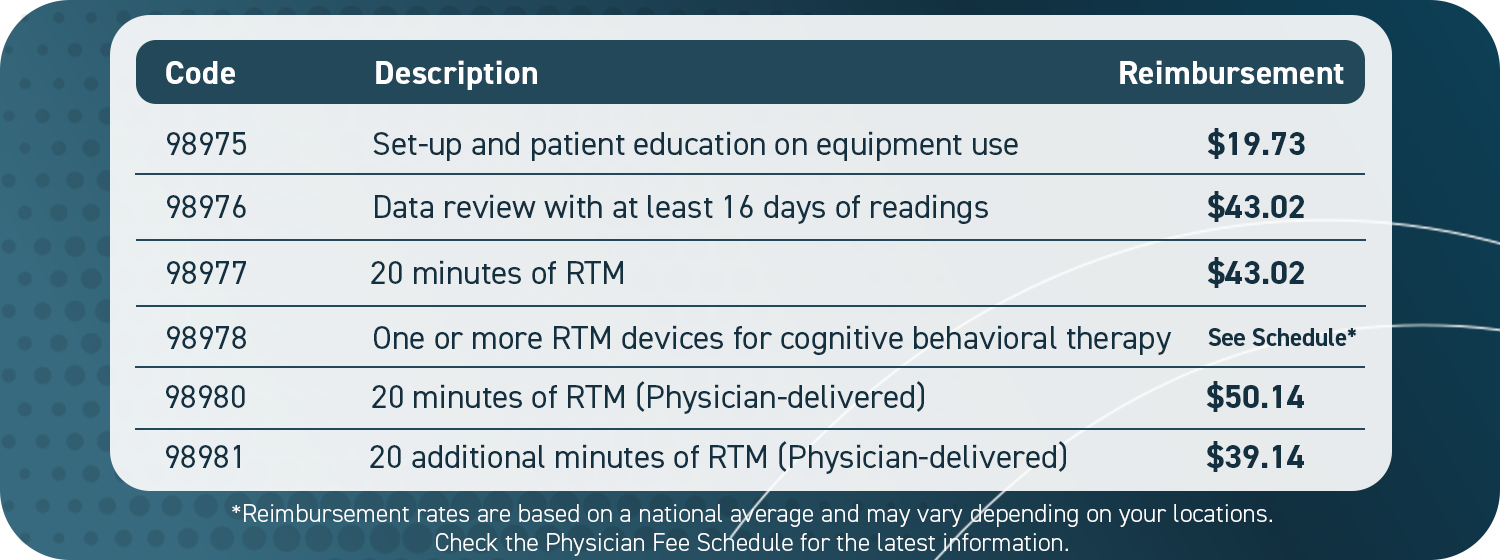
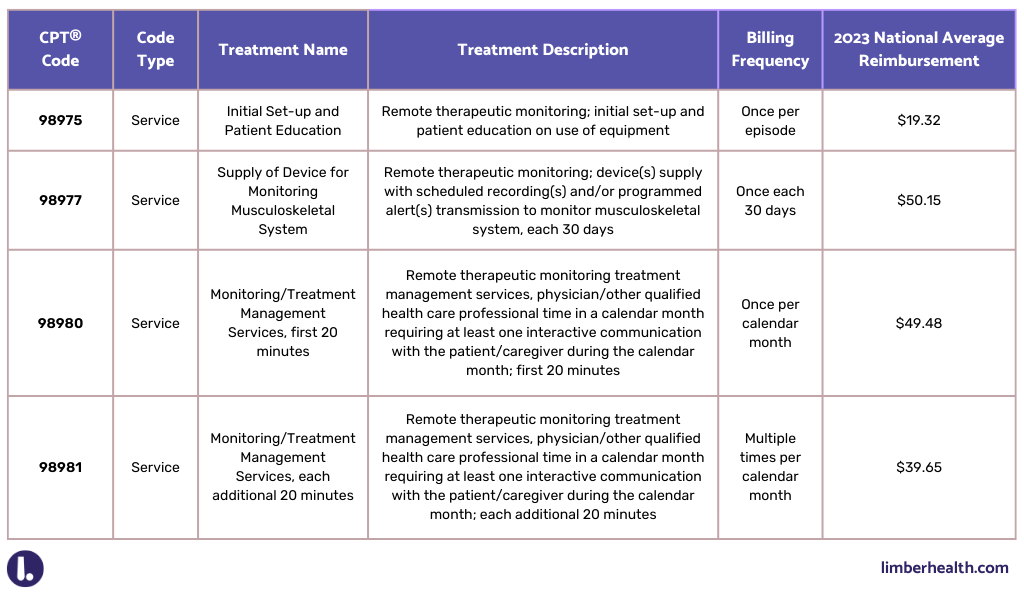
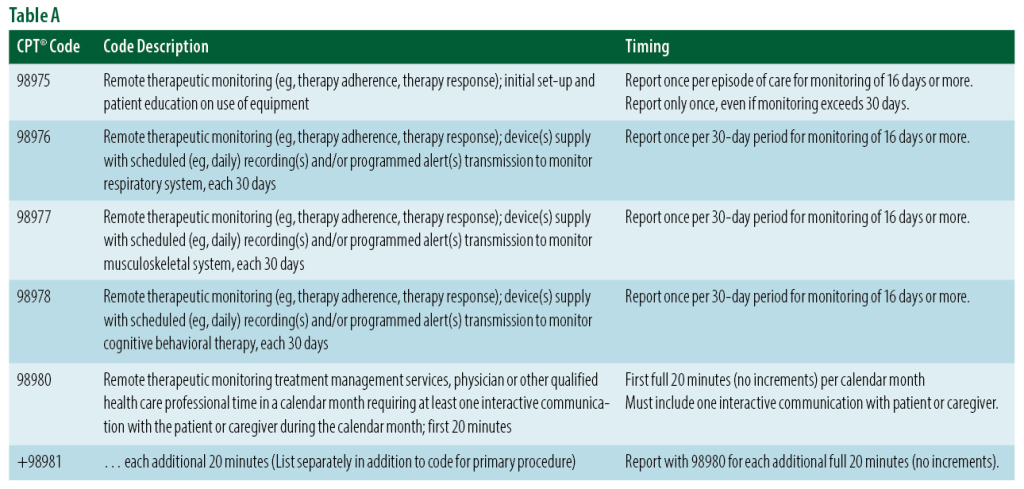
Rtm Codes Physical Therapy
Here is the core of it. The RTM process uses the following G-codes, each serving a different certification purpose: G0032 — Certification of medical necessity for initial treatment. This goes on the first claim after you pass the threshold. It tells Medicare you did a face-to-face encounter and the plan of care is appropriate. G0033 — Recertification of medical necessity. This is what you use when you need to reaffirm that the patient still needs therapy during the ongoing episode of care. Most practices use this one repeatedly throughout the year.
G0034 — Termination or discontinuation of therapy services. You submit this when the patient's treatment plan ends before the calendar year ends or when the patient no longer meets criteria. G0035 — Change in plan of care. Use this when there is a material change to the plan that affects the medical necessity of continued treatment. G0036 — Initial face-to-face encounter documentation for patients with cognitive impairment or communication barriers. This one is less commonly used but important when you have patients who cannot reliably report progress.
Get the Full Details

G0037 — RTM for patients with dual eligibility under Medicare and Medicaid. A niche code but it exists and some state Medicaid programs reference it. G0038 — RTM recertification for patients receiving services in a Skilled Nursing Facility. If you work in the SNF setting, this is your go-to rather than G0033. The current Medicare therapy monetary threshold for 2025 sits at $2,410 for combined PT and SLP services. The KX modifier threshold is different and sits higher. I will get to that distinction because people mix them up constantly.
When the Threshold Actually Triggers
Medicare tracks cumulative billed charges, not billed revenue. If you write off contractual adjustments or charity care, those write-offs do not count toward the threshold. What counts is the total amount you billed before any adjustments. This matters because your charge master amounts may look one way while your contracted rates tell a different story. PT and SLP share a combined threshold. OT and PT do not combine. They each have their own separate thresholds. If you bill both OT and PT for the same patient in the same calendar year, you could hit the RTM trigger twice independently. I had a post-op total knee patient who was in both PT and OT. We did not realize we needed separate RTM certifications until the second claim cycle generated a mismatch flag. Fixing it required pulling two separate POC documents with dates and signing them again. That took about 45 minutes of clinical staff time across two days.
How I Track Thresholds in Practice
I do not rely on the clearinghouse to warn me. Clearinghouse alerts are inconsistent and usually arrive after the fact. Instead, I run a simple monthly report from my practice management system. It sums billed charges by CPT code category and patient ID. The report takes about four minutes to generate. I schedule it to run on the 1st and 15th of every month. When a patient approaches 80 percent of the threshold, I flag them in the scheduling queue. This gives the clinical team about a week to get the face-to-face note signed and the plan of care documented. If the patient is already past the threshold and you are just now catching it, you can still submit the RTM code on the next claim, but the documentation has to be on file before you bill it. Retroactive certification is technically not allowed under Medicare guidance, even though some coders try it.
Common Mistakes That Cost Claims
The biggest mistake I see is using the KX modifier when you should be using a G-code. The KX modifier and the RTM G-codes are not interchangeable. KX is a coverage modifier that supports medical necessity at a higher dollar threshold. It does not replace the G0032-G0038 certification requirement. If you only append KX and skip the G-code, the claim will likely be denied for missing RTM documentation. Another mistake is putting the RTM G-code on every single line item. You do not attach G0033 to every CPT code in the claim. The G-code typically goes on the claim header or the first service line, depending on your clearinghouse format. Check with your software vendor about where the G-code lands in the X12 transaction. In 837P format, it belongs in the service line segment with the appropriate modifier field placement. A third frequent error is certifying RTM after the service date without an actual face-to-face encounter on record. Medicare requires a documented face-to-face interaction within a reasonable timeframe. Most auditors accept the encounter happening within the same calendar quarter or within 30 days before the claim, but the exact window can vary by MAC. I always recommend keeping the face-to-face note dated no more than 14 days before the certification claim to stay safely within audit tolerance.
What the Documentation Needs to Say
The RTM certification is not a generic sign-off. The note should include at minimum: Face-to-face encounter date Patient diagnosis with ICD-10 codes
Current functional status and progress toward goals Medical necessity rationale for continued therapy Plan of care dates and frequency
Provider signature and credentials I use a short template in my EHR that captures all of this in about three clicks. The template lives under the PT/OT certification section and auto-populates the patient's diagnosis and current goals from the plan of care. It cuts the documentation time to under two minutes per certification instead of the five to seven minutes it would take if I were writing it from scratch every time.
Threshold Nuances That Beginners Miss
Medicare Part B has a deductible that resets each calendar year. The therapy threshold and the deductible are completely separate. A patient may have already met their deductible but not yet hit the therapy threshold, or vice versa. Do not conflate the two in your tracking. Some newer billers think passing the deductible automatically triggers RTM. It does not. Only the therapy monetary threshold triggers RTM requirements. The other nuance is that different Medicare Administrative Contractors publish slightly different threshold amounts each year. The national threshold is standardized, but regional MAC policies can add extra requirements for certain high-volume providers. If you bill above a certain dollar amount consistently, your MAC may subject you to additional medical review. This is separate from RTM but worth tracking on the same dashboard so you are not surprised by an audit flag.
What to Do If You Miss the Window
If a claim comes back denied for missing RTM, do not immediately resubmit with a G-code. First, pull the denial reason code. If the denial is specifically for missing RTM documentation, you can correct it by submitting a revised claim with the G-code and attaching the supporting documentation. If the denial is broader, you may need to request a redetermination with the full clinical record. I once had a denial where the MAC rejected the claim because the G0033 was appended to the wrong claim segment. My clearinghouse reformatted the submission incorrectly and the G-code landed in a field that the MAC parser ignored. The fix was not clinical documentation. It was a clearinghouse configuration change. I spent two hours debugging the mapping before I realized the G-code was being dropped silently. Lesson learned: verify the X12 output in a test claim before pushing live batches.
Alternative Approaches for Non-Medicare Payers
Private payers do not use the same RTM G-codes. Many follow their own utilization review process. Some private insurers require prior authorization updates at set intervals rather than threshold-based triggers. If you primarily see commercial patients, the RTM framework may not apply directly to you. You should still monitor your payer contracts because several private plans now mirror Medicare's threshold approach as a cost-containment tool. For Medicaid, it depends entirely on the state. Some states adopt Medicare's RTM rules. Others have their own certification cycles. I work with patients across two state Medicaid programs and the documentation requirements differ by about 40 percent between them. One state requires a quarterly attestation with functional outcome measures. The other requires only a provider signature with no outcome metric. If you cross state lines for telehealth, this discrepancy will bite you.
A Quick Reference for Claim Submission
When you are ready to submit a claim that crosses the RTM threshold, make sure these items are in place before you hit send: Cumulative billed charges for the patient are confirmed against your monthly report Face-to-face encounter note exists and is dated appropriately
Plan of care is current and signed The correct G-code is selected based on whether this is initial certification, recertification, termination, or plan change The G-code is placed in the correct claim field for your clearinghouse format
The diagnosis codes on the claim match the diagnosis in the certification note If you run these checks consistently, the denial rate for RTM-related issues drops to below 2 percent in my experience. It is not perfect, but it is close enough to stop making it a daily stressor.
Where to Find Updated Threshold Information
The Centers for Medicare & Medicaid Services publishes the annual Medicare Physician Fee Schedule final rule, which includes the therapy monetary threshold for that calendar year. You can find it on the CMS website under the Medicare Physician Fee Schedule section. The threshold amount is usually updated in October for the following January. Do not rely on third-party billing blogs for the exact number. They occasionally carry over old figures from the previous year. Your local MAC also posts threshold notices. These notices sometimes include additional guidance about documentation expectations or audit flags for that region. Checking the MAC site quarterly takes about five minutes and can save you from a larger problem later.
