Sex-linked Traits In Practice
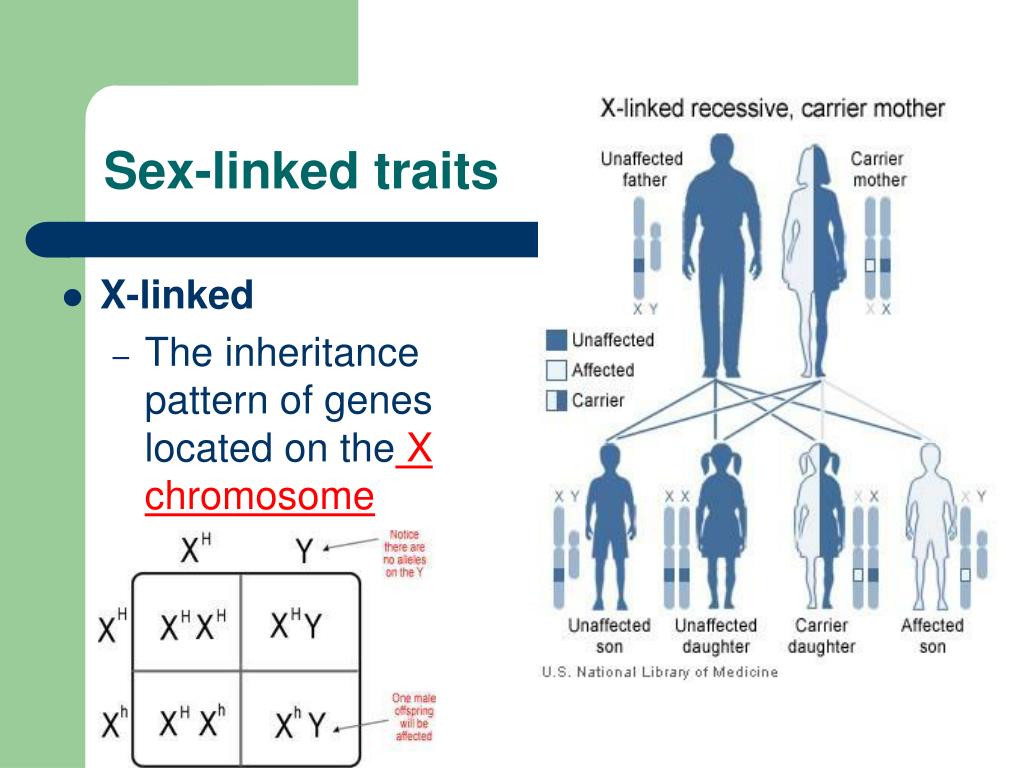
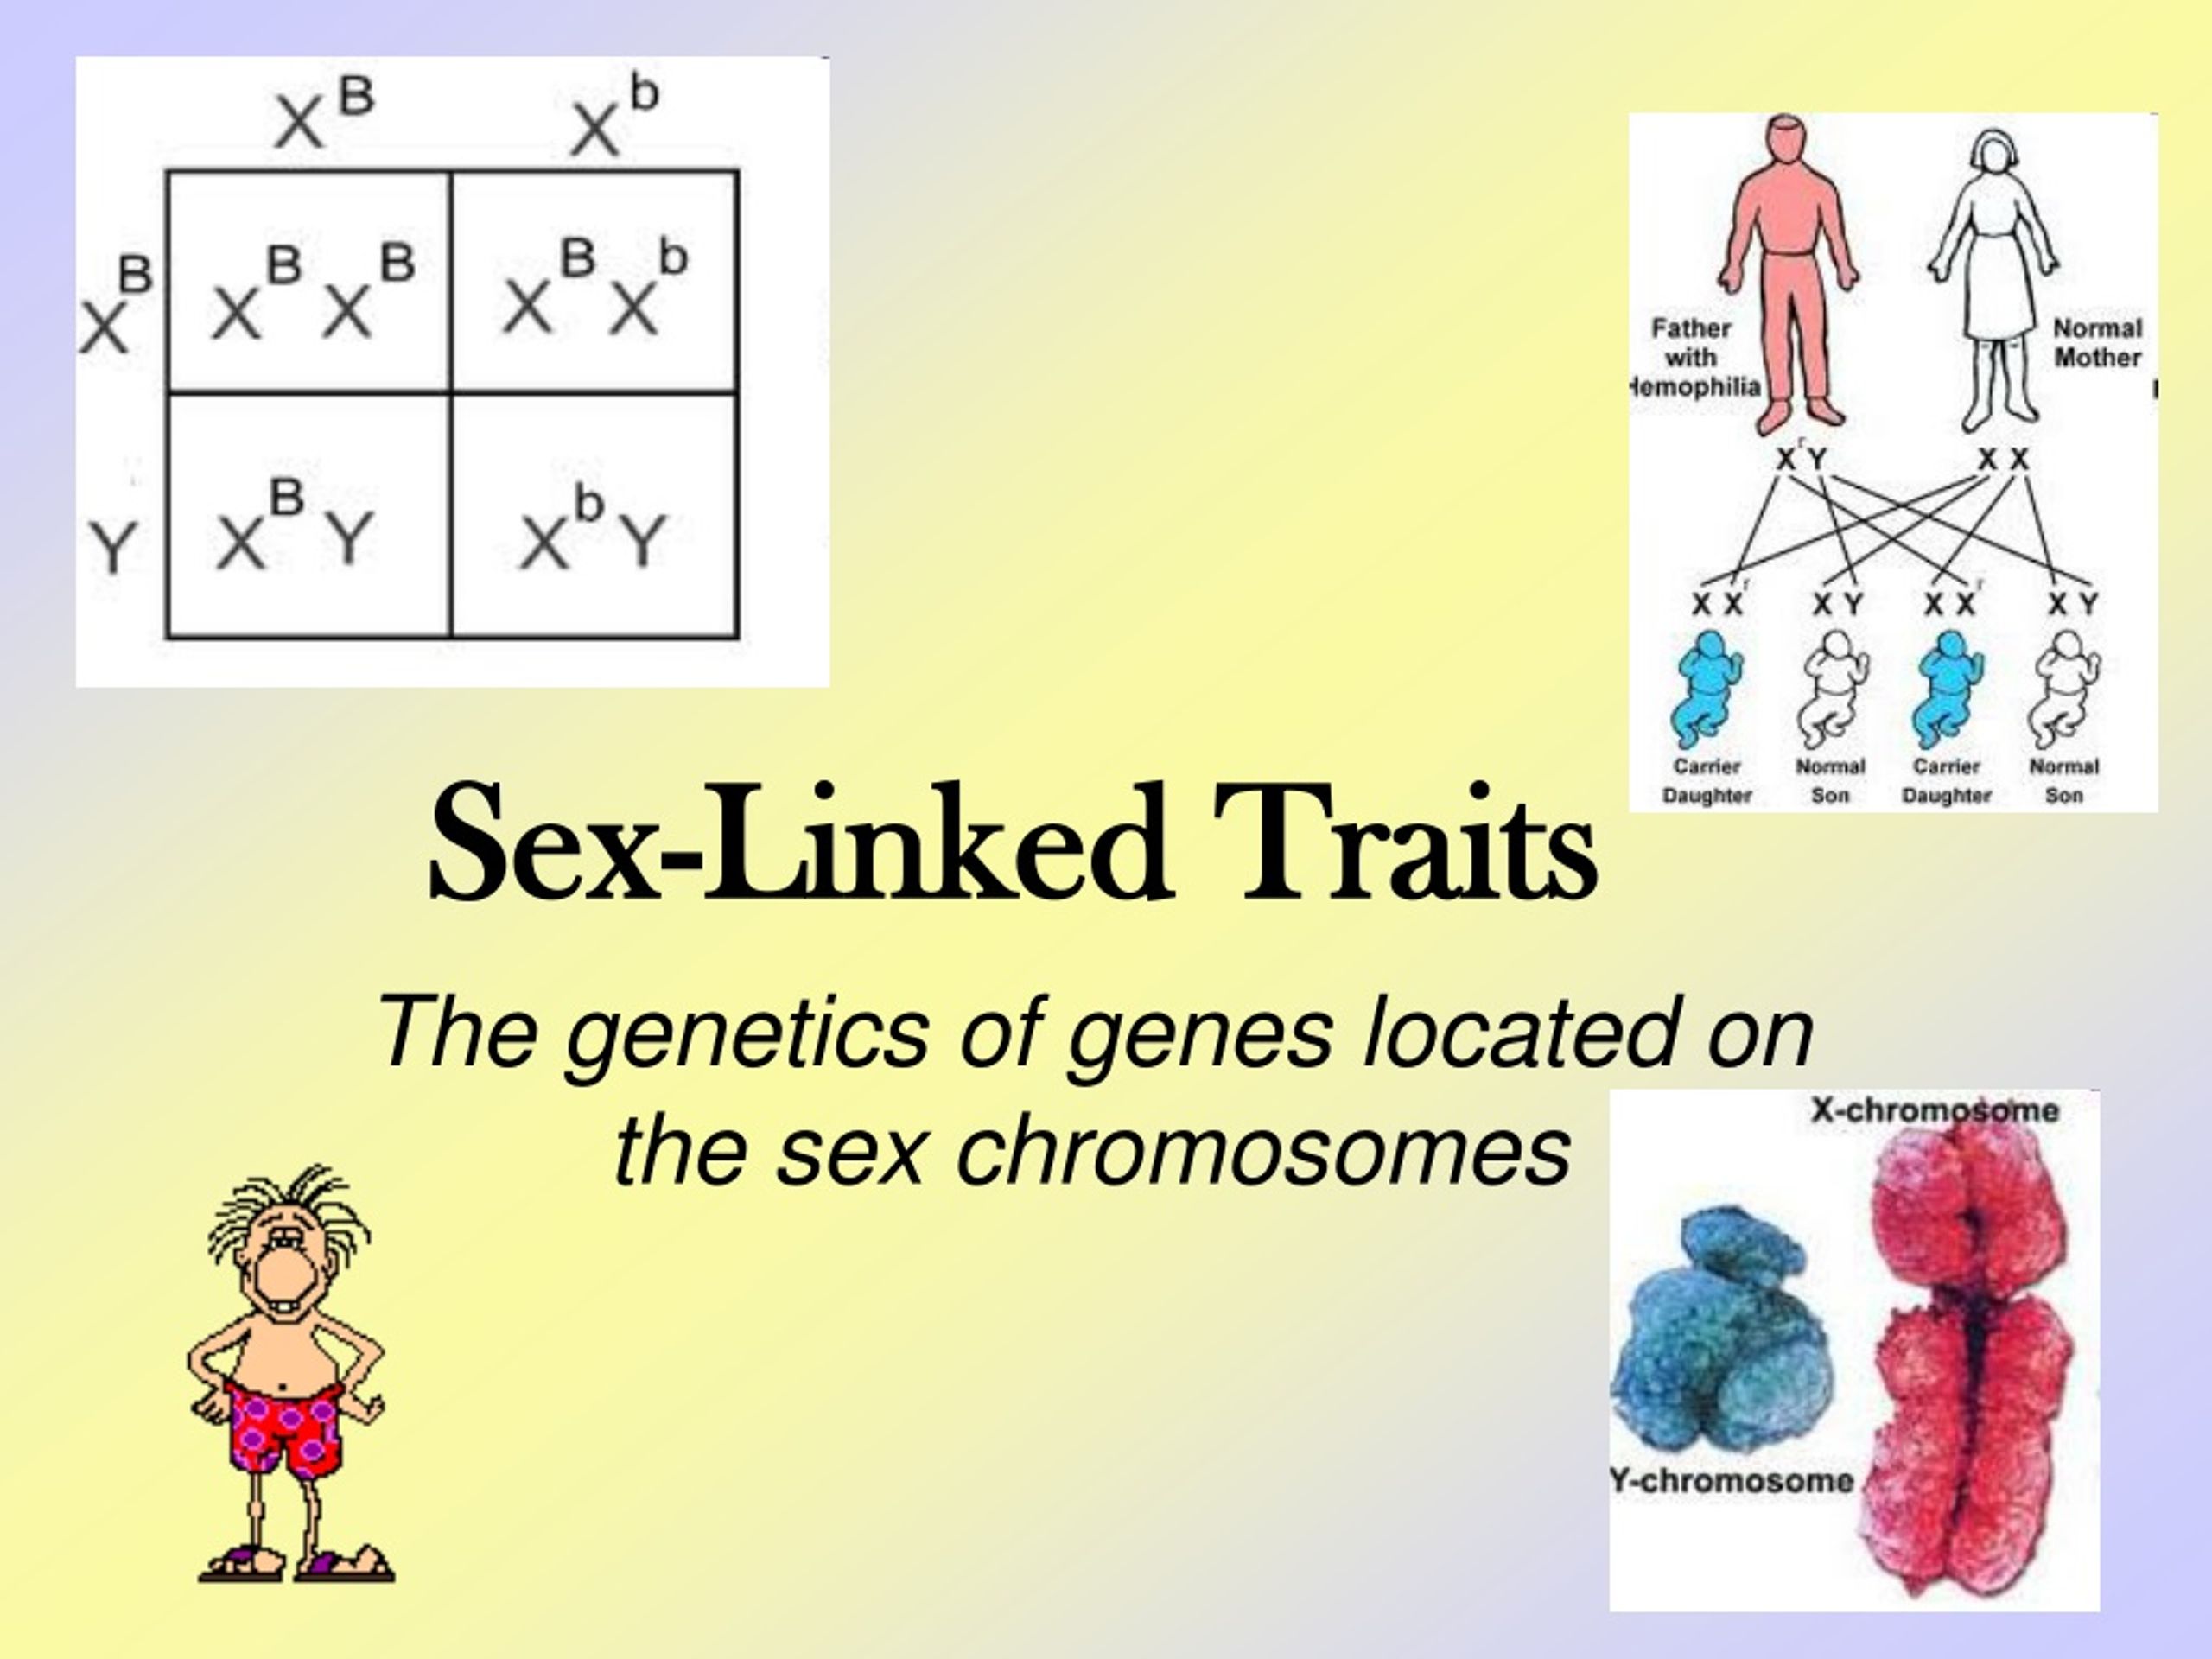
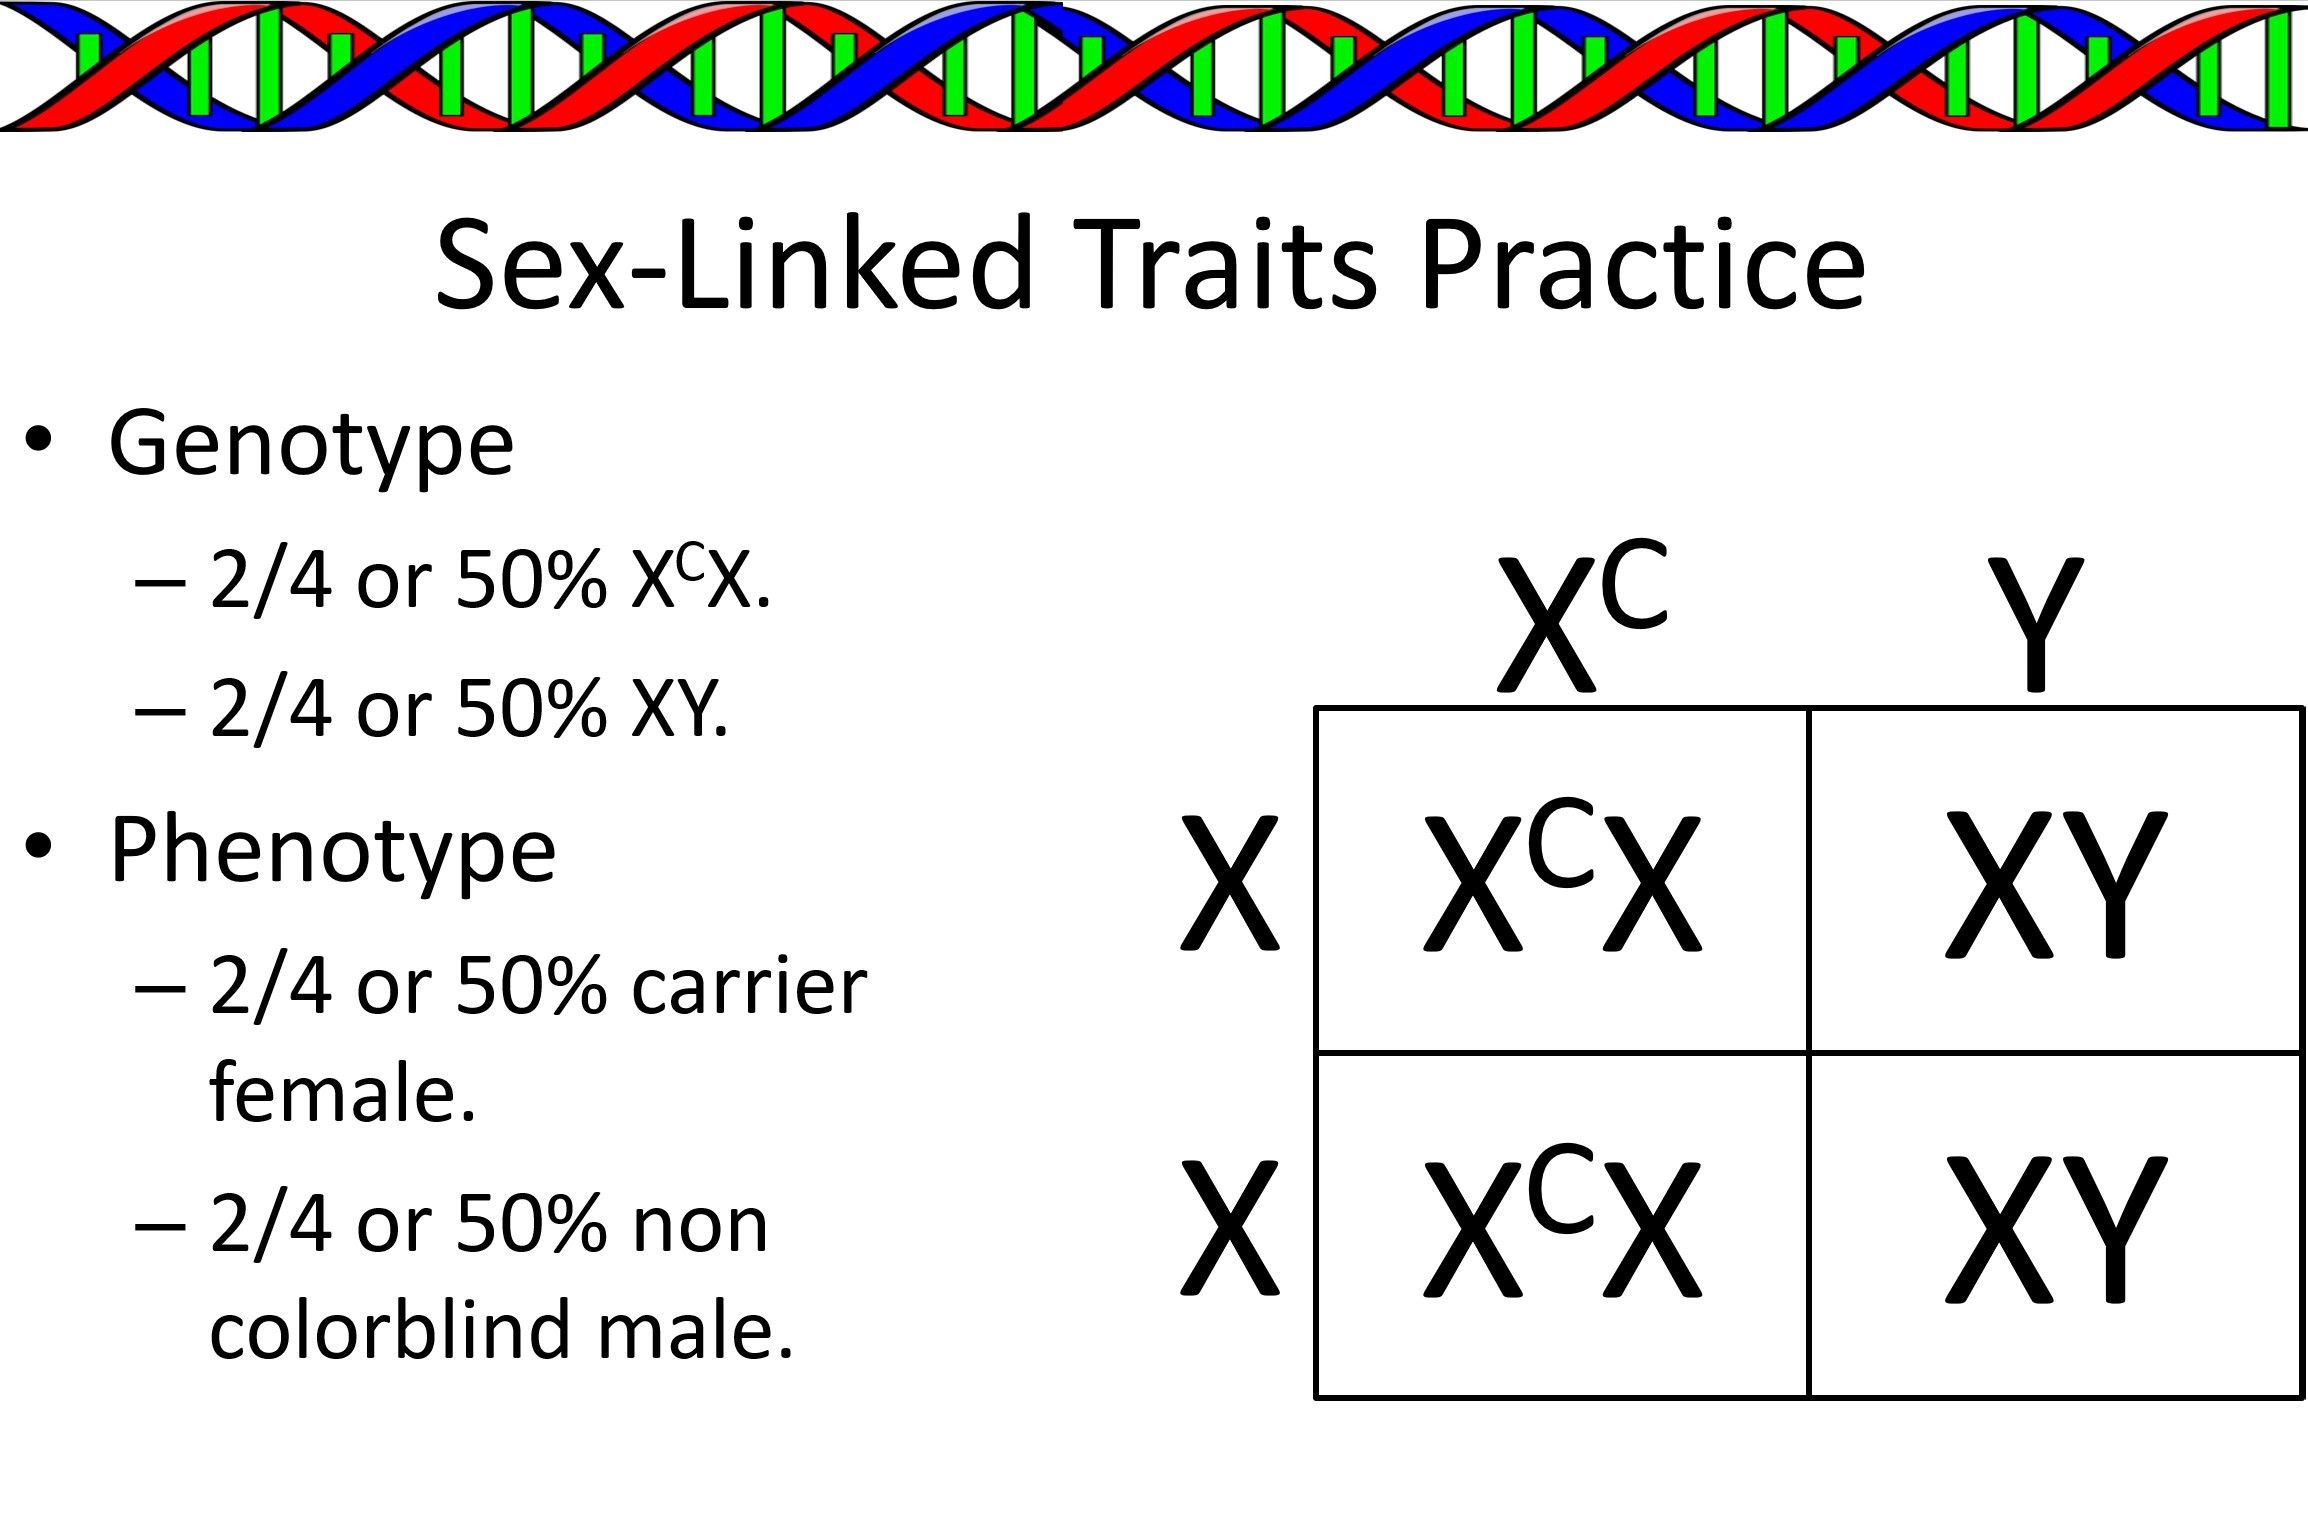
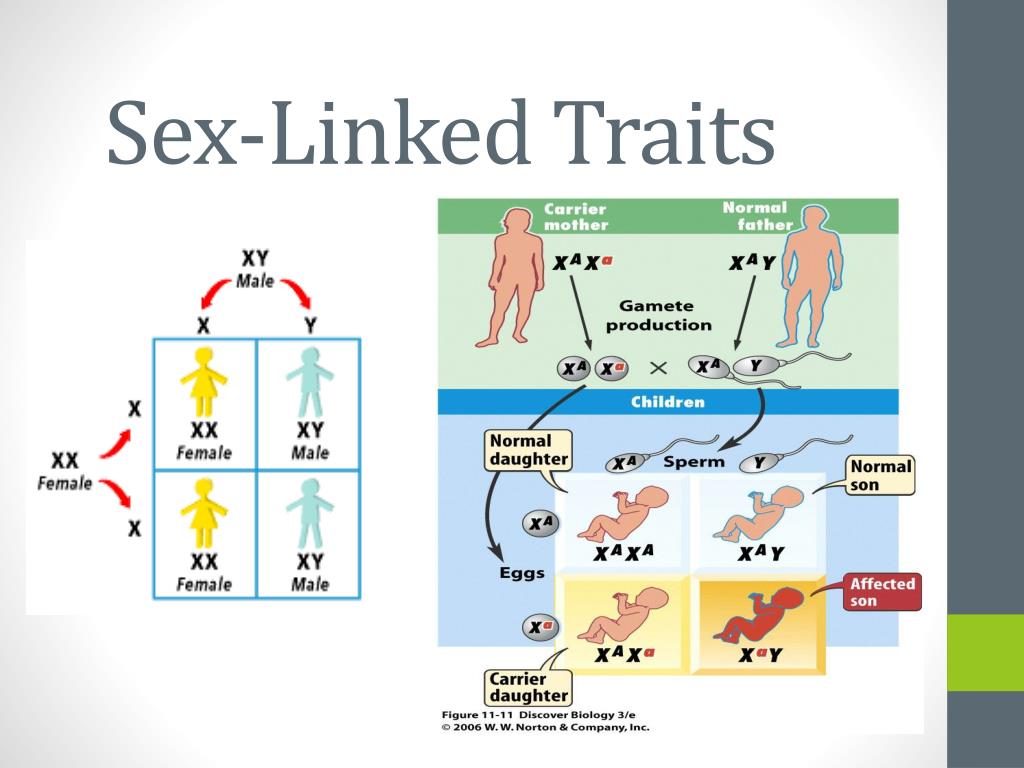
S E X Linked Traits are genetic variations tied to the sex chromosomes, mostly the X chromosome since it carries thousands of genes while the Y chromosome carries roughly seventy. This means inheritance patterns look completely different depending on whether the gene sits on X or Y. Most clinicians and genetic counselors working in this space are really talking about X-linked inheritance when they use the term, because Y-linked conditions are vanishingly rare and mostly involve male fertility or spermatogenesis genes. The X chromosome is large and gene-rich, which is why color blindness, hemophilia A, Duchenne muscular dystrophy, and several immunodeficiency disorders all show up in genetics textbooks under this heading. Understanding the basic mechanism is straightforward, but the patterns get weird fast once you look at real families. For X-linked recessive traits, males express the condition whenever they inherit one copy of the mutant allele because they only have one X chromosome. Females need two copies to express it, which is why these conditions disproportionately affect males in pedigrees. An affected father passes his X chromosome to all of his daughters, making every daughter at least a carrier. He passes his Y chromosome to all of his sons, so none of his sons inherit anything from him on the sex chromosome. A carrier mother passes the affected X to approximately half of her sons, who will be affected, and to approximately half of her daughters, who will be carriers unless the father also carries the allele.
Practical Patterns and S E X Linked Traits Inheritance Analysis
I spent three weeks tracking down a family pedigree for what initially looked like a simple X-linked recessive condition. The father was unaffected, the mother appeared to be a non-carrier based on standard testing, but two of their sons had the condition. Standard X-linked recessive inheritance doesn't explain that pattern unless you account for either a de novo mutation in the mother's germline, skewed X-inactivation in the mother revealing a mosaic pattern, or the possibility that the father's phenotype was misclassified due to incomplete penetrance or mild expression. In that particular case, targeted sequencing of the mother's blood DNA showed she was a confirmed carrier at low mosaicism levels that standard carrier screening had missed. The workaround was to test multiple tissue types, and the mutated allele showed up in buccal cells at a higher frequency than in blood. This is a real problem with standard carrier screening panels, especially for X-linked conditions where low-level somatic or germline mosaicism is common enough to matter clinically. There are nuances that people learning this material usually gloss over. Skewed X-inactivation, also called lyonization, is one of them. Carrier females have one normal X and one mutated X in every cell, but one X gets randomly inactivated early in embryonic development. In most carriers, the inactivation is roughly 50-50, so they remain asymptomatic. But if X-inactivation is heavily skewed toward the normal X being silenced, a carrier female can express the condition to varying degrees. I've seen females with Duchenne muscular dystrophy carrier status who presented with significant weakness because their skewing ratio was around 90-10 in favor of the mutant X. That's not theoretical. It happens often enough that any proper genetic counseling session for X-linked conditions needs to address this possibility with female carriers and their offspring. Another thing that trips people up is the difference between X-linked recessive and X-linked dominant inheritance. X-linked dominant conditions are far less common but follow a different pattern entirely. An affected father passes the condition to all of his daughters and none of his sons, which looks the same as X-linked recessive for paternal transmission. But an affected mother passes the condition to half of her sons and half of her daughters, because she has a fifty percent chance of passing either her affected or her normal X to each child. Conditions like Rett syndrome and X-linked hypophosphatemic rickets are X-linked dominant, and the mortality pattern is often skewed because affected males with severe X-linked dominant conditions frequently don't survive gestation. That selective loss of affected males is actually a useful diagnostic clue when you're reading a pedigree and wondering whether a condition is X-linked dominant versus autosomal dominant with sex-limited expression.
The practical side of working with these traits involves understanding what tests actually detect and what they miss. Standard chromosomal microarray won't catch most point mutations responsible for X-linked disorders. You need targeted gene sequencing, and even then, large deletion-duplication analysis should be run alongside because some X-linked conditions like Duchenne muscular dystrophy are caused by multi-exon deletions that sequencing alone won't identify. If you're doing carrier testing for females, whole gene sequencing plus deletion-duplication analysis is the minimum. And if that comes back negative in a family with a clear X-linked inheritance pattern, you should consider RNA analysis to catch splicing variants that DNA sequencing alone might classify as variants of uncertain significance. There are limitations worth being honest about. Predicting expression in female carriers is essentially guesswork without X-inactivation studies, and those studies aren't always available or reliable. The ratio can vary between tissues, so a blood sample might not reflect the pattern in muscle or brain. Newborn screening catches some X-linked conditions like X-linked adrenoleukodystrophy through elevated very long chain fatty acids, but many X-linked disorders have no newborn screening component and present only after symptoms appear. By that point, the window for certain interventions may have closed. Family planning options exist, including preimplantation genetic testing for monogenic disorders with IVF, but that's a lengthy and expensive process that not all families can access. For families already dealing with an X-linked condition, cascade testing of at-risk relatives is standard practice, and it usually takes multiple phone calls and awkward conversations to get extended family members to agree to testing. The bottom line is that sex-linked traits are straightforward in textbook form and much messier in real clinical practice. The inheritance patterns hold up when families conform to the expected ratios, but mosaicism, skewed inactivation, de novo mutations, and incomplete penetrance all show up regularly enough that rigid textbook models break down. The most useful approach is to treat any pedigree with an apparent X-linked pattern as a hypothesis to be tested with molecular data rather than a conclusion you can draw from family history alone. Testing strategy matters more than pedigree analysis in many cases, and knowing which test to order and when to order it is what separates competent clinical genetics practice from guessing.
Get the Full Details